Why Most Care Technician Training Programs Fall Apart Before Graduation
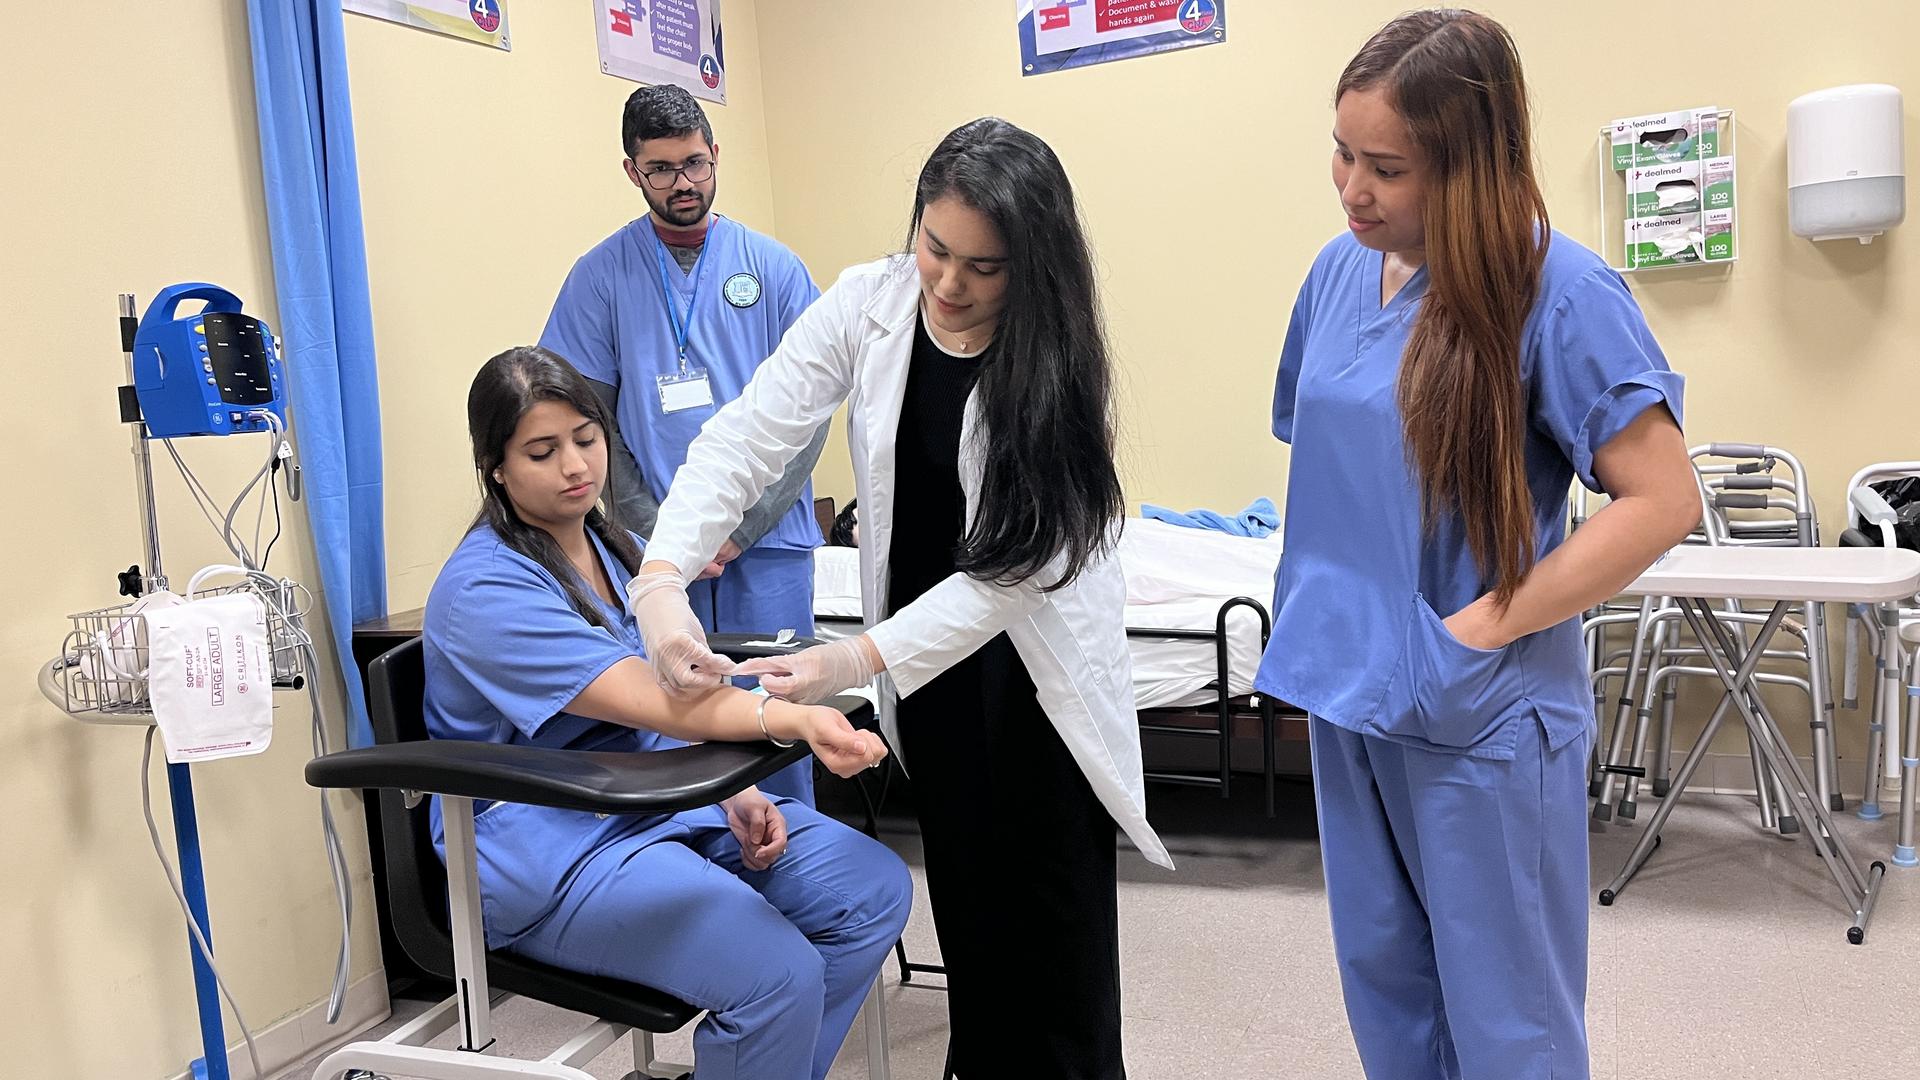
The first thing you need to understand is that most care technician training isn't structured the way people think it should be. You'll watch a module, pass a quiz, and call it done. Meanwhile, the actual competency gap between what the curriculum covers and what happens when you're alone in a patient's home with a fallen resident and no supervisor is staggering. I've watched technicians go through twelve weeks of program-only instruction and still not know how to properly document a skin integrity assessment on a scale that matters for regulatory compliance. Standard programs typically cover vital signs, basic medication administration under supervision, infection control protocols, mobility assistance, and documentation basics. They're designed to meet minimum state and federal requirements, which means they cover the checkboxes but often skip the nuanced decision-making you need in real scenarios. A typical 120-hour program might allocate eight hours to documentation and another eight to communication skills. In practice, I've seen technicians spend more time figuring out how to fill out an electronic health record than actually learning clinical procedures because the EHR system training was condensed into a single afternoon session. The counter-intuitive part is that the students who struggle most aren't the ones with weak academic backgrounds. It's the ones who had prior healthcare exposure through family members or part-time hospital jobs. They develop overconfidence quickly because basic tasks feel familiar, and instructors stop challenging them earlier than they should. I've had to intervene multiple times with students who could draw blood on the first try but couldn't explain the clinical reasoning behind choosing a butterfly needle versus a standard vacutainer for a dehydrated patient with poor veins.
Building a Training Framework That Actually Works
Start by mapping out the clinical competencies your program needs to cover and then cross-reference them against your state's specific certification requirements. Florida requires different clinical hour distributions than Texas, and California has additional documentation competencies that other states don't emphasize. Check your state board of nursing or equivalent certifying body website directly rather than relying on third-party summaries because those get outdated fast. The Florida Board of Nursing, for example, updated their direct care worker training requirements in 2023 to include additional fall prevention modules that older curriculum guides don't reflect. Structure your hands-on simulation sessions around scenarios that combine three or more competencies at once. Instead of having students practice vital signs in isolation and then practice medication administration separately, create a scenario where a patient presents with elevated blood pressure and respiratory distress and the technician needs to recognize both issues, document findings correctly, and communicate the change in condition to the supervising nurse within a specified timeframe. This mirrors the actual workflow instead of treating each skill as a disconnected module. Documentation training deserves at least fifteen percent of total program hours, not the five to eight percent most programs allocate. I learned this the hard way after my first cohort had a 40% failure rate on charting accuracy during their clinical rotations. We traced it back to realizing that students could verbally describe a wound description perfectly but would miss critical elements when typing it into an EHR because they weren't practiced in the specific fields and character limits of clinical documentation systems. We rebuilt the documentation module around actual EHR practice with pre-charted examples and deliberate error identification exercises where students had to find and correct mistakes in sample charts. That single change improved clinical charting accuracy from 60% to 89% on final evaluations.
A Specific Problem That Almost Cost Us a Program Accreditation
About three years ago, our state auditors flagged that our technique for training sterile dressing changes was insufficient. We had students practicing on arm models with simulated wounds, which covered the mechanical steps correctly, but the auditors pointed out that we weren't training them to recognize when a wound bed didn't match the expected appearance for their assigned patient population. A pressure injury in Stage II looks different on an 85-year-old with thin, atrophic skin than it does on a middle-aged diabetic patient, and our curriculum treated them the same. The workaround was immediate but expensive. We sourced cadaver specimens from our local university's medical donor program for advanced wound assessment practice, which ran about $400 per unit and required a separate storage and handling protocol. We also started requiring each student to complete at least ten supervised wound assessments on actual residents during their clinical rotations before they were cleared for independent dressing changes, rather than the six we had previously required. Pass rates on the practical skills exam went up by twenty-two percentage points the following year, and we hadn't received another audit finding related to wound care documentation in the subsequent review cycle.
Get the Full Details

The Hidden Bottleneck: Instructor-to-Student Ratios During Clinicals
This is where most programs quietly compromise. State regulations might allow a maximum ratio of one instructor per twelve students during clinical rotations, but that ratio only works if every student is performing hands-on tasks simultaneously. When students are observing rather than practicing, the effective ratio becomes one per twenty or more, and learning retention drops significantly. I recommend capping your clinical groups at eight students per instructor regardless of what the minimum regulation allows. The additional instructor cost usually pays for itself within the first semester through reduced remediation hours and higher certification exam pass rates. Consider the practical timeline for completing a full program as well. A compressed eight-week schedule efficient until you realize that students are absorbing roughly sixteen clinical hours per week in addition to classroom instruction. By week five, fatigue-related errors in documentation and procedural steps increase measurably. Spreading the same content across fourteen to sixteen weeks with built-in skill reinforcement weeks produces technically stronger graduates, even though it takes longer to complete.
How to Evaluate Whether a Training Program Is Legitimate
Check the program's certification exam first-pass rates and request them in writing. Any accredited program should track this data and share it upon request. If they deflect or can't provide numbers from the past two exam cycles, that's a signal. Also verify whether the program's clinical rotation sites are current contracts or historical affiliations. I've encountered programs that listed major hospital systems as clinical partners even though those agreements had expired the previous year, leaving students scrambling to find placement sites mid-semester. Ask specifically about the teaching methodology for handling agitated or combative residents during care routines. Programs that can't articulate a clear de-escalation and safety protocol for behavioral health scenarios are skipping one of the most critical components of direct care work. Most residents in long-term care settings have some degree of cognitive impairment, and technicians who haven't been trained in recognition and response strategies will either escalate situations through improper handling or avoid necessary care procedures altogether out of fear.
What to Do If Your Current Training Isn't Covering the Basics
If you're already working and realize your training left gaps, start with the areas that matter most for patient safety rather than trying to fill everything at once. Documentation accuracy and proper body mechanics for patient transfers should be your immediate priorities because errors in those areas create the highest risk for both patient injury and regulatory violations. Request additional shadowing shifts with experienced technicians who consistently pass internal competency reviews, and ask them specifically to observe and correct your technique rather than just letting you watch them work. There are supplemental resources available from organizations like the National Association for Health Skills and the Home Care Association of America that offer free or low-cost module supplements covering topics many programs gloss over. Their infection control and patient rights modules are particularly useful as add-ons to whatever foundation your initial training provided. The materials are designed for self-paced completion and take roughly three to five hours each to work through thoroughly.