Getting to Grips with Therapist Templates
I spent the better part of last Tuesday afternoon trying to format a batch of discharge summaries for my caseload. You know the drill — insurance auditors want one thing, your EHR system wants another, and somewhere in between there's a PDF template from 2019 that still circulates through email chains like a haunted object. That's when I actually sat down and stopped fighting with whatever broken form our practice was using. Casamba Sample Documentation For Occupational Therapy isn't a product I can point you at on Amazon. It's more of a reference standard — a collection of structured documentation samples that OTs across the country have shared, adapted, and occasionally argued about in forums and professional groups. The idea is straightforward: show rather than tell. Instead of reading five pages of theory about how to document a pediatric evaluation, you look at a completed example and reverse-engineer it.
Casamba Sample Documentation For Occupational Therapy
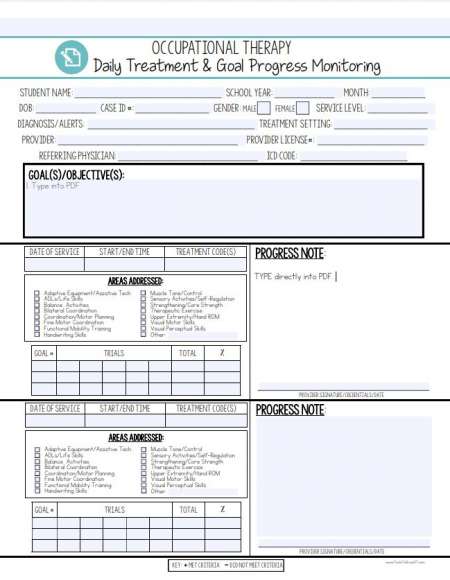
Here's what that actually looks like in practice. A sample set will typically include sections covering initial evaluation notes, daily progress reports, goal reassessments, and discharge summaries. Each section maps to the AOTA standards for performance-based documentation. The trick is that the samples aren't plug-and-play templates. They're illustrations of what compliant, defensible, clinically useful documentation looks like when someone has actually sat down and written it properly. I found this out the hard way. Back in early 2024, I tried to adapt a published OT documentation sample for a pediatric feeding disorder case. The sample assumed a standard fine motor evaluation framework. My patient was a 3-year-old with a complex oral-motor presentation. The sample had almost nothing on sensory oral integration, which was the core of the impairment. I ended up having to supplement it heavily with materials from the Sensory Integration and Praxis Tests (SIPT) documentation guidelines. Lesson learned: use the sample as a structural skeleton, not a content solution. The samples tend to follow a SOAP or DAP format depending on the source. SOAP is more common in medical settings where billing compliance matters. DAP shows up more in school-based and community OT environments. Neither is inherently better, but mixing them mid-chart is a fast track to audit flags. Pick one format per patient and stick with it across the entire episode of care.
Why Documentation Samples Matter More Than You Think
There's a gap between what OT school teaches you about documentation and what actually happens in a busy clinical schedule. School gives you the framework — subjective data, objective findings, assessment analysis, plan formulation. What it doesn't cover is the granular detail of how to write a goal that will actually survive a Medicaid audit three years later. Samples fill that gap. A well-constructed OT sample shows you the level of specificity required. Consider this example. A vague goal might read: "Patient will improve fine motor skills." A sample-driven goal reads: "Patient will sustain bilateral hand coordination for 12 minutes during self-care tasks (buttoning, utensil use) with minimal verbal cues, as demonstrated by a 40 percent improvement on the BOT-2 Manual Dexterity subtest over six weeks." One gets rejected by a payer. The other holds up under review. The downside of relying on samples is that they can create a false sense of completeness. You see a thorough-looking example and assume your documentation is adequate because it mirrors the structure. But documentation adequacy depends on clinical accuracy, not structural mimicry. A perfectly formatted note about a patient who didn't actually receive the documented intervention is worse than useless — it's a liability. I've seen colleagues get tripped up on this exact point during chart reviews.
Get the Full Details

Another limitation: samples often reflect ideal conditions. A sample evaluation might take 90 minutes because the therapist had a quiet room, full cooperation from the patient, and no interruptions. Your reality might involve a noisy clinic, a toddler who won't stay seated, and a parent asking questions every four minutes. The sample structure still applies, but you need to be honest in the objective section about environmental factors and patient responsiveness. Don't pretend the session went smoother than it did just to match a template. Auditors notice discrepancies between the note and the billed units.
How to Use These Samples Effectively
The most practical approach is to keep a small library of samples organized by patient population and setting. I maintain mine across three categories: pediatric motor, adult neurorehab, and geriatric fall prevention. Within each category, I save samples for initial evaluations, re-evaluations, progress notes, and discharges. That's roughly a dozen reference documents. It took me about two weeks to pull them together from various professional networks and conference handouts, but it's saved me hours since then. When you're drafting a note, open the relevant sample and compare structure, not content. Your patient's diagnosis, functional limitations, and treatment approach are unique. But the flow of information should be similar. Subjective report comes first. Then objective measures with specific test names and scores. Then your clinical reasoning that connects the two. Then a plan that is measurable and time-bound. One counter-intuitive thing I discovered: the assessment section is where most OT notes fail audits, not the objective section. Everyone knows to include test scores. Fewer people write a clear rationale for why a particular intervention was chosen and why it continues to be medically necessary. A sample will often show this, but you have to actually read the sample closely instead of skimming past it. I used to skip the assessment portions of samples when looking for formatting cues. That changed after my first audit flag — a reviewer wrote "insufficient medical necessity rationale" on three separate notes. I went back, studied how the samples in my library handled that section, and rewrote my approach. Medical necessity explanations in my notes now average about two paragraphs per session, and I haven't seen a flag since.
Another practical tip: don't copy sample language verbatim into your own notes. Reviewers can spot boilerplate text, and it raises questions about whether you actually assessed the patient or just filled in a form. Use the samples as models for structure and depth, but write in your own clinical voice. If a sample uses the phrase "patient demonstrates decreased proprioceptive input processing affecting bilateral coordination," and your patient actually presents with visual-spatial deficits impacting dressing, don't borrow that sentence. Write what you observed.

Where to Find Reliable Samples
There's no single official repository for Casamba Sample Documentation For Occupational Therapy because it's not a formally designated product. What exists are scattered collections — conference presentations, professional organization resources, shared drives among clinic networks, and discussion threads on OT forums. The AOTA website has some sample forms in their member resource section, though they lean toward administrative templates rather than clinical note examples. The most reliable samples tend to come from peer-reviewed journals that publish case studies with full documentation appendices. Journals like the American Journal of Occupational Therapy and the Occupational Therapy International sometimes include supplementary materials. Professional LinkedIn groups focused on OT documentation also circulate vetted samples, though you should verify any sample against current state and payer requirements before adopting it. I also recommend checking with your state's OT regulatory board. Some publish guidance documents that include documentation expectations, and occasionally they reference or include sample formats. This is especially useful for school-based OTs, since state education agencies sometimes have their own documentation standards that overlap with but diverge from clinical ones.
Common Pitfalls to Avoid
The biggest mistake I see OTs make with documentation samples is treating them as checklists rather than learning tools. A sample shows you the end result, not the clinical thinking that produced it. If you only copy the format without understanding why each section exists and what it's supposed to communicate, your notes will look correct on the surface but may still miss critical elements. Take time to understand the purpose behind each section. Subjective isn't just a place to dump patient quotes. It's context for why treatment is being sought. Objective isn't just a score sheet. It's the evidence base for your clinical conclusions. Assessment is the bridge. Plan is the roadmap. A second pitfall is documentation lag. It's easy to think, "I'll catch up on notes this weekend," and then the weekend comes and goes. Samples are most useful when you're drafting notes in real time, not when you're trying to retroactively reconstruct a session from memory. The gap between when you provide care and when you document it directly affects the accuracy of your objective data. I keep my most relevant samples open on a second monitor while I'm seeing patients. When I finish a session, I draft the note immediately while the specifics are fresh. This habit alone cut my average note completion time from about 45 minutes per patient to roughly 15 minutes. There's also the problem of outdated samples. Documentation standards shift. Payer requirements change. New assessment tools get adopted and old ones get retired. A sample from 2018 might reference the Beery VMI in a way that doesn't align with current best practices, or it might use ICD-10 codes that have since been updated. Always check the date on any sample you're using and verify that the assessment tools and coding references are current. I once used a sample that referenced the OTF — the Occupational Therapy Function screen — which had been discontinued years prior. Caught it before submission, but it was a reminder to always sanity-check the references in any sample material.
If you're looking for a starting point, the AOTA's Practice Guidelines for Occupational Therapy provide a framework that most samples align with. Beyond that, reaching out to experienced colleagues in your region and asking what documentation resources they rely on tends to yield more practical results than searching online. The term Casamba Sample Documentation For Occupational Therapy comes up occasionally in these conversations, usually as a reference to shared drive collections that circulate within local OT networks. There's no centralized download link because the materials exist in distributed form across professional communities. The bottom line is that good documentation documentation is something you build over time, not something you find ready-made. Samples give you direction. They show you what competent, compliant, clinically meaningful notes look like when written by experienced practitioners. But they can't replace the work of developing your own documentation habits, understanding your specific payer requirements, and maintaining the clinical reasoning that makes your notes defensible and useful. Start with a few solid samples, adapt them to your context, refine your approach as you encounter real-world feedback, and keep your references current. The process isn't glamorous, but it's the foundation that keeps your practice intact when questions arise.