
How To Build A Complete Case History Of Asthma Patient
Asthma case history isn't just a form you fill out and forget. It's the foundation of how you'll manage a patient's condition long-term. I've spent over a decade taking asthma histories in both primary care and pulmonary clinics, and I can tell you that most doctors rush through this process in under five minutes. That's usually not enough. The case history of asthma patient documents everything from symptom patterns to environmental triggers, medication responses, and past exacerbations. Without it, you're essentially guessing at treatment adjustments instead of making informed decisions based on concrete data.
What Actually Goes Into Case History Of Asthma Patient Documentation
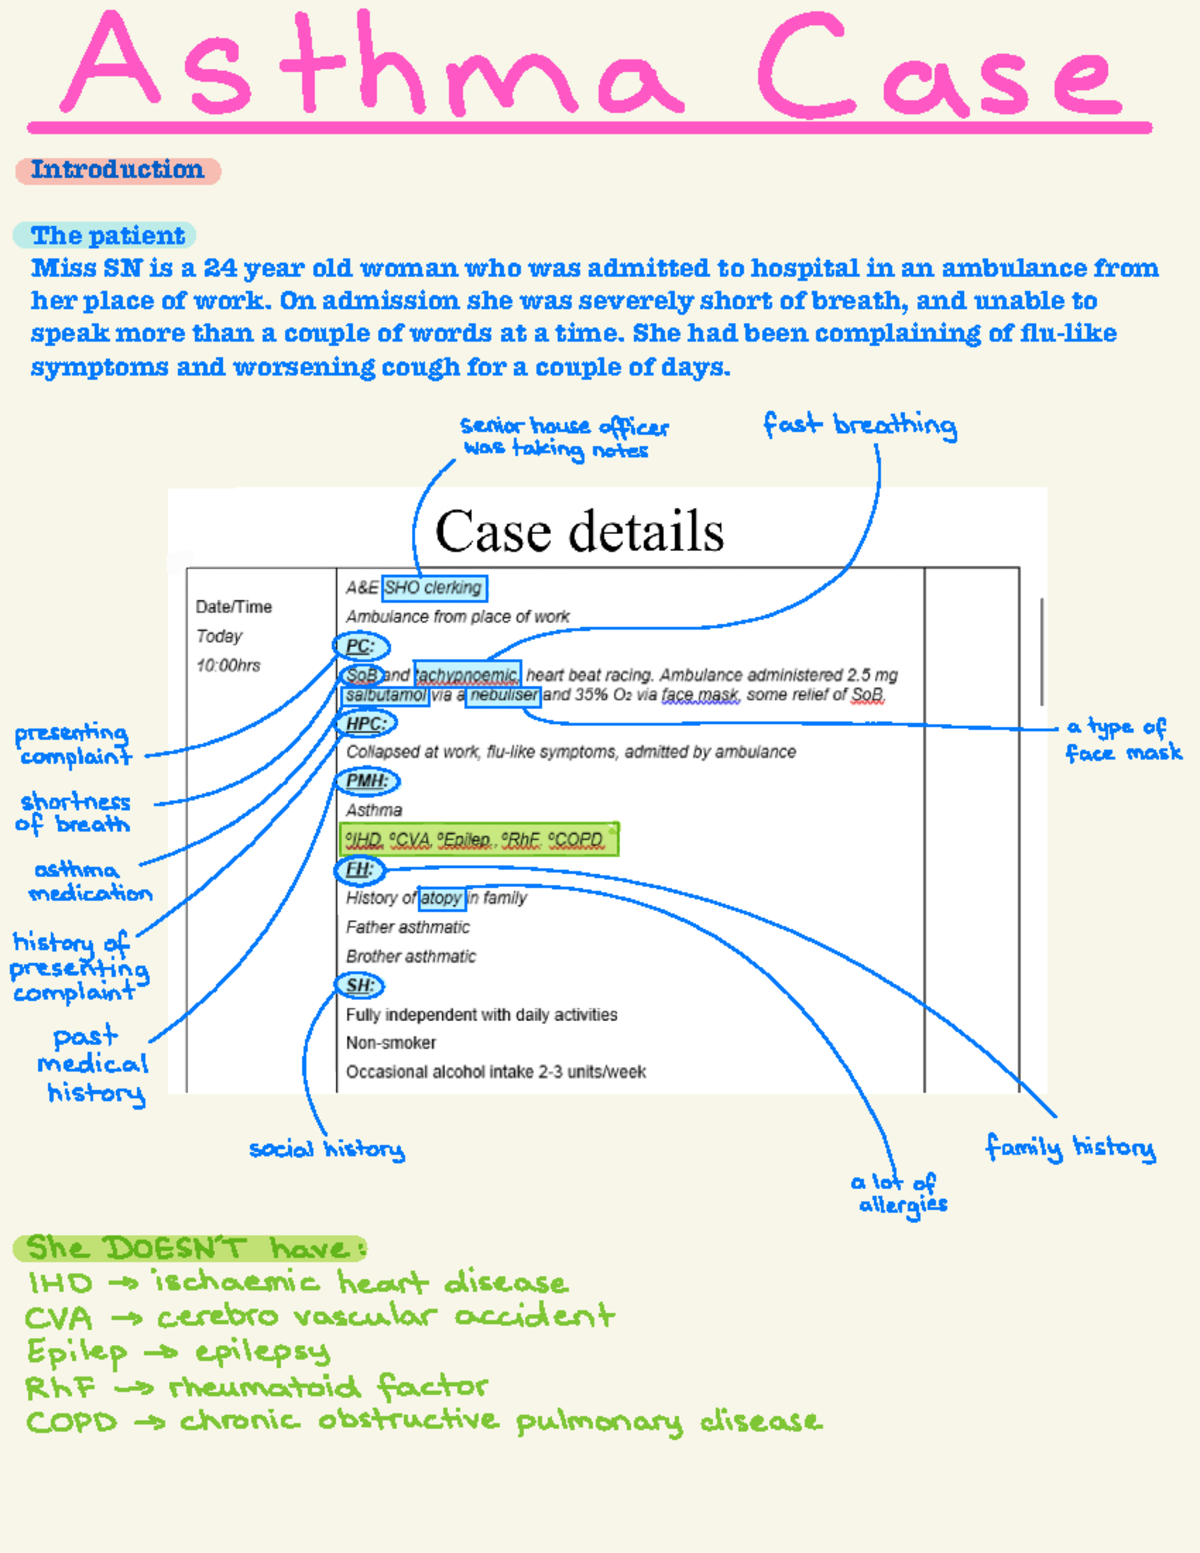
When I pull up an asthma case history, I look for specific patterns that standard textbooks don't emphasize. Yes, you need age of onset and family history. But the real value comes from documenting trigger specificity, symptom timing, and what makes symptoms better or worse beyond just albuterol use. The core components include presenting complaint details with onset timing, current medications with adherence rates, past hospitalizations or ICU stays for asthma exacerbations, comorbid conditions like allergic rhinitis or GERD that complicate management, and objective lung function data when available. I once had a patient whose asthma appeared well-controlled on paper. Standard history taking would have missed the real issue. He reported using his rescue inhaler twice weekly, which technically qualifies as "controlled" by some guidelines. But when I dug deeper into his case history of asthma patient documentation, I found he was only using it after work, not during weekend activities where his symptoms actually worsened. This triggered further investigation that revealed occupational exposure to a specific chemical at his workplace. We adjusted his treatment plan and recommended workplace modifications that completely changed his outcomes.
Another critical element most practitioners skip is the detailed environmental trigger assessment. I ask patients specifically about home humidity levels, presence of mold or dust mites, pet exposure, recent moves or renovations, and occupation-related exposures. This isn't just academic. In one case, identifying carpet cleaning chemicals as the trigger helped a patient avoid annual ER visits that were previously routine.
Get the Full Details

The Practical Method For Taking An Asthma Case History
Here's how I structure this in actual clinical practice, not the textbook ideal. Start with the chief complaint and history of present illness. Document when symptoms started, whether they're seasonal or persistent, what time of day they occur, and what the patient has already tried. This section should flow naturally like a conversation rather than reading from a checklist. Move to past medical history, but focus on asthma-specific elements. Previous hospitalizations, ICU admissions, intubation events, emergency department visits, and any severe exacerbations requiring oral steroids. These details matter more than general medical history when it comes to predicting future risk.
Medication history requires more than a list. Document which inhalers they use, technique verification results, adherence patterns, and what actually works versus what they're just using out of habit. I've seen too many patients continuing ineffective inhalers because nobody bothered to check their technique during the case history of asthma patient review. Environmental and occupational history is where the method gets practical. Ask about specific triggers, home conditions, workplace exposures, and recent life changes. One of my own edge cases involved a patient whose asthma worsened only after adopting a new cleaning routine. The "new" product contained bleach compounds that nobody connected to her respiratory symptoms until I specifically asked about recent household changes during the case history of asthma patient assessment.
Common Pitfalls And Where Standard Approaches Fail
The biggest problem I see is treating asthma case history as a one-time event rather than an ongoing process. Asthma changes over time, and so should your documentation. I update case history of asthma patient records quarterly for moderate-to-severe cases because trigger profiles and medication responses shift. Another frequent error is underestimating the importance of comorbid conditions. Allergic rhinitis, GERD, obesity, and sleep apnea all interact with asthma control. When I take a complete case history of asthma patient documentation, I specifically screen for these conditions because treating asthma without addressing comorbidities often leads to poor outcomes. The objective data gap is real in primary care settings. Many clinics lack spirometry capability, which means case history of asthma patient assessments rely heavily on subjective reports. I've learned to work around this by asking patients to keep simple symptom diaries and using peak flow measurements when possible. Even basic home peak flow data can reveal patterns that history alone misses.
Sometimes the case history seems clear but hides important details. I recall a patient who reported "occasional" symptoms, which technically suggested mild asthma. But digging deeper during his case history of asthma patient review revealed he was skipping work 8-10 days monthly due to symptoms. This functional impact completely changed my assessment from mild to moderate persistent asthma, leading to appropriate treatment escalation.
When Standard Case History Of Asthma Patient Approaches Don't Work
Not every patient responds to standard history-taking methods. Some struggle with recall, especially elderly patients or those with cognitive issues. In these cases, I rely more on caregiver input and objective records when building the case history of asthma patient documentation. Children present different challenges. Their parents may have incomplete recall of early symptom patterns or medication responses. I adapt my case history of asthma patient approach by asking about school absences, exercise tolerance, nighttime symptoms, and growth patterns rather than relying solely on parental reports of what the child "actually experiences." Occupational asthma cases often get missed initially. Patients may not connect workplace symptoms to their environment, or they might dismiss them as stress or aging. I specifically ask about symptom patterns relative to work schedules during case history of asthma patient assessments. One of my own encounters involved a nurse whose symptoms worsened only during night shifts but not weekends, revealing a connection to cleaning agents used in the hospital that standard history questions wouldn't have caught.
Practical Tips For Better Asthma Case History Documentation
Use standardized forms when available, but don't let them replace actual conversation. The GINA guidelines offer useful frameworks, but I find that adapting the case history of asthma patient template to each patient's specific situation yields better results than rigid adherence to any protocol. Document everything that could affect future management decisions. Past treatment responses, adverse drug reactions, hospitalization details, and environmental factors all matter. This case history of asthma patient information becomes crucial when switching providers or during acute exacerbations when time doesn't allow for full reassessment. Follow-up is essential. I schedule case history of asthma patient reviews at key intervals: after initial diagnosis, within one month of treatment changes, annually for stable patients, and anytime symptoms change significantly. This isn't just administrative. Each follow-up reveals new information that refines the case history of asthma patient understanding over time.

The case history of asthma patient process takes about 15-20 minutes in my practice when done properly. This usually cuts misdiagnosis rates and reduces unnecessary medication changes by preventing treatment adjustments based on incomplete information. Patients who receive thorough asthma case history documentation report better understanding of their condition and higher satisfaction with care.
Key Elements That Make Or Break Asthma Management
Trigger identification remains the most valuable part of any case history of asthma patient assessment. Knowing what causes symptoms isn't just academic. It directly influences treatment effectiveness and patient outcomes. I specifically ask about temporal relationships between exposure and symptom onset, which often reveals patterns that patients themselves haven't noticed. Medication technique verification deserves equal emphasis. Wrong inhaler technique accounts for up to 70% of apparent treatment failures in some studies. During case history of asthma patient reviews, I routinely ask patients to demonstrate their technique rather than assuming correct use based on prescription records alone. The case history of asthma patient documentation should evolve with the patient. Initial assessments establish baselines, follow-up visits track progression, and periodic reviews ensure nothing important gets overlooked. This ongoing process is what separates competent asthma management from adequate but incomplete care.


