The Math Behind Going Cash-Only
A cash based physical therapy business plan is essentially a document that maps out how you will operate without insurance networks. It tells you your pricing, your marketing costs, your overhead, and when you break even. Most therapists skip straight to the revenue projections without working through the operational details first, which is why so many cash-based practices stall out around month eight. The core structure is straightforward, but the assumptions need to be real numbers, not optimistic guesses. I built my first one in 2019 using a simple spreadsheet with four sheets: patient volume projections, marketing spend and acquisition costs, fixed and variable overhead, and a break-even analysis. The volume sheet was the one people got wrong most often. They assumed 20 new patients per month by month three. That rarely happens. My actual first six months brought in roughly four to seven new patients monthly for the first two months, then slowly climbed to about twelve per month by month six. Marketing was almost entirely word of mouth and local SEO at that stage. Paid ads didn't start showing returns until around month four, and even then the cost per acquisition hovered between $85 and $140 depending on the platform.
The overhead sheet is where people underestimate themselves. Rent for a small clinic space runs $2,500 to $6,000 depending on your market. A part-time front desk person or billing assistant adds another $3,000 to $4,500 per month. Supplies, malpractice insurance, EHR software, and utilities bring the total fixed costs to somewhere between $8,000 and $14,000 monthly before you pay yourself anything. Your pricing needs to cover that gap. Most cash-based PTs charge between $125 and $250 per session. If you bill $150 per session and see an average of twelve visits per patient, that's $1,800 per patient over the course of treatment. With twenty active patients per month, you are looking at roughly $36,000 in monthly revenue. Subtract the overhead and you have your profit margin. But the number of active patients at any given time depends entirely on your intake rate, your treatment length, and your cancellation rate. All three are variable.
Where the Model Actually Breaks Down
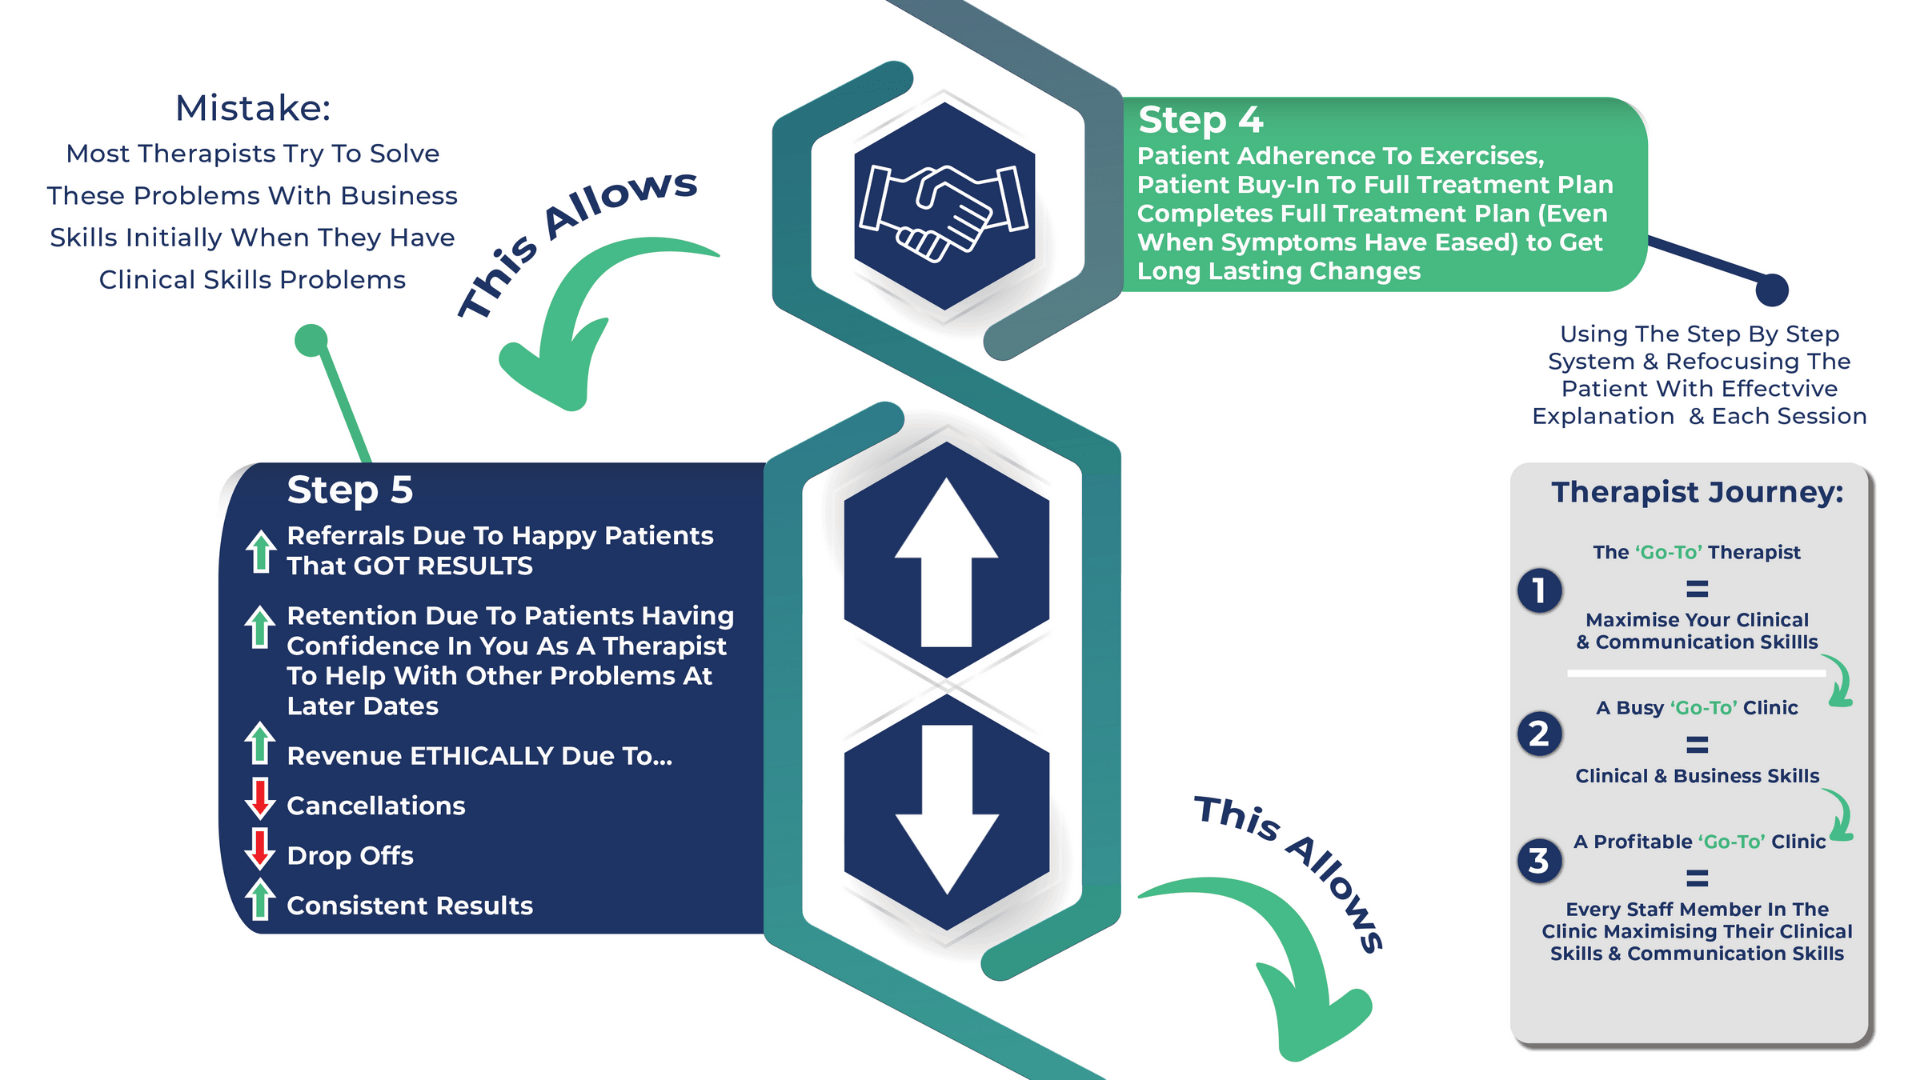
I ran into a specific problem in my second year that most business plan templates don't account for. I had projected an average treatment length of twelve visits based on what I saw in my insured practice. My cash-based patients averaged only six visits. The reason wasn't lack of need. It was that without insurance requiring authorization, patients self-discharged much sooner once they felt better. Some left at four visits. A few stayed at eighteen, but the median pulled the average down hard. This completely destroyed my revenue projection. I had planned for roughly double the actual cash flow. The workaround was to restructure my pricing into packages instead of per-session billing. I offered a twelve-visit program at a slight discount rather than $150 per individual visit. It locked patients in longer and gave me predictable revenue from the start. I also added a retainer model for maintenance care at $75 per visit, billed monthly, which stabilized income between acute treatment episodes. The business plan needed updating to reflect package-based revenue instead of per-session estimates. I rewrote the volume assumptions, and the projections aligned with what actually happened. The counter-intuitive insight here is that going cash-based does not automatically mean higher per-patient revenue. It means higher per-patient revenue only if you can extend treatment adherence. Without insurance driving compliance, patient retention becomes your single most important metric. Your business plan should weight retention and treatment adherence more heavily than acquisition.
Get the Full Details

Building the Financial Model
Start with your break-even point. Figure out your total monthly overhead including your own salary as an expense. Divide that by your average revenue per patient. That gives you the minimum number of active patients you need each month just to stay operational. In most markets, that number falls between fifteen and twenty-five patients. If you cannot commit to seeing enough patients to clear that threshold within six months, the cash model is going to be very tight. Next, map your patient pipeline. You need a steady intake to maintain your active patient count because people leave treatment. If your average episode is twelve visits and you see three visits per week, each patient occupies a slot for about four weeks. To keep twenty active patients, you need to onboard roughly five new patients per month. That is your target acquisition rate. Your marketing budget should be sized to hit that rate at your cost per acquisition. If your CPA is $120 and you need five patients monthly, your marketing spend should be at least $600 per month, but realistically closer to $900 to account for variability. Include a cash reserve line. I recommend planning for three months of operating expenses in the bank before you open. The first quarter of a cash-based practice is almost always lower revenue than projected. Insurance reimbursement models smooth out income with predictable claim cycles. Cash-based practices do not. You will feel the gap acutely in months one through three.
Pricing strategy deserves its own section. Underpricing is the most common mistake. Therapists coming from insurance models instinctively want to appear affordable. But cash pricing communicates value. If your sessions are not clearly differentiated from a hospital outpatient clinic, patients will compare you to the cheapest option in the area. You need to articulate why your practice is worth the price. Specialization helps. Sports rehab, pelvic health, vestibular therapy, and post-surgical protocols command higher rates because the outcomes are specific and measurable. General musculoskeletal PT competes on price. Pick a niche or plan to operate on thin margins.
Operational Details That Matter
Your consent forms and financial agreements need to be airtight. Cash patients pay upfront or on a weekly basis. You need a clear no-show and cancellation policy written into the intake paperwork. I learned this the hard way when a patient scheduled three sessions per week for two months, canceled one session without notice every single time, and still expected to receive the full treatment plan. By then I had already allocated that time to other patients who never showed up. The policy I added after that experience charges for missed appointments within twenty-four hours and applies a late cancellation fee. It reduced no-show revenue loss by about sixty percent. Marketing channels vary significantly by market size. In a city of two hundred thousand or more, Google Ads and Facebook Ads can work reliably. Below that threshold, referral networks become far more important. Orthopedic surgeons, primary care physicians, chiropractors, and personal trainers are the main referral sources. A single referring physician who sends two patients per month is worth more than a poorly targeted ad campaign. Build relationships before you need them. That means sending periodic case updates, offering free seminars to local gyms, and making it easy for other providers to refer. I spent about an hour per week writing brief email updates to my top five referring sources during the first year. It generated roughly thirty percent of my new patient volume by month ten.
When Cash-Based Doesn't Work
Be honest about where this model fails. If you live in a rural area with limited population density, your addressable market may be too small. A cash-based practice needs enough affluent or self-funded patients in the area to sustain volume. If the nearby demographics skew toward Medicare and Medicaid populations, you will struggle. Insurance-accepted practices absorb that reality. Cash-only practices do not. Another scenario where this fails is if you prefer not to do sales. Running a cash-based practice requires constant outreach, follow-up, and conversion of inquiries into committed patients. It is not a passive business. If you would rather focus entirely on clinical work and hire someone else to handle the front office, you can, but that increases your overhead and shrinks your margin. There is a middle ground where you use a virtual intake coordinator for about five hundred dollars per month, but then you are paying for someone to do the selling you might have been able to handle yourself. Finally, consider the hybrid approach. Some practices accept insurance for select plans while running a cash-based track for others. This reduces risk and stabilizes cash flow. The tradeoff is that you need credentialing and billing infrastructure for the insured patients, which brings back much of the administrative burden you were trying to avoid. It depends on whether you want a simpler operation or a more resilient one.
The download link for a working template is not something I can host directly, but the structure I described above is easy to replicate in Google Sheets or Excel. Start with the four sheets I mentioned, plug in your real local costs, and stress-test the volume assumptions against a conservative scenario. If the practice still looks viable at sixty percent of your projected patient count, you have a reasonable chance of success. Anything thinner and you are gambling more than building.