How Cath Lab RN Training Actually Works When No One Tells You
Most Cath Lab RN Training programs are 6 to 12 months long, depending on the hospital and how many procedures your site does. You get assigned a preceptor. You show up. You watch. You touch things after you are cleared to touch them. That is the surface version. The real version involves a lot of standing in a lead apron for eight hours while someone explains the same thing three times because you missed it the first two times.
I watched a new grad struggle for three weeks with transducer management during femoral access cases. The problem was not that she did not understand the concept. It was that she kept reaching for the transducer with her left hand while simultaneously adjusting the C-arm with her right, which means she had to reposition the leg table twice per case. We ended up marking the transducer handle with a small piece of colored tape so her hand always found the right orientation without looking down. That cut her setup time from about five minutes per case to two minutes and removed the constant leg repositioning.
What Cath Lab Rn Training Covers
You learn radiation safety first because if you mess this up there is no second chance. Time, distance, shielding. The fluorescent time dose rate on the monitor is not a suggestion. I have seen people who treated it as background noise and later paid for it. You will learn about the dosimeter badges, how to read them, and why wearing two is sometimes required depending on the facility policy.
Then you move into hemodynamics. Understanding arterial waveforms is something that separates the people who can function independently from the people who need a radiologist to narrate every single beat. A damped waveform means something. A foreign body on the line means something else. You learn to recognize these before they become emergencies instead of after.
Pharmacology in the cath lab is its own category. This is not med-surg dosing. You are working with vasoactive drips, anticoagulants, intra-aortic balloon pumps, Impella devices, and contrast media under real-time fluoroscopy. The learning curve for vasopressor management during angioplasty is steep. Blood pressure can drop fast when you inflate a balloon in a stenotic vessel.
I remember one case where a patient's systolic dropped from 140 to 82 within seconds of balloon inflation during a renal artery stent placement. The attending was focused on the fluoroscopy image and did not see the waveform collapse until it was already happening. The nurse on that case had been watching the systemic pressure trace directly and called for ephedrine before the pressure went below 70. That is the difference between training that teaches you to monitor equipment and training that teaches you to monitor the patient through the equipment.
The Simulation vs. Reality Gap
Simulators are useful. They are also limited in ways that will frustrate you. A simulator will not reproduce a calcified iliac artery that refuses to accept a 6 French sheath. It will not show you what happens when the guidewire goes subintimal and you have to decide whether to attempt re-entry or abort. Simulator time usually covers ideal anatomy and standard procedures. Real cases cover everything else.
A common pitfall is over-relying on simulator credentials and arriving at the lab thinking you are ready for live cases. You are not. The simulator builds motor familiarity with the controls. It does not build clinical judgment under pressure. You will find this out quickly when the radiologist asks for a specific projection and you have to set it up without disrupting the sterile field.
Another thing people do not tell you about Cath Lab Rn Training is the documentation requirement. Some facilities require case logs for 100 to 200 procedures before you are considered competent. This is not arbitrary. The numbers exist because certain complications only appear after a minimum exposure threshold. Complications like retroperitoneal hemorrhage or distal embolization do not happen in the first twenty cases. You need volume to recognize the early signs.
Here is a practical workaround for the volume problem. If your program restricts certain procedures for trainees, you can still track preparatory and assistive tasks that count toward your log. Needle sticks, sheath insertions under supervision, wire transfers, contrast administration timing, post-procedure sheath management, and hemodynamic monitoring during complex cases all count if your program allows it. Not all programs count them equally, so check your specific competency checklist early.
Communication Under Pressure
The cath lab environment is loud, rushed, and hierarchical. The attending does not have time for a paragraph. You will learn to communicate in short phrases that contain the necessary information without waste. "Sheath is 6 French femoral. Air flushed. Bed is flush." That is three seconds. It saves more than three seconds.
I encountered a situation where a new RN spent ninety seconds explaining the entire vascular access sequence to the attending because she had not learned the format yet. The attending was in the middle of a delicate intervention and needed the information instantly. She froze because she had memorized the steps but not the delivery method. We practiced a standardized verbal report format for the rest of her rotation and it reduced her communication errors to almost nothing.
This is also where many people stumble on cross-crowding communication. The radiologist speaks one language. The anesthesiologist speaks another. The perfusionist if present speaks a third. You are the translator between them. If you are not comfortable interrupting a flow to clarify a medication order, you will cause problems. It is better to say "Let me confirm that dose" than to administer something and discover later it was wrong.
Radiation Safety and Your Long Term Health
This is the part people acknowledge in training and then ignore once they feel comfortable. Lead aprons are heavy. Thyroid shields matter. Scattered radiation hits you from the patient, not from the tube. The tube direction does not determine where the scatter goes. The patient does.
I worked with a nurse who avoided positioning herself behind the lead shield during long cases because it felt restrictive. She accumulated significant scatter exposure over two years and her dosimeter readings reflected it. Once she started standing properly behind the portable shield and using ceiling-suspended acrylic shields, her annual effective dose dropped by roughly forty percent. That is a meaningful difference when you are calculating lifetime exposure.
Wrist and eye dose is another thing that gets overlooked. The thyroid badge tells you part of the story. Personal dosimeters on the dominant wrist and near the eyes give you a more complete picture if your facility offers them. Some programs do not provide these by default. Ask for them during your first week.
Technical Skills That Separate Competent From Dangerous
Pacing wire management is a skill that most training programs do not cover adequately. When you are managing temporary transvenous pacing, you need to understand impedance checks, capture thresholds, and sensing patterns. A nurse who understands basic ECG interpretation and pacing fundamentals will catch a loss of capture event faster than one who only knows the alarm sounds when something is wrong.
Intra-aortic balloon pump management requires understanding the timing waveform. The dicrotic notch, the augmentation phase, the timing relationship to the R wave. Mis-timed IABP augmentation can reduce coronary perfusion instead of increasing it. You should be able to look at the pressure waveform and tell within seconds whether the timing is optimal.
Vasovagal response management is another area where textbook knowledge does not translate directly to competence. The classic presentation is bradycardia and hypotension after femoral sheath removal or during angiography. But the atypical presentation happens more often in real life. A patient who becomes nauseated and diaphoretic without a dramatic blood pressure drop. If you wait for the numbers to crash before intervening, you are already late.
I had a trainee who managed a vasovagal episode correctly according to the protocol but failed to anticipate the recurrence because she did not recognize the early signs in a second patient ten minutes later. We went back and reviewed the prodromal symptoms until she could identify them before the full episode developed.
What Good Programs Get Wrong
Some Cath Lab Rn Training programs rush through contrast nephropathy prevention because it is not flashy. It should not be rushed. Hydration protocols, contrast volume tracking, N-acetylcysteine administration where indicated, and post-procedure monitoring are among the highest-impact nursing responsibilities in the lab. A single case with excessive contrast in a diabetic patient with borderline renal function can result in a prolonged stay and potential permanent kidney damage.
Another gap is psychosocial preparation. Patients coming into the cath lab are anxious. They are often in pain. They may not understand what is happening. The nurse who takes thirty seconds to explain each step loses fewer patients to anxiety-driven complications than the nurse who assumes the patient will cooperate because they were sedated.
The documentation burden is real. Electronic medical record entry in the cath lab slows you down because the interface was designed for floor nursing, not procedural documentation. Spend time in the first two weeks learning the shortcut keys and templated phrases your facility uses. It will save you hours per week once you are independent.
A Realistic Timeline Expectation
Months one and two are survival. You will feel like you are learning everything at once. That is normal. Months three and four is when the foundation starts holding weight. You begin anticipating next steps instead of reacting to them. Months five and six is when most people feel functional. Competence comes later, usually around month eight or nine when you have seen enough variation in patient anatomy and complication patterns to trust your own judgment.
If your program moves faster than this, pay attention. Accelerated programs exist. They also have higher attrition rates because the cognitive load is higher and the safety margin is thinner. If you are in an accelerated track, request additional simulation time and extra case observation hours during the first eight weeks. It will feel slow at the time. It will prevent mistakes later.
The cath lab is not a difficult environment if you respect the complexity of what you are learning. It is a difficult environment if you pretend the complexity does not exist. Cath Lab Rn Training works best when you approach it as a continuous learning process rather than a checklist to complete. The patients you care for will notice the difference, and the attending radiologists will notice it too.
Gallery Cath Lab Rn Training
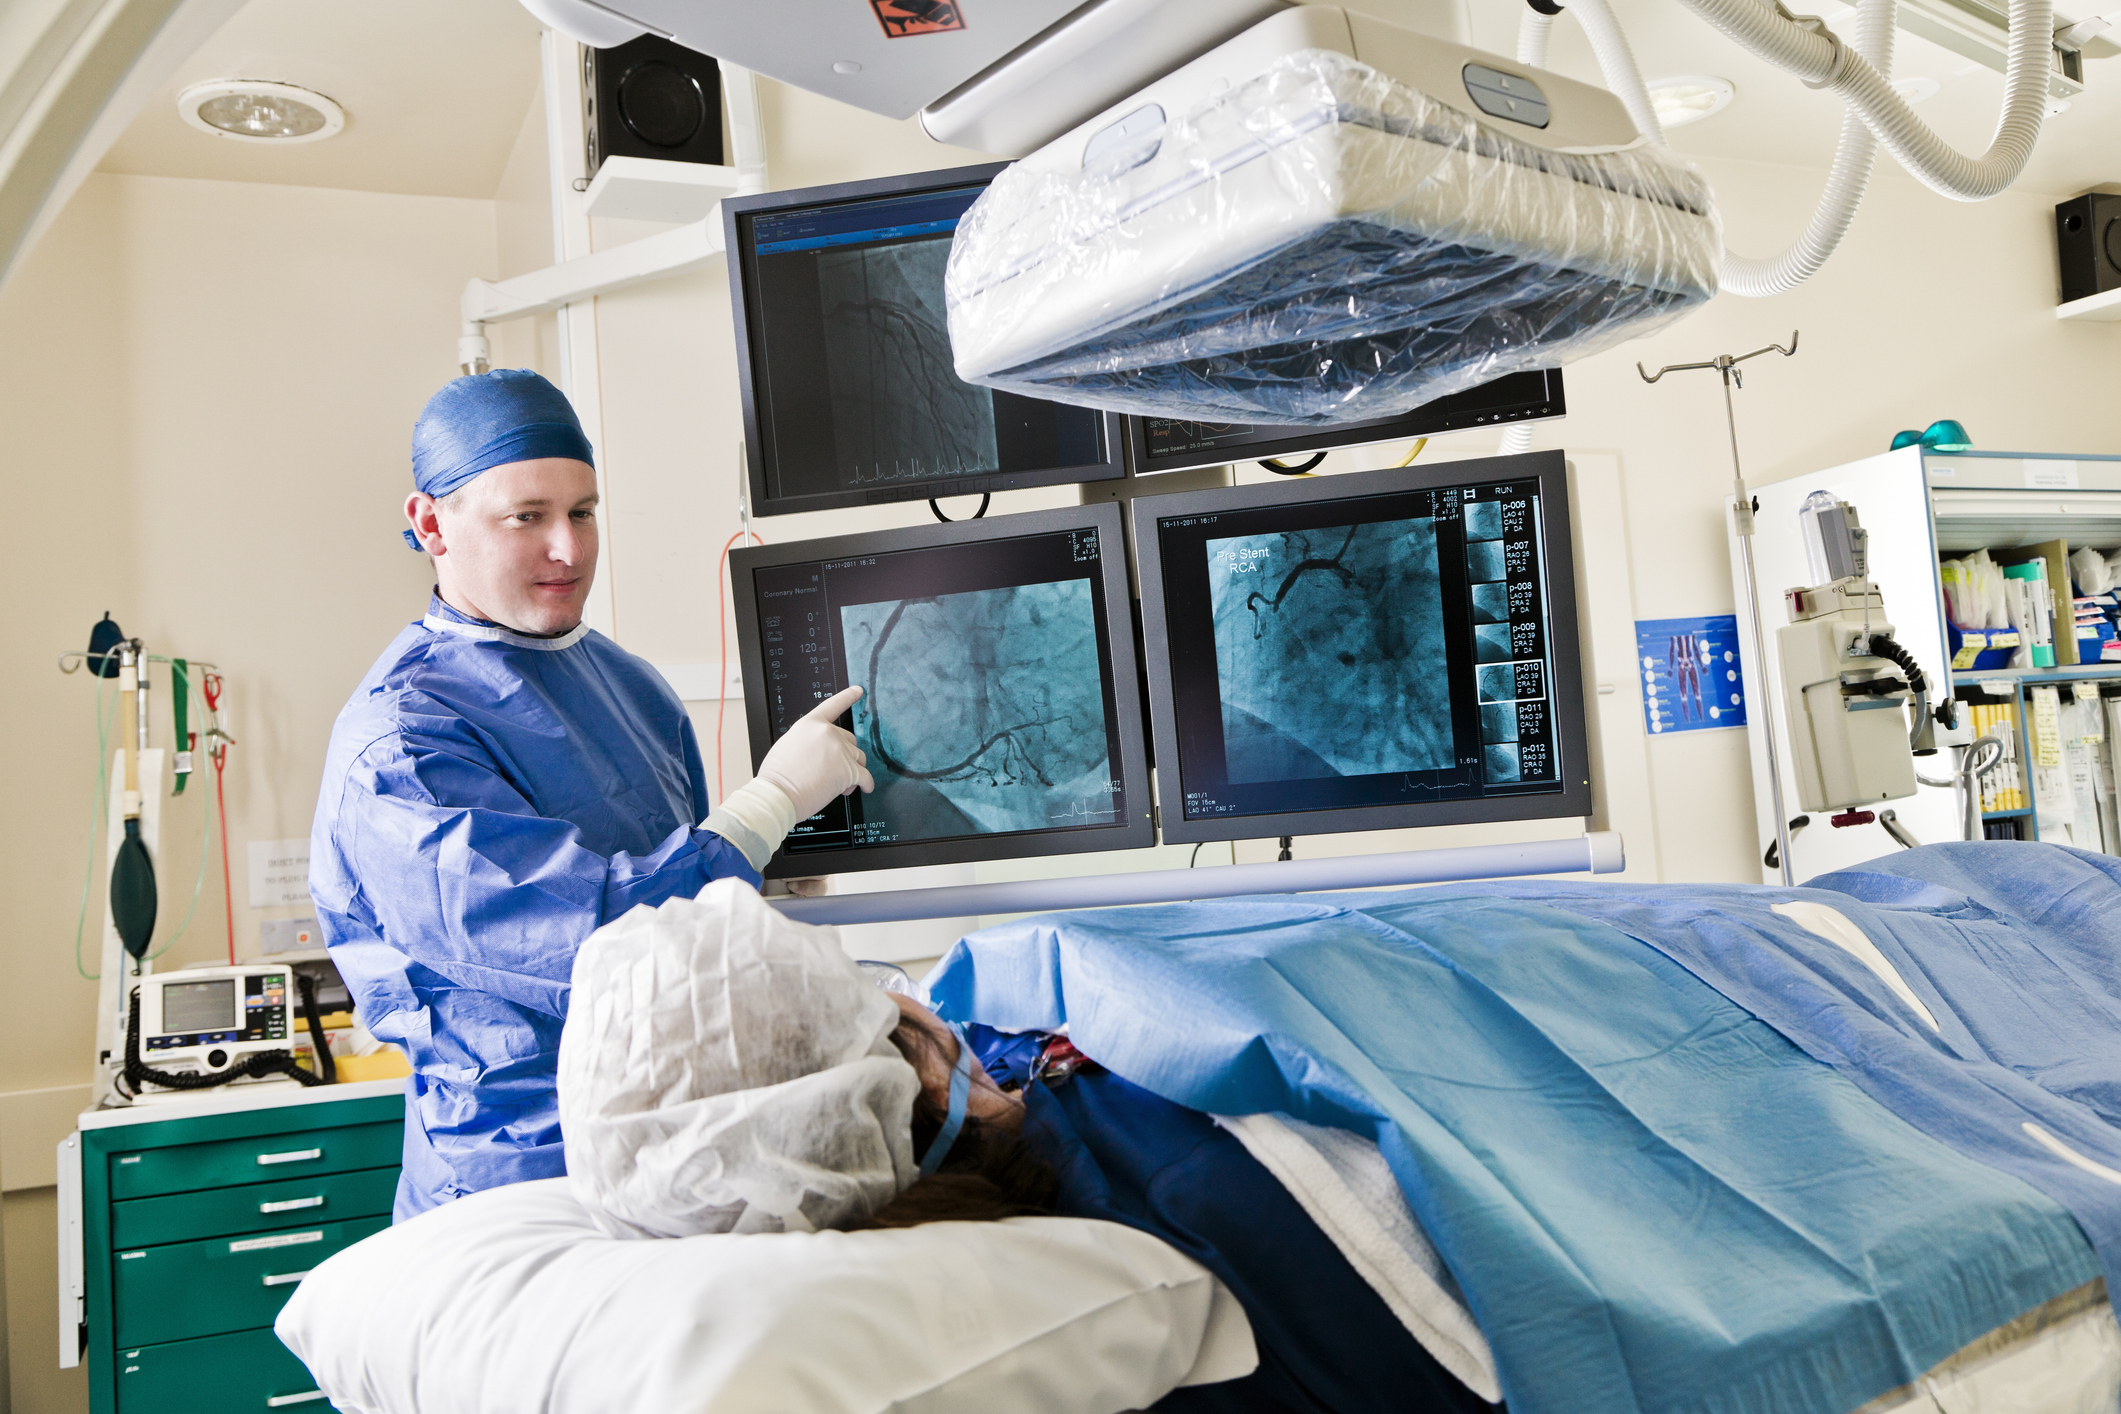
Cardiac Cath Lab Spotlight – Interview with Katie Hansen, BSN, RN, PCCN – Nurse Clinicial ...
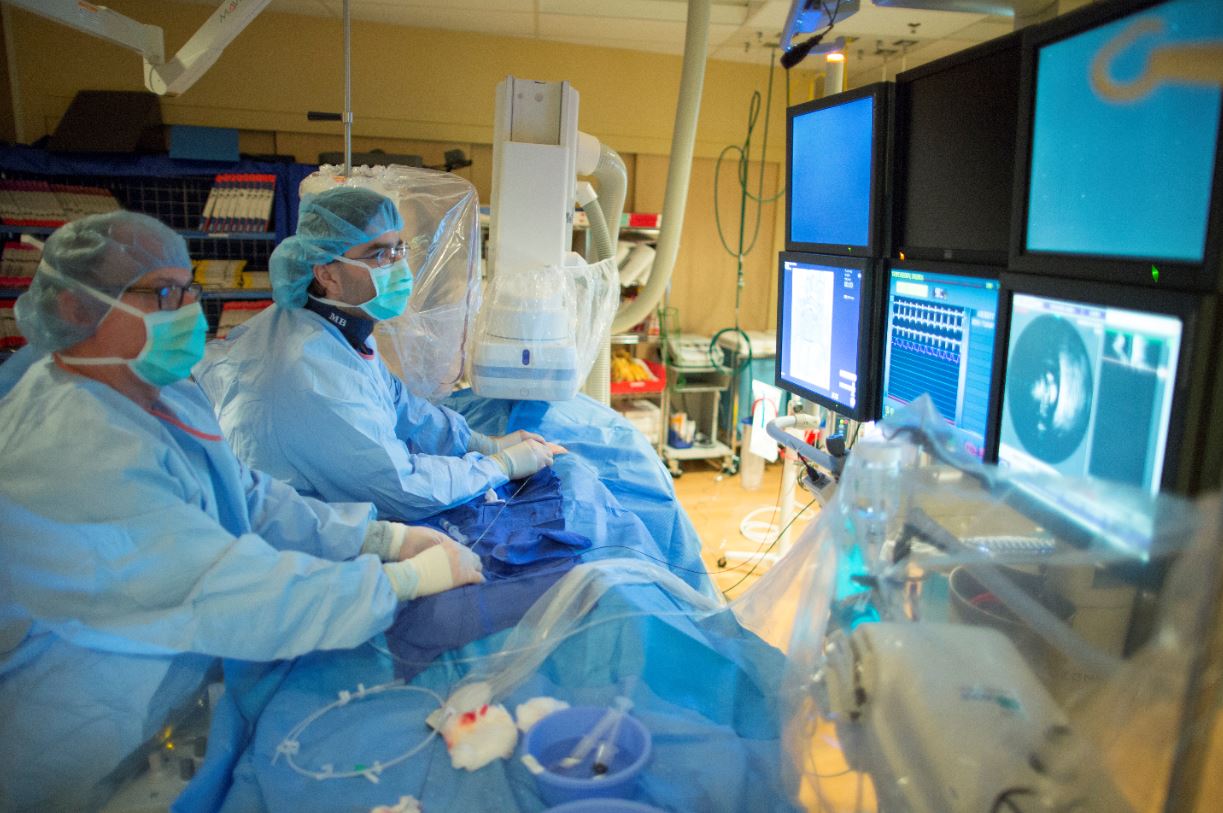
Join our Cath Lab Team as an RN or Rad Tech! The Cardiac Cath Lab, located in the Heart ...
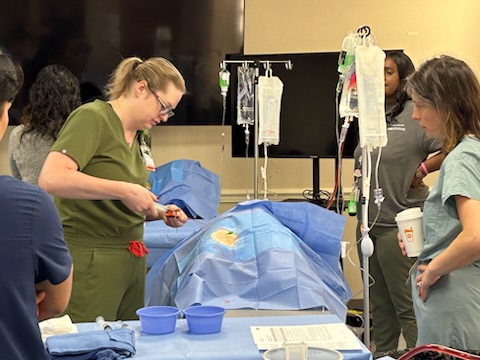
Cath Lab Skills sim boosts confidence, patient safety - UAB Clinical Simulation
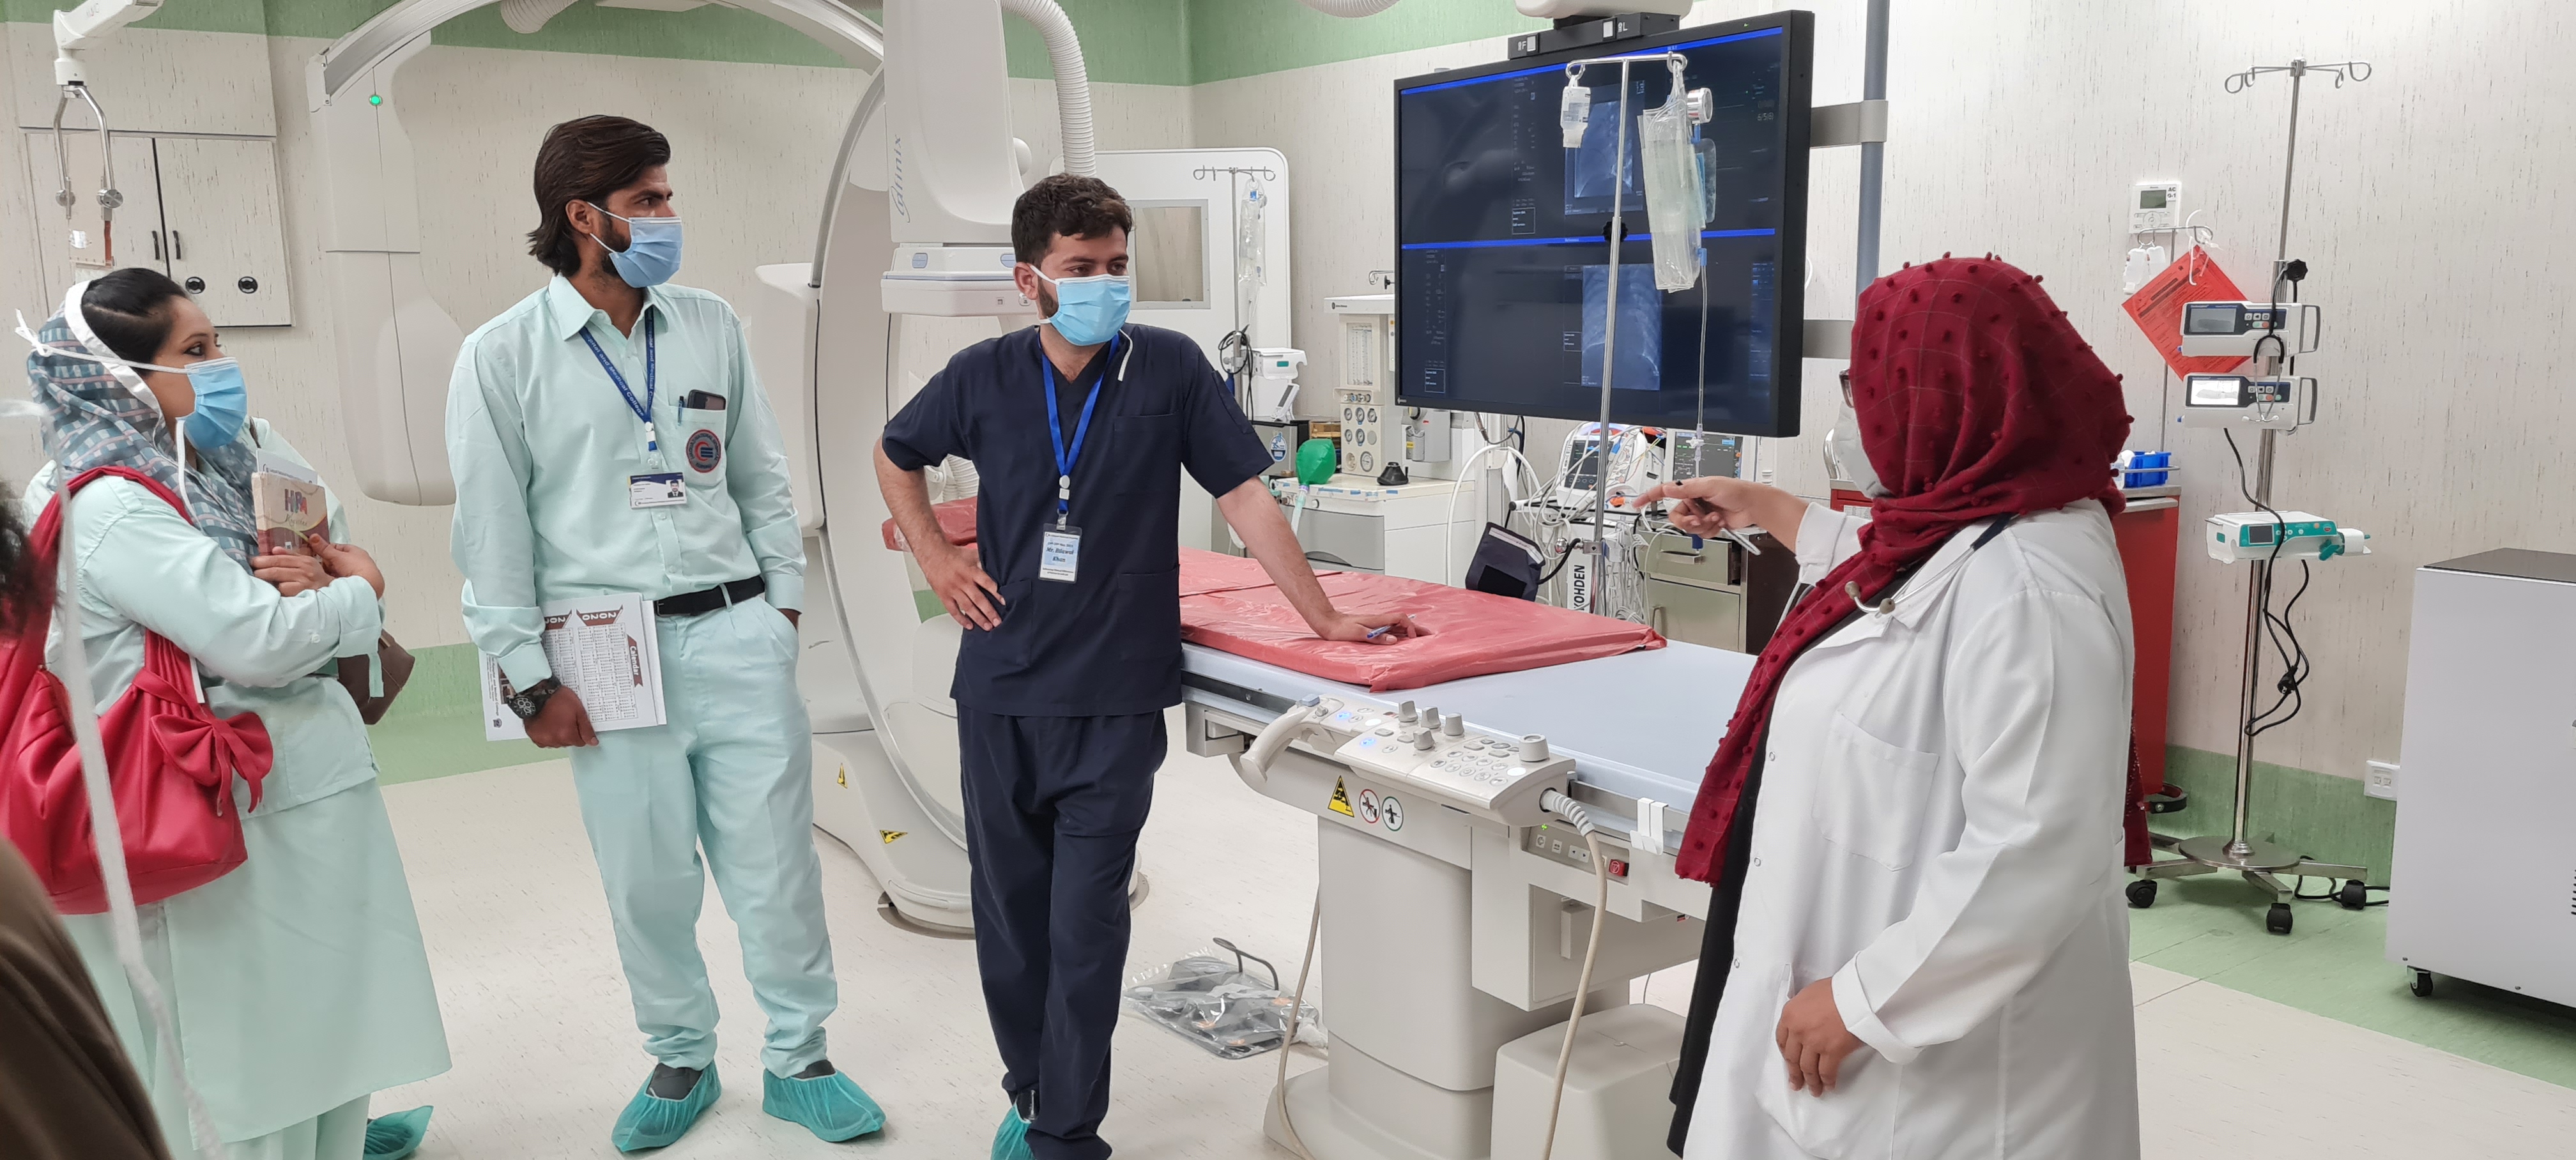
Course on Enhancing Clinical Efficiencies of Nurses in Cath Lab
What Is A Cath Lab At A Hospital at Marvin Bruner blog