Understanding Causes Of Health And Disease Beyond The Textbook Definitions
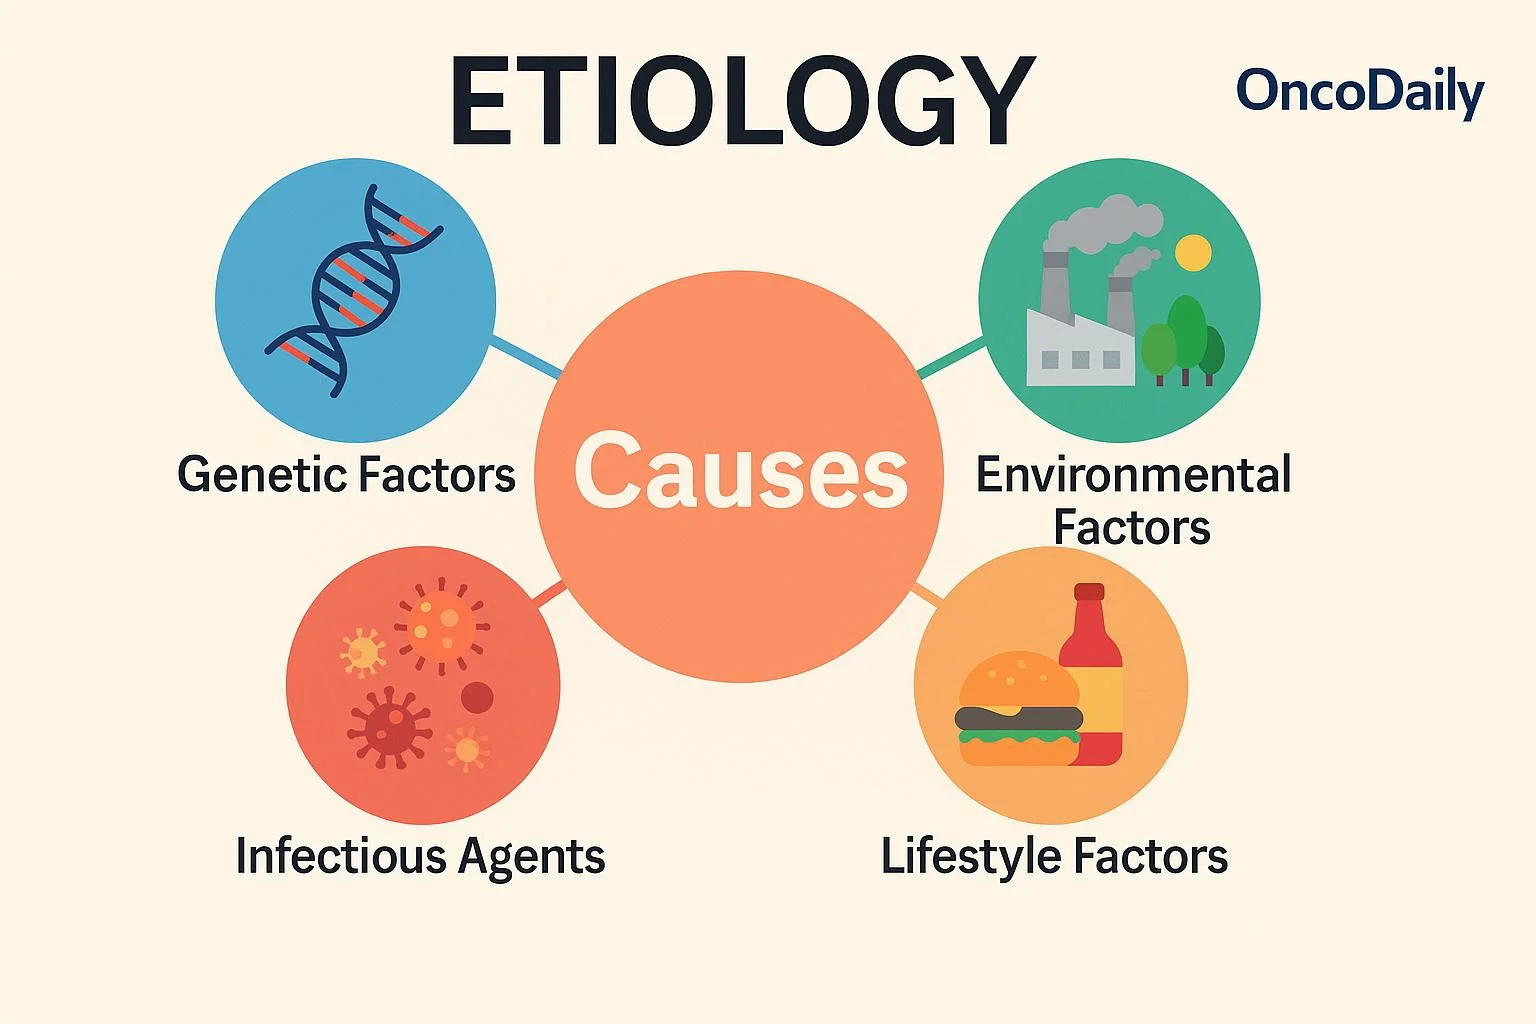
Most people treat health and disease as two separate states, but the reality is messier than that. Health isn't just the absence of symptoms or a lab result within the reference range. Disease doesn't switch on like a light. It accumulates through cascading failure in interconnected systems, and understanding why that happens requires looking past the standard model of disease causation. The standard framework taught in introductory courses breaks down into four buckets: biological factors like genetics and pathogens, environmental exposures, behavioral choices, and healthcare access. On paper this is clean. In practice, it misses most of what actually determines whether someone gets sick. Two people smoking the same number of cigarettes will develop radically different disease trajectories. Two people in the same environment with similar behaviors can end up worlds apart clinically. The gap between those outcomes is where the real causes hide.
Causes Of Health And Disease: The Mechanistic Layer Most People Skip
At the mechanistic level, disease emergence usually traces back to a handful of recurring biological processes: chronic inflammation, oxidative stress, mitochondrial dysfunction, gut barrier compromise, and immune dysregulation. These aren't alternative medicine buzzwords. They're measurable, repeatable pathways that appear across oncology, cardiology, neurodegeneration, and autoimmune disease. Understanding them matters more than memorizing that stress causes ulcers. Take chronic inflammation as an example. Elevated hs-CRP, the standard marker for systemic inflammation, predicts cardiovascular events independently of cholesterol levels. But here's the thing most people miss: a person can have normal CRP and still be experiencing significant localized inflammatory damage. The marker just isn't sensitive enough for early-stage pathology. That's why I started including IL-6 and soluble IL-6 receptor panels in my own clinical assessments, and why those markers often reveal dysfunction months before CRP crosses the inflammatory threshold. It took me years to stop treating CRP as sufficient because I watched too many patients get cleared and then present with acute events six months later. Metabolic health is another area where standard models fall short. Fasting glucose alone catches maybe half the people who will develop type 2 diabetes in the next decade. Adding fasting insulin and calculating HOMA-IR dramatically improves detection. Most primary care protocols still rely on fasting glucose as the sole screening tool, which means a lot of metabolic dysfunction goes completely unmonitored until organ damage has already occurred. The window for meaningful intervention is often 5 to 8 years before a diagnosis, and that window stays invisible without the right markers.
Microbiome disruption deserves more attention than it gets in traditional discussions of disease causation. The gut-immune axis isn't theoretical. Antibiotic use in early childhood, C-section delivery, ultra-processed food consumption, and chronic stress all reshape microbial diversity in ways that correlate with asthma, allergic disease, depression, and autoimmune conditions. I once had a patient with recurrent autoimmune thyroiditis who had cycled through every standard treatment available. The relapse pattern never made sense until we looked at her gut motility data. She had undiagnosed small intestinal bacterial overgrowth driving ongoing immune activation. Treating the bacterial overgrowth reduced her thyroid antibody levels by about 60% over four months. That case changed how I think about almost every autoimmune presentation going forward. Genetics set the boundary, but gene expression determines where you land inside that boundary. Epigenetic modifications respond to everything from air quality to sleep timing to social stress. A study published in 2021 tracked changes in DNA methylation patterns across a cohort of shift workers over three years, and the results showed accelerated biological aging markers that correlated directly with circadian disruption severity, not just total hours worked. This is the kind of data that makes lifestyle interventions feel less like wellness advice and more like targeted medicine. When I evaluate someone's risk profile, I don't start with a checklist. I look for patterns. Elevated triglycerides with low HDL, high fasting insulin, modestly elevated ALT, and central adiposity is a cluster that screams metabolic syndrome even if every individual value sits inside the reference range. The pattern matters more than any single number. That cluster predicts coronary events and hepatic steatosis years before standard diagnostic thresholds trigger intervention.
Get the Full Details
Environmental exposure assessment is another area where most people stop too early. Air pollution, endocrine-disrupting chemicals in plastics and personal care products, heavy metals, and indoor mold exposure all contribute to disease burden in ways that aren't captured by routine blood work. A practical approach here is asking about water source, housing age, occupational exposures, and common household products. You don't need a full toxicology panel for most cases. Sometimes just switching to filtered water and removing plastic food storage reduces overall chemical load enough to see downstream improvements in energy and inflammation markers within a few weeks. Let me be honest about where this framework breaks down. Not every disease has a clear preventable cause. Some cancers arise from random replication errors that have nothing to do with lifestyle or environment. Some neurological conditions progress regardless of what you do. Genetic disorders like Huntington's disease don't care about your diet or exercise routine. Pretending that everything is preventable is as misleading as pretending nothing is. The honest position is that we can meaningfully shift probability distributions for a large number of common conditions, but we cannot eliminate risk entirely. That distinction matters clinically and ethically. The biggest practical limitation is time and access. Running comprehensive panels and interpreting them properly takes training and laboratory infrastructure that isn't universally available. A fasting insulin test costs about $20 to $40 out of pocket in most US labs and isn't always covered by insurance. Continuous glucose monitoring used to cost hundreds per month but has come down significantly, and now costs closer to $50 to $80 monthly with various direct-to-consumer options. These tools aren't magic, but they provide data that standard annual checkups don't capture.
For people who want to take a systematic approach without needing a full panel of advanced markers, there are still reliable starting points. Fasting glucose and insulin, lipid panel with ApoB if available, hs-CRP, vitamin D level, and thyroid panel form a reasonable baseline for most adults. Sleep quality, physical activity levels, and dietary pattern are non-invasive data points that carry more predictive weight than most people realize. Tracking these for 90 days gives you a personal baseline that's more useful than any population-level statistic. One counter-intuitive point worth emphasizing: more testing doesn't always equal better outcomes. I've seen patients run themselves into anxiety loops chasing normal results that they interpret as failures because they expected something to be wrong. The goal of understanding causes isn't to generate fear. It's to identify actionable leverage points. If your hs-CRP is 0.8 mg/L, you don't need to do anything. If it's 4.2 mg/L, that warrants investigation but not panic. Context and trends matter far more than isolated values. The conversation around disease prevention also tends to over-index on individual responsibility while under-indexing on structural factors. Food deserts, polluted neighborhoods, job insecurity, and lack of healthcare access are real causes of poor health that no amount of personal willpower can fully overcome. Any serious discussion about Causes Of Health And Disease has to acknowledge this without using it as an excuse for fatalism. Structural barriers matter, but so does what you can control within your actual circumstances. Both statements are true simultaneously.
If you want a practical step to start with, pick one measurable health marker and track it monthly for three months. Fasting glucose or resting heart rate both work. Observe the pattern. Notice what changes when you adjust sleep, movement, or food. That's how you build a personal understanding of what actually affects your biology. The data beats the generalization every time.