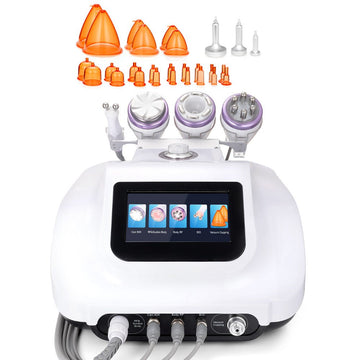
Getting Your Teeth Into Cavitation And Vacuum Therapy
I ran a clinic for about eight years before moving strictly to consultations and equipment servicing. During that time, cavitation and vacuum therapy machines showed up in nearly every mid-tier aesthetic practice. They were the entry-level revenue drivers. That doesn't mean they're easy to run well. Here's what actually happens when you put the transducer on someone's flank and turn the machine on. The ultrasonic probe emits low-frequency sound waves at around 40 kHz. Those waves travel through the subcutaneous layer and create alternating high-pressure and low-pressure cycles in the adipose tissue. During the low-pressure phase, microscopic vacuum bubbles form inside the fat cells. During the high-pressure phase, those bubbles collapse. The mechanical stress from that cycle ruptures the adipocyte membranes, releasing triglycerides and free fatty acids into the interstitial space. The lymphatic system then clears that material. Vacuum therapy, running simultaneously on the same area, pulls the skin upward into a cone, which mechanically stimulates the lymphatic vessels and pushes fluid toward regional lymph nodes. The two modalities are synergistic because the cavitation loosens the cellular contents while the vacuum provides the clearance pathway.
Setting Up A Cavitation And Vacuum Therapy Session
You don't need a degree to operate the equipment, but you do need to understand impedance matching, which most operators completely ignore. The gel you spread on the skin isn't just a lubricant. It's an acoustic coupling medium that eliminates air gaps between the probe and the skin surface. Air has an acoustic impedance of roughly 400 Rayls compared to soft tissue at about 1.6 million Rayls. Without gel, over 99 percent of the ultrasonic energy reflects off the skin surface and never reaches the fat layer. I've watched technicians use a thin, hurried swipe of gel and then wonder why the client feels nothing and the treatment is ineffective. Apply enough gel that the probe doesn't chatter against the skin. You should see it compress slightly under the transducer head. The typical protocol runs at 40 kHz for cavitation and anywhere from 20 to 40 kPa of vacuum pressure depending on the client's comfort and skin tolerance. A standard session covers one anatomical region for 25 to 40 minutes. Most manufacturers recommend a treatment interval of four to seven days between sessions, with a full course running 6 to 12 treatments. The fat cell destruction happens acutely during the session, but the actual reduction in tissue volume becomes visible over the following two to four weeks as the lymphatic system processes the released lipids. Hydration matters more than people admit. A client who comes in dehydrated will clear the released triglycerides significantly slower. I always require clients to drink at least 500 milliliters of water before the session and continue hydrating for 48 hours afterward. The metabolism of free fatty acids occurs primarily in the liver, and that pathway functions optimally with adequate water availability. Skipping hydration doesn't just slow results, it increases the likelihood of post-treatment headaches and mild nausea because the metabolic load spikes without sufficient fluid volume to support hepatic processing.
There's a specific issue I ran into repeatedly with vacuum therapy that isn't covered in any manual. When working on the inner thigh or the area just above the knee, the skin is thinner and more mobile than on the abdomen or flanks. If you set the vacuum too high on those areas, the machine pulls enough tissue into the cone that you can occlude superficial blood flow. The client will report a burning sensation rather than the normal pulling sensation, and you may see the skin in the cone turn dusky purple within three to five minutes. The workaround is simple but unintuitive: drop the vacuum pressure by roughly 30 percent and increase the session time by a comparable margin rather than pushing harder. The lymphatic stimulation comes from the rhythmic compression and release, not from maximum suction force. I also switch to a smaller diameter probe on those areas because the larger cones concentrate too much negative pressure on a small surface area. Contraindications aren't a suggestion list. I'm talking about actual hard stops. Pregnancy is one. Pacemakers and other implanted electronic devices are another because the electromagnetic field from the cavitation transducer can interfere with device function. Active cancer, especially in the treatment area, is a stop. You should also not treat over broken skin, active infections, or areas with deep vein thrombosis. I once had a technician argue with a client who wanted treatment over a varicose vein on the calf because the vein was "just on the surface." The ultrasonic energy penetrates approximately 1 to 2 centimeters into tissue. That depth absolutely reaches the venous structures underneath. We moved the treatment to the adjacent area and explained the reasoning. The client understood. One thing that surprises people is that cavitation does not destroy fat cells permanently in the way liposuction does. The ultrasound disrupts the cell membrane, yes, but the body also triggers a repair response. Some adipocytes recover and reseal their membranes, particularly if the energy output is too low or the treatment duration is insufficient. This is why underpowered settings produce inconsistent results. You want enough energy to cause irreversible membrane disruption but not so much that the body mounts an inflammatory response leading to fibrosis or discomfort. The sweet spot on most quality machines sits around 35 to 45 kHz at an intensity that produces a warm sensation without pain. The client should feel heat and a deep vibration, never sharp or burning pain.
Get the Full Details
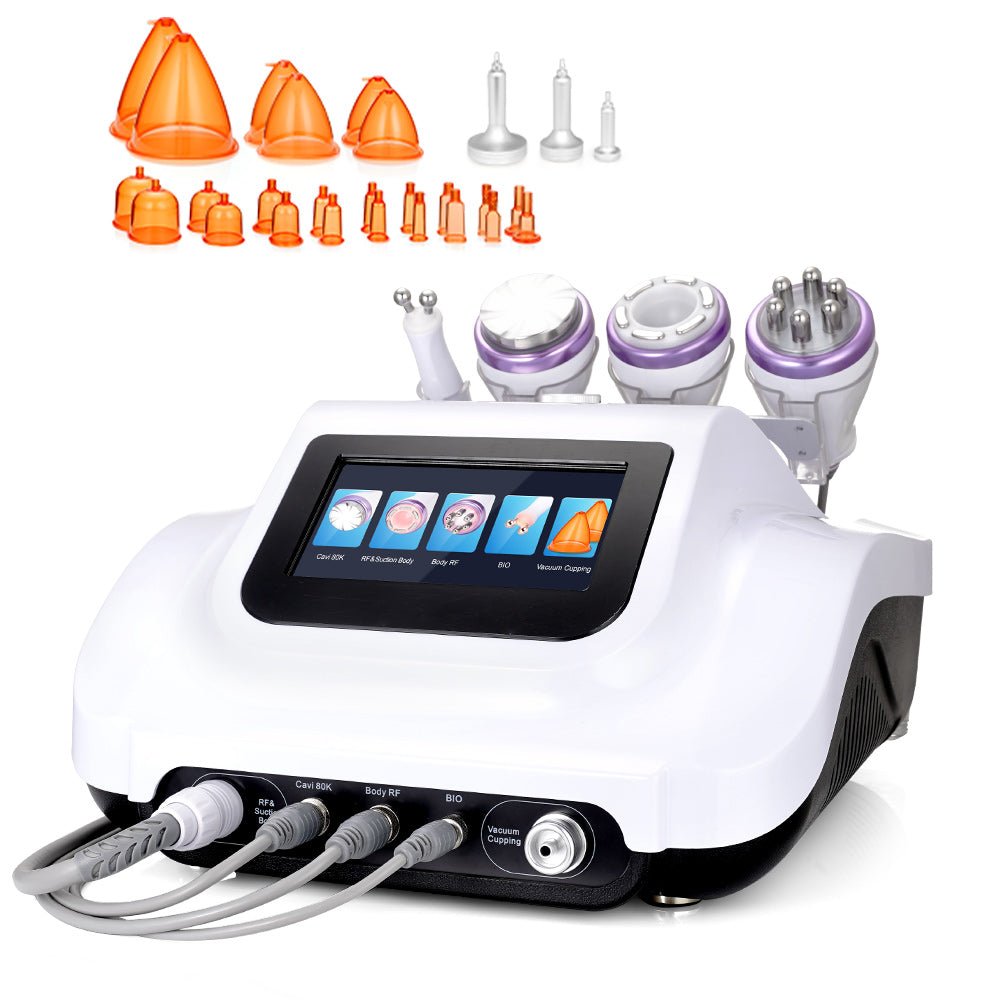
Post-treatment alcohol avoidance for 48 hours is standard advice, and it's not just tradition. The liver is already processing the mobilized triglycerides. Alcohol competes for the same metabolic pathways, specifically alcohol dehydrogenase and the microsomal ethanol-oxidizing system. Introducing alcohol during that window slows lipid clearance and can amplify side effects like fatigue and headache. I tell clients to avoid it for three days to be safe, not two. Machine maintenance is where most clinics cut corners and then complain about inconsistent results. The gel pads on the transducer head wear down. After roughly 500 to 1,000 treatments depending on the manufacturer, the coupling surface develops micro-abrasions that scatter the ultrasonic waves. You'll notice it as a gradual decrease in perceived warmth and effectiveness even though the machine's power output hasn't changed. Replace the gel pads or the transducer head according to the manufacturer's schedule. Also check the vacuum tubing for micro-cracks. A small leak reduces effective suction pressure by 15 to 20 percent, which means you're delivering less mechanical stimulation than the gauge indicates. A $30 hose replacement every six months prevents this. The clinical evidence for these treatments is mixed but leans positive when protocols are followed correctly. A 2017 systematic review in the Lasers in Surgery and Medicine journal found that radiofrequency-assisted lipolysis and ultrasonic cavitation both produced statistically significant circumference reductions, though the effect sizes were modest. Average reduction per session across studies was approximately 0.5 to 1.5 centimeters in the treated area. The results compound across a full course. Clients who complete 8 to 10 sessions typically see 2 to 5 centimeters of total reduction depending on baseline body composition and adherence to post-treatment guidelines.
The biggest mistake I see is setting unrealistic expectations. This isn't weight loss. It's localized fat reduction. Clients who expect to drop three dress sizes from a cavitation and vacuum course will be disappointed. The treatment works on subcutaneous fat deposits that are resistant to diet and exercise, primarily the abdomen, flanks, thighs, and upper arms. It does not address visceral fat or significant obesity. The best candidates are within 10 to 20 pounds of their ideal body weight and have discrete, pinchable fat deposits. Anything beyond that and you're better off directing them toward nutritional counseling and structured exercise programs, possibly with medical supervision if metabolic factors are involved. Documentation is something I wish more operators took seriously. Before and after photos taken under consistent lighting and positioning, along with circumference measurements at standardized anatomical landmarks, provide objective tracking. Without this data, you're relying on client perception, which is notoriously unreliable. Clients often overestimate progress in the first two sessions and underestimate it by session six. The numbers don't lie, and they protect you if a client disputes the outcome. The equipment market is flooded with no-name import machines that claim the same specifications as established brands but use inferior transducers and uncalibrated vacuum pumps. The difference shows up within three months of regular use. Power output drifts, vacuum pressure becomes inconsistent, and the transducer generates excess heat that can cause mild thermal injury if the operator isn't constantly monitoring skin temperature. Invest in reputable equipment or rent before you buy if you're about volume. The cost of replacing a degraded transducer on a cheap machine often equals half the price of a decent used unit from a established manufacturer.
Things I Wish Everyone Knew Before Booking
Cavitation and vacuum therapy is a tool, not a transformation. It works within the constraints of human physiology and requires client compliance to deliver measurable results. The mechanism is sound, the technology is mature, and the outcomes are predictable when protocols are followed. What it won't do is replace fundamentals like caloric balance, protein intake, and regular physical activity. The clients who get the best results are the ones already doing the work and using this as an adjunct rather than a primary intervention.