Understanding Body Cavity Diagrams: What Actually Matters
Most anatomy resources show the same four or five diagrams repeated across textbooks. They work, but they leave out details that matter when you're actually working with real cases. Here's how to use them properly and where they fall apart.
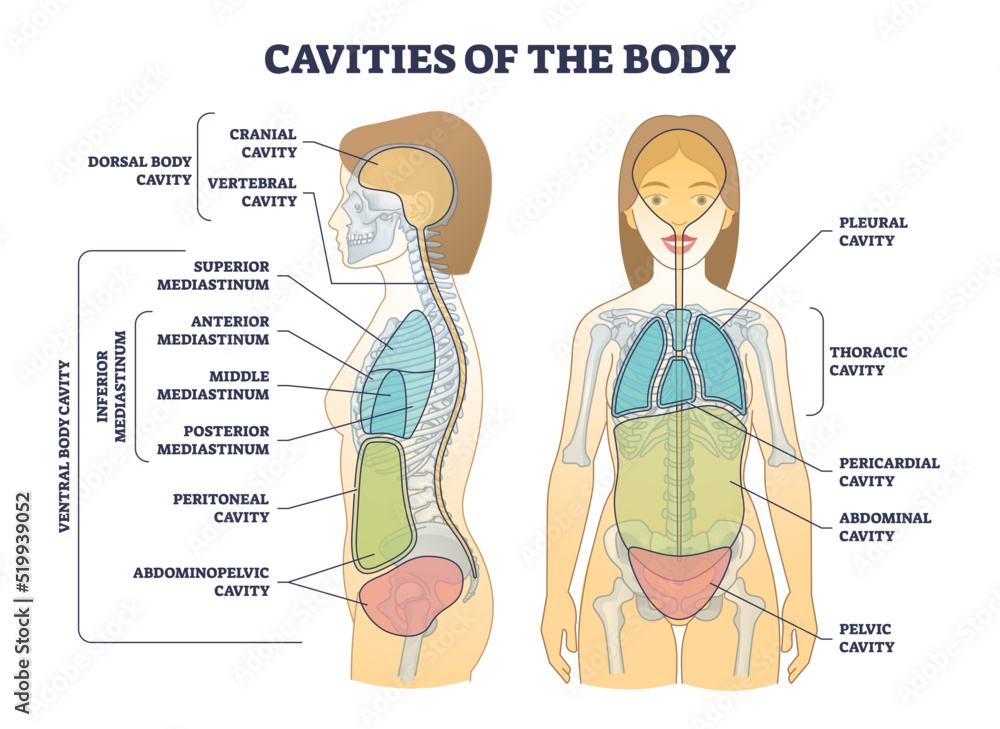
The Cavities Of The Body Diagram Explained
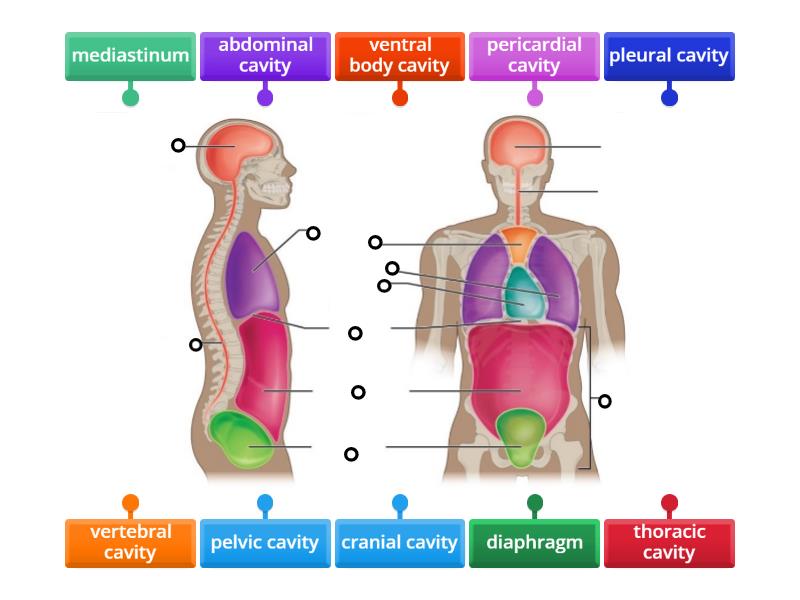
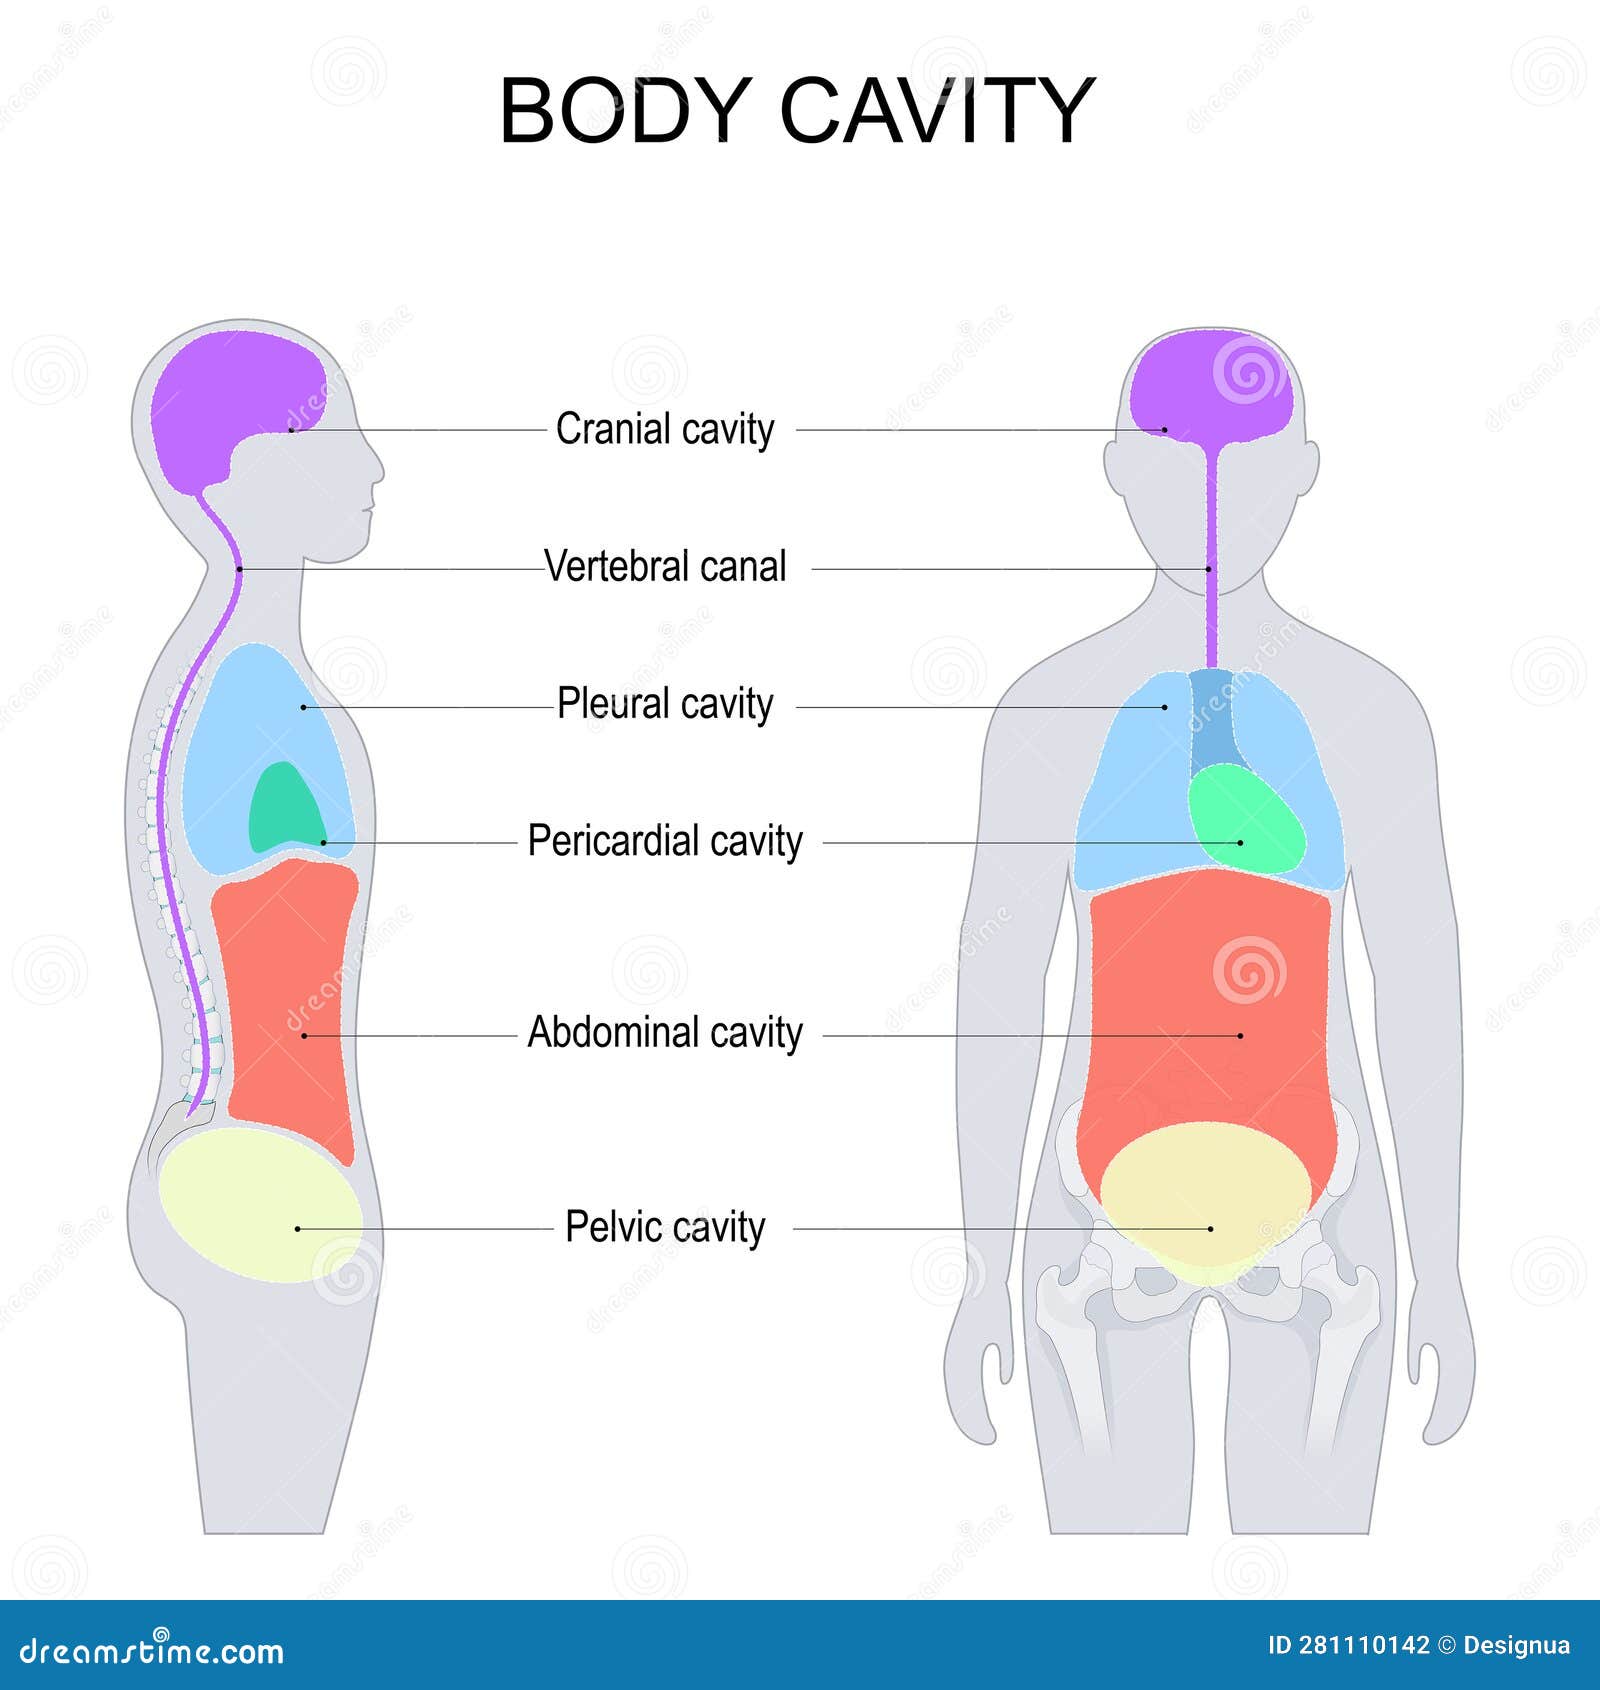
The body has two major groups of cavities: dorsal and ventral. The dorsal cavity contains the cranial and vertebral cavities, housing the brain and spinal cord. The ventral cavity splits into the thoracic and abdominopelvic cavities. Within the thoracic cavity, you have the pleural cavities around each lung, the mediastinum containing the pericardial cavity around the heart, and the small peritroneal space. The abdominal cavity holds the stomach, liver, intestines, and spleen, while the pelvic cavity contains the bladder, reproductive organs, and rectum.
That's the standard breakdown. It's accurate. It's also incomplete in ways that trip people up constantly.
I'll get into the complications in a moment. First, a note on terminology that causes more confusion than it should. In anatomy, the term "cavity" doesn't always mean an actual hollow space you could see with the naked eye. The abdominal cavity, for example, is a potential space. The organs press against each other and the abdominal wall, but there's fluid between them allowing movement. When you look at a diagram showing empty space between organs, that's schematic, not literal. Real CT scans and dissections show organs packed much tighter than textbook illustrations suggest.
This distinction matters when you're trying to trace a pathology from a cavity diagram to actual imaging. If you expect to see the clean separation shown in every diagram, you'll misread ultrasound and MRI images repeatedly.
A real example: I was reviewing a case where a diaphragmatic hernia had pushed loops of bowel into the thoracic cavity. The student on rotation immediately identified it on the X-ray because they'd been taught to expect the abdominal contents to stay below the diaphragm line, as every diagram shows. The cavity diagram never mentions that the diaphragm can fail as a boundary. The hernia sat right where the diagram told them nothing should exist, and for about two minutes nobody spotted it because the textbook mental model overrode what the image was actually showing. After that, I started telling everyone to look at the real imaging first and use the diagram only as a reference framework, never as an expectation.
How to Read These Diagrams Without Getting Fooled
The first thing to understand is that most body cavity diagrams you'll encounter come from one of two traditions: the gross anatomy tradition and the clinical radiology tradition. They serve different purposes and they look different even when they're showing the same thing.
Gross anatomy diagrams prioritize clarity. They show organ positions, boundaries, and relationships in an idealized subject. Labels point directly at structures. Lines separate compartments cleanly. These are useful for learning terminology and spatial relationships.
Clinical diagrams prioritize accuracy over readability. They show what radiologists and surgeons actually see, which means organs overlap, boundaries are fuzzy, and the diagram needs annotations just to tell you which structure is which. These take longer to study but transfer better to real work.
When I need to study a cavity diagram, I start with the clinical version, then check the gross anatomy version to lock down the labels. Going the other direction usually means memorizing pretty pictures that don't map well onto actual scans.
The ventral cavity is where most people struggle, and it's not because the anatomy is hard. It's because the subdivisions overlap in ways that diagrams rarely make clear. The peritoneal cavity, for instance, isn't a single chamber. It's divided into the greater and lesser sacs by the omentum, and the lesser sac communicates with the greater sac through the epiploic foramen of Winslow. Most basic diagrams skip this entirely or show it as a tiny footnote. If you're studying for exams, you need that detail. If you're reading imaging, you need it even more, because a pancreatic pseudocyst tracking into the lesser sac is a common complication that follows exactly that pathway.
Common Mistakes and What to Do About Them
People consistently confuse the mediastinum with the thoracic cavity. The thoracic cavity is the entire space inside the rib cage. The mediastinum is the central compartment within it. The rest of the thoracic cavity on either side of the mediastinum contains the pleural cavities and lungs. Diagrams often label the whole thing "thoracic cavity" without making this distinction clear, which causes errors when you're trying to localize a mass or effusion.
Another persistent issue is the difference between the peritoneal cavity and the abdominal cavity. The peritoneal cavity is the potential space lined by peritoneum. The abdominal cavity is the larger anatomical region that includes both the peritoneal cavity and the organs within it. On a diagram, they're drawn as the same area. In practice, knowing which space a pathology occupies determines whether it's intraperitoneal or retroperitoneal, which completely changes the clinical approach.
Retroperitoneal structures include the kidneys, adrenal glands, pancreas, duodenum (most of it), ascending and descending colon, and the aorta and inferior vena cava. These sit behind the peritoneum and aren't inside the peritoneal cavity at all. When a retroperitoneal tumor grows, it pushes the peritoneum and intraperitoneal organs forward, which changes how it appears on imaging compared to an intraperitoneal mass. Diagrams that don't explicitly show the posterior position of these organs make this distinction invisible.
Where Cavity Diagrams Break Down Completely
The biggest limitation is that they're static. They show one position, one body type, one state of health. Real bodies move. Organs shift position with respiration, posture, and pathology. The liver drops lower in deep inspiration. The stomach can distend to hold over a liter of content, pushing the transverse colon downward. A massively enlarged spleen can occupy the entire left upper quadrant and push the left kidney inferiorly and posteriorly. None of this is reflected in a standard diagram.
Second, they don't show vascular relationships clearly. The relationship between the splenic artery and the pancreas is clinically critical because pancreatic surgery involves controlling that vessel, but most cavity diagrams either omit the vasculature or place it generically. You need a separate vascular diagram to understand that relationship properly.
Third, and this is the one that costs people the most, cavity diagrams rarely show the fascial planes. The fascial planes are what actually separate compartments in the body. They're the boundaries surgeons follow and the pathways infections and tumors use to spread. A retroperitoneal abscess doesn't respect the "abdominal cavity" boundary on your diagram. It tracks along fascial planes into the pelvis, the flanks, or even up into the thorax. Understanding where those planes are matters more for clinical work than knowing which organs sit in which cavity.
If you're studying from diagrams alone, supplement them with cross-sectional anatomy atlases and, if possible, actual CT or MRI studies. The diagrams give you the framework. The scans give you the reality. Combining both cuts the time needed to translate diagram knowledge into imaging literacy significantly. I've seen people spend weeks trying to connect their textbook diagrams to real scans because nobody told them to just look at actual imaging alongside the diagrams from day one.
Gallery Cavities Of The Body Diagram
Poster Cavities of body and anatomical compartment medical division outline diagram – Muurposter ...
Identify the body cavities - Labelled diagram
Body Cavities Diagram With Organs
Body cavities labeled organs membranes definitions diagram and lateral view – Artofit
Body Cavities Diagram | Quizlet