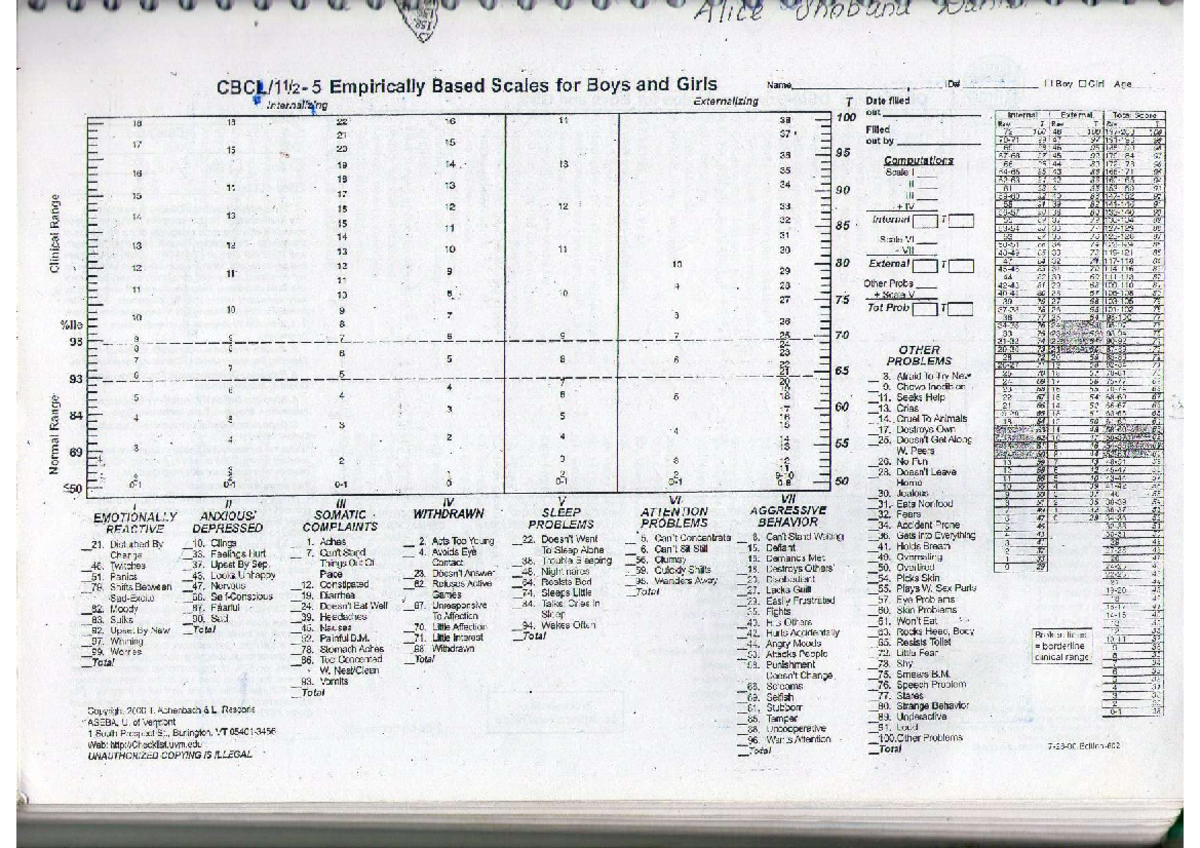
Scoring the CBCL Without Losing Your Mind
The CBCL — Child Behavior Checklist — is one of the most widely used instruments in child clinical assessment. Achenbach developed it, and it has gone through several revisions. The current version most people use is the CBCL/1½-5 and CBCL/6-18, along with the youth self-report form and teacher report. Each version comes with its own scoring manual. If you're doing this work, you'll find yourself constantly returning to it. Here is how the actual scoring process works in practice, not the version you would read in a textbook.
CBCL Scoring Manual
Each item on the checklist is rated by a parent, caregiver, or teacher on a three-point scale: 0 for not true, 1 for sometimes or sometimes true, and 2 for often or very true. You take those raw responses and feed them into a scoring algorithm. The algorithm produces syndrome scales, DSM-oriented scales, and broader broadband scales. The broadband scales are the Internalizing, Externalizing, and Total Problems composites. Those are the numbers people look at first, and they are also the numbers people misinterpret most often. Scoring is not done by hand unless you enjoy unnecessary suffering. Most people use the computerized scoring system through the XLORE database or the Achenbach System of Empirically Based Assessment (ASEBA) server. You enter the raw data, the system spits out T-scores, and you compare those T-scores against normative tables provided in the manual. A T-score of 60 to 63 is considered borderline. Anything above 63 is in the clinical range. These cutoffs are based on norm-referenced samples, so they shift depending on which norms you are using. The norm groups are age-specific and gender-specific. This sounds obvious but I have seen people use the wrong norm group because they mixed up the child's birth month or misidentified the gender category. One time a research assistant scored a boy's results using the female normative table. He got a totally different profile. It took me forty-five minutes to trace the error. I still keep a simple checklist now: verify age, verify gender, verify form version before entering a single item. That prevents most basic mistakes.
One edge case that comes up more than you might expect involves missing items. The manual gives specific rules for how many items can be missing before a scale becomes unscorable. For the syndrome scales, up to about half of the items in a subscale can be missing and you can still compute a valid score by prorating. But if too many are missing, or if the missing items cluster in one area, proration inflates the score or creates a false picture. I had a case where a caregiver skipped every item under the Somatic Complaints scale. Prorating filled it with zeros and the child appeared to have zero physical symptoms. That was not realistic. Instead of prorating, I flagged the entire scale as unreliable and moved on to clinical interview data. The manual technically allows proration, but allowing it does not mean it is always appropriate. Another thing people miss is that the DSM-oriented scales are not independent diagnoses. They map onto DSM diagnostic categories, yes, but a T-score above 65 on the Anxiety Problems scale does not mean the child meets criteria for an anxiety disorder. It means the parent checked enough anxiety-related items to push the score into the elevated range. Clinical interpretation requires matching patterns across multiple scales, not looking at one score in isolation. A high Externalizing score paired with a high Aggressive Behavior subscale tells a different story than a high score on just the Rule-Breaking Behavior subscale. The manual explains this, but it gets buried in pages of normative tables. There are legitimate limitations to the CBCL that the manual does not emphasize enough. It is a parent-report instrument. Parent perception is shaped by the parent's own mental health, stress level, cultural background, and relationship with the child. Two parents can look at the same child and produce meaningfully different CBCL profiles. There is also significant cross-informant discrepancy. Teacher reports and parent reports often agree only around 30 to 40 percent. That is not a flaw in the instrument, it is a feature of how behavior varies across settings. But beginners often treat the CBCL as if it produces an objective truth about the child rather than an informed report from one specific observer.
Get the Full Details

Another limitation is cultural validity. The original norming samples were predominantly White, middle-class American families. If you are administering the CBCL in a different cultural context, you are comparing a child against norms that may not reflect that context. Elevated scores may reflect cultural differences in behavior rather than psychopathology. Some researchers have developed culture-specific norms, but availability varies. If you are working outside the original norming population, you should note this as a limitation in any report you produce. The manual itself is quite dense. The Achenbach & Rescorla edition for the 6-to-18 age range runs over five hundred pages. Most of those pages are normative tables and scaling algorithms. You do not need to read it cover to cover. The scoring chapter and the interpretation chapter contain the essential material. Keep the manual nearby during initial scoring runs. After a few uses, you will memorize the major pathways. The rest is reference work. For the actual scoring software, ASEBA provides the computerized scoring service online. You create an account, upload your data, and receive scored profiles. The cost structure has changed over the years. Currently there is a fee per assessment, and institutional licensing is available for organizations that administer the CBCL regularly. The ASEBA website hosts all of this, and they also offer free demo versions for training purposes. If you are a student or a clinician in early practice, starting with the demo version saves money while you learn the interface.
A final practical note about the output. The computerized scoring generates a full profile report with graphs, T-scores, and percentile ranks. It is tempting to print that report and call it a day. It is not that simple. The report tells you what the scores are. It does not tell you why they are what they are. Always combine CBCL results with clinical interview, observational data, and when possible, collateral information from other informants. The CBCL is a screening and assessment tool, not a diagnostic endpoint.


