How CBT Worksheets Actually Work for Quitting
I've spent years watching people try to use cognitive behavioral therapy frameworks to quit smoking, and honestly, most of them use them wrong. Not because the approach is bad, but because the standard worksheets don't map cleanly onto the reality of nicotine withdrawal. Here's what I've learned from actually seeing this through. The PDFs themselves are everywhere. Free versions float around mental health sites, Reddit threads, and hospital wellness portals. The good ones come from established CBT practitioners like David Burns or the UK's NHS materials, which tend to be more clinically sound than the ones generated by content farms. When I'm recommending something, I usually point people toward the worksheets from Smokefree.gov or the ones used in Stop Smoking Services across the UK National Health Service. Those have been field-tested. The free downloadable versions I find most useful are the 7-session protocol from the American Psychological Association, which breaks down into identifiable modules: trigger identification, urge surfing, cognitive restructuring of smoking beliefs, and relapse planning. What most people don't realize is that the worksheet itself is only about ten percent of the intervention. The rest is the actual process of sitting with the discomfort while you fill it out.
The Method Behind the Blank Boxes
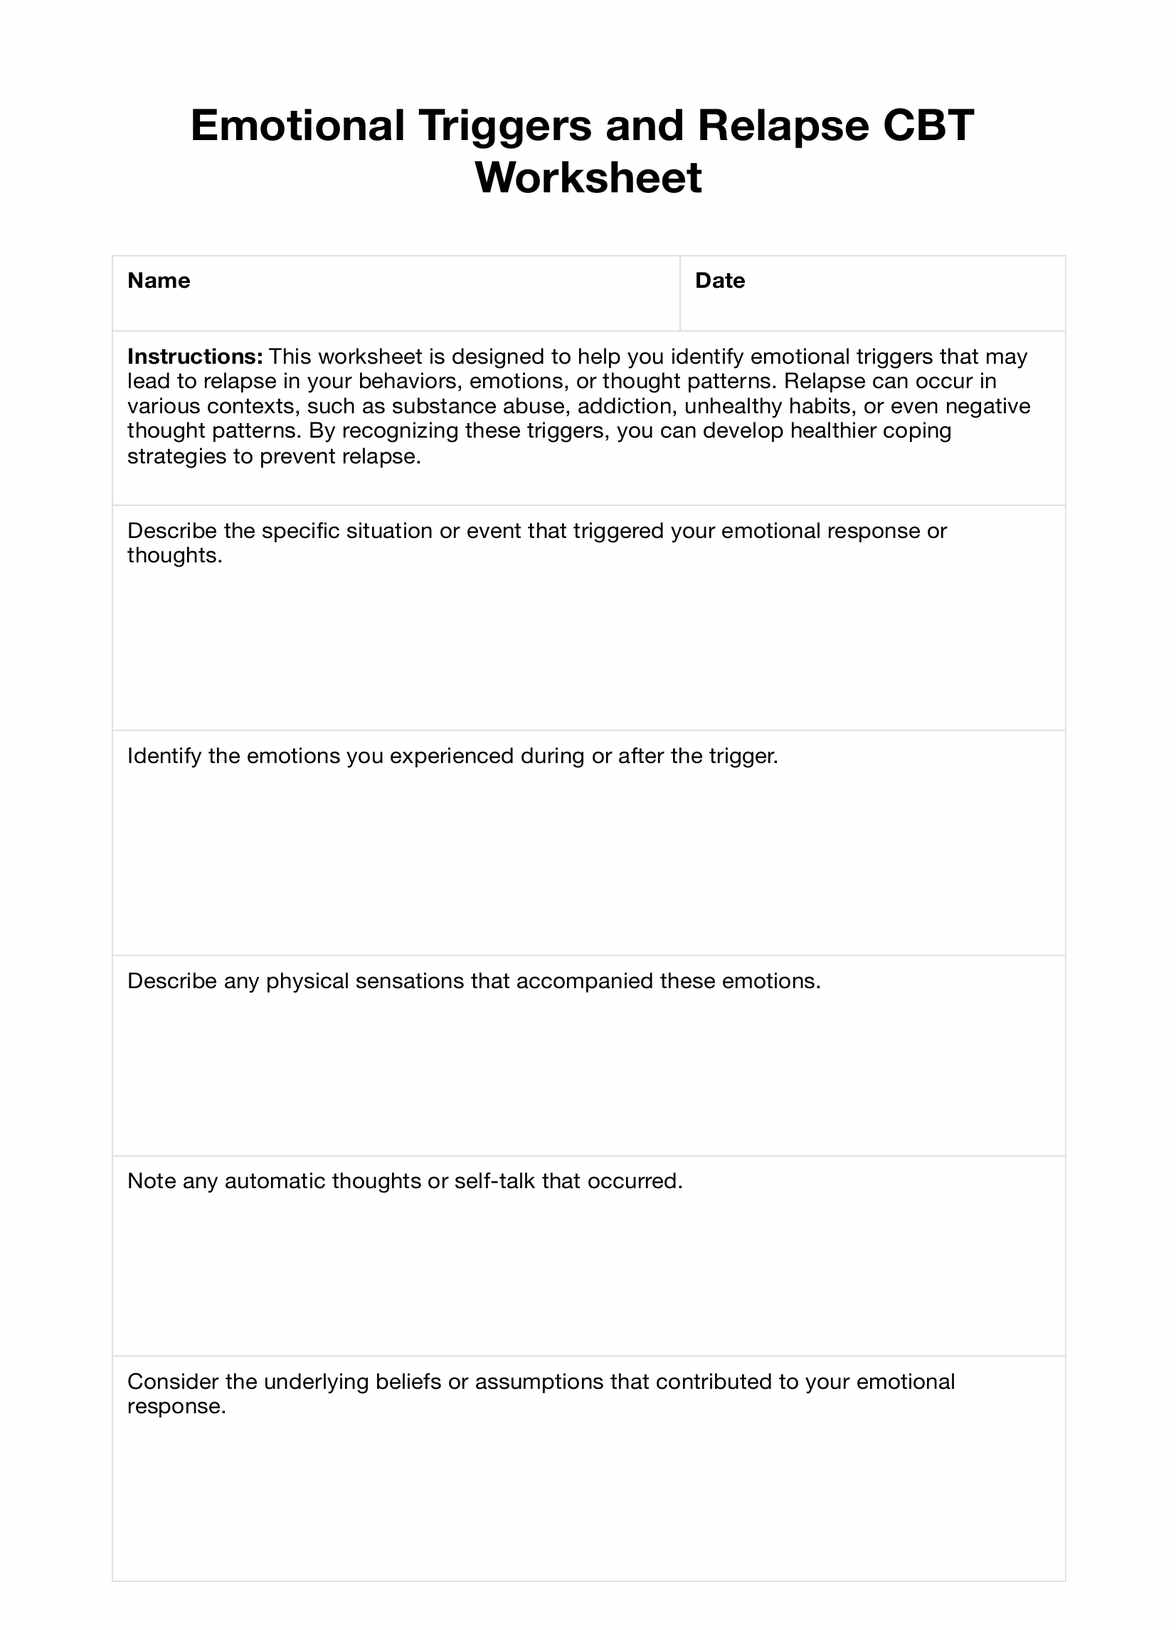
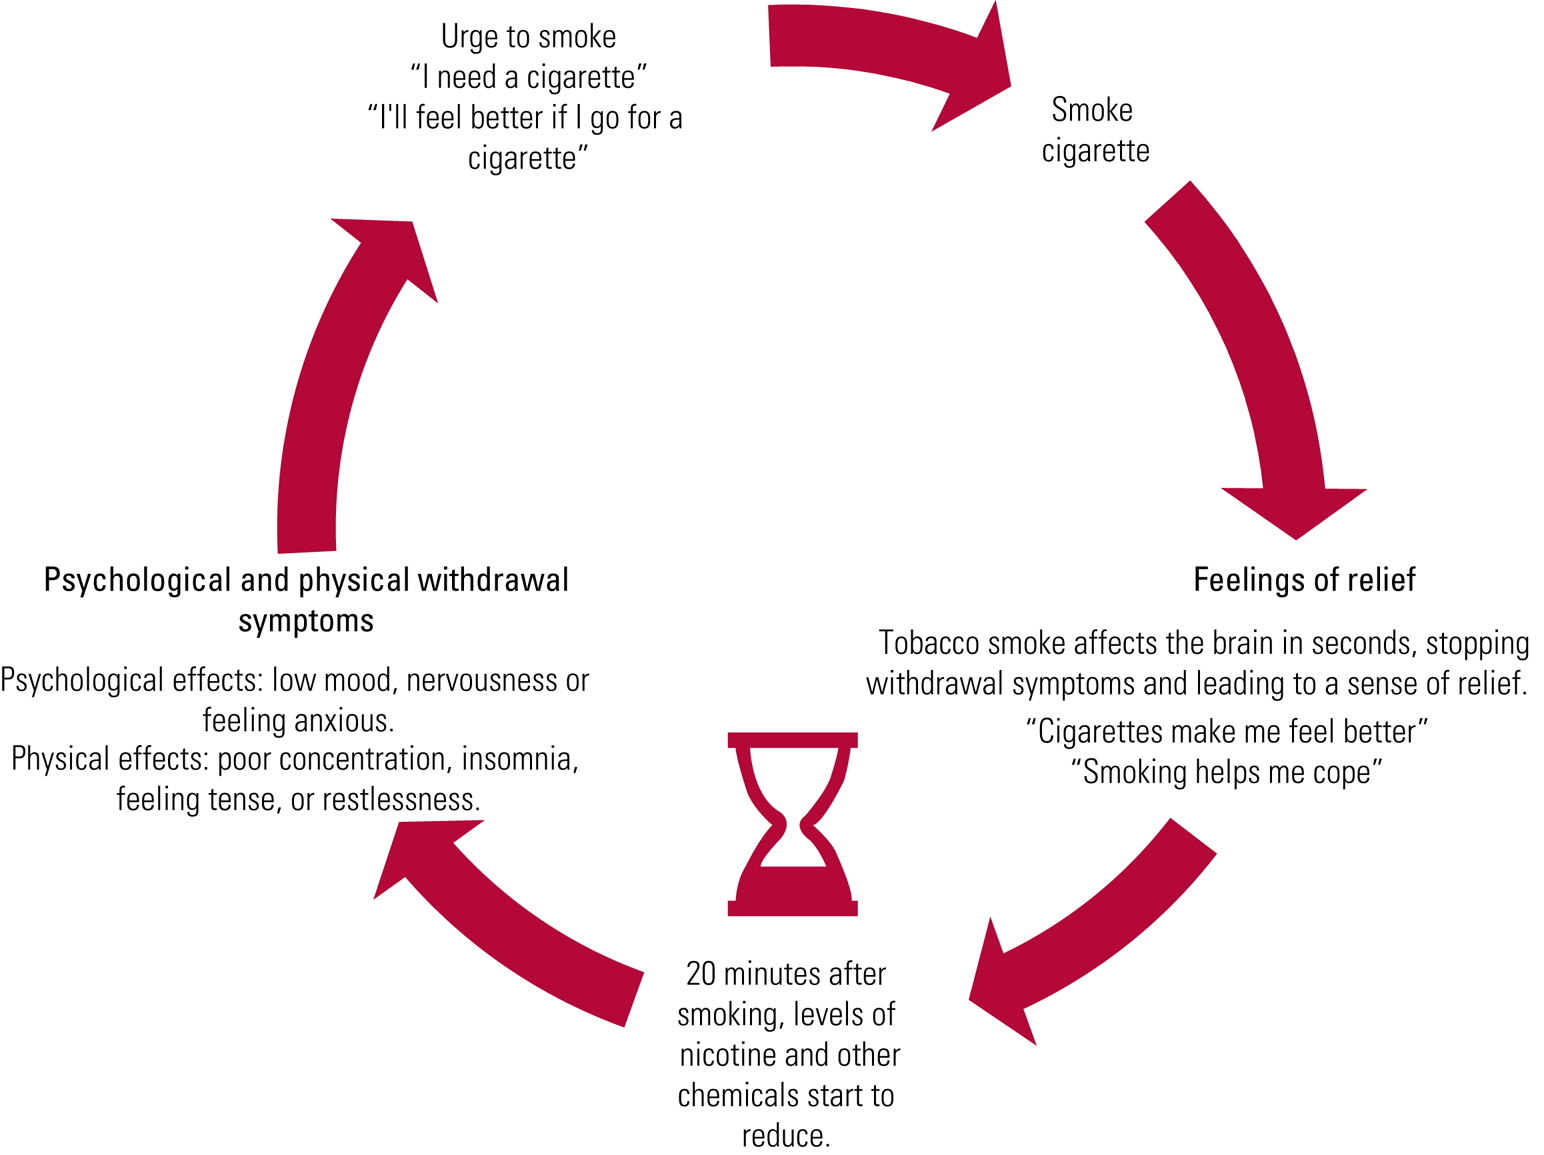
A CBT worksheet for smoking cessation typically asks you to do three things in sequence. First, log a smoking episode with every variable that existed around it: time of day, emotional state, location, what you were doing, and who was nearby. Second, rate the intensity of the urge on a zero-to-ten scale before and after any intervention you tried. Third, write down the automatic thought that preceded the cigarette and then deliberately challenge it with evidence for and against that thought. That third part is where it gets useful, but also where most people bail. The automatic thought is usually something like "I need this to handle stress" or "I've already had one, might as well finish the pack." The worksheet asks you to write evidence against that thought. For the "I need this to handle stress" one, the evidence against is straightforward: nicotine actually increases physiological arousal. Heart rate goes up. Cortisol spikes. The feeling of calm after a cigarette is the relief of withdrawal symptoms going away temporarily, not any actual stress reduction. Most people skip writing this out because it feels like arguing with yourself. That's the wrong way to think about it. You're not trying to win an argument. You're building a database of your own behavior patterns so you can see them objectively. I had a client once who filled out forty-three worksheets over eight weeks and never smoked fewer than two packs a week. The problem wasn't the worksheets. He was filling them out on autopilot, writing the same vague thoughts in every box. "Stressed at work" appeared in forty-two different entries. The worksheet was becoming a diary entry generator rather than a cognitive restructuring tool. The fix was simple but annoying: I made him use a different color pen for the challenge column each week, and he had to write at least three specific details in every trigger entry before moving on. Specificity forced engagement. Week two, he logged "Argument with Sarah at 2:14 PM, she mentioned the bills, felt trapped, lit up in the garage, smoked 4 cigarettes over 22 minutes." That kind of data actually changes how you see your relationship with smoking.
Counter-Intuitive Things Nobody Tells You
Here's something most beginners miss. The worksheets are least effective during the first two weeks of quitting. That's when withdrawal is sharpest and cognitive function is slightly degraded. Nicotine withdrawal impairs working memory and executive function, which means the very skill the worksheet demands—logically restructuring thoughts—is the skill withdrawal undermines most. The optimal window to really benefit from CBT worksheets is week three through week eight. By then, the acute physical symptoms have faded enough that your prefrontal cortex is back online and you can actually do the cognitive work properly. The second thing people get wrong is the order. Standard protocol says identify triggers first, then restructure thoughts. But for many smokers, trigger identification creates more anxiety than it prevents because suddenly you're hyper-aware of every moment you used to smoke and now you have to sit with that awareness. I've found it works better to start with cognitive restructuring of the core beliefs—specifically the identity-level belief that "I am a smoker"—before you even begin logging specific situations. If you haven't shifted the self-concept, the trigger logs just become a catalog of failures.
Get the Full Details
What These Worksheets Can't Do
CBT worksheets are a tool, not a treatment on their own. They're designed for people with mild to moderate nicotine dependence who are highly motivated. If you're drinking heavily, have a history of mood disorders, or your nicotine dependence is severe enough that you're smoking thirty or more cigarettes a day, worksheets alone will feel inadequate. The cognitive piece is only one part of addiction. There's a physiological dependency that CBT doesn't address. Pharmacological support like varenicline or bupropion changes the neurochemical landscape enough that the psychological work actually has room to operate. I also need to be blunt about something. CBT worksheets have a dropout rate that's not pretty. Studies show that about sixty percent of people who start a structured CBT program for smoking cessation don't complete it. The workbook format assumes a level of sustained motivation that most people don't have during the quit window. It also assumes you have the executive functioning to sit down and do detailed written reflection, which sounds trivial until you're at 10 AM on a Tuesday and your brain feels like it's packed with wet cotton because you haven't had nicotine in four hours. The worksheet isn't failing you. The expectation that you'd want to do it in that state is unrealistic. For people in that position, the alternative is simpler. Use the same framework but in a different format. Audio recordings of guided CBT sessions, smartphone apps with push-based prompting, or just a phone note app where you type raw thoughts without any structure. The mechanism matters more than the medium. What matters is the deliberate act of interrupting an automatic thought and examining it. How you capture that interruption is secondary.
A Practical Starting Point
If you're going to try the worksheet approach, here's the minimal version that actually works. Print or download a set of the standard CBT smoking templates. Start on a weekend when your schedule is light. Fill out one entry per day for the first week, even if it's just one line. Don't aim for completeness. Aim for showing up. The habit of looking at your smoking behavior with some distance is the actual intervention. The content of what you write matters less than the act of writing it. The worksheets you'll find linked on psychology today, the NHS website, and various smoking cessation forums follow the same general structure. Look for ones that include a section on urge surfing specifically, because that's the technique with the most empirical support for smoking cessation. David Archibald's work on urge surfing shows that urges follow a wave pattern—they peak and then subside within about fifteen minutes if you don't act on them. The worksheet forces you to track that pattern, which makes the wave predictable. Predictability reduces panic. Panic is what turns a minor discomfort into a relapse. I've seen people quit using nothing more than a notebook and a spreadsheet tracking their smoking times against their mood ratings. The formal worksheet is just a structured version of that. Don't let the format intimidate you into thinking you need the perfect template. You need the habit of observation. Everything else is just scaffolding.