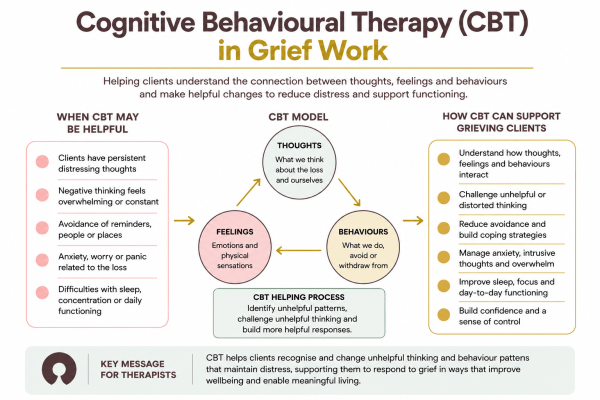
A Practical Guide to Using CBT When You're Dealing With Grief
Cognitive Behavioral Therapy works differently for grief than it does for most other issues people bring into the room. The standard CBT model assumes you can identify a cognitive distortion, challenge it with evidence, and replace it with something more balanced. Grief doesn't play by those rules. You can't logically argue your way out of missing someone who's dead. I've seen people try, and it usually just makes them feel worse and more broken. The version of CBT that actually helps with grief tends to be more behavioral activation combined with selective cognitive reframing. You're not trying to eliminate the sadness. You're trying to keep the person functioning enough that the sadness has somewhere to go without consuming every other part of their life.
Cbt Therapy For Grief And Loss
The protocol I rely on most starts with a grief timeline and a behavioral schedule. The client writes out the major events surrounding the loss—the diagnosis, the death, the funeral, the first empty anniversary, the first time they went to a grocery store alone and had to make a decision about milk. This sounds simple but it reveals patterns most people miss. Some clients realize their worst days aren't the anniversary but three weeks later, when the initial support network disappears and the silence hits. Other clients discover that their panic attacks correlate with specific triggers like hearing a certain song or walking into a room that still smells like the deceased. Once you have that data, you build a weekly schedule. Not a productivity schedule. A schedule that includes at least one small action that is neutral or mildly positive each day, and one scheduled grief period where the person allows themselves to fully feel whatever is there. The second part is non-negotiable. Suppressing grief until it leaks out uncontrollably is how people end up in crisis six months after the fact. I tell clients to set a 30-minute block, maybe twice a week, where they look at photos, write letters they'll never send, or just sit and cry. Outside that block, when a grief wave hits, they acknowledge it and defer it: "I'll deal with this during my 4pm grief block." This isn't avoidance. It's containment. It prevents the person from spending every waking hour in emotional chaos while still giving the grief regular attention. The cognitive piece focuses on meaning-making rather than restructuring. Standard CBT would challenge a thought like "my life is over" by asking for evidence. With grief, that approach is almost cruel and mostly ineffective. Instead, I use a modified schema approach. The loss has disrupted the person's core beliefs about safety, continuity, and purpose. The work is gradual and involves rebuilding a narrative where the person can still imagine a future that includes the loss without being destroyed by it. It's slower than treating depression with CBT. Expect six to twelve sessions minimum for meaningful shift, though simple acute grief cases can see improvement in four to six.
One specific edge case that trips people up involves guilt-driven rumination. A client lost a parent to cancer and couldn't stop cycling through memories of arguments, missed visits, or small resentments. The standard cognitive triangle would label this all-or-nothing thinking and try to reframe it. That didn't work for months. The client needed a completely different mechanism: I introduced a guilt inventory exercise. They wrote down every instance of guilt they could think of, and for each one, they had to write what evidence supported it and what evidence contradicted it, then assign a percentage of truth. Not a binary yes or no. A percentage. This forced the brain out of absolute statements and into nuance. After about eight entries, the average guilt rating dropped from 90 percent certainty to roughly 35 percent. The grief didn't disappear. The guilt lost its coercive power. That's a technique worth keeping in your toolkit if you're working with complicated grief specifically. Common pitfalls to watch for. Therapists sometimes push cognitive restructuring too early in the grief process. The person is still in the acute phase where emotions are raw and unprocessed. Pushing them to "challenge negative thoughts" at this stage reads as dismissive and damages the therapeutic alliance. Wait until the initial shock subsides, usually three to six weeks post-loss, before introducing structured cognitive work. Also, don't mistake numbing behaviors for coping. Clients who switch to heavy exercise, workaholism, or substance use might appear functional on the surface. They're not. The behavioral activation component of CBT should explicitly address these substitutes and help replace them with healthier engagement patterns. Another mistake is treating all grief the same. Anticipatory grief, where the loss was expected, has a completely different trajectory than sudden loss. People going through anticipatory grief often have already begun some internal processing before the death occurs. Their grief tends to be less complicated but longer lasting in a low-grade form. Sudden loss clients may experience more acute symptoms initially but can integrate the loss faster if they have adequate support. Your CBT approach should reflect this difference. With anticipatory grief, focus more on continuation of relationship themes. With sudden loss, behavioral activation and grounding techniques tend to be more immediately useful.
Get the Full Details

The biggest limitation of CBT for grief is that it doesn't work well for prolonged grief disorder when it's entrenched. If someone has been stuck in intense grief for over a year with significant impairment in daily functioning, CBT alone often falls short. In those cases, Complicated Grief Treatment (CGT), also called Prolonged Grief Therapy, has stronger evidence. It combines exposure-based techniques with meaning-making and is specifically designed for this population. If you're a therapist and you notice a client isn't progressing after six to eight sessions of standard CBT, consider whether they might benefit from a CGT framework instead. The good news is that elements of both approaches can be blended if needed. For self-guided work, the basics are straightforward enough that structured workbooks exist and are generally adequate. The key is consistency. Doing the behavioral activation and cognitive exercises sporadically produces almost no benefit. Thirty minutes a day, five days a week, is where results show up. The guilt inventory I described earlier can be done alone with a notebook. The grief timeline works fine as a solo exercise. What you can't do alone effectively is the deeper schema work around meaning reconstruction. If you're doing this solo and you hit a wall where the same negative thoughts loop without any shift after two to three weeks, that's a sign you need a trained therapist, not a better workbook. The research on CBT for grief is reasonably solid. Multiple randomized controlled trials show moderate effect sizes, particularly when the protocol includes both behavioral and cognitive components rather than either alone. The effect sizes are smaller than for depression or anxiety, which makes sense given that grief is a normal human response rather than a pathology. You're not trying to cure grief. You're trying to prevent it from becoming disabling. That's an important distinction that affects how you measure success and how long you should expect treatment to take.
I also want to mention something that isn't covered in most manuals. Cultural context matters enormously. In some cultures, prolonged expressive grief is normative and supported by the community. In others, stoicism is expected. A client from a culture that values emotional restraint might respond better to a more structured, skill-based CBT approach. A client from a culture where grief expression is communal might benefit more from integrating group support and narrative techniques alongside the cognitive work. The protocol isn't one-size-fits-all, and pretending it is does a disservice to clients from diverse backgrounds. If you're looking for resources, the Beck Institute website has worksheets and guides specifically adapted for grief. There are also several peer-reviewed protocols available through academic databases if you want the full treatment manuals rather than consumer-friendly versions. For most people reading this, a structured self-help workbook like "Rewriting the Grief Story" by Deborah Carr or "The Grief Recovery Handbook" by John Bufferd will cover the essential components adequately. The workbook alone won't replace therapy for complicated cases, but it's a legitimate starting point for straightforward grief responses. The bottom line is that CBT can help with grief, but it's not a magic bullet and it requires adaptation to work properly. The standard depression protocol needs modification. The behavioral activation component does most of the heavy lifting in the early stages. The cognitive component becomes more relevant as the acute shock wears off. And when grief has become chronic and complicated, other evidence-based approaches outperform standard CBT. Knowing when to use which tool is what separates competent grief work from mediocre grief work.




