Understanding the CELF-5 Scoring Process
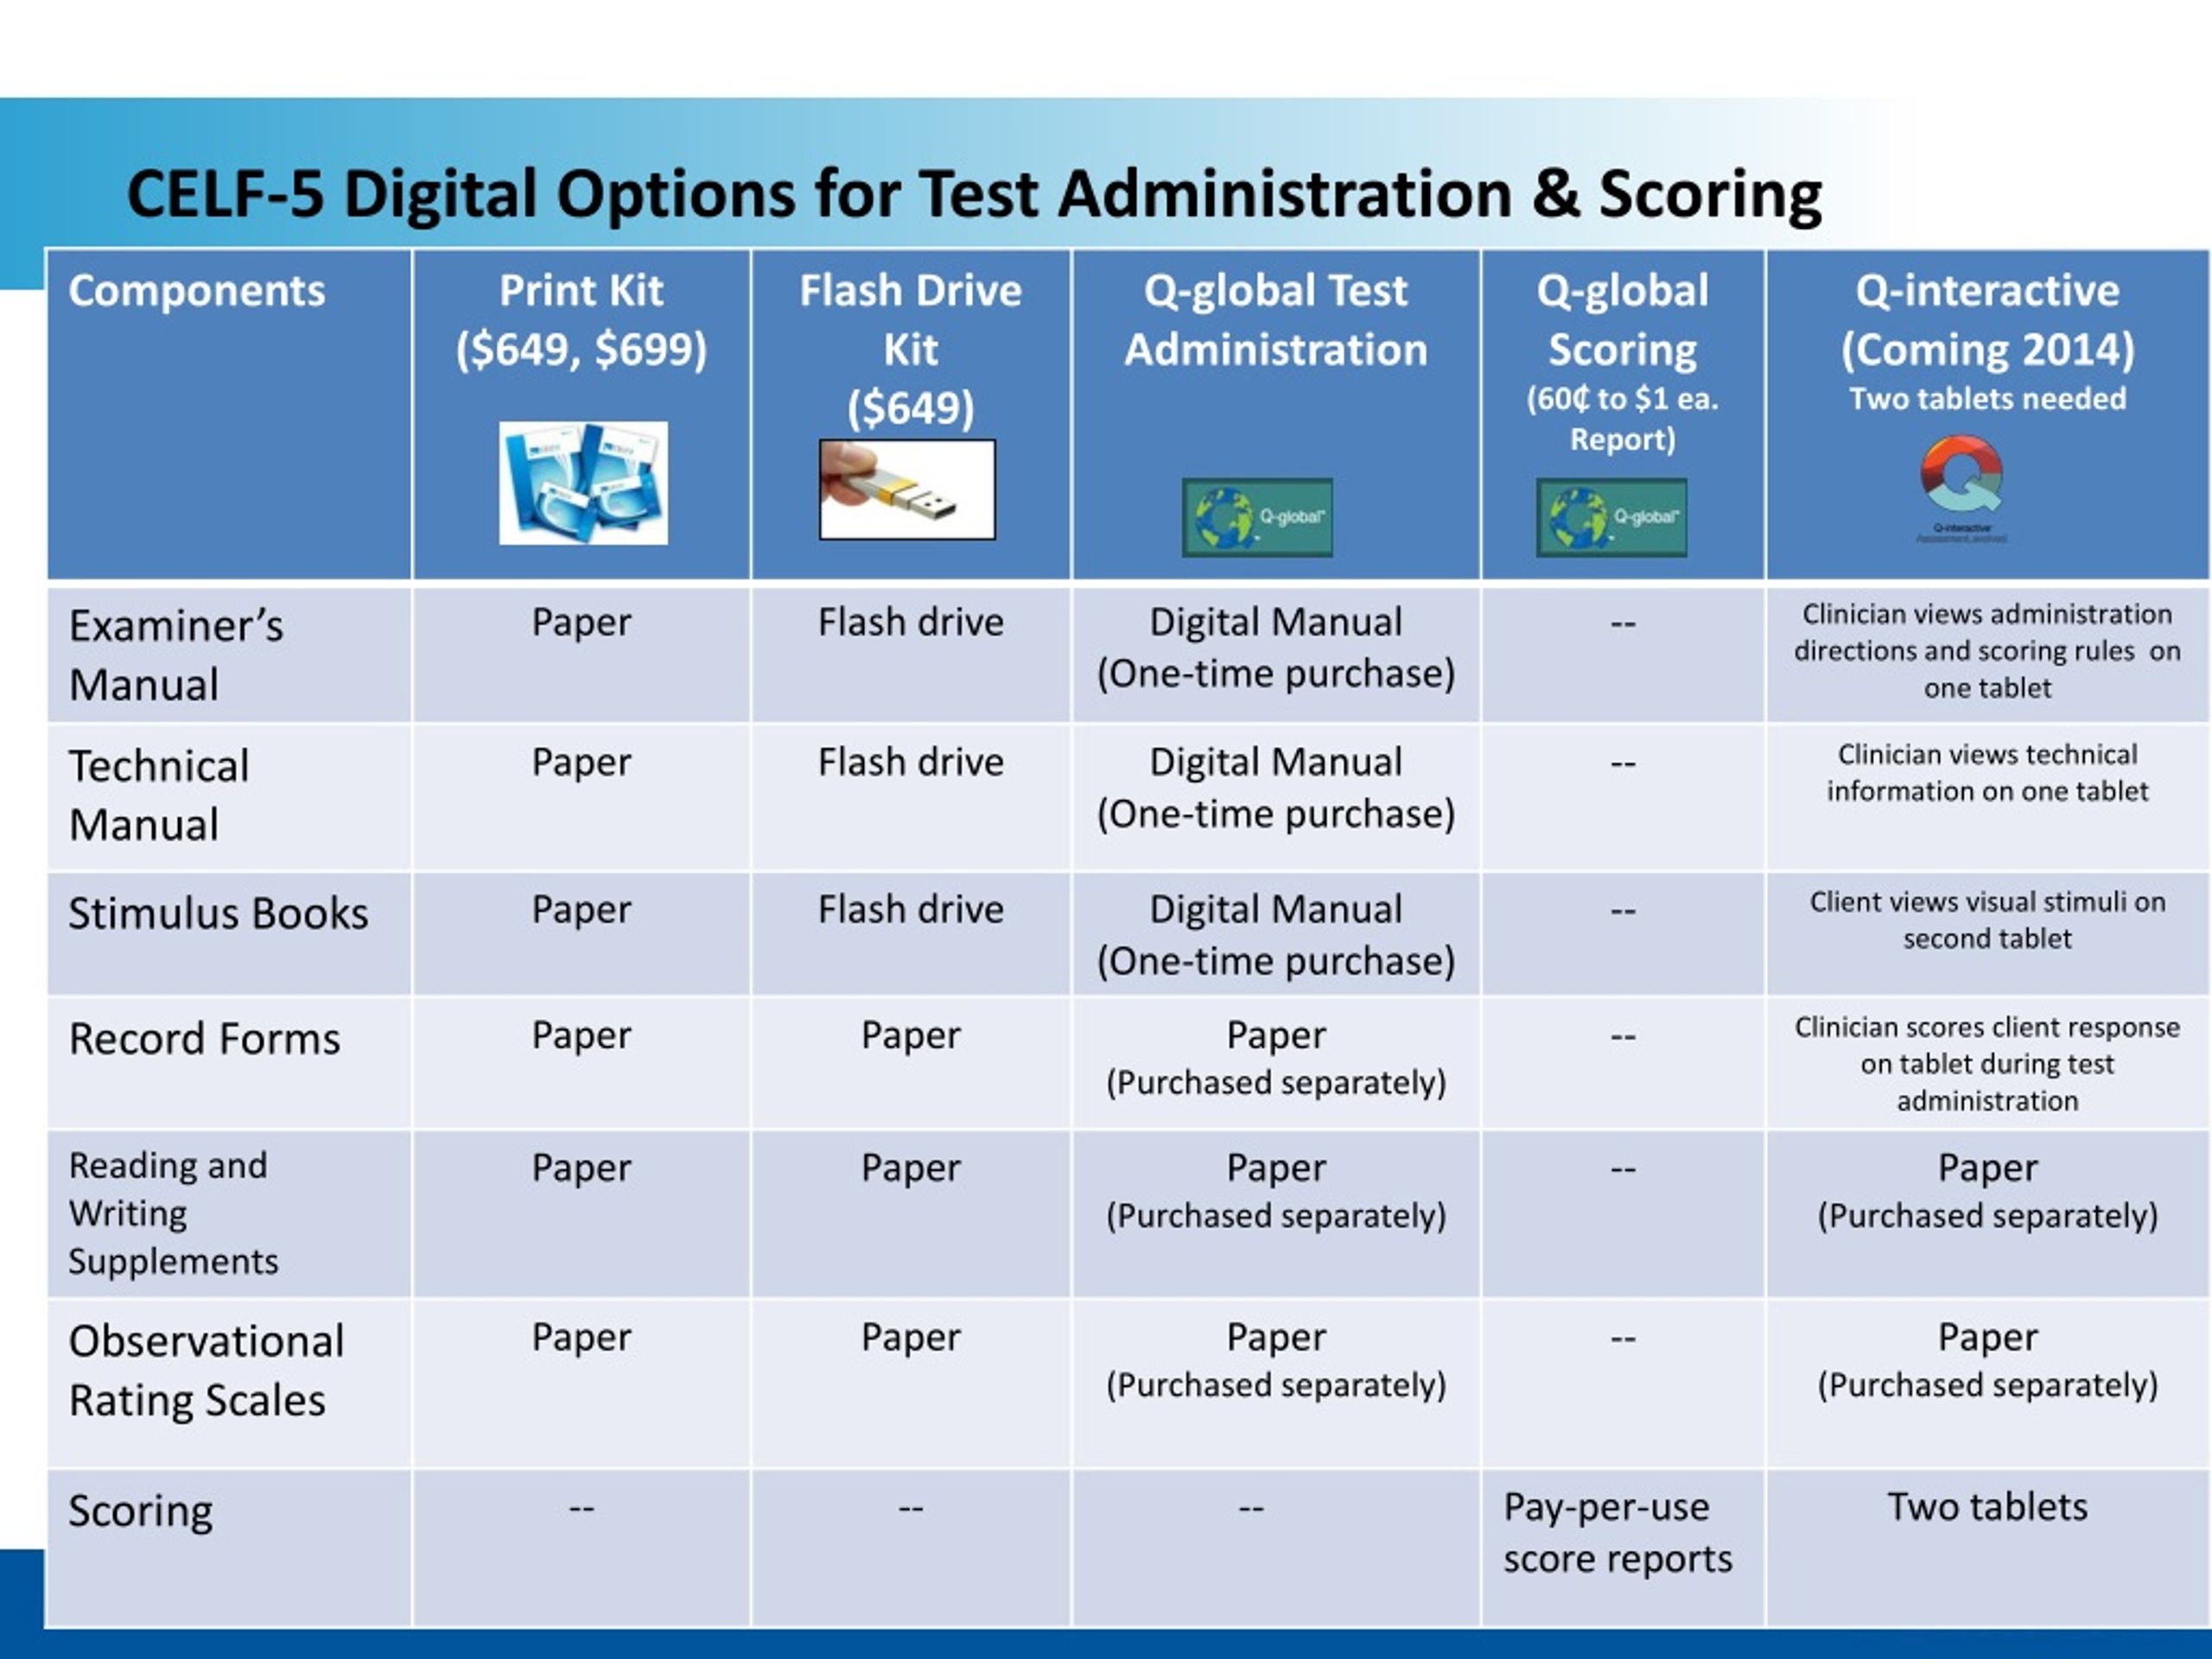
The CELF-5 is the fifth edition of the Clinical Evaluation of Language Fundamentals, published by Pearson. It measures language skills in individuals aged 5 through 21 years. The scoring manual walks you through how to convert raw responses into standard scores, percentile ranks, and clinical classifications. Most people looking for a Celf 5 Scoring Manual Online are SLPs, graduate students, or school-based clinicians who need to administer and interpret this assessment correctly. The manual itself is dense, and the scoring tables span dozens of pages. Getting it right matters because the scores drive eligibility decisions in schools and treatment planning in clinics. Here is how the scoring actually works from a practical standpoint. You administer the subtests, tally the raw scores, then look them up in the manual's norm tables. The norm table accounts for age and sometimes gender. You get a standard score with a mean of 10 and a standard deviation of 15. Scores below 80 fall in the low average to below average range. Scores above 120 are well above average. The core language composite pulls together several index scores, and the language score index is the one most commonly used for diagnostic purposes. A quick note: the CELF-5 uses three different age bands, and the subtest battery changes slightly depending on whether the client is 5-7, 8-13, or 14-21. Mix those up and your composite score will be wrong. I ran into a specific problem last year that took me about two hours to track down. I was scoring a 12-year-old client and the Core Language Score kept coming out lower than I expected based on the raw numbers. I went back through every step, recalculated twice, and even checked the norm table against the printed manual. Nothing matched. The issue turned out to be the Oral Directions subtest. For the 8-13 age band, Oral Directions is included in the Language Score Index. But if the examinee was on the upper end of the band, Pearson's scoring software sometimes flags it differently than the manual suggests, and the manual's footnote on page 87 explicitly states that Oral Directions should be excluded from the index for clients whose expressive/receptive language profiles are uneven by more than 10 points. I had missed that footnote on my first read. The workaround was straightforward: I re-scoped the index, dropped Oral Directions, recalculated, and the resulting Language Score Index jumped by seven points, which changed the clinical interpretation entirely. Always read the footnotes in the manual carefully before locking in a composite score.
Common Pitfalls in CELF-5 Scoring
There are a few things that go wrong repeatedly. The first is using the wrong norm table for the client's exact age. CELF-5 norms are (month-of-age) based in some tables, so a client who is 8 years and 11 months should not be scored using the 8-year-old row if the table distinguishes between months. Pearson provides month-specific tables in the manual, and they are non-negotiable for accurate scoring. The second pitfall involves the Listening Comprehension subtest. This subtest has two parts: Auditory Closure and Spelling Words. Some clinicians score only Auditory Closure and forget that Spelling Words is required for the index score. If Spelling Words is omitted, the Listening Comprehension index is invalid, and any composite that includes it should not be reported. The third is misunderstanding the difference between the Language Score Index and the Core Language Score. The Language Score Index uses five subtests. The Core Language Score uses a different subset and is the broader measure. Confusing the two leads to incorrect reporting in evaluation reports. I have seen both errors in actual clinical documents, and neither is subtle.
Scoring Workflow That Works
Here is a straightforward process that saves time and reduces errors. First, record raw scores directly on the record form as you administer each subtest. Do not rely on memory to fill in scores later. Second, after administration, verify that the client's age falls within the tested band and that all required subtests were completed. Third, use the norm table for the exact age and month. Fourth, cross-reference any calculated composite score against the manual's example tables. Pearson includes worked examples at the end of the manual, and they are useful for sanity-checking your math. Fifth, document every step, including which norm table version you used and any exclusions applied, so another clinician can replicate your scoring if needed. Using the Celf 5 Scoring Manual Online does cut down on lookup time compared to flipping through the printed version, but the online versions I have seen vary in accuracy. Some are scanned copies with poor resolution on the tables. Others are third-party summaries that omit footnotes and exclusions. I recommend sticking to the official Pearson version whenever possible, because the footnotes contain the exceptions that matter most for clinical interpretation.
Get the Full Details

What the Scores Actually Mean
A standard score of 80 is the cutoff between low average and below average. A score of 70 and below is clinically significant and typically indicates an language disorder. The percentile rank gives you the percentage of same-age peers who scored at or below the client's score. A percentile of 12 means the client performed better than or equal to 12 percent of peers. The percentile and standard score do not map linearly, which is why you need the conversion table rather than estimating. One counter-intuitive point that beginners often miss: a client can have a significant deficit on one index but a statistically average score on the Core Language Score, and still qualify for services. The discrepancy between indices is clinically meaningful. Pearson's own interpretive guidelines note that index scatter of 15 points or more warrants further investigation regardless of the composite score. I have seen this happen frequently in school evaluations where a child with a strong receptive vocabulary but a weak narrative structure score was denied services based solely on the composite. The composite was 88, which looks borderline, but the index scatter told a different story. The manual's scoring section does mention scatter analysis, but it is easy to overlook if you are focused on getting the composite number quickly.
Limitations and When It Fails
The CELF-5 scoring system is reliable when used correctly, but it has known limitations. The norm sample was collected in 2019, so results may not reflect current demographic shifts. The test assumes standard administration conditions, and deviations from those conditions can invalidate scores. If a client was fatigued, distracted, or had hearing difficulties during administration, the scores may not accurately reflect true ability, and the scoring manual cannot correct for that. In those cases, the manual recommends supplementary assessment rather than forcing a score interpretation. Another limitation is the ceiling effect. Clients with higher language abilities tend to hit the ceiling on multiple subtests, which compresses the score distribution and makes it harder to differentiate among high-performing individuals. The CELF-5 has extended norms, but they are not always practical in a school setting due to time constraints. If you are working with gifted populations, consider supplementing with a different instrument rather than relying solely on CELF-5 ceiling extensions.
Bottom Line
Score the CELF-5 methodically, verify every age-band selection, read the footnotes, and don't let a composite score blind you to index scatter. The manual is thorough but not forgiving of shortcuts. Take your time with the norm tables and double-check your exclusions. That is where most scoring errors originate.