Understanding Celiac Disease Testing: What You Actually Need to Know
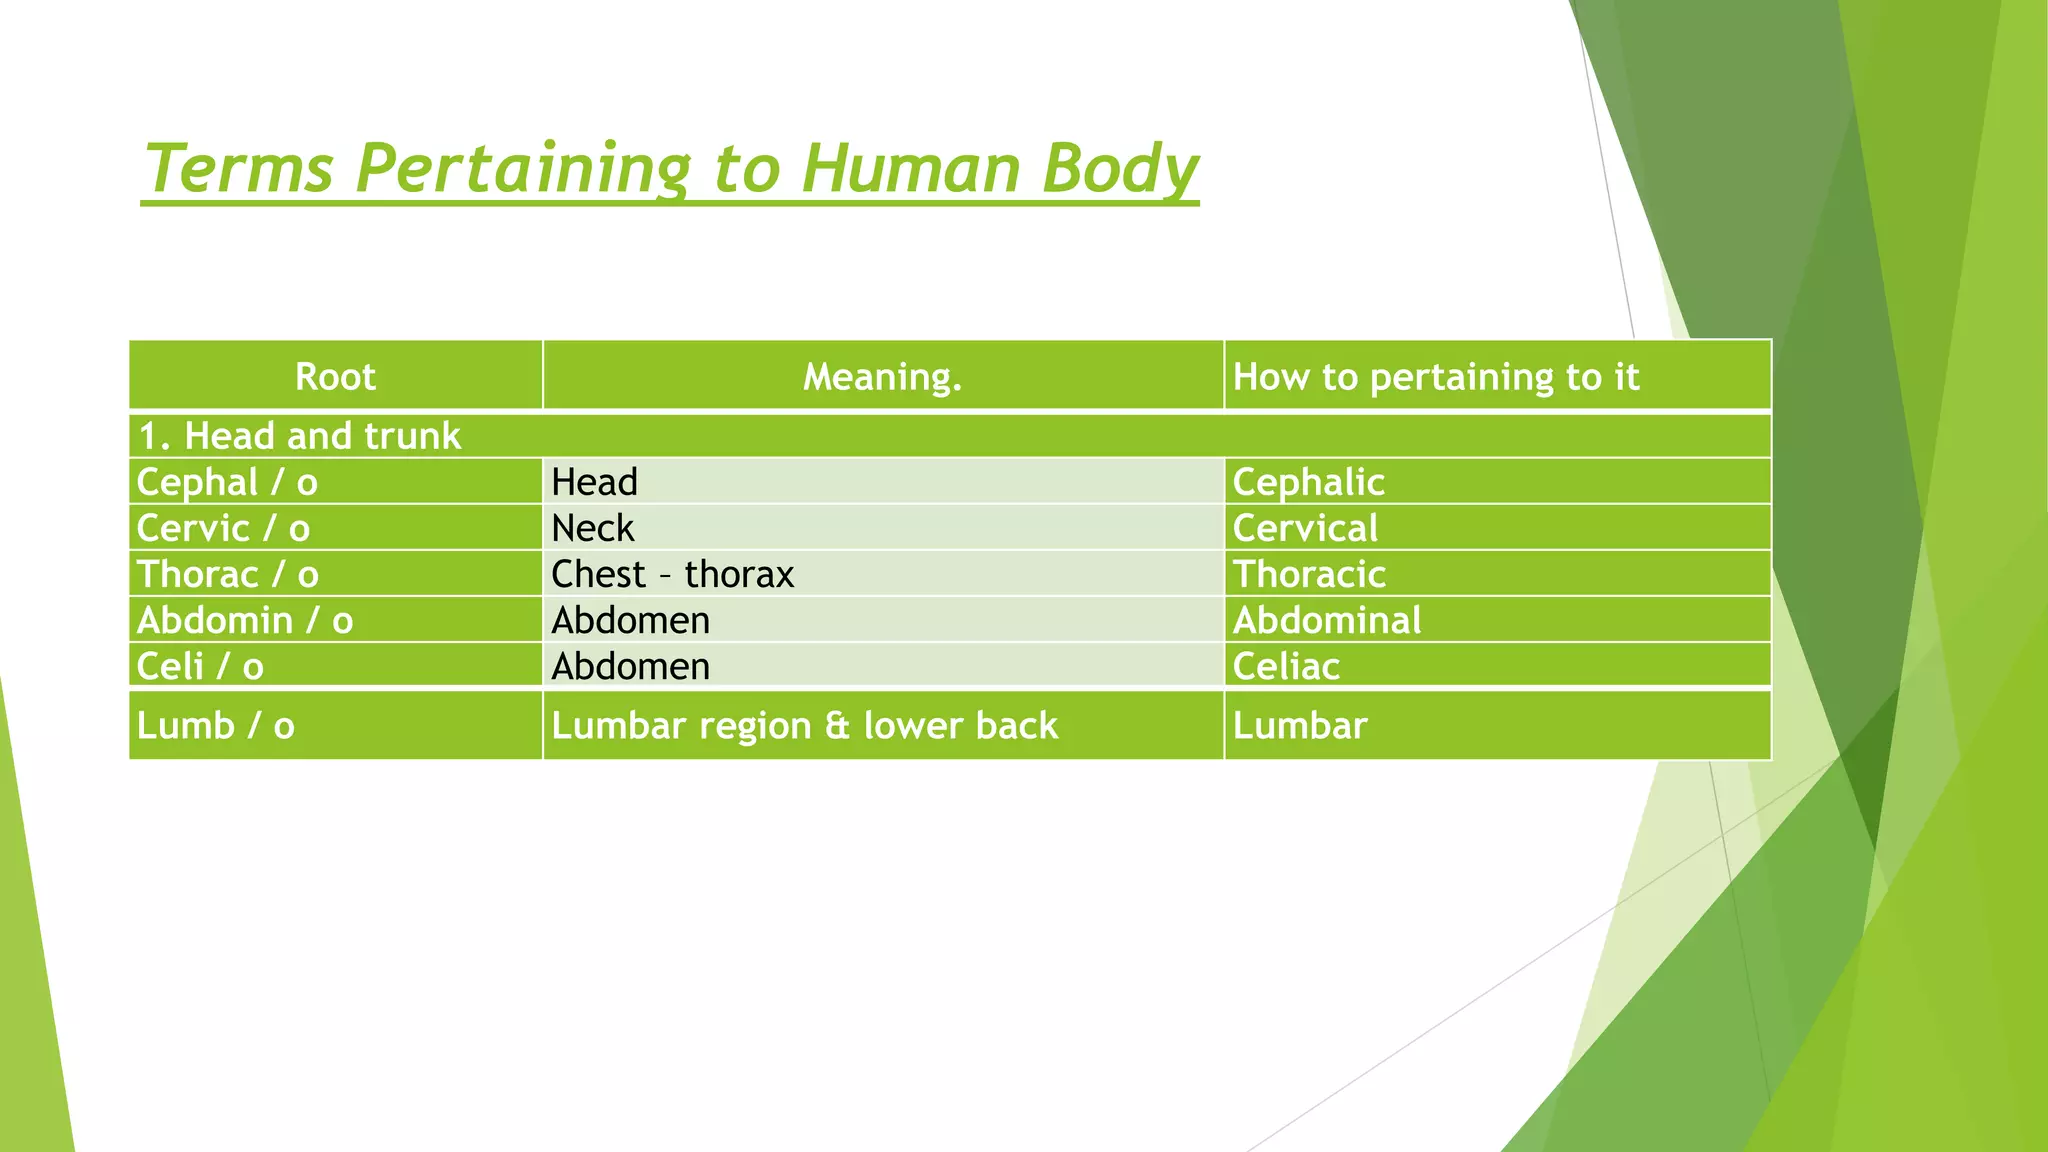
The phrase "Celi O Medical Term" comes up in patient forums and some provider messaging boards, usually when people are trying to parse their lab reports or understand what their gastroenterologist is recommending next. The short version is that it is not a standalone formal medical term in any major coding or nomenclature system. It tends to appear as shorthand for celiac disease screening panels — the IgA-based antibody tests, genetic HLA typing, and the endoscopic biopsy that confirms the diagnosis. If you saw that string on a form or a message board, it is likely a condensed reference to the overall diagnostic workflow rather than a specific billable code or defined laboratory marker. In practice, when someone uses that term they are talking about the standard celiac serology panel. That means total IgA, tissue transglutaminase IgA (tTG-IgA), and sometimes deamidated gliadin peptide IgA and IgG if there is known IgA deficiency. The workflow moves from those blood tests to an upper endoscopy with duodenal biopsies, following the AGA and ACG guidelines. Most first-line screening happens with tTG-IgA because it has strong sensitivity and specificity in the general population. Endomysial antibody testing is more specific but also more expensive and operator-dependent, so it is usually reserved for borderline or discordant results. I ran into a situation a few years back where a patient had a negative tTG-IgA but continued to have significant symptoms, and their doctor was using loose shorthand in documentation that looked like a complete rule-out. The problem was that the patient had already started a gluten-reduced diet before the blood work. Once gluten is removed, serology can drop quickly, and false negatives become much more common. We ended up doing HLA-DQ2/DQ8 genotyping to assess genetic risk, and the patient was put back on a gluten-containing diet under supervision so they could complete proper serologic and endoscopic evaluation. That workaround is important to know because lots of people self-modify their diet before testing, and then the results are useless for ruling anything in or out.
How the Diagnostic Pipeline Actually Works
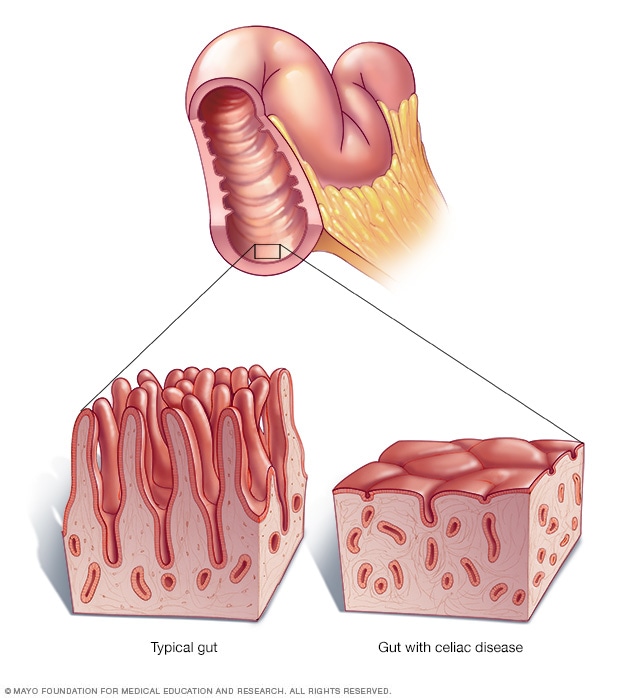
The first step is serology while the patient is still eating gluten regularly. That usually means at least 1 to 2 grams of gluten per day for about six to eight weeks before blood is drawn. If the tTG-IgA comes back positive, especially at higher titers like four times the upper limit of normal, the next step is referral for an upper endoscopy with multiple duodenal biopsies. The Marsh-Oberhuber classification is what pathologists use to grade the villous atrophy, and a diagnosis of celiac disease generally requires compatible histology along with positive serology and clinical response to a gluten-free diet. There are a few things people miss about this process. One is that total IgA must always be checked at the same time. If the patient has selective IgA deficiency, which occurs in about 1 in 20 to 1 in 40 celiac patients, the tTG-IgA will be falsely negative because there is not enough IgA to detect. In those cases, you switch to IgG-based tests like tTG-IgG or DGP-IgG. Another thing that gets overlooked is the effect of advanced age. Serologic sensitivity drops somewhat in older patients, and some clinicians end up relying more heavily on endoscopy in that group even when antibody titers are low-positive or borderline. A second counter-intuitive point is that celiac serology does not perfectly correlate with disease severity in every case. I have seen patients with quite high tTG-IgA titers who had only mild histologic changes on biopsy, and I have seen the reverse with modest titers and more advanced villous atrophy. The numbers are useful for monitoring dietary adherence over time, but they are not a precise measure of how much intestinal damage is present. That is why biopsy remains the gold standard even though it is invasive.
What the Guidelines Actually Say About Biopsy
Current guidelines allow for a subset of patients to potentially avoid biopsy if they meet strict criteria, but those criteria are narrow. The ESPGHAN approach applies mainly to children and requires very high tTG-IgA levels, a positive endomysial antibody on a second blood draw, and supportive genetic testing. For adults, the American College of Gastroenterology still recommends biopsy in almost all confirmed or highly suspected cases. There is ongoing debate about whether that standard should change, but as of now most adult diagnostic pathways include endoscopy. The biopsy itself is not trivial. It involves sedation, scope insertion, and taking samples from the duodenum and sometimes the distal jejunum. Complications are rare but real, including bleeding and perforation. The procedure usually takes about 20 to 30 minutes, and patients typically go home the same day. Recovery is quick for most people, but it is still a procedure, and that is why accurate serology beforehand matters so much. Running the right blood tests first prevents unnecessary scopes in low-probability cases.
Get the Full Details
Genetic Testing and Its Actual Role
HLA-DQ2 and HLA-DQ8 typing is the third piece of the diagnostic puzzle. About 95 to 99 percent of people with celiac disease carry at least one of these haplotypes, which makes the test very sensitive as a rule-out tool. If you do not carry DQ2 or DQ8, the likelihood of celiac disease is extremely low. The problem is that roughly 30 to 40 percent of the general population also carries those genes, so a positive result tells you almost nothing on its own. It is useful mainly for ruling out celiac disease in ambiguous cases, not for confirming it. I had a case where a primary care provider ordered HLA typing as a first-line screening test for a patient with vague gastrointestinal complaints. The result came back positive for DQ2, which naturally caused unnecessary anxiety because the patient interpreted it as a diagnosis. It was not. That is a common pitfall. Genetic testing should be interpreted by someone who understands its limitations, and it should never replace serology and clinical correlation.
Monitoring After Diagnosis
Once someone is diagnosed and on a strict gluten-free diet, the standard monitoring approach is to repeat tTG-IgA at six to twelve months and then periodically after that. The expectation is that titers will decline over time, ideally becoming negative within one to two years for most patients. If titers do not drop or they rise again, the usual explanations are ongoing gluten exposure, either intentional or accidental, or occasionally misdiagnosis. Refractory celiac disease is rare but possible, and that is when a specialist needs to get involved. One practical detail that people often do not plan for is the variability in lab reference ranges. Different laboratories use different assays and cutoff values, so a tTG result from one lab may not be directly comparable to a result from another. It is better to use the same laboratory for follow-up testing whenever possible. Tracking the trend over time matters more than any single number.
When the Standard Approach Fails
There are scenarios where the typical serology-plus-biopsy pathway does not give clear answers. Small bowel biopsy can miss focal areas of damage, which is why guidelines recommend taking multiple samples from different sites. Some patients have seronegative celiac disease, meaning they meet histologic and genetic criteria but never develop detectable antibody levels. In those cases, diagnosis relies more heavily on biopsy and genetic findings, and management is the same once confirmed. Another failure point is lactose intolerance developing temporarily after diagnosis. Many newly diagnosed patients also have secondary lactose malabsorption because the damaged intestinal lining produces less lactase. That can mimic ongoing celiac symptoms even when the diet is otherwise appropriate. A brief trial of lactose restriction often helps clarify whether that is happening. It is not a sign that the celiac diagnosis is wrong.
Practical Steps for Someone Facing This Workup
If you are being evaluated for celiac disease, the most important thing is to stay on a gluten-containing diet until all testing is complete. Do not start a gluten-free diet on your own before blood work and endoscopy. Bring a list of all your symptoms and any family history of autoimmune conditions to your appointment. Ask your provider which specific antibody tests are being ordered and whether total IgA is included. If you have already reduced gluten, be upfront about that because it changes how the results should be interpreted. The diagnostic process for celiac disease is straightforward in most cases but has several ways to go wrong if shortcuts are taken. Serology first, biopsy when indicated, genetic testing selectively, and careful follow-up afterward. That sequence works for the vast majority of patients. Deviating from it without a clear reason is where things tend to get confusing.