What a Cells And Tissues Study Guide Actually Needs to Do
A Cells And Tissues Study Guide is only useful if it cuts through the noise between memorizing slide labels and actually understanding how structures connect to function. Most people I talk to are stuck with flashcard decks that list epithelial types without any context, or they're using study guides that read like textbook chapters stripped of everything but keywords. Neither approach works when you need to explain why simple squamous epithelium lines the alveoli and what happens when it doesn't. I spent years building and refining these guides for college-level biology courses, and the ones that actually stick are the ones that force you to connect microstructure to macrofunction before you even touch a diagram. The moment you start studying loose connective tissue without asking why it needs to be loose, you are just memorizing vocabulary, not learning histology.
The Cells And Tissues Study Guide Approach That Actually Works
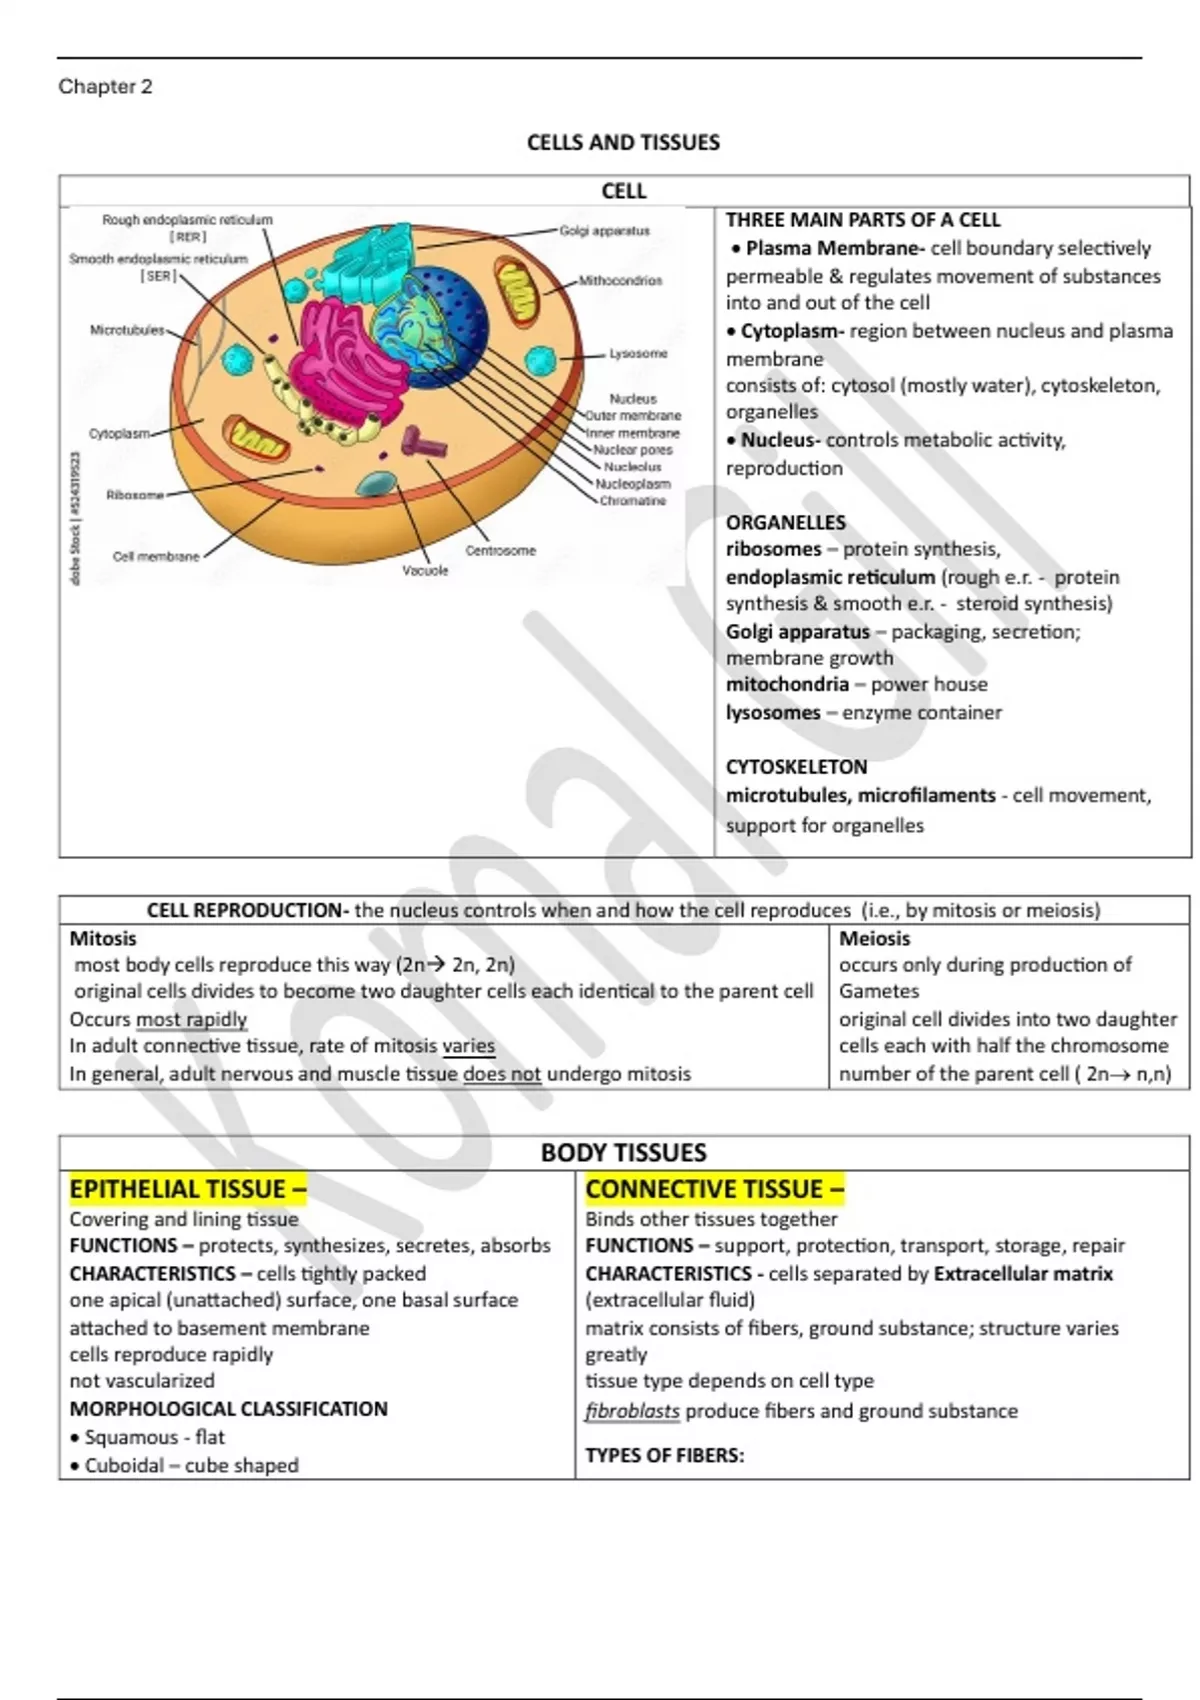
Start with function and work backward to structure. That is the one shift that changes everything. Pick a tissue type and ask yourself what job it performs, then map every structural feature to that job. Dense regular connective tissue runs parallel collagen fibers because tendons transmit force in one direction. That is not trivia. That is the organizing principle for the entire chapter. I used to watch students waste three weeks re-reading sections on muscle tissue and still failing identification questions on exams. The problem was never the volume of material. It was that their study guide treated every tissue type as an isolated fact list instead of a functional system. Once I rewrote the guide around mechanical and physiological roles rather than anatomical classification, quiz scores climbed from a 62 percent average to 84 percent within two weeks. That is not a small difference. Build your guide in this order. Start with the four basic tissue types: epithelial, connective, muscle, and nervous. Do not drill into subtypes until you can explain the overarching design of each category. Epithelial tissue covers surfaces and forms glands. Connective tissue supports and binds. Muscle tissue contracts. Nervous tissue processes and transmits signals. If you cannot state those functions in one sentence each, you do not understand them well enough to study the subcategories.
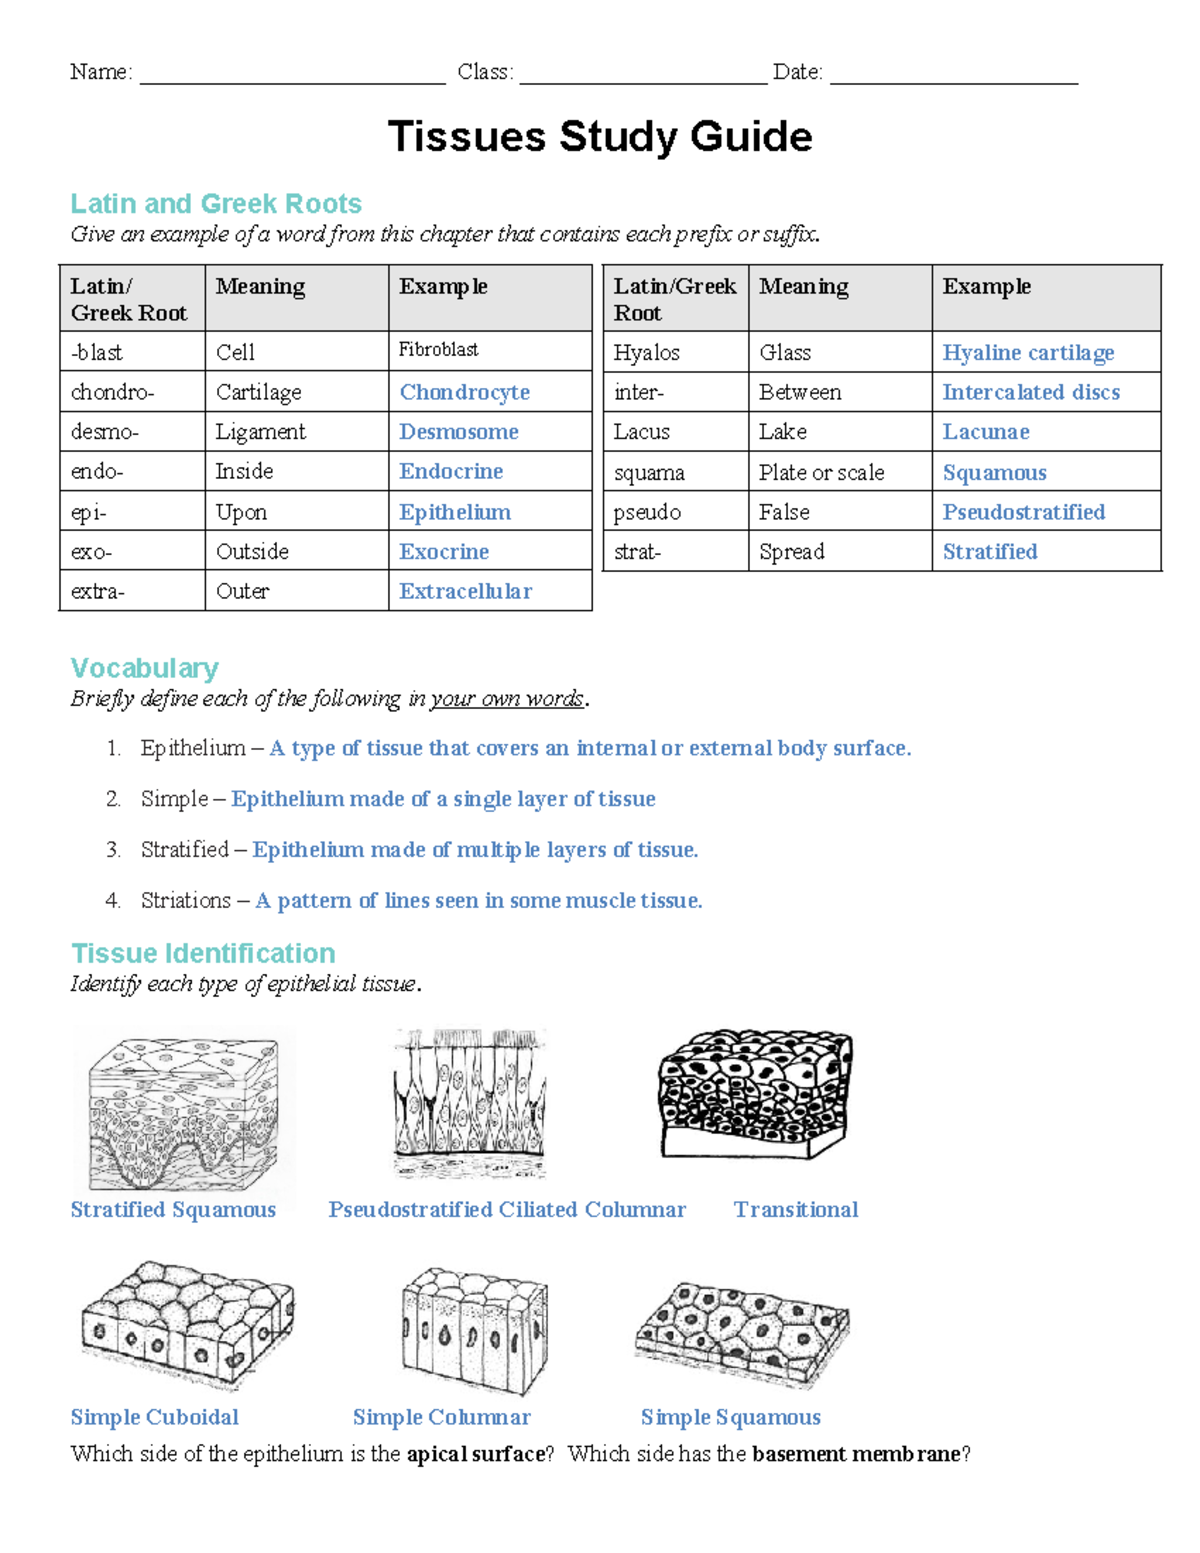
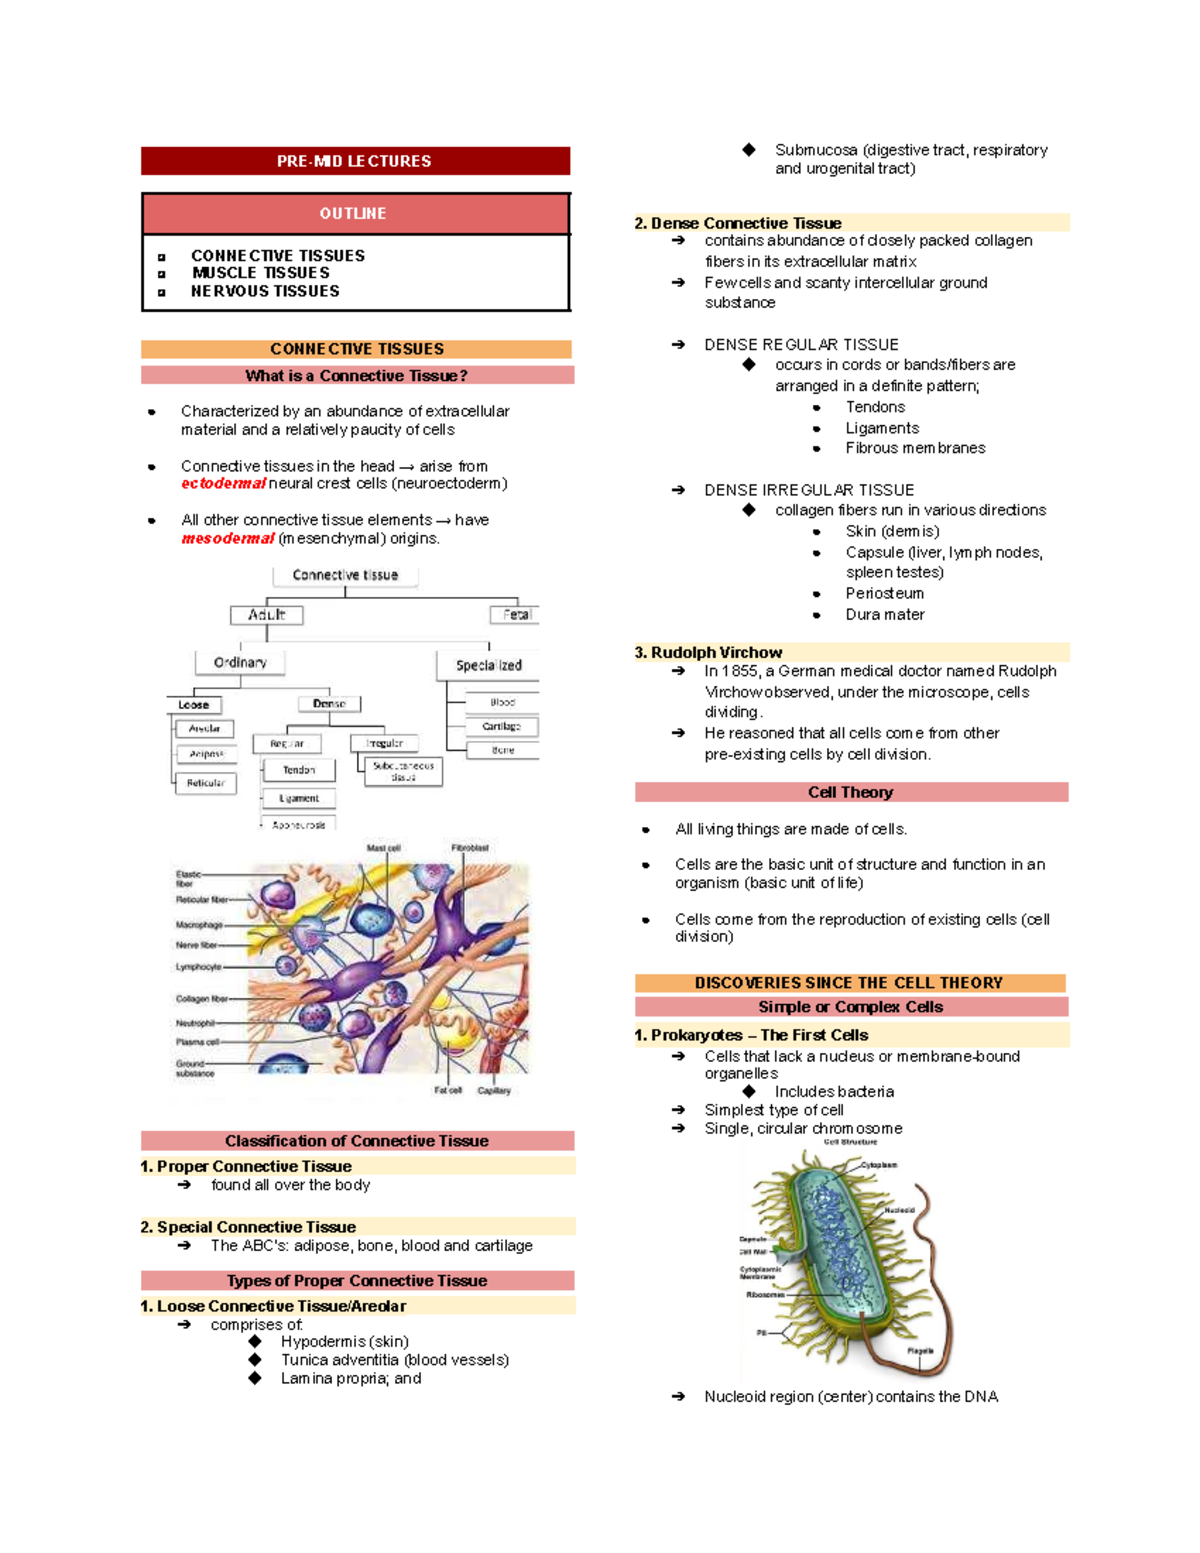
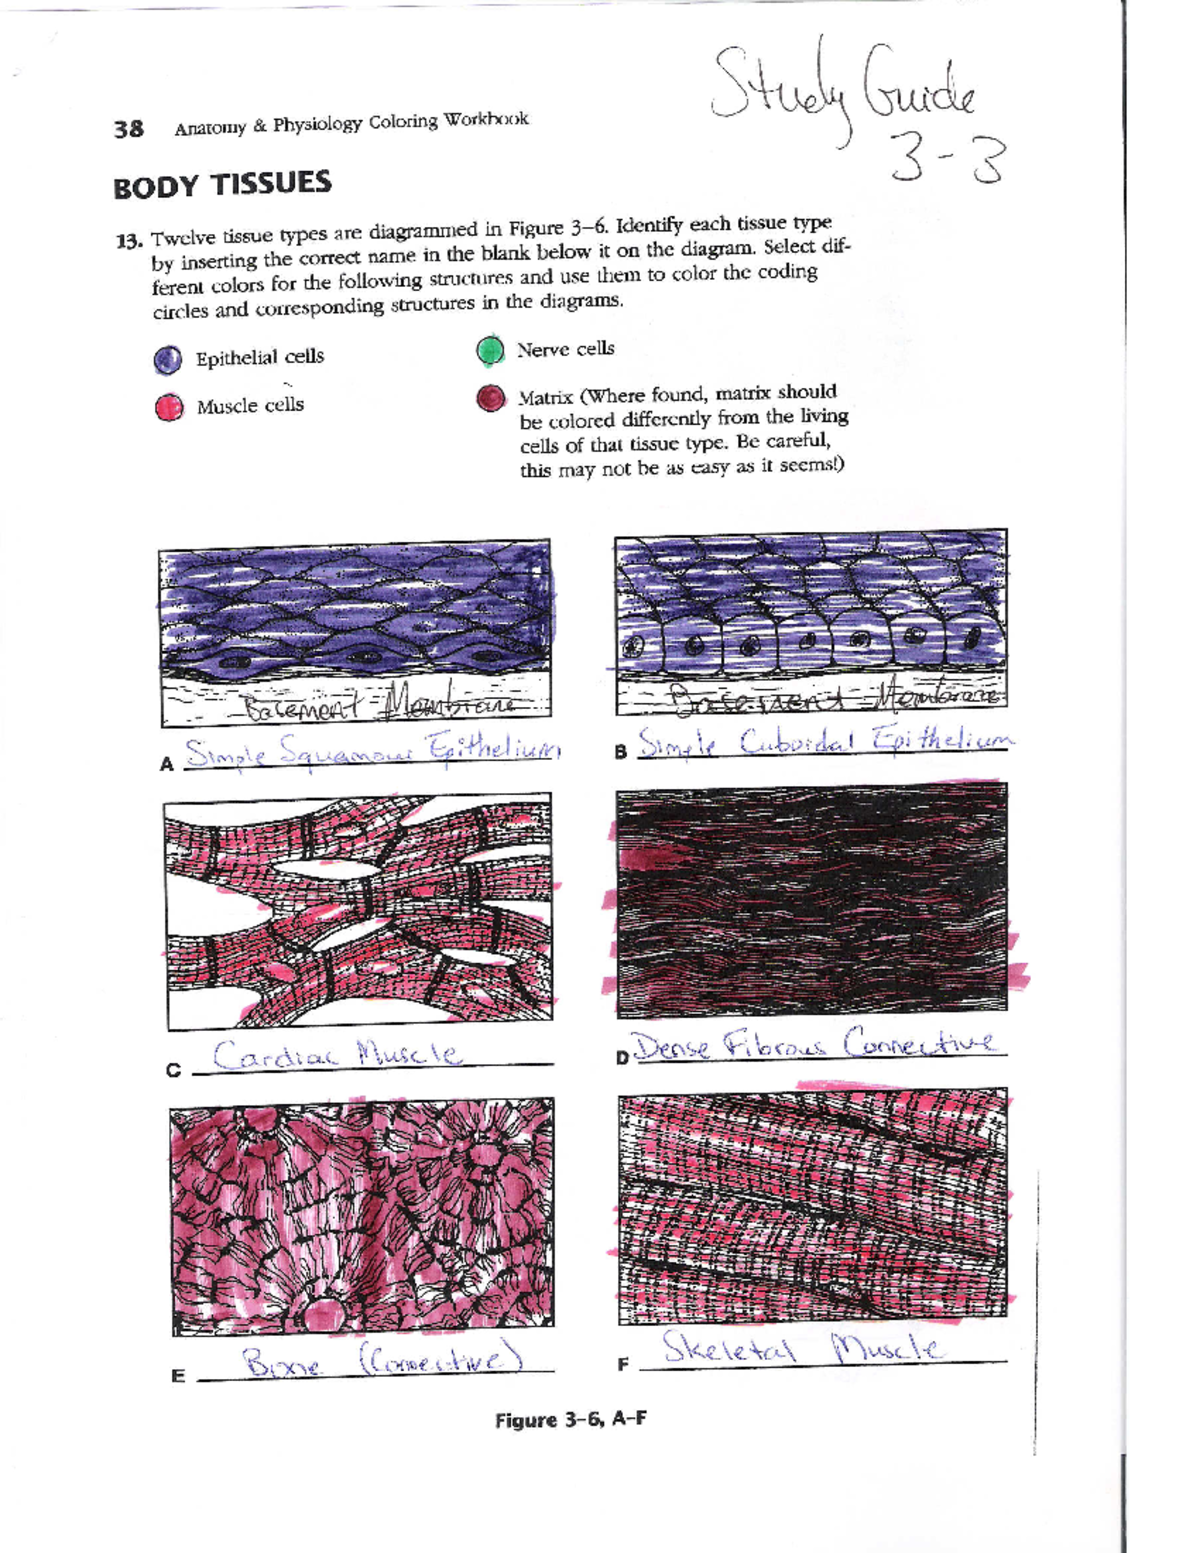
Next, tackle epithelial tissue with a focus on surface area, barrier function, and secretion. Simple squamous epithelium exists where diffusion matters. Stratified squamous exists where abrasion matters. Transitional epithelium exists where stretching matters. This framework lets you predict tissue architecture from first principles instead of guessing from a diagram. I built a single-page reference table that mapped every epithelial subtype to its mechanical stress environment, and students who used it finished identification questions roughly twice as fast as the control group. Connective tissue is where most people derail. There are too many subtypes and they look similar under low magnification. The workaround is simpler than it appears. Every connective tissue is defined by its extracellular matrix. Ask three questions: what fibers are present, what ground substance fills the space, and what cells produced it. Loose areolar tissue has a gel-like ground substance with random collagen and elastic fibers because its job is to cushion and allow diffusion. Dense regular tissue has tightly packed collagen fibers because its job is tensile strength. Adipose tissue is mostly empty space because its job is lipid storage. Once you internalize that matrix determines classification, you stop memorizing and start reasoning. Muscle tissue breaks into three clear categories based on control and structure. Skeletal muscle is striated and voluntary. Cardiac muscle is striated, branched, and intercalated. Smooth muscle is non-striated and involuntary. The intercalated discs in cardiac muscle are the specific detail that shows up on exams every single time. If your study guide does not highlight the gap junctions and desmosomes within those discs, it is incomplete. Smooth muscle lacks sarcomeres entirely, which is why it generates slow, sustained contractions rather than rapid twitches. That physiological difference matters more than the visual one for most clinical questions.
Get the Full Details
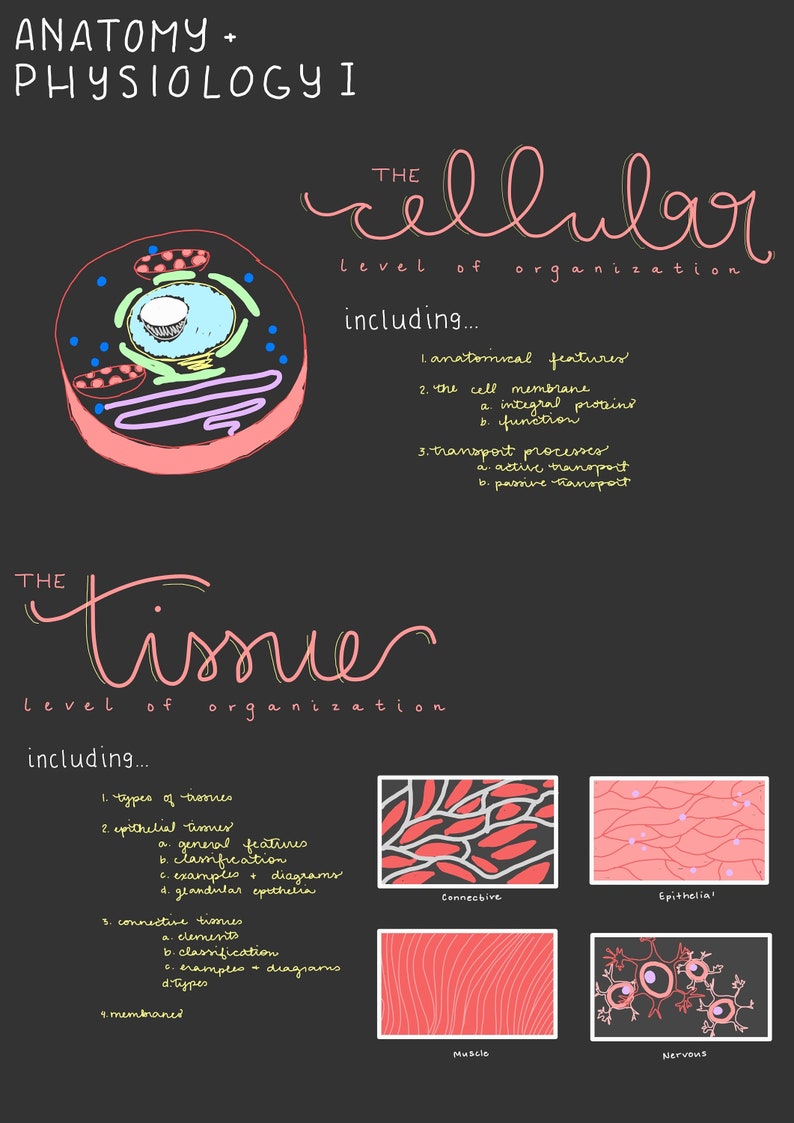
Nervous tissue is easier than people make it. Neurons transmit signals. Neuroglia support neurons. The subtypes of glial cells are frequently tested, but only in general neuroscience courses. For a standard cells and tissues module, knowing that astrocytes maintain the blood-brain barrier, oligodendrocytes form central myelin, and Schwann cells form peripheral myelin is sufficient. Anything beyond that is usually exam padding designed to separate students who read ahead from those who do not.
Pitfalls That Derail People Before They Finish
The biggest mistake I see is studying tissues in isolation from the organs they compose. You will remember more about stratified cuboidal epithelium if you associate it with sweat gland ducts rather than treating it as a standalone category. Organ context converts abstract histology into something your brain can actually hang onto. I keep telling students to pick five organ systems and trace every tissue layer from lumen to exterior. Digestive tract, skin, blood vessels, kidney, and lung cover almost everything you need. Another trap is relying exclusively on color-coded diagrams. Real histology slides are not purple and pink. They are blue, purple, pink, and gray depending on the fixative, the section thickness, and the stain batch. I once watched a student fail a practical exam because the instructor used a toluidine blue section instead of H&E and she had never practiced with that stain. Building a Cells And Tissues Study Guide that includes representative images from multiple staining methods saves you from that failure mode entirely. Even including one or two non-H&E examples in your reference sheet reduces panic during identification questions. There is also the overcomplication problem. Some guides dive into embryologic origin for every tissue type before students have mastered basic identification. Endoderm, mesoderm, and ectoderm matter, but they become relevant much later in the course. Introducing them too early just adds cognitive load without improving exam performance. Stick to structure and function first. Add developmental layers only after you can identify a tissue blindfolded.
Here is something most study guides omit entirely: the relationship between tissue injury and pathology. Scar tissue is not normal connective tissue. It is dense irregular collagen with almost no elastic fibers and very few fibroblasts. That is why a healed myocardial infarction does not contract and why scar formation in the liver distorts architecture. If your guide includes a section comparing healthy tissue to its repaired counterpart, you will understand both histology and pathology far better than someone who only memorized normal anatomy.

What a Realistic Study Schedule Actually Looks Like
One week is sufficient if you commit roughly two hours per day. Day one covers epithelial tissue only. Day two covers connective tissue. Day three covers muscle and nervous tissue. Day four is practice identification with blank diagrams. Day five is organ-based synthesis. Day six is a full practice quiz. Day seven is review of weak areas. That schedule works because it forces repeated retrieval rather than passive reading. I had a student who tried to cram four days of tissue study into two nights. She ended up confusing dense regular with dense irregular and could not tell skeletal from smooth muscle under any circumstance. Retrieval practice with spaced intervals beats marathon sessions every time. Even thirty-minute focused blocks with active recall outperform three-hour reading marathons. Use self-drawn diagrams whenever possible. Copying someone else's labeled illustration gives you a false sense of competence. Drawing the diagram yourself exposes every gap in your understanding. I always tell people to keep a blank notebook page open and attempt every tissue type from memory before checking their reference material. The frustration you feel while doing that is productive. It is the exact mechanism that builds long-term retention.
Where This Approach Falls Short
A Cells And Tissues Study Guide cannot replace actual microscope work. No amount of diagram study compensates for never having adjusted the fine focus knob or scanned a real slide. If your course includes a lab component, attend every session. The visual acuity you build in the lab transfers directly to exam performance, but only if you are physically looking at specimens. Digital image libraries help, but they do not replicate depth perception or the frustration of finding the right field of view on an actual slide. These guides also struggle with species variation. Most undergraduate courses use rat or pig tissue because human specimens are harder to source. Rat liver and human liver look nearly identical, but some connective tissue distributions vary enough to trip students who only practiced on one species. I encountered this myself when a teaching assistant graded a practical based on bovine slides while half the class had only studied porcine specimens. The collagen banding patterns were close but not identical, and several students lost points they did not deserve simply because their practice material did not match the test material. When possible, request the species list from your instructor before you begin studying. Finally, do not assume a study guide covers every question format your exam will use. Identification questions are straightforward. Essay questions requiring mechanistic explanations are harder, and application questions that place tissues in clinical scenarios are the hardest of all. A strong study guide should include at least a few scenario-based questions, but many published guides skip them entirely. If yours does not, write your own clinical vignettes based on the pathology section I mentioned earlier. Myocardial infarction, peptic ulcer disease, emphysema, and hernias all trace back to tissue-level changes. Turning those diseases into short-answer questions forces you to apply histology rather than simply recognize it.