Running a Center For Physical Therapy Is Less Clinical and More Administrative Than People Expect
You think about opening a center for physical therapy, most people imagine a bright clinic with rubber bands and ultrasound machines. The reality is mostly compliance paperwork, insurance renegotiation, and learning which documentation habits will get you audited six months down the line. I spent years watching good clinicians burn out because nobody taught them the operational side. Here is how it actually works. Licensing is the first wall you hit, and it varies enough by state that a generic answer is useless. You need a facility license from your state board of physical therapy, a federal EIN, NPI numbers for both the organization and each treating PT, and malpractice coverage that actually covers facility-level claims. Too many people treat the NPI piece as an afterthought and then realize six months later that payer enrollments are tied to the wrong number. Fix that before you accept your first patient. Insurance credentialing is where most new centers bleed money without knowing it. Getting contracted with major carriers takes between four and nine months depending on the payer and your state. During that window, you are either billing cash or routing claims through a group you piggyback on, which means you are taking a cut and losing direct patient relationships. I had a clinic owner who didn't understand this and turned away roughly $18,000 in the first quarter because she thought credentials came through in six weeks. They did not. Start the application before you sign a lease.
The Business Model Most People Get Wrong
Physical therapy revenue does not scale linearly with patient volume because evaluation time is fixed and reimbursement rates are compressed. A typical center runs on a mix of self-pay cash plans, direct-access patients without physician referrals, and insurance panels that pay significantly less than billed charges. The math gets worse fast if you are relying only on one or two payers. I once saw a clinic lose its contract with the largest carrier in the region and drop to sixty percent of revenue overnight because the owner had never diversified. Build at least three payer relationships before you open, and have a cash-based plan ready for patients who cannot wait for authorization. Staffing is the other silent killer. You need a front desk person who understands scheduling, basic insurance verification, and empathy. Not the same skill set. Hiring a receptionist who can do neither well will tank your no-show rate and your patient satisfaction scores within ninety days. The clinical side requires either a lead PT who can handle evaluations and supervise aides, or a management structure that separates clinical oversight from business operations. Mixing those roles in one person usually means one of them suffers.
Documentation And Compliance Basics That Actually Matter
Documentation in a physical therapy setting is not a clerical task. It is your legal shield and your primary billing tool. Each visit needs to show medical necessity, measurable progress or lack thereof, and a clear plan that justifies the next session. Skimpy notes get denied. Overly detailed notes get audited. The middle ground is specificity without redundancy. I started using a modified SOAP format that forced me to include objective measure deltas on every note, and our denial rate dropped from about fourteen percent to under five percent in three months. The trick is building the habit early, because retrofitting documentation for sixty past patients is basically impossible. Coding matters too. CPT codes for PT are straightforward on the surface, but modifiers, time bundling rules, and the eight-minute rule for modalities trip people up constantly. If you bill more time codes than the minutes you documented, you are creating audit exposure. Track your minutes per visit in real time and reconcile them before you submit. Most practice management software can generate a simple exception report if you configure it properly.
Get the Full Details

Choosing Your Space And Equipment Without Overcommitting
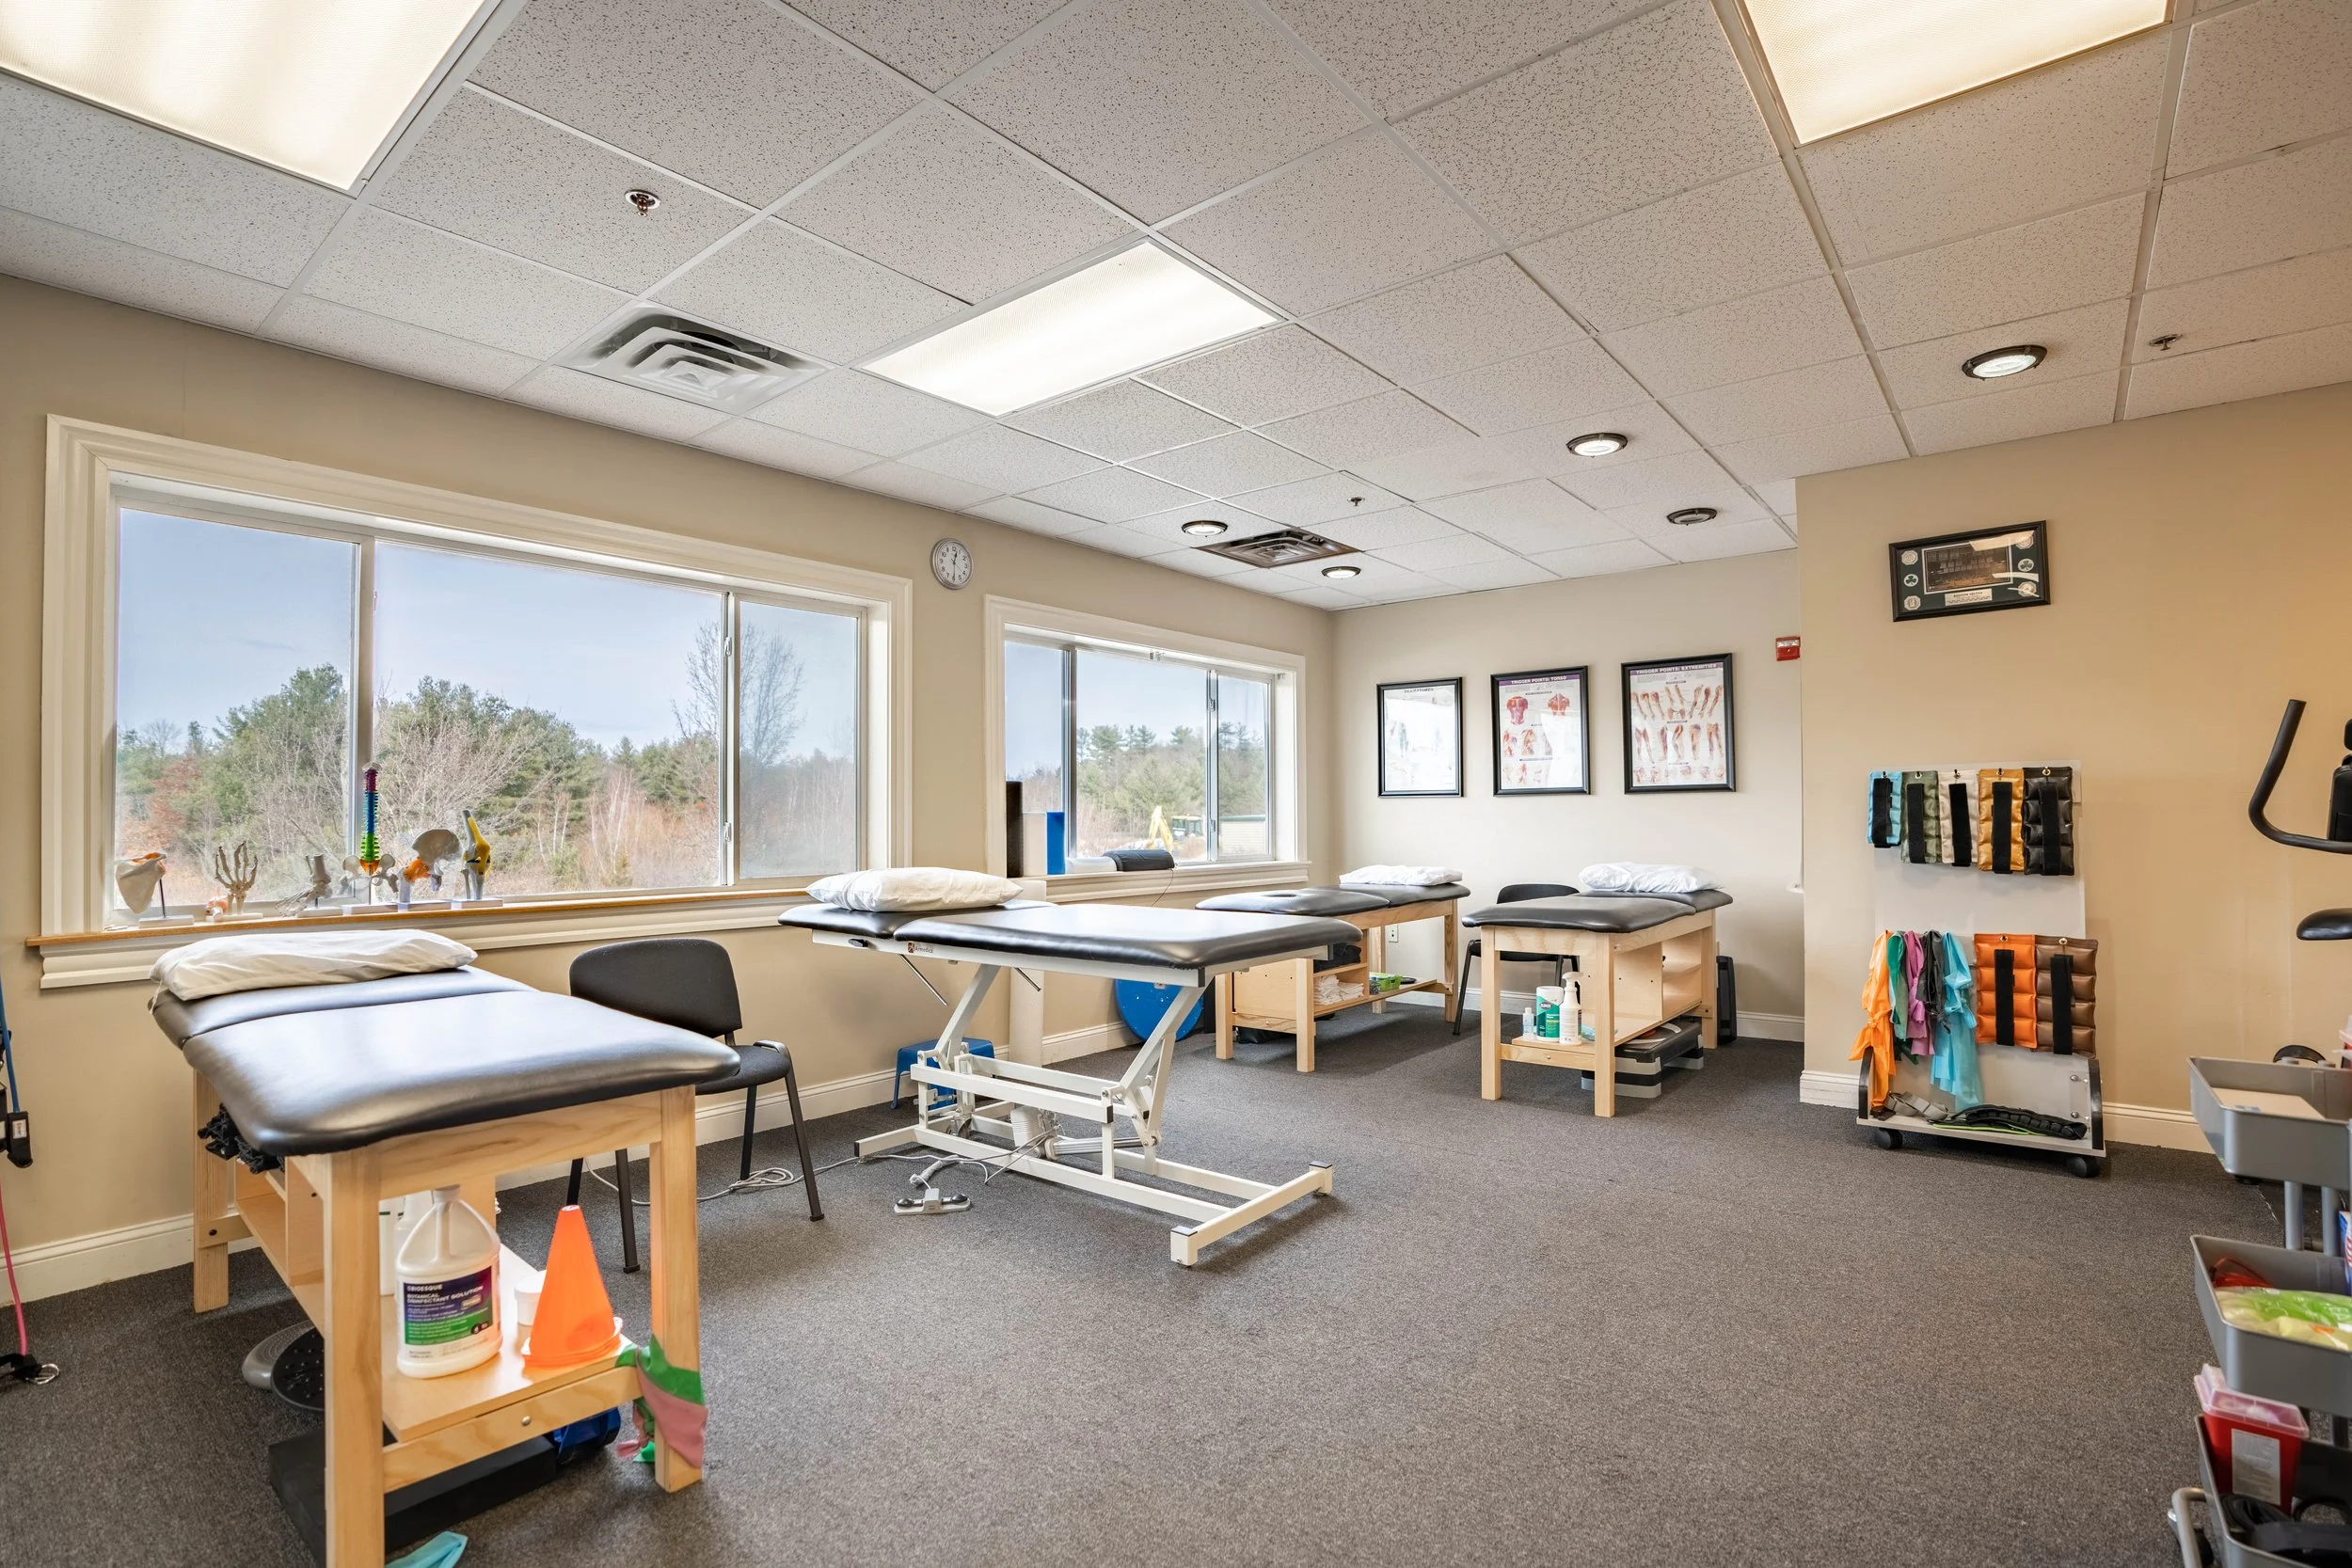
Location matters less than accessibility and parking. A place that is hard to reach will kill your attendance rate faster than anything else. I worked with a center that moved to a fancier downtown suite to look established, and their no-show rate jumped because patients could not find parking. They moved back to a ground-floor unit with free parking within six months and recovered most of the lost revenue. The cosmetic appeal of an office building does not translate to patient volume in this field. Equipment should be bought based on the treatments you actually plan to offer, not the catalog. A full balance and gait lab is overkill for a general practice. You need basics: treatment tables, a moderate resistive training setup, a cardio zone, ultrasound, electrical stimulation units, and TENS. That is it for most centers. Specialty equipment like hydrotherapy or traction systems should come later once you have patient demand that justifies it. I once saw a clinic finance a \$40,000 aquatic therapy unit in year one and barely use it twice a week. The loan payments ate into staff salaries for two years.
Patient Acquisition That Does Not Feel Desperate
Referral relationships are the core revenue engine for most physical therapy centers. Building them takes time and consistency. You need to identify the physicians, orthopedic surgeons, neurologists, and primary care providers in your area and make yourself easy to refer to. That means fast intake, clear communication back to the referring provider, and documentation that makes their job easier. I had a surgeon who stopped referring to a competitor because their discharge summaries were late and incomplete. It was not about quality of care. It was about administrative reliability. Online presence is table stakes now. Most patients search for physical therapy near them before they have a referral. Your Google Business Profile, basic website with hours and services, and a few legitimate reviews carry more weight than any advertising spend in the early months. Do not skip the review strategy. Ask every satisfied patient at checkout, and respond to every review, even the negative ones. I once turned a one-star review about wait times into a two-month process improvement that actually reduced our average check-in time by twelve minutes.
What To Avoid And When To Pivot
There are scenarios where a standalone physical therapy center is a bad idea. If you are in a market with three or more established centers within a two-mile radius, competition will compress your margins unless you have a genuine differentiator like a specialty population focus or a unique treatment model. Primary care overlap is another reason to reconsider. Some regions have so many PT centers that payer panels are essentially saturated, and new contracts are rarely granted. Another failure point is trying to be everything at once. Geriatric rehab, sports performance, pediatric therapy, vestibular treatment, and post-surgical care all require different staffing, different equipment emphasis, and different referral networks. A center that tries to serve all of them equally usually serves none of them well. I recommend picking one or two niches to build credibility and referral pipelines around, then expanding once those streams are stable. The clinics that survived my observation period all had a clear specialty identity in their first two years, even if they broadened later. Telehealth has changed the landscape but not in the way most people assume. It works well for follow-up visits, education, and exercise progression checks. It does not replace hands-on treatment or initial evaluations that require palpation and functional testing. Several states expanded telehealth permanently during the pandemic, but payer coverage for PT telehealth varies widely. Verify your contracted payers' telehealth policies before you invest heavily in that infrastructure.

Opening a center for physical therapy is manageable if you treat it as a healthcare business first and a clinical practice second. The clinical skills get you licensed. The operational discipline keeps you open. Focus on compliance, payer diversification, documentation quality, and referral relationships, and you will be ahead of most people who start this hoping the patients will just show up.



