
Writing Effective Therapy Dialogues: A Practical Guide
Therapy dialogue writing is one of those skills that looks simple on paper but gets messy fast when you actually try to produce usable examples. Most training materials give you polished transcripts that read like nothing ever happens in a real session. The gap between those textbook examples and actual clinical work is bigger than people admit. Centered Therapy generally refers to approaches where the therapist anchors conversations in the client's immediate experience rather than abstract analysis. When I say anchored, I mean literal grounding in what the client is reporting, feeling, or noticing in the room. Centered Therapy Dialogue Examples reflect this by keeping the focus tight on present-moment awareness instead of drifting into history-taking or interpretation-heavy blocks. A centered dialogue starts with what the client said last, not what the therapist wants to explore next. Beginners often reverse this instinctively because they're trained to "be directive" and they mistake direction for leading. Directing and leading are different things. Directing follows the client's current track. Leading pulls them onto yours.
Here is a basic example structure: Client says something like "I've been feeling really stuck at work." A centered response would be "Stuck. What does that feel like in your body right now as you say it?" rather than "When did this start? How long has this been going on?" The second question isn't wrong per se, but it moves away from centering. It shifts the focus outward to narrative instead of inward to experience.
The Method Behind the Dialogue
The core method rests on three moves: acknowledge, ground, and follow. Acknowledge means reflecting back what the client said without adding meaning. Ground means directing attention to the present moment experience. Follow means letting the client's next report dictate where the conversation goes next rather than steering toward your hypothesis. I spent years watching trainees struggle with the acknowledge step because it feels passive. It doesn't feel like doing therapy. It feels like parroting. But parrot work is where most sessions get stuck anyway, and the client senses the therapist's impatience long before the reflection lands. A rushed acknowledgment signals that the therapist is checking a box rather than listening. Once you land the acknowledgment, the grounding step usually takes one of two forms: sensory or somatic. Asking "what do you notice in your body" is somatic. Asking "where in the room do you feel that tension" is sensory. Both work. The choice depends on the client's comfort level and your orientation.
Get the Full Details

The follow step is where most people fail. They ground and then immediately pivot to their own intervention model. A centered dialogue stays with the client's report for at least two or three turns before introducing anything new. This doesn't mean you do nothing. It means you listen longer than feels natural.
Common Pitfalls I See Constantly
The biggest mistake is over-reflection. When a therapist reflects everything the client says, it sounds mechanical and drains the session of momentum. You don't need to reflect every statement. Pick the ones that carry emotional weight or physical sensation. Skip the informational stuff like "so you had a meeting with your boss" unless the client is clearly seeking validation. Another pitfall is premature depth. Clients will sometimes offer surface material because they're testing whether the space feels safe. Pressing for deeper emotion too early creates resistance that looks like client defensiveness but is actually therapist impatience. I've seen this play out in supervision countless times. The trainee pushes, the client shuts down, and everyone blames the client's "resistance" instead of recognizing the timing error. There is also the trap of sounding scripted. Centered dialogue has a rhythm, but if you apply it like a checklist, it reads obviously artificial. The rhythm should emerge from genuine curiosity about what the client is experiencing right now. If you find yourself thinking about your next reflection while the client is still talking, you've already lost the thread.
A Specific Problem I Encountered
Once I worked with a client who was highly intellectual and verbally fluent. Every time I tried to ground her in bodily experience, she'd redirect the conversation toward analysis of why she felt a certain way. She could talk about anxiety for twenty minutes with perfect vocabulary and zero actual contact with the feeling itself. Standard centered techniques weren't working because she was using language as a buffer. The workaround I used was simple and slightly counterintuitive. Instead of asking her to notice her body, I asked her to describe the voice in her head that was doing the analyzing. I said "sounds like there's a part of you that's constantly explaining things. Can you hear what it's saying right now without trying to change it?" This bypassed her intellectual defense because I wasn't asking her to drop into sensation. I was asking her to observe the observation process itself. It took three sessions before she broke through, but when she did, the grounded work actually became possible. That's an edge case worth noting. Centered techniques aren't universally plug-and-play. Sometimes you need to find the specific door the client can actually walk through.

Centered Therapy Dialogue Examples in Practice
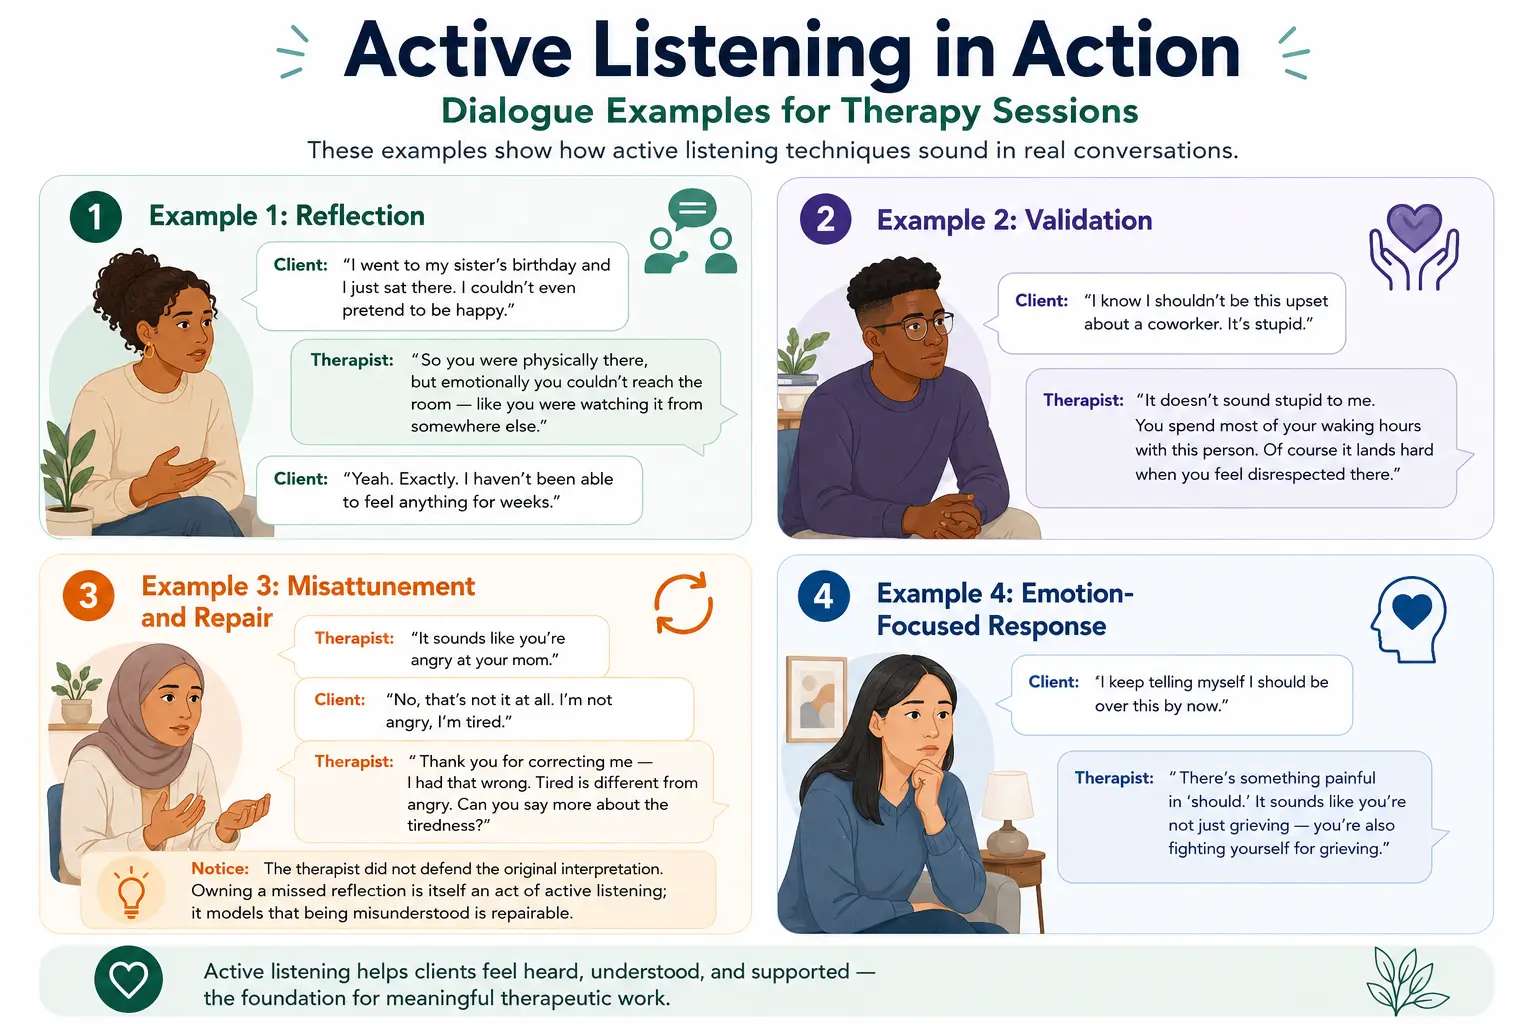
Below are a few dialogue snippets that illustrate the method in action. These are simplified but closer to real sessions than most published examples. Example one: anxiety presentation. Client: "I keep worrying about the presentation tomorrow. I can't stop thinking about it."
Therapist: "Can't stop. What happens in your body when you try not to think about it?" Client: "My chest gets tight. My shoulders go up." Therapist: "Stay with the chest tightness for a moment. What does it want to do?"
Client: "I don't know. It just sits there." Therapist: "Just sits there. Okay. Let it sit. What happens when you don't try to fix it?" Notice the therapist isn't offering coping strategies or cognitive restructuring. The therapist is keeping the focus on the felt sense and letting the client discover what emerges naturally.

Example two: relationship conflict. Client: "My partner said something that really got under my skin. I just blew up." Therapist: "Blew up. Where in your body do you feel that blow-up now?"
Client: "In my jaw. And my hands are clenched just thinking about it." Therapist: "Let your hands be clenched right here. Don't change them. What do they need?" Client: "I guess they need to open. It's been hours and I'm still gripping my pen like this."
Therapist: "Let the pen go. Notice what happens when you release it." This kind of exchange takes time. A single session might contain three or four exchanges like this before moving anywhere else. The pacing feels slow to therapists who are used to problem-solving frameworks, but the depth of contact tends to be higher because the client is actually experiencing the emotion rather than talking about it.
Limitations You Should Know About
Centered dialogue techniques don't work well in crisis situations where concrete action planning is needed. If a client is actively suicidal or in immediate danger, sitting with felt sense isn't the priority. Safety assessment and stabilization come first. The technique is also less effective with clients who have severe dissociation or trauma histories that make body awareness triggering rather than regulating. In those cases, grounding needs to be much gentler and more titrated. There is also a time constraint. Centered therapy dialogue moves slower than directive approaches. If you're working in a brief therapy model with a fixed number of sessions, spending twenty minutes helping a client stay with a sensation might not align with your treatment goals. In those contexts, a more structured approach like CBT or solution-focused therapy might be more appropriate. The technique also depends heavily on the therapist's own capacity for patience and presence. If you're personally uncomfortable with silence or feel anxious when you're not "doing something," centered dialogue will feel unbearable. You'll catch yourself filling space with questions or interpretations instead of staying with the client's experience. This is a personal limitation more than a technique limitation, but it matters for match quality.
How to Build Your Own Repository
The best way to improve at writing and using centered dialogues is to record your sessions with permission and transcribe them afterward. Compare your actual language against ideal centered responses. You'll notice patterns in how you drift away from centering, whether it's asking too many questions or jumping to advice too quickly. Supervision helps here. Having someone watch you work and point out when you've left the present moment is far more effective than trying to self-observe in real time. Most therapists can't listen to their own recordings without cringing, which is actually a good sign. It means your ear for authentic dialogue is developing. If you want reference material, look for transcripts from Gestalt therapy, process-experiential therapy, and somatic experiencing frameworks. These traditions share the centered approach even if they use different terminology. The dialogue patterns will be similar across them.

