Understanding the Divide
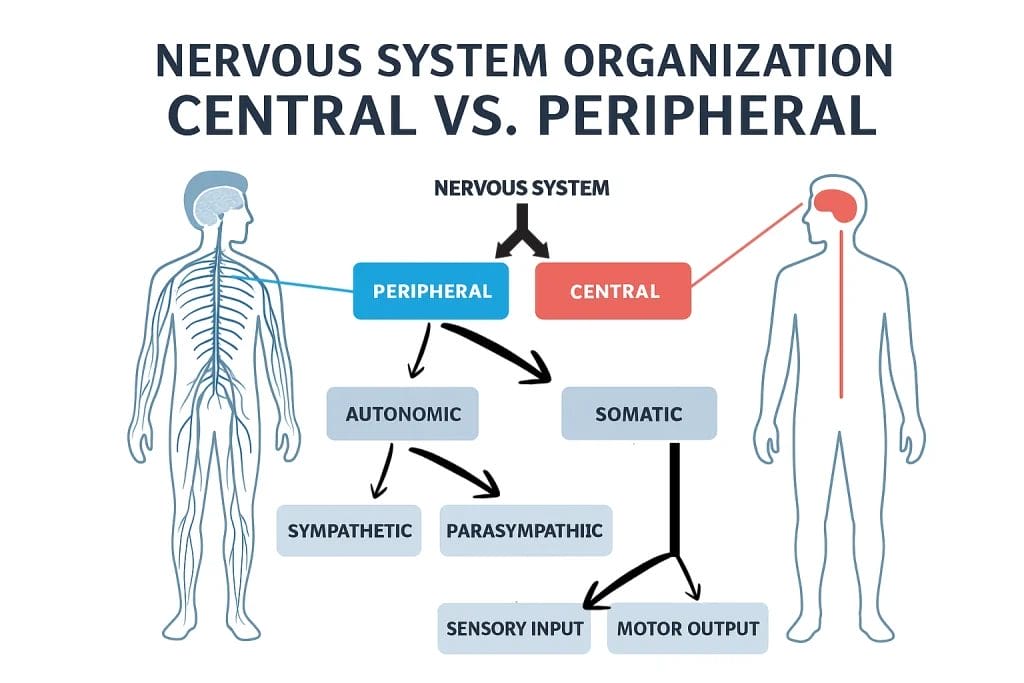
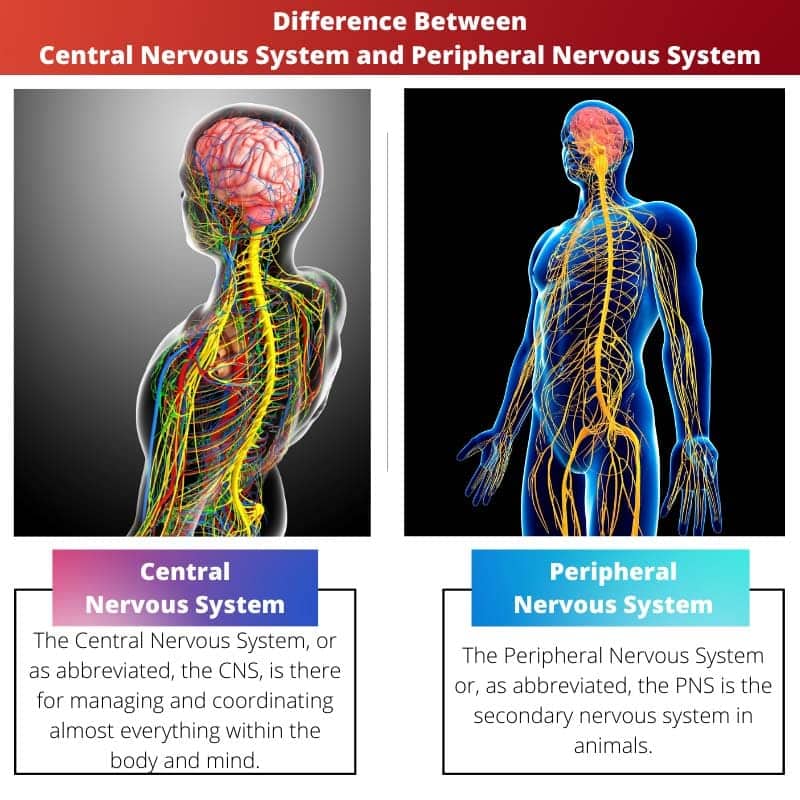
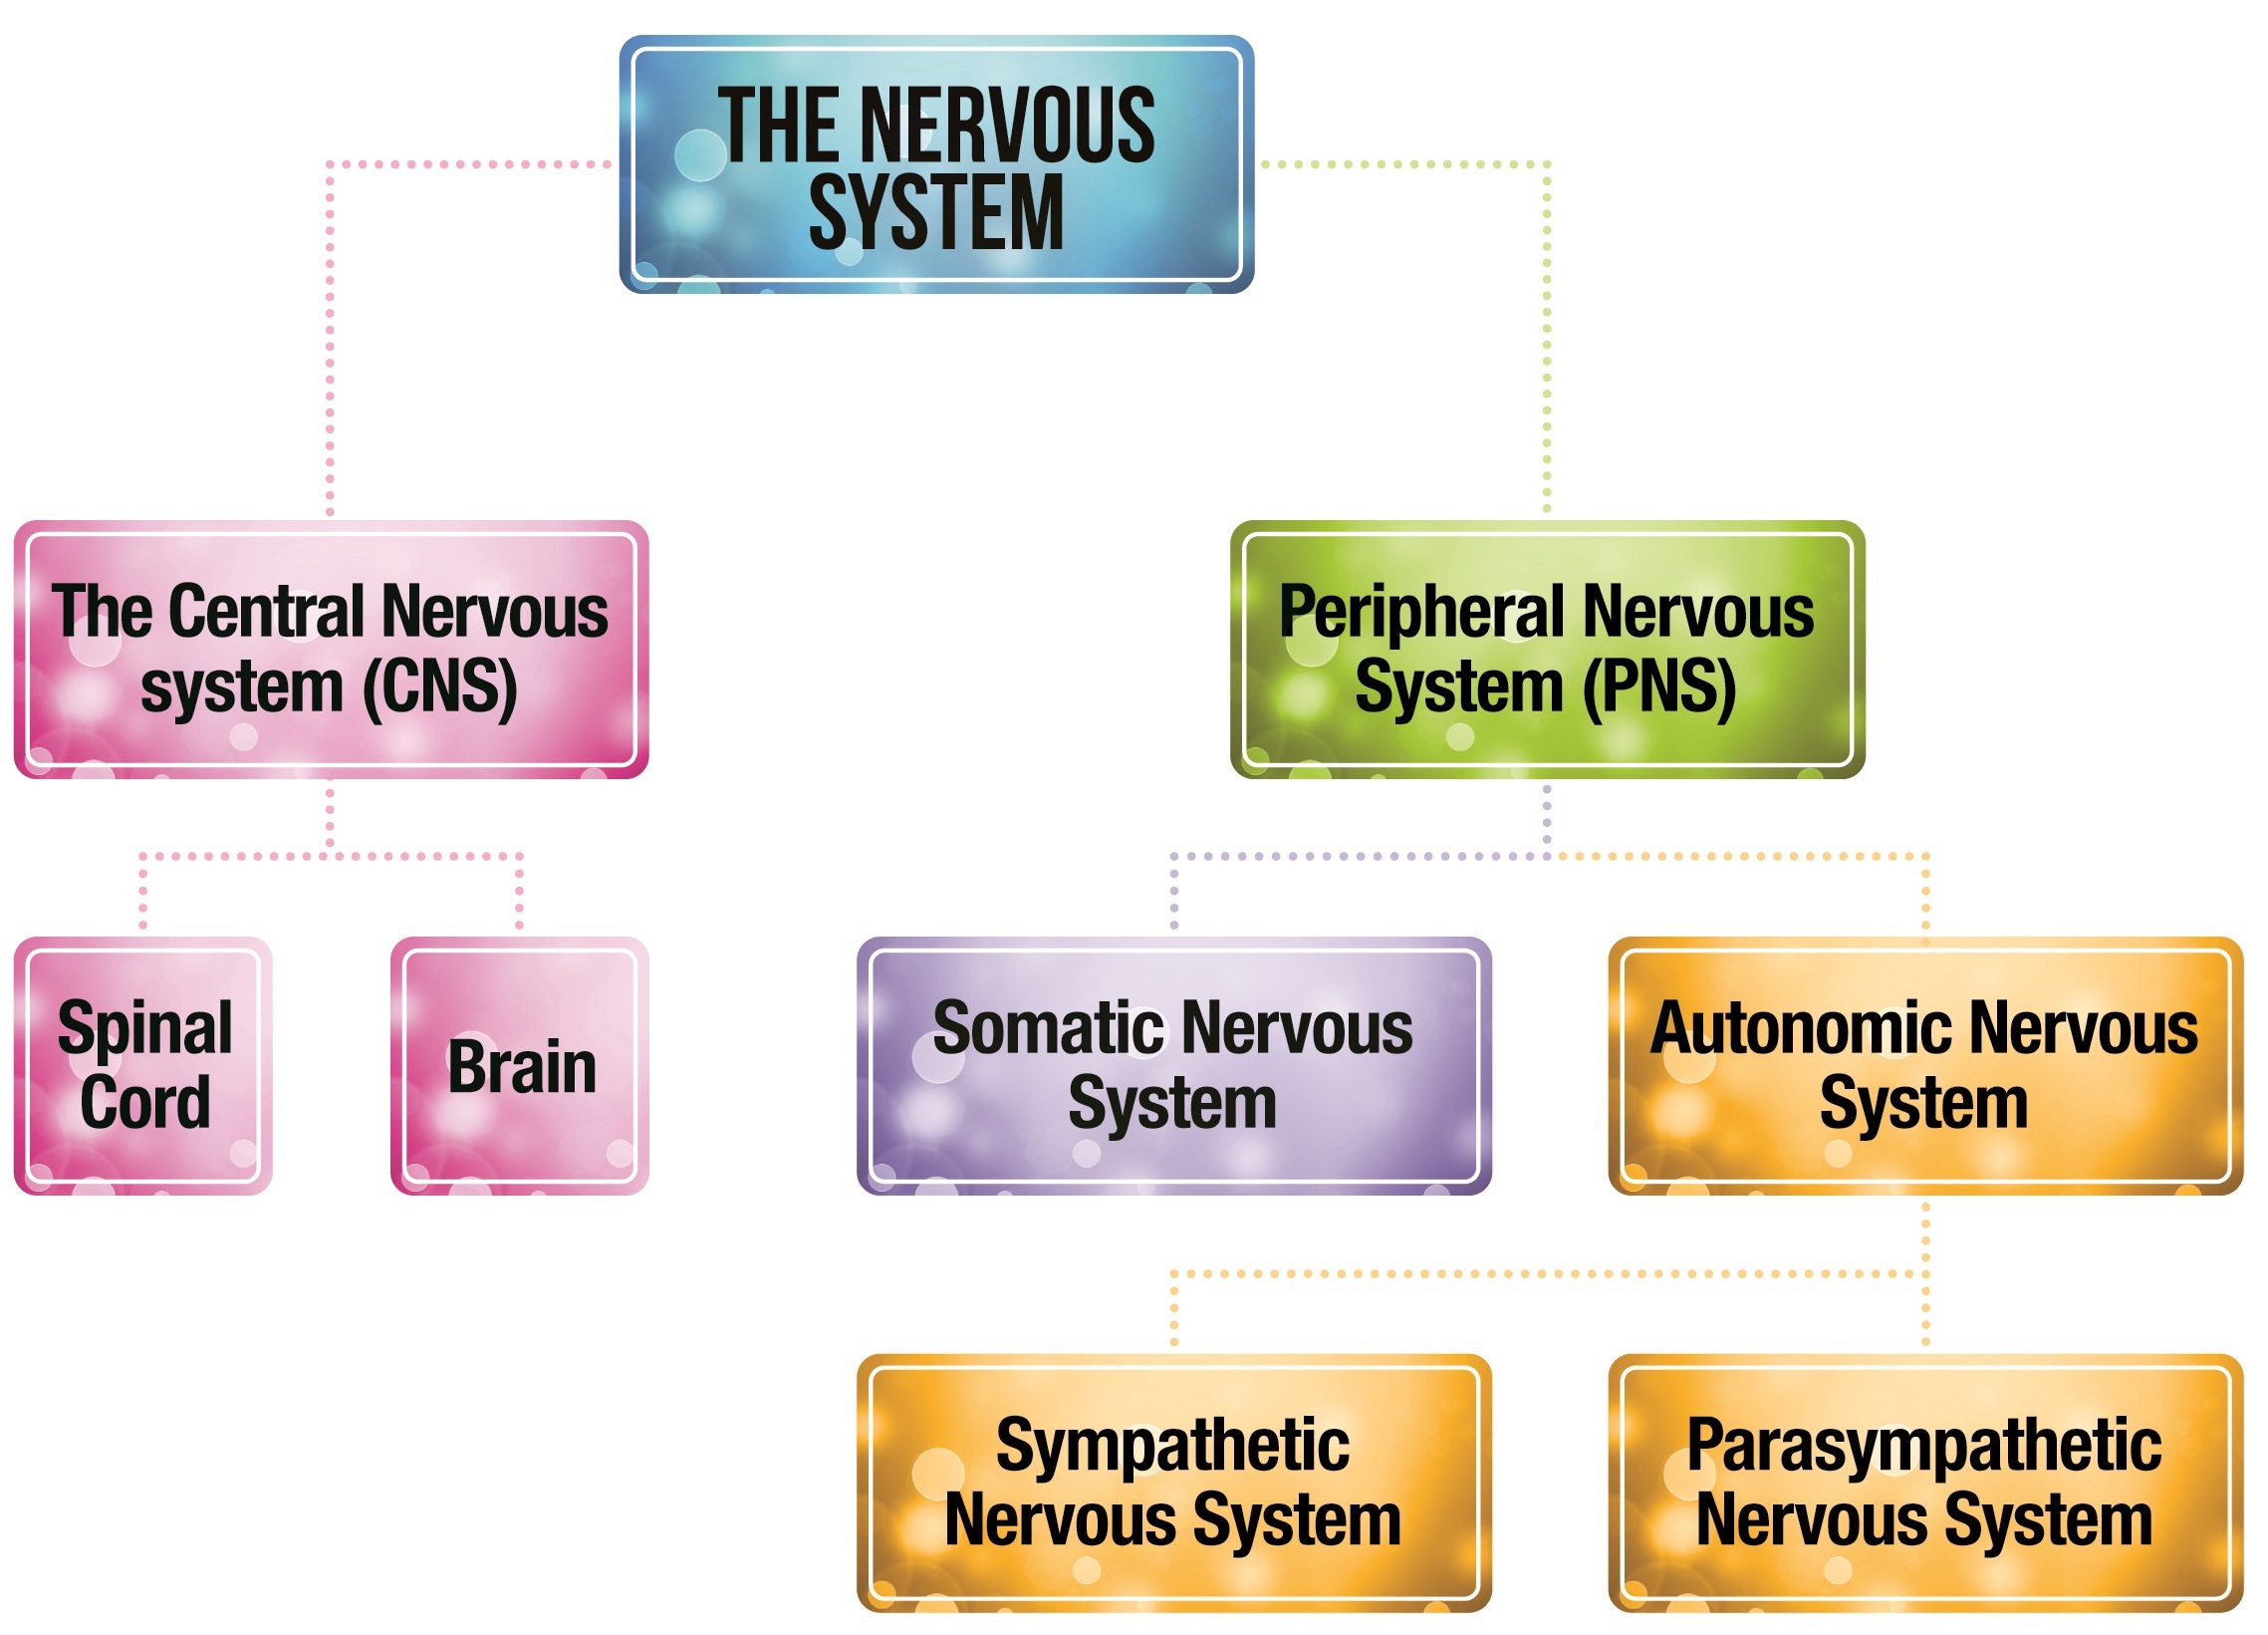
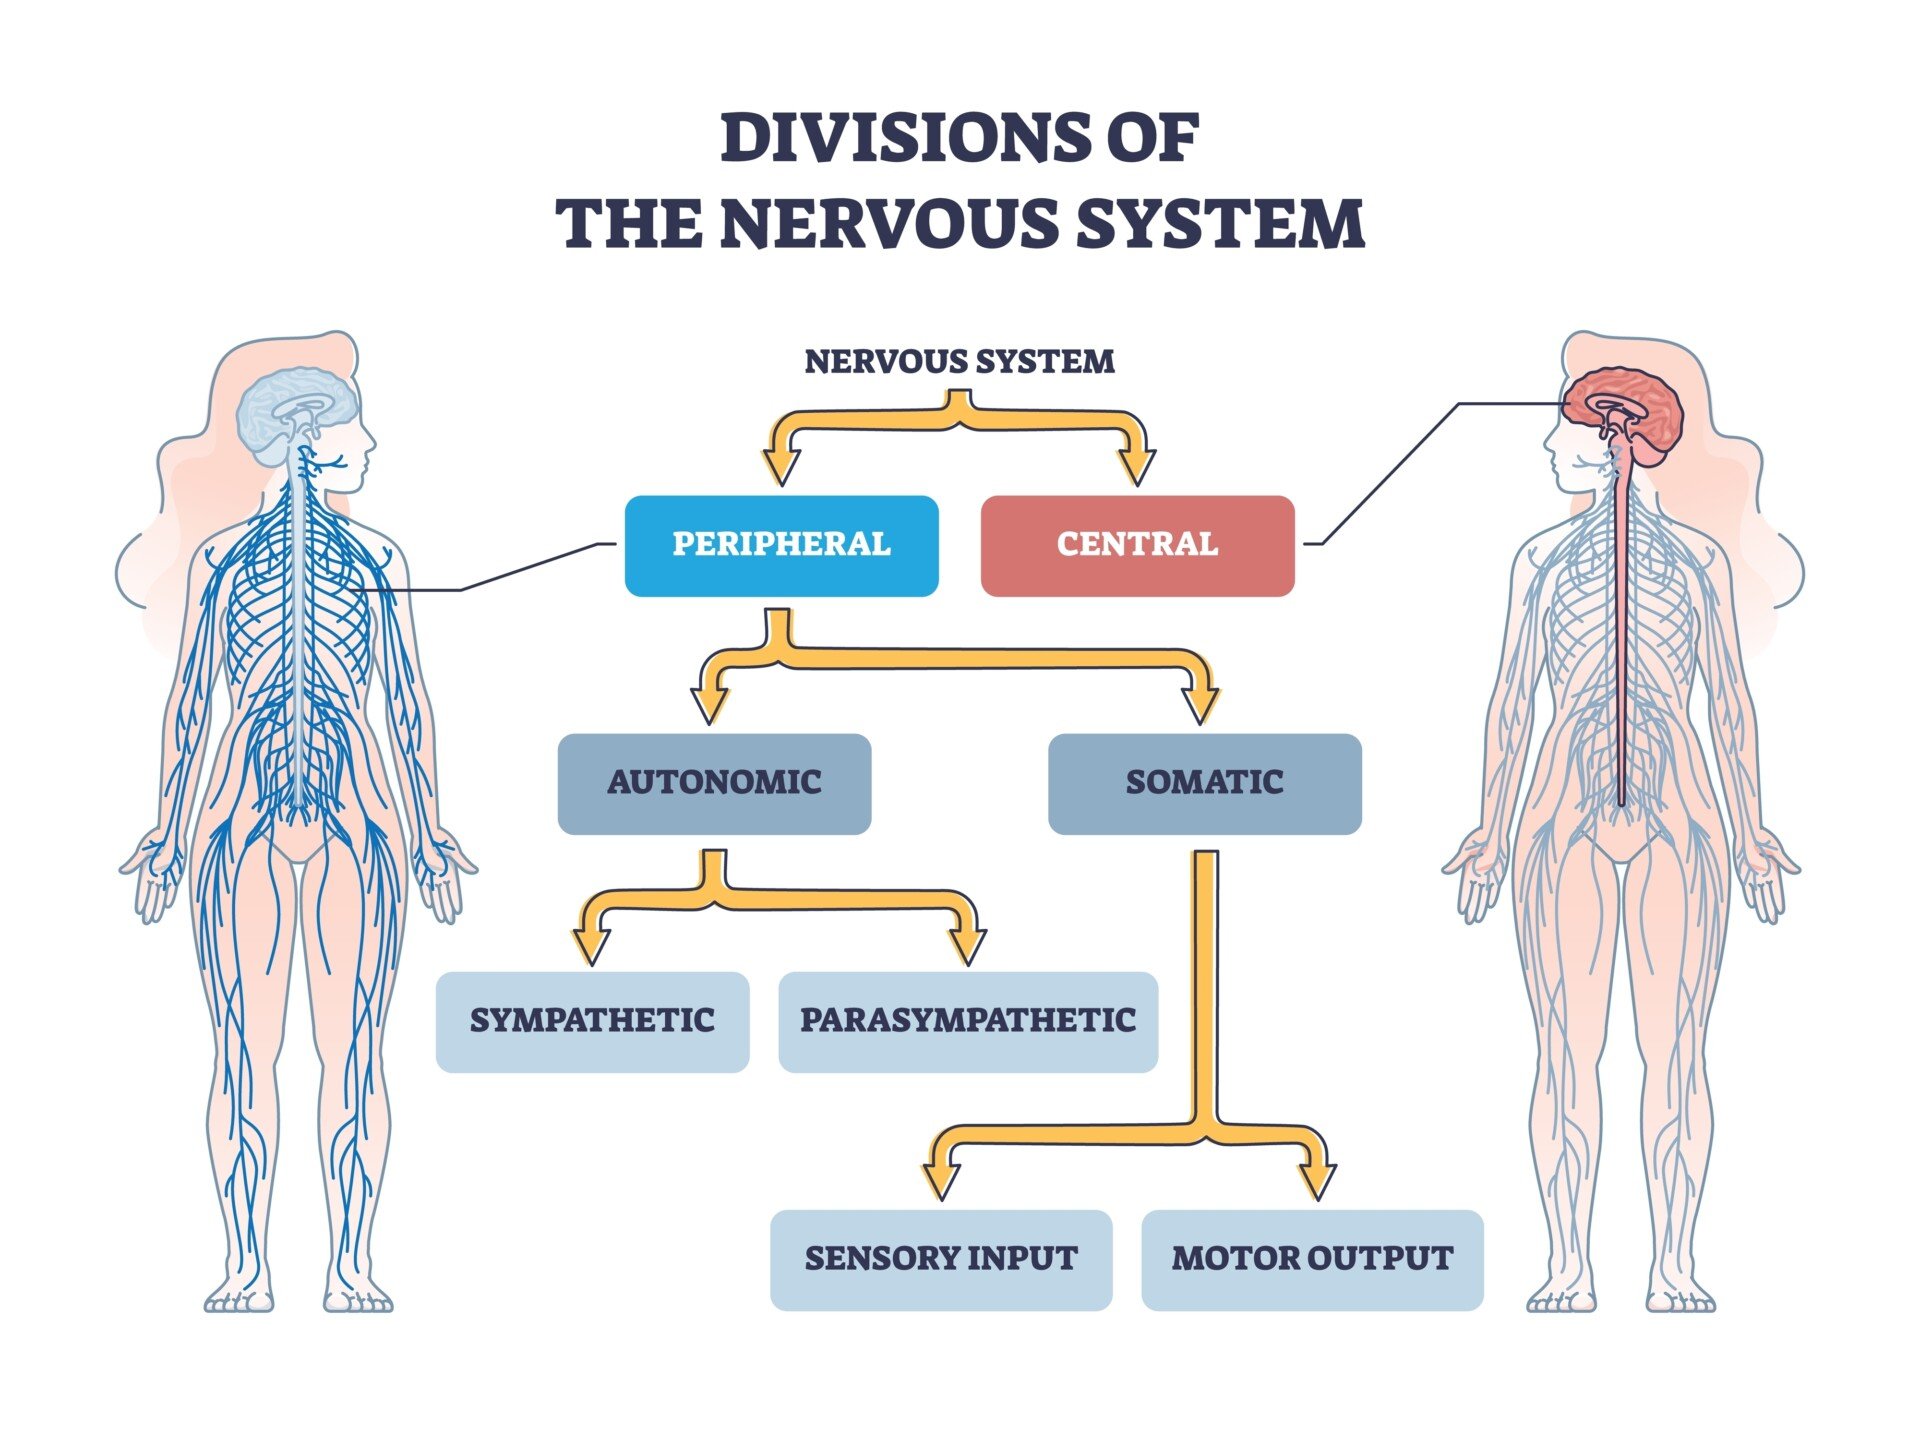
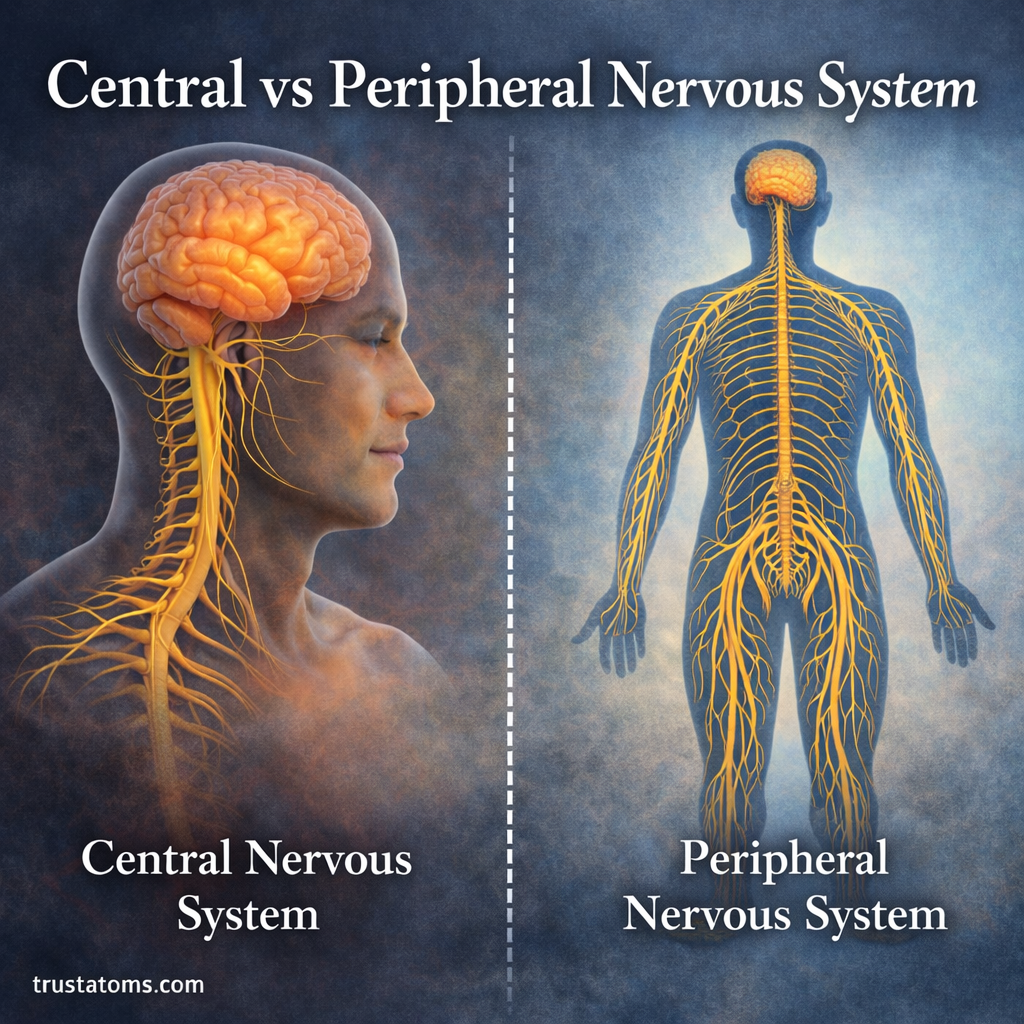
The nervous system breaks into two main branches that most people conflate. The CNS is your brain and spinal cord. The PNS is everything else — nerves branching out to limbs, organs, skin, and so on. Knowing where one ends and the other begins matters when you're diagnosing neurological issues or studying for boards. The CNS processes information. It's the command center. The PNS collects data from the body and delivers it to the CNS, then carries outgoing commands back out. Simple framework, but the overlap gets messy fast. Take reflex arcs. You touch something hot, your hand pulls away before your brain even registers pain. That arc runs through the spinal cord, not the brain. The PNS handled the sensory input, the CNS processed the immediate motor response, and then the PNS sent the "ouch" signal upward to your cortex. Three steps, two systems, milliseconds apart.
I ran into a case recently where a patient presented with peripheral neuropathy symptoms — tingling in the feet, weakness in the hands — but MRI showed no spinal compression. The reflexes were diminished but present. That distinction between CNS and PNS involvement changed the entire diagnostic path. We ended up testing for B12 deficiency and thyroid dysfunction rather than chasing structural spine issues. If I'd just assumed central, we'd have been ordering repeat MRIs and wasting weeks.
Key Differences That Actually Matter
Location of damage dictates symptoms. CNS lesions tend to produce upper motor neuron signs — spasticity, hyperreflexia, Babinski reflex. PNS lesions show lower motor neuron signs — flaccid weakness, atrophy, fasciculations, absent reflexes. This isn't just academic. It tells you whether you're looking at a stroke, MS, or something like Guillain-Barré syndrome. Regeneration differs drastically. PNS axons can regenerate at roughly 1 mm per day if the cell body survives and the endoneurial tube stays intact. CNS axons generally don't regrow. The glial scar, inhibitory molecules like Nogo-A, and lack of supportive scaffolding make recovery from spinal cord injuries so much harder than peripheral nerve injuries. That's why a severed finger nerve might heal with therapy, while a spinal cord transection typically doesn't. Barriers are different too. The blood-brain barrier protects the CNS but creates a delivery problem for medications. A drug that works fine systemically may never reach therapeutic concentrations in brain tissue. The PNS has no such barrier, which is why some chemotherapies cause peripheral neuropathy as a side effect — they're hitting nerves directly.
Get the Full Details
Where People Get Confused
Autonomic nervous system territory trips people up. The ANS has both sympathetic and parasympathetic branches, and it operates through both CNS and PNS pathways. The hypothalamus (CNS) orchestrates autonomic responses, but the actual efferent signals travel through peripheral nerves to organs. When someone says "autonomic nervous system," they're referring to a functional system that spans both divisions, not a third category. Another common error: assuming all cranial nerves are PNS. Nine out of twelve are peripheral nerves in the strict sense, but the optic nerve (CN II) and olfactory nerve (CN I) are actually CNS tracts wrapped in meninges. They myelinate with oligodendrocytes, not Schwann cells. Hit them with a demyelinating disease and you get CNS-type pathology, not PNS.
Practical Application
If you're studying neuroanatomy, draw the pathways. Trace a sensory signal from a toe receptor all the way to the somatosensory cortex. Note where it synapses. The first synapse in the dorsal column-medial lemniscus pathway is in the medulla — that's CNS tissue. The peripheral nerve segment before it is PNS. Mapping it out cements the distinction better than any flashcard. For clinical work, start with the reflex exam. It's the fastest way to localize a lesion between CNS and PNS. Hyperreflexia points central. Hyporeflexia or areflexia points peripheral. Then move to sensation testing, strength grading, and imaging accordingly. Don't skip the basic exam because you have an MRI ordered — the exam tells you what kind of MRI to order. The CNS versus PNS framework isn't perfect. There are transition zones, mixed pathways, and edge cases that blur the line. But as a working model for diagnosis, study, and treatment planning, it holds up well enough that every neurology resident learns it in year one and uses it every day after.