What Central Service Technical Training Actually Looks Like
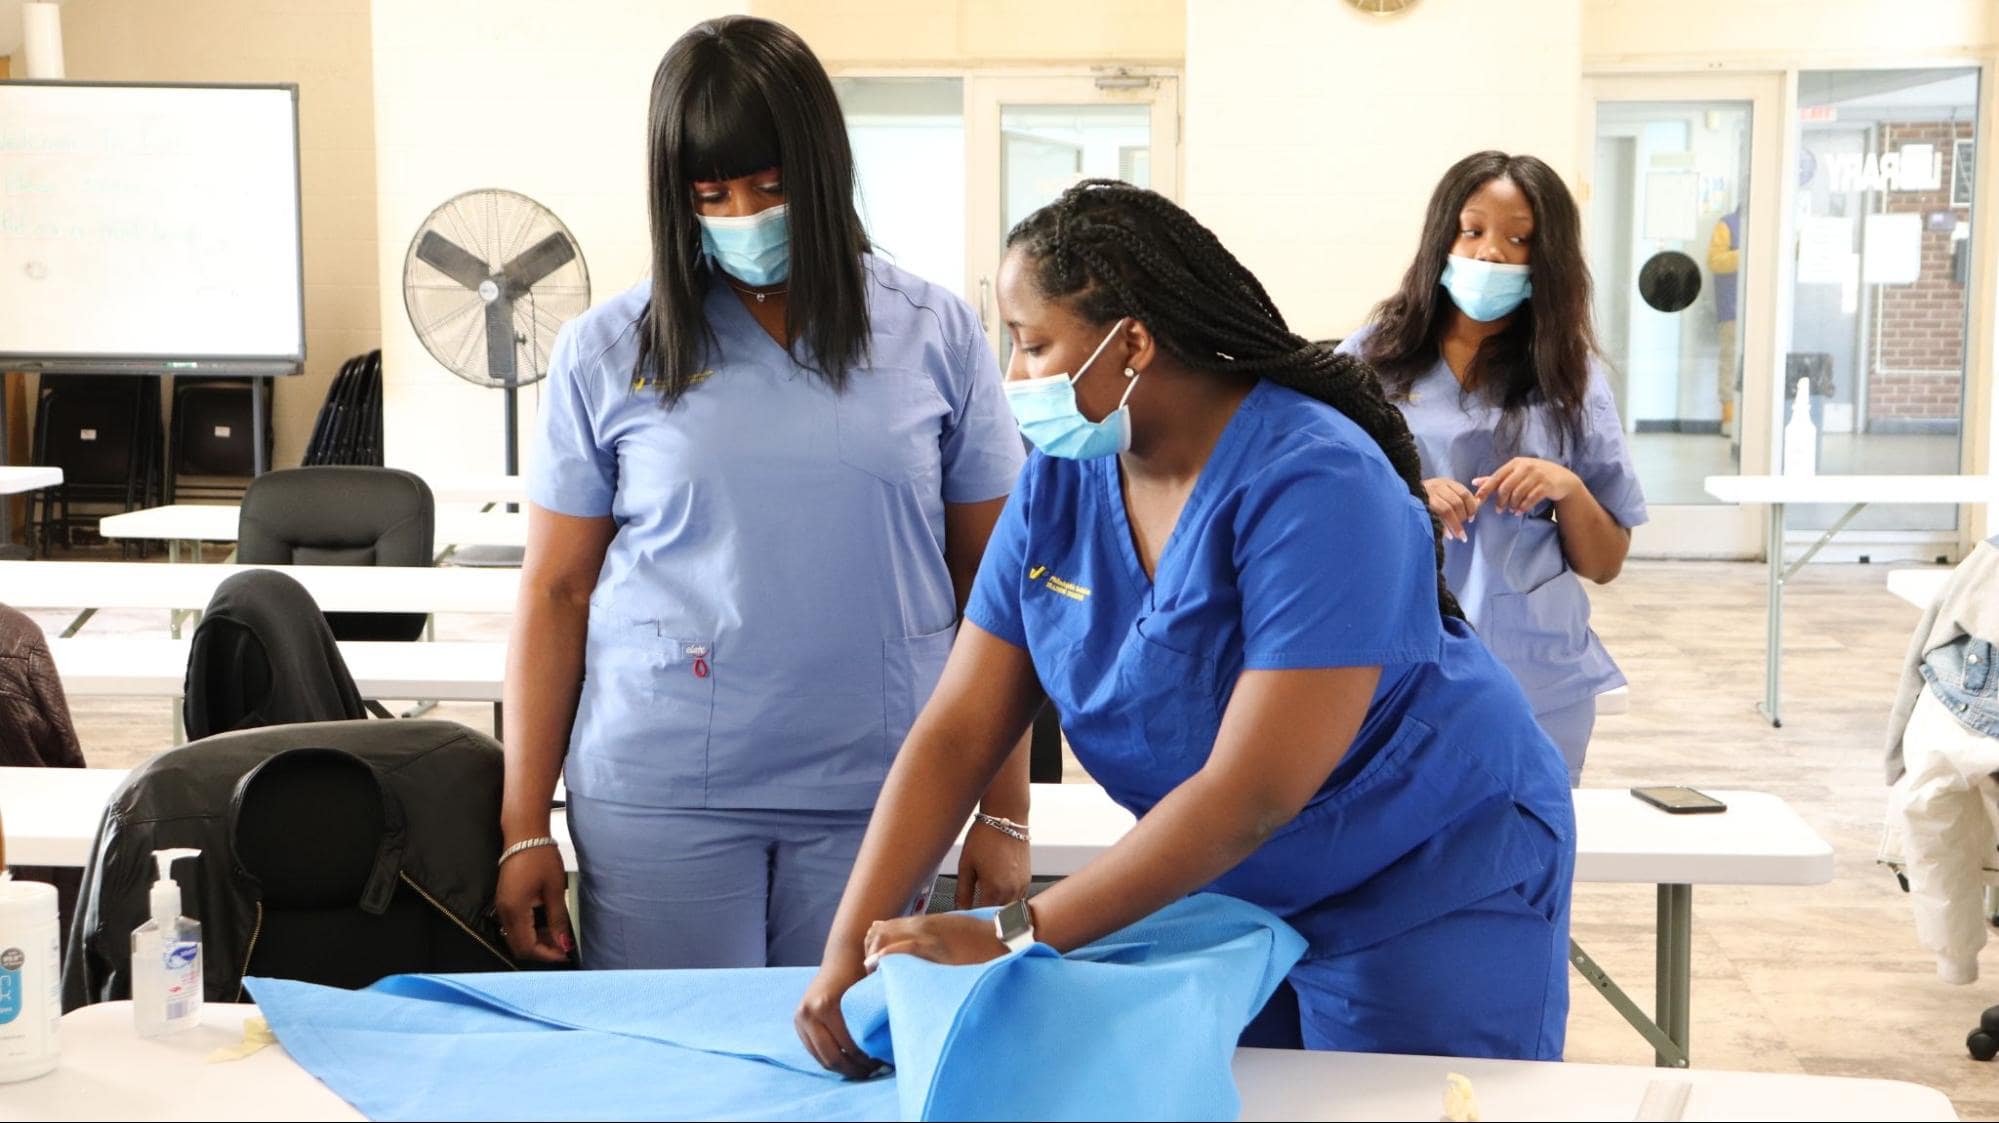
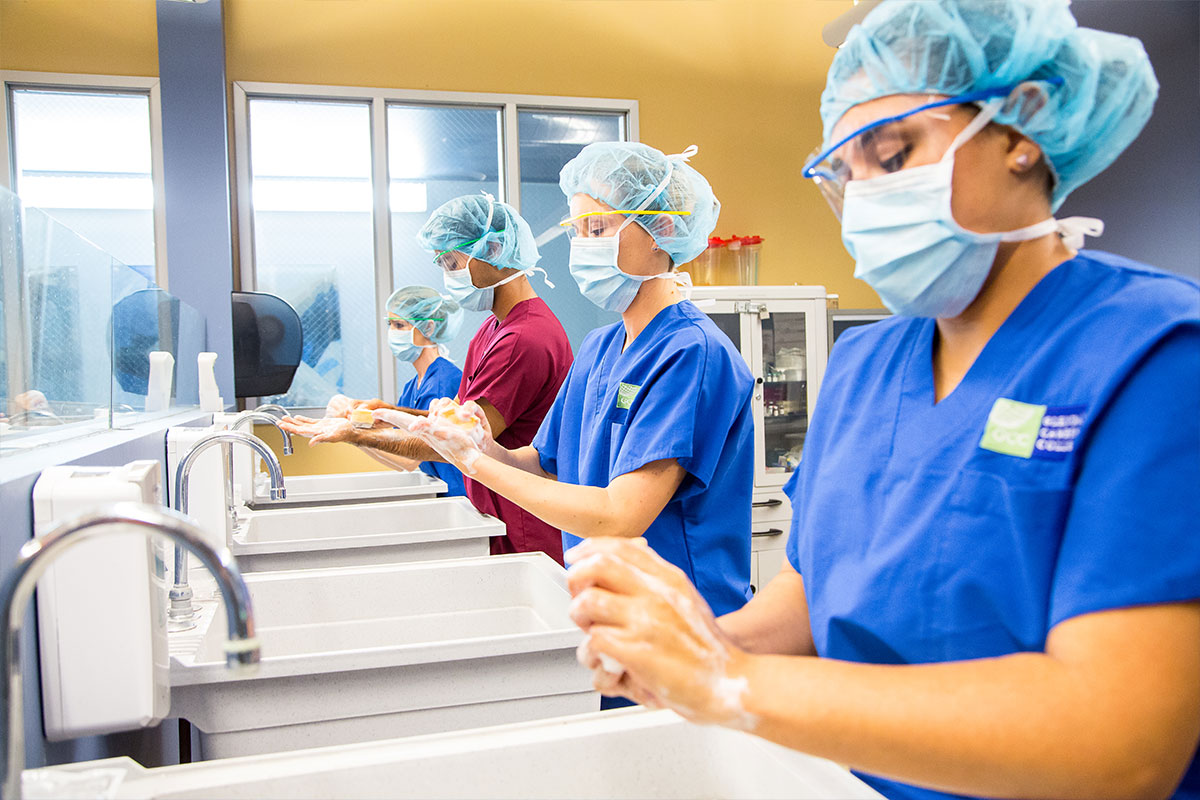
Central Service Technical Training covers the skills needed to clean, sterilize, assemble, and distribute medical instruments in a healthcare facility. It is not glamorous work, and anyone who tells you otherwise has never spent eight hours on their feet reprocessing orthopedic tray sets. The training itself typically runs 160 to 240 hours depending on the program and employer requirements, mixing classroom instruction with hands-on clinical rotation. You learn instrument identification, decontamination procedures, packaging methods, sterilization cycles, and quality assurance documentation. That last part is where most people get sloppy, and it is also the part that shows up in every audit failure I have ever seen. I went through a formal CST training program about eight years ago after being hired as a sterile processing tech with no prior experience. The classroom portion was manageable. The equipment manual sections were dense but straightforward. What caught me off guard was how much of the training hinges on reading and following manufacturer instructions for use, or IFU, without questioning them even when they seem wrong. I spent my first two weeks on the floor watching a veteran tech override an IFU sterilization time because "the tray always gets through" in a standard cycle. That approach works until it doesn't, which is exactly what happened when a laparoscopic instrument set failed to sterilize due to biofilm buildup inside a scope channel that had been shortened on purpose for years. I learned to flag IFU discrepancies through the proper channels instead of improvising around them. The core curriculum breaks down into a few overlapping areas. Instrument identification and assembly covers everything from basic hemostats to complex robotic surgical tooling. Decontamination training teaches manual cleaning, ultrasonic cleaning, and washer-disinfector operation. Packaging and labeling involve understanding wrap materials, rigid containers, chemical indicators, and lot tracking. Sterilization covers steam, low-temperature plasma, and ethylene oxide cycles, along with biological and chemical monitoring protocols. A few programs also include endoscope reprocessing, though that often requires separate certification depending on state regulations and facility policy. Quality assurance and documentation round out the program, teaching you how to maintain sterilization logs, track instrument lifecycle data, and prepare for accreditation surveys from organizations like AAMI and The Joint Commission.
One thing beginners consistently underestimate is the documentation workload. A single instrument tray can generate multiple records: cleaning verification, packaging check, sterilizer load ID, chemical indicator results, biological spore test logs, and release signatures. Most training programs spend maybe an hour on this. In practice, you could easily spend ten minutes per case just on paperwork for complex instruments. I started keeping a pocket notebook during training to track the exact fields each facility required, because the forms vary enough between hospitals that memorizing one set does not help you at another workplace. It cut my first-week errors in half. There are several training pathways available. Community colleges offer associate degree programs in sterile processing technology, usually spanning two semesters with embedded clinical hours. Hospital-based apprenticeship programs train you internally while you work, which means you get paid but the classroom instruction tends to be less comprehensive. Third-party vendors like Laerdal, STERIS, and 3M run their own CST training courses, often tied to their equipment and consumable products, so there can be a bias toward their specific solutions. Certification through HSPA or IAHD is not always required but it helps with job placement and pay scale at most facilities. If you are evaluating programs, compare the actual clock hours of hands-on sterilizer operation, not just total program length. Some online-heavy programs list 200 hours but only assign twenty of those to live equipment work. Here is a realistic edge case I ran into that most training manuals barely mention. We received a shipment of flexible endoscopes from a specialty surgery center that had been stored improperly for six months in a humidity-controlled room that was actually running at above-optimal moisture levels. The training teaches you to visually inspect every instrument before processing, but it does not prepare you for what adhesive degradation on scope channels looks like after long-term moisture exposure. The O-rings were tacky, the rubber seals had started to delaminate, and a few channels were partially collapsed. Running these through a standard reprocess cycle would have pushed degraded particles into the patient line. I flagged the entire batch for vendor replacement and documented the seal condition with photographs, which became the template our department now uses for incoming scope inspections from external facilities. The training gave me the inspection checklist. Experience taught me what to look for beyond the checklist.
The main limitation of most CST training programs is that they cannot replicate the pace of a real hospital central service department. A training sterilizer runs one or two cycles per day while a busy facility runs sixty or more. You do not get exposure to overflow situations, simultaneous tray demands, or the kind of instrument damage that only appears when you are handling four hundred cases a week. Some programs address this by having students shadow experienced techs during high-volume days, but that depends entirely on the cooperating facility being willing to let a trainee stay out of the way. If your program does not include that, you will fill in the gap on your own after starting work, which is fine but slows down your initial competency timeline. Another under-taught area is troubleshooting sterilization failures. When a biological indicator comes back positive, the training tells you the steps: quarantine the lot, recalculate, reculture. It does not teach you how to systematically determine whether the failure came from improper cleaning, incorrect packaging, a sterilizer malfunction, or compromised steam quality. I once traced a recurring negative BI result to a faulty steam trap that was allowing condensate into the chamber, which was then microbially contaminating the load during the dry phase. The issue looked like a cleaning problem until we pulled the sterilizer maintenance logs and compared them to the failure pattern. Learning to read equipment service data alongside your processing data is something you pick up slowly on the job. Make sure your training gives you at least a basic foundation in sterilizer mechanics, because that knowledge separates people who replace loads blindly from people who actually solve problems. If you are looking for training materials or a program, the main resources are your state health department's approved CSPD training list, AAMI standards documents, and the HSPA and IAHD certification exam prep courses. Several community colleges also publish their course syllabi online, which you can review before enrolling to see if the curriculum matches what your local employers actually expect. There is no single downloadable manual that covers everything because the field changes enough with new instruments and updated IFUs that any static document becomes outdated within a year. Your best bet is a current textbook, the latest AAMI guidelines, and direct mentorship from someone who has been through a full accreditation cycle.
Get the Full Details

I should also mention that not everyone needs formal training. Some facilities hire people with no background and train them internally, which works if the facility has a solid in-house program and adequate staffing to support it. Others require certification before hire, especially larger hospital systems and ambulatory surgery centers that contract with insurance networks requiring documented credentials. Know what your target employers require before you invest in a program. Wasting a thousand dollars on a course that does not align with local hiring standards happens more often than you would think. The work is physically demanding, repetitious, and critical to patient safety. The training is adequate if you pay attention to the documentation and equipment troubleshooting sections and ask questions when something does not match what you saw in the classroom. The people who do well in this field are not the ones who memorize the fastest. They are the ones who notice when a tray looks wrong, who read the IFU before opening the box, and who understand that a sterilizer is a precision medical device, not an appliance. Central Service Technical Training gets you started. The rest comes from paying attention every single shift.