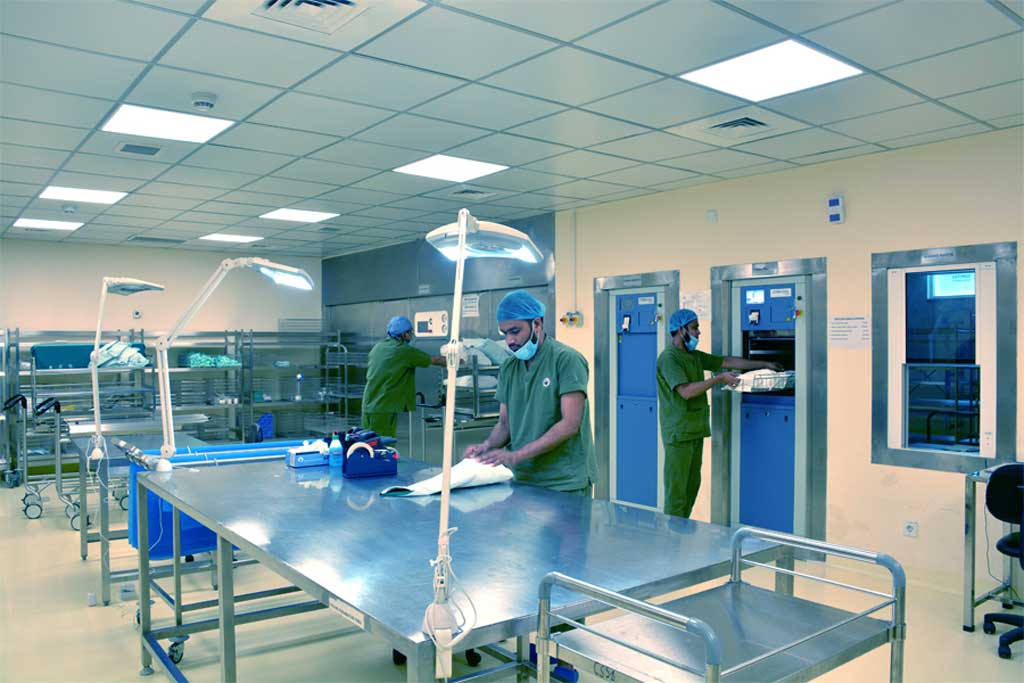
The Actual Workflow of a Functional CSSD
The Central Sterile Supply Department is essentially the gatekeeper between a used instrument tray and a surgeon who needs it to work. It sounds like a simple cleaning and packaging operation, but anyone who has worked in a hospital knows that the gap between "looks clean" and "actually sterile" is where everything falls apart. The department handles decontamination, inspection, packaging, sterilization, and distribution of surgical instruments across an entire facility. Here is how the process actually moves in practice. Instruments arrive from the OR in closed containers. They get unloaded in the dirty zone, taken apart if needed, and then go through manual cleaning and ultrasonic baths. After that, they move to inspection, where you are checking for rust, broken tips, and functioning hinges. Then comes packaging — wrap or rigid containers — followed by sterilization in an autoclave or other validated method. Finally, they go to sterile storage until picked up for a scheduled case. The sequence matters because crossing back from clean to dirty is a violation that takes serious effort to correct.
Central Sterile Supply Department: Setting Up the Workflow Correctly
The layout has to follow a unidirectional flow. Dirty instruments enter one side and sterile sets exit the other. If your department has two-way traffic where staff carry used instruments past already packaged trays, you are creating cross-contamination risk whether you mean to or not. I have seen this happen in older hospitals where the physical space was never redesigned to support the workflow. The fix is usually a physical barrier or a strict scheduling system that separates dirty and clean movements by time rather than space. It is not elegant, but it works when renovation is not an option. The cleaning stage is where most departments cut corners. Manual cleaning with brush and detergent is still the foundation, even with ultrasonic cleaners available. Ultrasonication removes debris from hard-to-reach areas like lumen channels and hinged joints, but it does not dissolve protein that has baked onto steel. I once dealt with a recurring sterilization failure on a set of laparoscopic instruments where the mechanical and chemical indicators all passed but biological cultures came back positive. The problem was dried blood inside the scope channel that ultrasonication alone could not dislodge. Switching to a neutral-pH enzymatic detergent with a longer soak time before the ultrasonic step eliminated the issue. That was a three-month investigation to figure out. Instrument maintenance is another area where departments quietly fail. A hemostat with a stiff spring does not close properly, which means the wrap cannot be secured tightly and the sterile barrier is compromised. Saw a lot of this in older facilities where maintenance budgets got trimmed. Implementing a simple check-before-pack protocol where every instrument gets a function test takes about thirty seconds per tray and prevents a significant number of distribution errors. Pair that with regular lubrication schedules for hinged tools and you cut down on the attrition rate considerably.
Sterilization Methods and When They Break Down
Steam autoclaving is the workhorse. It is fast, effective, and relatively inexpensive per cycle. But it requires instruments to be dry before packaging and it cannot handle heat-sensitive materials. Ethylene oxide gas works for delicate items but has a long cycle time of six to eighteen hours and requires a lengthy aeration period to remove toxic residue. Hydrogen peroxide plasma is faster than EtO and leaves no residue, but it is expensive and cannot process instruments wrapped in linen or paper, nor can it handle long narrow lumens longer than a certain depth. Understanding these limitations is the difference between selecting the right method and shipping out a compromised set. A biological indicator test should run at least weekly on each sterilizer, not just rely on mechanical prints and chemical strips. Mechanical indicators tell you the machine reached temperature and pressure. Chemical indicators tell you the item was exposed to the sterilization process. Biological indicators with Geobacillus stearothermophilus spores tell you whether actual microbial death occurred. If your department only uses the first two, you are operating on assumption rather than verification. I had a situation where an autoclave gasket was slowly leaking — the mechanical readout looked fine because the sensor was downstream of the leak point. The biological indicator caught it two days before the gasket failed completely. That one piece of data saved us from potentially distributing non-sterile instrument sets to the OR.
Get the Full Details

Packaging and Storage Realities
Packaging is not just wrapping. The material you choose determines shelf life, sterility barrier integrity, and compatibility with your sterilization method. Peel pouches, paper-plastic pouches, woven wraps, and rigid containers each have specific use cases. A rigid container system is more expensive upfront but reduces labor time per tray by roughly forty percent over the long run and provides a more reliable barrier than wrap. The trade-off is that they require validation for each load configuration and add weight to transport. Storage conditions matter more than most departments track. Temperature should stay between fifty-five and eighty degrees Fahrenheit and relative humidity below seventy percent. When humidity runs high, wrapper materials absorb moisture and lose their sterility barrier properties before the tray is ever opened. I worked in a facility where the sterile storage room shared a wall with a boiler room. The temperature in that space regularly exceeded the recommended range during winter months when the heating system cycled on. We moved the storage shelving six feet away from the shared wall and installed a small ventilation fan. The problem was not obvious from the outside but the effect on wrap integrity was measurable. Shelf life labeling is another area of inconsistency. Many facilities use arbitrary dates like seven or fourteen days for wrapped trays without considering actual storage conditions or wrapper type. The relevant standards tie shelf life to the storage environment and the packaging material, not a blanket rule. If your sterile storage room is properly controlled, some packaging types can reliably maintain sterility for up to six months. If the environment fluctuates, that drops to days. Write your policy around monitored conditions, not convenience.
Documentation and Compliance That Actually Works
Every sterilization cycle needs a record: load number, instrument tray identification, cycle parameters, operator initials, and biological indicator results. Modern facilities use barcode scanning systems that log this automatically. Older departments still rely on paper logs, which introduces transcription errors and makes traceability nearly impossible during an outbreak investigation. If you are stuck with paper, at minimum use pre-printed cycle log sheets organized by date and sterilizer unit. Handwriting that can be read six months later is a genuine challenge. FDA guidance requires traceability for implantable devices. If a surgical implant goes into a patient, you need to be able to every instrument that touched that implant back to the specific sterilization cycle it went through. This is not aspirational — it is a regulatory requirement. The implementation usually involves assigning unique lot numbers to implant trays and linking them to cycle records. Facilities that wait until an inspection to figure this out typically scramble for weeks.
Staffing and the Human Factor
The CSSD runs on people who understand both the technical process and the consequences of getting it wrong. Turnover is high in many departments because the work is repetitive, physically demanding, and rarely recognized by the rest of the hospital. Staff who have been there for years develop shortcuts that save time but introduce risk. A tray counted as twelve pieces when it should be thirteen means a surgeon opens it in the OR and finds a missing instrument mid-procedure. Those moments create cascading delays that ripple through the entire surgical schedule. Recurrent training on instrument identification and assembly is more valuable than another generic infection control module. Every new hire should be able to disassemble and reassemble a basic surgical tray blindfolded, quite literally. I found that having staff quiz each other on instrument names and functions during shift changes kept knowledge fresh without requiring formal training sessions. It also surfaced gaps — people realized they had been calling instruments by the wrong name for years and assembling trays incorrectly without anyone noticing. The department is often seen as a cost center rather than a clinical function. That perception affects budget, staffing, and equipment replacement timelines. But the CSSD directly determines whether a hospital can safely run an operating room. When sterilization fails, surgeries get cancelled. When instruments are missing or broken, procedures get delayed. The department does not generate revenue, but it enables every revenue-generating procedure in the building. That relationship is straightforward if anyone takes the time to see it.