Writing therapy goals that actually get documented correctly
Most occupational therapists I work with struggle with one thing: turning a vague clinical wish into a goal that survives insurance review and also describes something the kid can genuinely do. The problem isn't knowing what cerebral palsy is. The problem is precision under pressure. A goal like "improve fine motor skills" gets rejected because it means nothing on paper. Here's how I write them so they stick. I always start with the context, not the impairment. That means I describe the activity first, then the accuracy or speed criterion, then the timeframe. The order matters because parents and reviewers parse the sentence differently depending on where you put the measurable part. If the measurable outcome comes last, people miss it. I put it in the middle and reinforce it at the end.
Cerebral Palsy Occupational Therapy Goal Examples
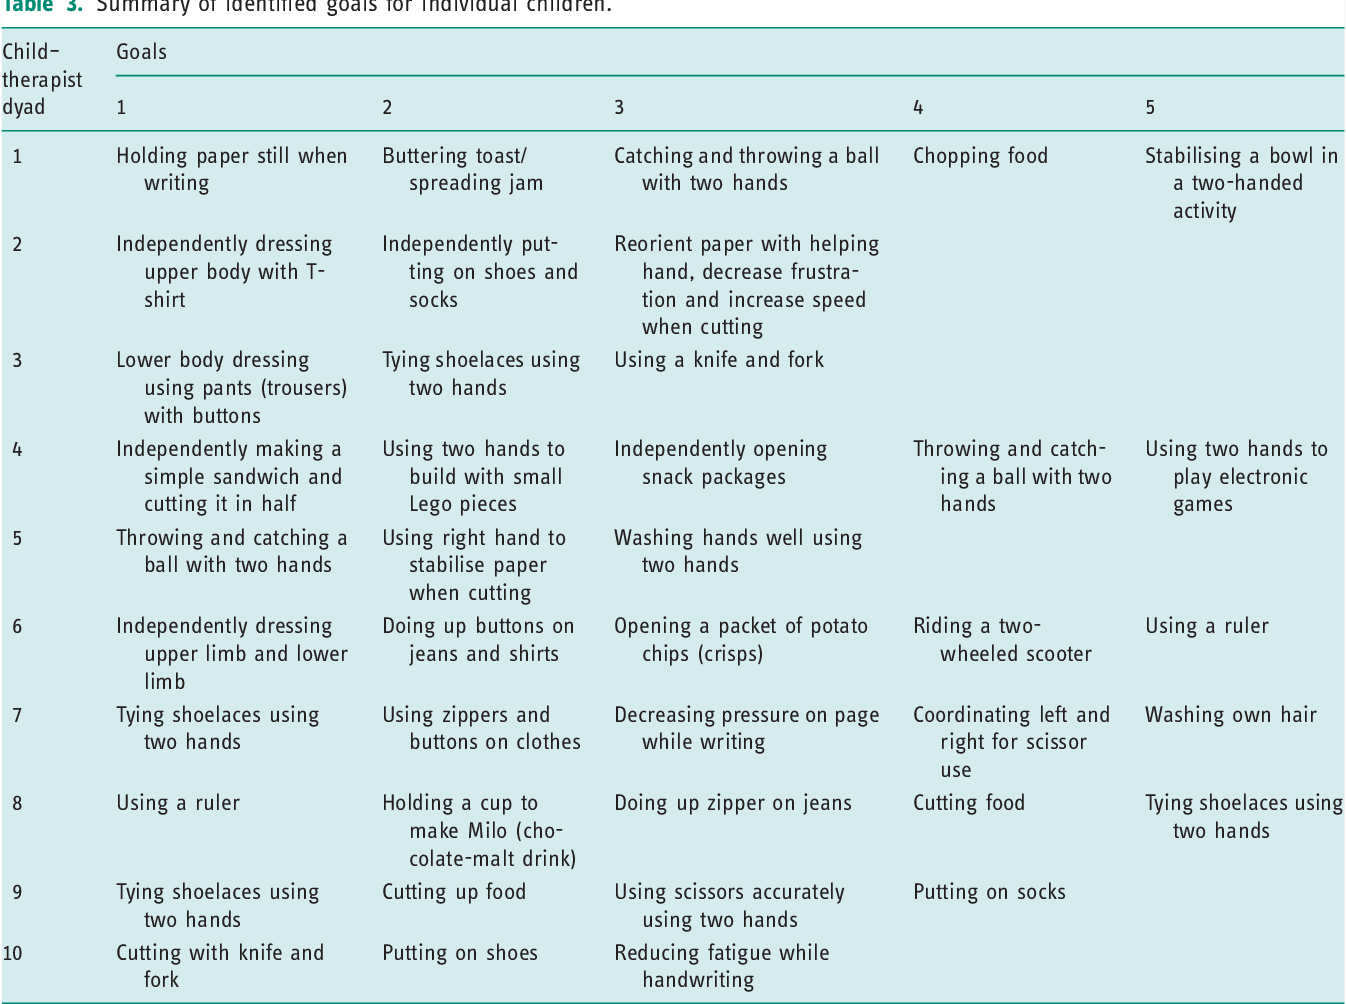
Here are some that have actually worked in my notes over the years. Not all of them are appropriate for every child, but they follow a structure that holds up to scrutiny: When given a 10-piece zippered bag and a set of 5 buttons, the client will independently fasten 4 of 5 buttons and close the zipper with a sequential hand movement pattern within 3 minutes, with no more than verbal cueing, in 4 out of 5 opportunities across two consecutive sessions. During a supervised meal, the client will use an adapted utensil (weighted fork with a built-up handle) to transfer food from plate to mouth independently for at least 8 of 10 bites, maintaining a stable wrist position and completing the task within 20 minutes, across three consecutive therapy days.
When presented with a shirt requiring overhead arm elevation, the client will independently put on the garment using a sequential dressing strategy (dominant arm first, then non-dominant) with visual demonstration only, achieving successful completion in 4 out of 5 trials over two weeks. While seated at a desk, the client will use a slant board and adaptive pencil grip to trace 5 straight lines and 3 circular shapes with a pencil held in a mature tripod grasp, producing legible marks without excessive pronation or shoulder elevation, in 3 out of 4 attempts. When participating in a self-care routine at home, the client will independently complete a modified toothbrushing sequence (wet brush, apply paste, brush all surfaces, rinse) using a built-up manual toothbrush and a non-slip mat, with only tactile prompting on the non-dominant hand, demonstrated in 4 of 5 opportunities at home over one week.
Get the Full Details
These look long because they have to be. Short goals get denied. Long goals that are specific get funded. There's a reason for that, and it's not complicated. One thing people miss about writing these goals is that the baseline matters more than the target. A lot of therapists write a good goal with a baseline that's either invented or so vague it's useless. If the baseline says "client demonstrates difficulty with fine motor tasks," insurance has no anchor point. You need a starting number. "Client currently requires maximal verbal and tactile cueing to grasp a spoon and brings food to mouth in 6 of 10 attempts" tells everyone exactly where the kid begins. Without that, the whole goal is floating. I had a kid a few years ago — severe spastic diplegia,GMFCS level III, significant upper extremity involvement on the left side. The goal was feeding independence with an adapted utensil. We picked a built-up spoon and practiced for six weeks. The kid hit the target in session every single time. Then at home, the parent reported zero carryover. The kid would just sit and wait. What was happening was the child had learned to associate the spoon with the therapist's presence and the structured therapy room environment, not with the actual act of feeding. The goal was technically met, but functionally it was worthless. The workaround was simple: we moved practice into the kitchen during actual meals, had the parent record video of feeding times, and revised the goal to include "in home dining setting with present caregiver" as part of the success criteria. It added about ten minutes per session but the carryover appeared within three weeks. The lesson wasn't complicated. Generalization doesn't happen by accident.
Another counter-intuitive thing: writing a goal too ambitious early on creates more work for everyone. I've seen therapists set a target that requires a 60% improvement in twelve weeks for a child with moderate-to-severe CP who hasn't had consistent therapy in months. The goal fails, the report looks bad, and the kid gets labeled as non-responsive when really the goal was just poorly calibrated. I'd rather write a smaller, achievable goal that's clearly documented as Phase 1. You rebuild the next goal on top of actual progress, not on hope. There's also the question of which body systems you prioritize. Upper extremity goals get written more often because they're easier to measure. But sensory processing, perceptual organization, and visual-motor integration are equally important for functional independence and they get ignored because they're harder to quantify. A child who can grasp a cup but floods when the water is too hot isn't making real progress. Document sensory tolerance as part of the goal when it's relevant. "Tolerates water at hand-washing temperature without avoidance behavior for 30 seconds" is a legitimate goal that opens doors to other interventions. The limitations are worth stating plainly. This framework works well for children who can follow multi-step directions and have some voluntary movement control. It breaks down for kids at GMFCS levels IV and V who have minimal voluntary control, because the measurable outcomes become so narrow they stop being useful for family communication. For those kids, I shift toward comfort, positioning, and participation goals rather than independence goals. "Maintains midline orientation during seated play for 10 minutes with current positioning support" is a different category of documentation, and it deserves the same level of specificity even though the function it measures is entirely different.
Insurance companies vary wildly in what they accept. Some will reject a goal that doesn't include a numeric accuracy percentage. Others want a specific timeframe. A few payers prefer process goals over outcome goals. You learn which version your local reviewers prefer by watching what gets approved and what gets sent back. Keep a running list. It saves hours of revision work later. If you want a quick reference sheet I keep updated with goal templates organized by domain — self-care, fine motor, visual-motor, sensory, and participation — I can point you toward a shared document. The core structure hasn't changed much in years. What changes is the payer landscape, and that's something you track locally rather than internationally.