What This Credential Actually Gets You
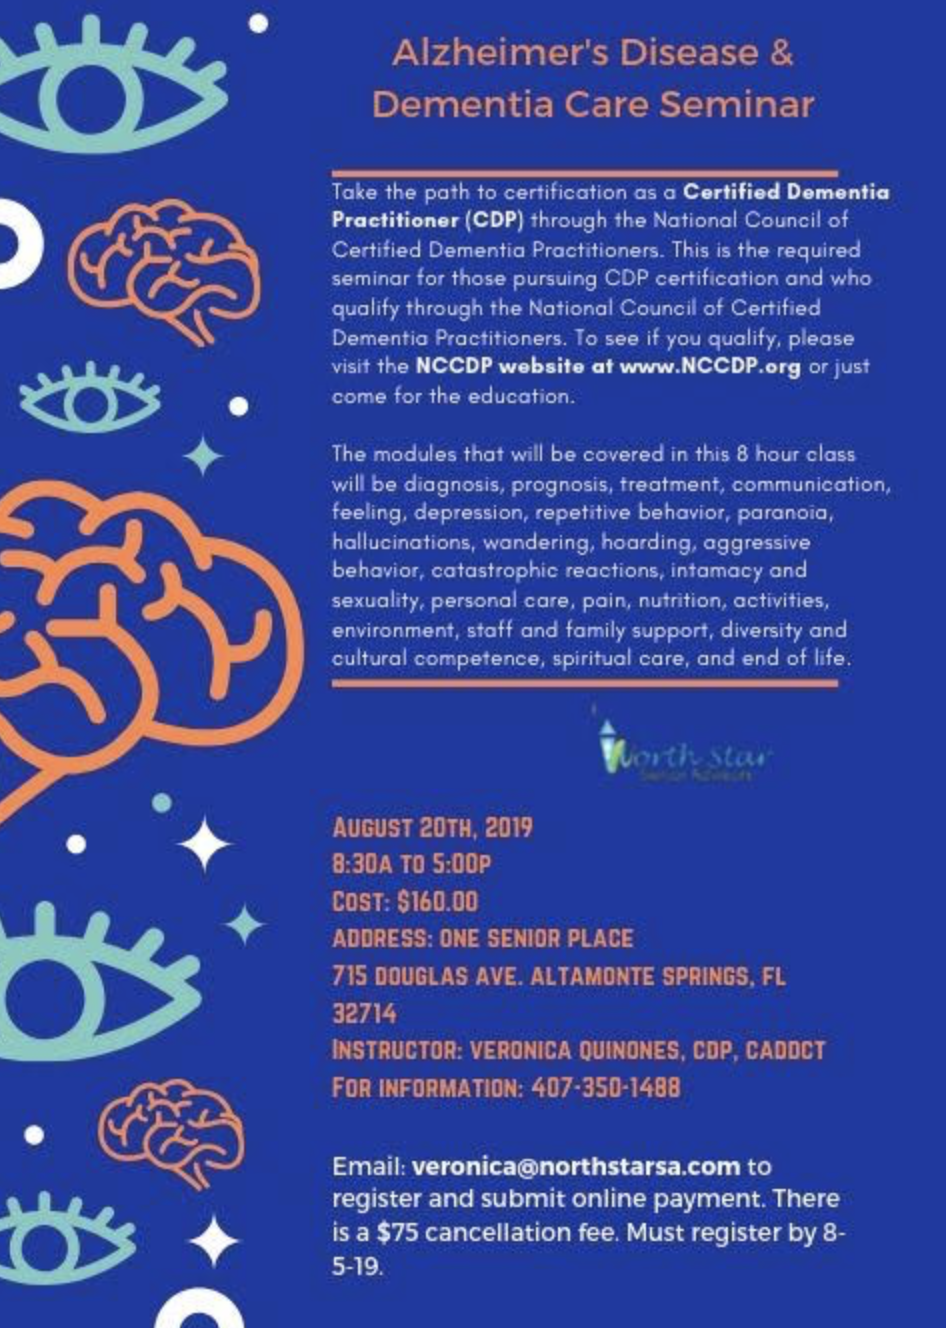
A Certified Dementia Practitioner credential isn't a license to practice medicine. It's a vocational designation that proves you've completed a structured curriculum covering cognitive disorders, communication strategies, behavior management, and quality-of-care frameworks. Most employers accept it as evidence that you understand dementia beyond basic compassion fatigue. The certification comes through the National Council of Cognitive Impairment (NCCI) or state-level gerontology organizations depending on your jurisdiction. I spent three years working memory care units before I pursued this. Here's what surprised me most: the exam doesn't test you on drug interactions or diagnostic criteria the way a nursing credential does. It tests whether you can explain to a frustrated family member why their mother refuses to bathe without making them feel judged. That's the part they don't put on the marketing materials.
Starting Your Certified Dementia Practitioner Training
The first thing you need is eligibility. Most programs require 40 hours of approved continuing education in dementia care, six months of full-time work in a setting where at least 51% of residents have a cognitive impairment diagnosis, or a combination of both. If you're a direct care aide with no formal coursework, you'll need to complete the education requirement first. There are several approved providers online, but make sure the program is NCCI-recognized or endorsed by your state's health department. The cheap $50 courses from random websites won't count toward your application. The education portion covers the big areas: neuroanatomy basics (you need to understand what happens to the hippocampus, not just that memory gets worse), the progression models of Alzheimer's and other dementias, behavioral and psychological symptoms of dementia (BPSD), person-centered care planning, and caregiver burnout prevention. The material is dense but straightforward. What trips people up is the applied component. You'll be asked to develop a care plan for a specific case study involving sundowning and aggression, then defend your choices under peer review. I had to rewrite mine twice because my initial approach relied too heavily on pharmacological assumptions rather than environmental modification.
The Work I Got Wrong Early On
Here's a specific problem I ran into during my training that the study materials barely touched. A resident in my unit, late-stage vascular dementia, would become combative only between 3 PM and 5 PM on days when the facility had activities scheduled. Standard protocol suggested reducing stimulation during that window, but that wasn't the issue. The combative episodes stopped completely on Wednesdays because the volunteer music therapy session ran at 2 PM and carried over into the aggressive window, effectively resetting his agitation cycle. The workaround was scheduling a low-key one-on-one activity starting at 1:45 PM on Tuesday, Thursday, and Friday to replicate that calming effect without needing a group session. The textbook answer would have been "modify the environment" but the real answer was understanding the temporal pattern of his triggers. This is the gap between passing the exam and actually being competent. The certification teaches you frameworks. Real practice requires you to notice when the framework doesn't fit.
Get the Full Details

Pitfalls Beginners Miss
Most people entering this field assume the hardest part is learning the content. It's not. The hardest part is unlearning the instinct to correct, redirect, or reason with someone who has lost the neural architecture to process logical inconsistency. I watched a newly certified CDP spend twenty minutes trying to convince a woman with moderate Alzheimer's that her deceased husband wasn't coming home from work because "he passed away three years ago." The woman became increasingly agitated. The CDP was technically correct. She was also completely ineffective. The certification covers validation therapy and life review techniques, but it can't simulate the emotional pressure of that moment. You have to absorb the principle that being right is sometimes the wrong clinical decision. That counter-intuitive shift separates practitioners who last from those who burn out within eighteen months. Another common mistake: treating all dementia as Alzheimer's. Vascular dementia, Lewy body, frontotemporal, and mixed etiologies present differently, progress differently, and respond differently to interventions. A behavior management strategy that works for Alzheimer's can worsen symptoms in Lewy body. The exam tests this distinction but many candidates gloss over it because Alzheimer's is more prevalent and more covered in introductory courses.
How the Application Process Actually Works
After completing the required education hours and accumulating your work experience verification, you submit your application through the certifying body's portal. You'll need employer signatures confirming your job duties and patient population. Processing typically takes 2-4 weeks. Then you schedule the exam, which is multiple choice with 150 questions and a three-hour time limit. The pass rate hovers around 78-82% for first-time takers according to recent NCCI data. The exam fee runs approximately $250-$325 depending on whether you're a member of the certifying organization. State-level credentials may cost less but offer narrower recognition. If you plan to work across state lines or for national healthcare systems, the NCCI certification has broader portability.
When This Certification Doesn't Help
I need to be blunt about the limitations. This credential does not qualify you to diagnose, prescribe, or provide clinical therapy. It will not substantially increase your salary in most entry-level direct care positions, though it often becomes a requirement for lead or charge aide roles. Some facilities use it as a checkbox for federal compliance surveys rather than as genuine professional development. If you're pursuing this primarily for a pay bump, the return on investment is modest unless you're already on a management track. The credential also expires. Most pathways require 20 continuing education credits every two years, with at least 10 focused on dementia-specific topics. If you move into administrative work and stop encountering residents with cognitive impairment directly, maintaining the certification becomes tedious without providing proportional value. An alternative to consider is the dementia care specialty certification through the National Alliance for Care at Home or the Gerontological Advanced Practice certificates if you're pursuing a nursing path. Those carry different weight depending on your career trajectory. The CDP designation sits in a middle ground—respected in long-term care and memory care communities, less recognized in hospital or acute settings.

What to Do After You Pass
Getting certified is the easy part. The harder part is staying current. Dementia care research moves faster than most continuing education requirements demand. New findings on non-pharmacological interventions for agitation, updated guidelines on delirium differentiation, and evolving best practices around antipsychotic reduction in residential settings all deserve ongoing attention. I dedicate roughly three hours per month to reading peer-reviewed journals and attending webinars from the Alzheimer's Association and the Society for Social Work in Dementia Care. It's not glamorous. It keeps you from becoming the person who recommends the same tired redirection techniques while missing newer evidence-based approaches. The certification opens doors to consultation roles, staff training positions, and quality assurance work in memory care units. I transitioned from direct care to a training coordinator role within two years of getting certified, and my annual salary increased by approximately $8,000. That's not extraordinary but it's meaningful when you're coming from direct care wages. The real payoff comes in the reduced turnover and burnout rates among the teams I help train, which is something no salary figure captures.