
Getting a 12-lead EKG right is harder than the textbooks make it look
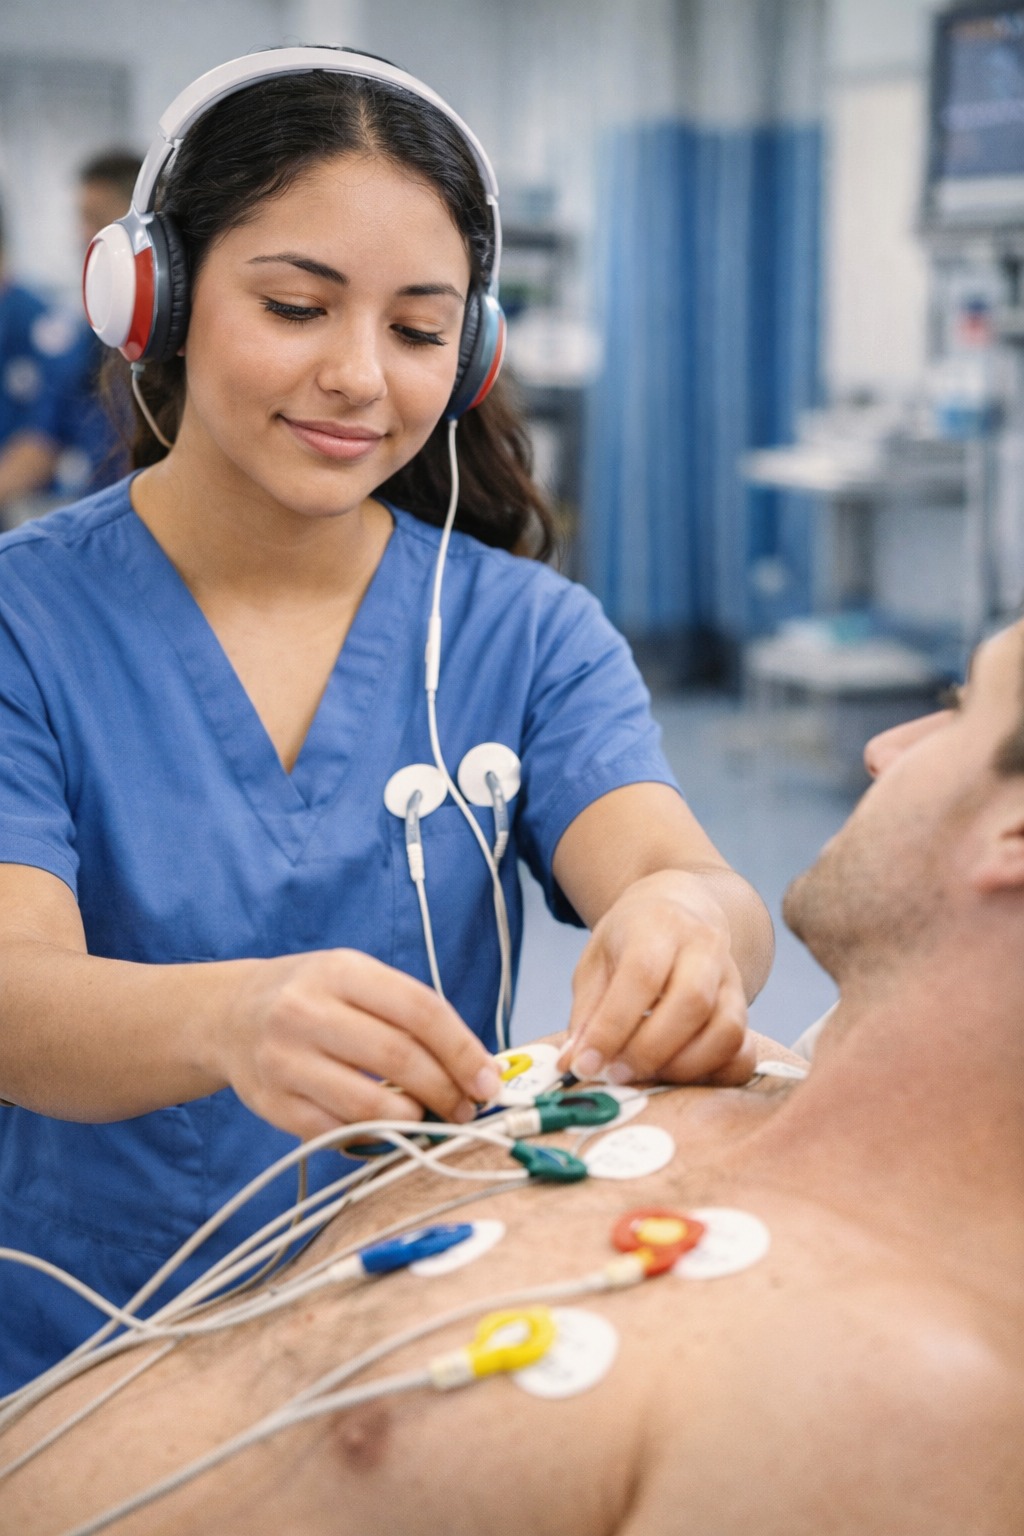
I spent about six years running EKGs in a cardiology clinic before moving into training. The patients who show up with the worst-looking tracings aren't usually the ones with the most obvious pathology. They're the ones with movement artifact, lead placement errors, or equipment that hasn't been grounded properly. Certified Ekg Technician Training should cover that stuff from day one, but a lot of programs gloss over it because they want to get students through the NHA CCT exam as fast as possible. The NHA CCCT exam tests three things: procedure knowledge, infection control, and interpreting tracings. The hands-on portion is where most people fall apart. You'll be given a manikin or a live volunteer, you'll have seven minutes to place all ten electrodes correctly, attach the leads, and produce a tracing that passes technical quality standards. Technical quality means no baseline wander, no muscle artifact, no inverted P waves in lead II, and proper calibration marks at 25 mm/sec and 10 mm/mV. I've seen people who could interpret atrial fibrillation in their sleep fail the placement portion because they put the right leg electrode on the wrong ankle. The NHA doesn't tell you exactly which ankle they want in the study guide, but the standard is right lower quadrant, near the iliac crest. If you put it on the medial malleolus, you'll get ground loop noise that looks like atrial flutter and the examiner will mark it wrong.
How to Actually Prepare for the Exam
Most study guides focus on rhythm interpretation. That's important, but it's only about 40% of the exam. The rest is procedure. Here's what I recommend doing differently than most programs suggest. First, practice placing leads on yourself until you can do it blindfolded in under three minutes. Not fast — accurate. I have students measure their own intercostal spaces with calipers, not eyeballs. The fourth intercostal space at the right sternal border is easy. The left precordial leads? People consistently place V4 two ribs too high or V5 too far anterior. Measure every time. Second, learn to recognize artifact types and fix them in real time. Baseline wander comes from patient movement or poor skin preparation. Muscle tremor looks like fibrillatory waves but the patient is anxious or shivering. Power line interference is exactly 60 Hz and shows up as consistent vertical lines across all leads. If you can't distinguish these during the exam, you'll waste time trying to interpret a tracing that needs re-recording instead.
Third, understand EKG paper math cold. Paper speed is 25 mm/sec unless stated otherwise. Each small box is 0.04 seconds. Each large box is 0.20 seconds. R-R interval method for heart rate: 300 divided by the number of large boxes between R waves. This only works for regular rhythms. If the rhythm is irregular, you count the number of QRS complexes in a six-second strip and multiply by ten. I've had students try to use the 300 method on atrial fibrillation and get flagged for the wrong answer every time.
Get the Full Details
What Most Programs Get Wrong
The biggest gap I see in training programs is that they don't teach students how to handle difficult patients. A patient with bilateral mastectomy, severe arthritis, , or constant tremor isn't a hypothetical scenario. It's a Tuesday. The NHA exam doesn't test this directly, but it comes up in clinical practice immediately after certification, and employers notice when new hires have never dealt with anything outside the standard case. Here's a specific example from my clinic. A patient came in with a history of left mastectomy and lymph node dissection. Standard protocol says avoid the left arm for blood pressure and IV access. For EKG placement, that meant I couldn't use the standard left arm lead position. I moved the LA electrode to the left shoulder, just distal to the acromion process, and kept the left leg electrode on the left lower quadrant as usual. The tracing came back technically adequate, though the QRS axis was slightly shifted because the lead vector changed. The patient needed a repeat EKG six months later for comparison, and I made sure the modified placement was documented on the tracing itself so the cardiologist knew what they were looking at. That kind of problem-solving doesn't come from memorizing the NHA study guide. It comes from doing real EKGs under supervision.
Using Technology During Training
There are simulation apps and EKG practice platforms available now. Some are decent. The ones I've used that actually help are the ones that show you the tracing first, then ask you to identify the rhythm, then show you what common misreads look like. The ones to avoid are the gamified apps that make it too easy by giving you perfect sinus rhythms every time. Real patients don't do that. I recommend downloading free EKG strips from the California Healthcare Foundation or Medtronic's teaching archives. These are actual clinical tracings, not generated examples. The artifacts, the baseline issues, the borderline normal findings — it's all there. Practice interpreting these before you touch a patient.
The Interpretation Portion — Where People Lose Points
The NHA exam gives you about 90 multiple choice questions on interpretation. Most people underestimate how fast they need to work. You get roughly 90 seconds per question if you're going to finish on time. That means you can't sit and stare at a tracing trying to find every abnormality. You need a systematic approach. Rhythm first. Look at lead II. Is it regular? Count the P waves. Are there more P waves than QRS complexes? Then rate. Is the ventricular rate between 60 and 100? Then axis. Then intervals. Then hypertrophy. Then infarction pattern. That order matters because missing the rhythm means you'll misinterpret everything else. A paced rhythm changes the entire appearance of the QRS complex and makes axis and hypertrophy assessments unreliable anyway. The most commonly missed question type is distinguishing sinus arrhythmia from first-degree AV block with dropped beats. Sinus arrhythmia varies with respiration and the P wave morphology stays identical. First-degree AV block has a prolonged PR interval greater than 200 ms in every beat. If you don't measure the PR interval on every strip, you'll miss it. I tell my students to grab a piece of paper, hold it up to the screen, and literally count the small boxes between P wave onset and QRS onset. It takes three seconds and it saves you from guessing.

After You Get Certified
Certification is the beginning, not the end. The EKG tech role varies wildly depending on where you work. In a hospital telemetry unit, you're monitoring continuous strips and recognizing acute changes. In a cardiologist's office, you're doing resting EKGs and stress test setups. In a mobile phlebotomy or home health company, you're dealing with uncontrolled environments — poor lighting, limited space, patients who aren't prepped for the procedure. The skills that matter most after certification aren't in the exam review books. They're in knowing how to explain what you're doing to an anxious patient, how to document modified placements, and how to recognize when a tracing is uninterpretable and needs to be repeated with a different method. I see a lot of new techs who can name every dysrhythmia but can't figure out why their tracing has 60 Hz interference. It's usually the patient's hand touching the metal bed frame or the cable being routed parallel to a power cord instead of across it. If you're going through Certified Ekg Technician Training right now, practice on real people as much as possible. The manikins don't move. Real patients do. And the difference between a passable tracing and a diagnostic-quality one is usually three inches of electrode placement and twenty seconds of skin prep.



