
The mechanics of why your arm hurts when your neck is the problem
Cervical radiculopathy happens when a nerve root in your neck gets compressed or irritated, usually from a herniated disc or a bone spur pressing on the nerve as it exits the spine. That pressure causes the classic symptoms: sharp pain that travels down the shoulder, arm, or hand, tingling in specific fingers, and sometimes weakness that makes simple things like gripping a coffee cup feel impossible. The symptoms map directly to which nerve root is affected, which is why the diagnosis matters before you start any exercise program. The C6 nerve root typically refers pain down the thumb side of the forearm. C7 hits the middle finger. C8 involves the ring and little fingers. Getting this mapping right determines everything about treatment. A patient with C6 radiculopathy doing exercises targeted for C8 isn't just wasting time—they're likely aggravating the actual problem. Most cases improve within six to eight weeks without surgery, but the wrong exercises or poor progression can extend that timeline significantly or make symptoms worse.
Cervical Radiculopathy Exercises Physical Therapy
There are three categories of exercises that actually move the needle here: nerve gliding, isometric strengthening, and scapular stabilization. Most physical therapists will cycle through all three, but the order and timing depend on whether you're in the acute phase or the rehabilitation phase. Nerve gliding exercises are designed to help the compressed nerve move more freely through the surrounding tissues rather than staying stuck and inflamed. The key upper extremity nerve glides for cervical radiculopathy are the median nerve glide for C6-C7 issues, the ulnar nerve glide for C8-T1 problems, and the radial nerve glide when the posterior arm and forearm are involved. Here's how the median nerve glide actually works: start with your arm at your side, then extend the elbow, bend the wrist backward, and extend the thumb. Then reverse the sequence—bend the wrist forward, flex the elbow, and bring the shoulder into external rotation. It sounds complicated, but the rhythm is usually four to six repetitions, two to three times per day. The movement should feel like a gentle stretch, never sharp pain. If you feel increased tingling during the glide, you're going too far and need to reduce the range of motion. A common mistake I see constantly is patients holding the end position and pulsing or bouncing. That's not gliding—that's agitating the nerve. Nerve tissue doesn't tolerate repetitive microtrauma well. Each repetition should be smooth and controlled, taking about two seconds in each direction. Most patients see improvement in symptom frequency within two to three weeks of consistent daily practice, though the nerve can take six to twelve weeks to fully calm down after the compression is relieved.
Isometric neck strengthening
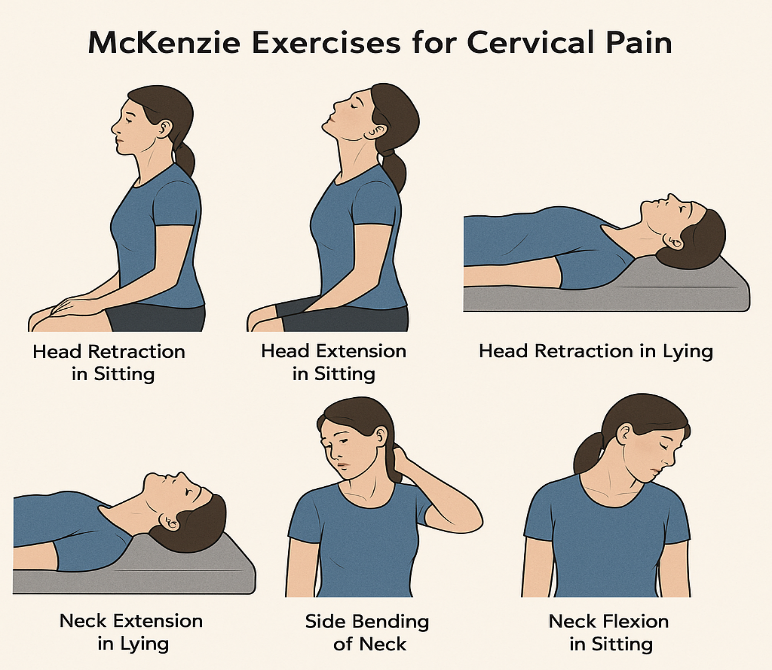
Isometric exercises involve contracting the neck muscles without moving the joints, which means less irritation to the compressed nerve while still building the stabilizing musculature that protects the cervical spine. The four fundamental positions are: pressing your forehead into your palm for anterior resistance, pressing the back of your head into your hand for posterior resistance, pressing your temple into your hand on each side for lateral flexion resistance, and a gentle chin tuck hold against light finger pressure. Hold each contraction for five to ten seconds, rest for five seconds, and repeat five to ten times per direction. Start with two rounds per day and work up to three as tolerance allows. The intensity should be moderate—you're looking for muscle fatigue, not pain. If the exercise reproduces your radiating arm symptoms, the compression is still too acute for strengthening work and you should step back to pure nerve gliding and pain management only. Isometrics are generally safe across most radiculopathy severities because there's no joint movement to further narrow the neural foramen, but that doesn't mean you should push through radiating pain. The radiating symptoms are your nervous system telling you the nerve root is still under threat.
Get the Full Details
Scapular stabilization work
This is the category most patients skip and most therapists emphasize once the acute pain settles. The muscles around your shoulder blade—lower trapezius, serratus anterior, rhomboids—control the position of your entire shoulder girdle, which directly affects cervical spine alignment. When these muscles are weak, your neck muscles compensate by overworking, which increases compression on the nerve roots. The basic exercises are scapular retractions (squeezing shoulder blades together), scapular depression (pulling shoulders down away from ears), and protraction holds against a wall. Start with ten repetitions of each, one to two times daily, progressing to three sets as tolerated. I had a patient once who had persistent C7 radiculopathy that wasn't responding to any amount of nerve gliding or cervical traction. She'd been doing her exercises faithfully for four weeks with minimal improvement. The breakthrough came when we started focusing aggressively on lower trapezius activation—specifically prone Y raises with emphasis on keeping the shoulder blades down and back. Within two weeks, her radiation symptoms decreased substantially. The issue wasn't her neck exercises; it was that her scapular stabilizers were so weak her cervical spine couldn't maintain neutral alignment during daily activities, creating intermittent compression that no amount of direct nerve work could overcome. That case reinforced something I see repeatedly: cervical radiculopathy exercises that ignore the shoulder girdle are often incomplete treatment.
Cervical traction as an adjunct
While not technically an exercise, traction is frequently paired with the exercise program and deserves mention here. Sedentary cervical traction at approximately 10 to 15 pounds of force with the neck in about 15 to 30 degrees of flexion can create space in the neural foramen where the nerve root exits. Patients with home traction units typically use 10-minute sessions, two to three times per day. The literature suggests traction is most effective when combined with exercises rather than used alone, with studies showing roughly 60 to 70 percent of patients experience meaningful relief compared to 40 to 50 percent with exercises alone. The combination approach tends to produce faster and more sustained outcomes. Cervical radiculopathy exercises physical therapy approaches simply don't work for everyone, and pushing harder when they're not working is how patients make things worse. If you have progressive neurological deficits—growing weakness in the arm or hand, loss of coordination, difficulty walking, or bowel or bladder changes—these exercises are contraindicated and you need immediate medical evaluation. Those symptoms suggest myelopathy, which is spinal cord compression, not just nerve root irritation. Myelopathy requires surgical consultation, not a exercise program. Even within pure radiculopathy, there are patients for whom conservative management fails entirely. Roughly 10 to 15 percent of cervical radiculopathy cases don't improve with six to eight weeks of structured physical therapy and may require epidural steroid injections or surgical decompression. The indicators that you're in that group include: pain that remains severe and unchanging despite consistent exercise, weakness that progresses rather than stabilizes, and symptoms that disrupt sleep and daily function despite medication and activity modification. If you've been doing the exercises correctly for four weeks with zero improvement, that's not a sign to push harder—it's a sign to reassess the diagnosis and discuss alternative treatments with your provider.
Another limitation worth stating plainly: nerve gliding exercises can temporarily increase symptoms in the first one to two weeks of starting them. This is normal inflammatory response as the nerve begins moving again after being irritated. But there's a difference between temporary aggravation and actual harm. If symptoms spike dramatically during or immediately after nerve gliding and don't settle within a few hours, the exercise is too aggressive for your current state and needs modification. Reducing the range of motion by half usually resolves this without losing therapeutic benefit entirely. The evidence for cervical radiculopathy exercise programs is reasonably solid, but the quality of outcomes depends heavily on accurate diagnosis, appropriate exercise selection for the specific nerve root involved, proper technique, and realistic timelines. Most patients improve within six to eight weeks with a structured program combining nerve gliding, isometric strengthening, and scapular stabilization. Some need longer. A small minority need something beyond physical therapy. The exercises themselves are straightforward—the hard part is knowing which ones to use, when to use them, and when to stop and seek a different approach entirely.


