
Starting With Mechanism, Not Exercises
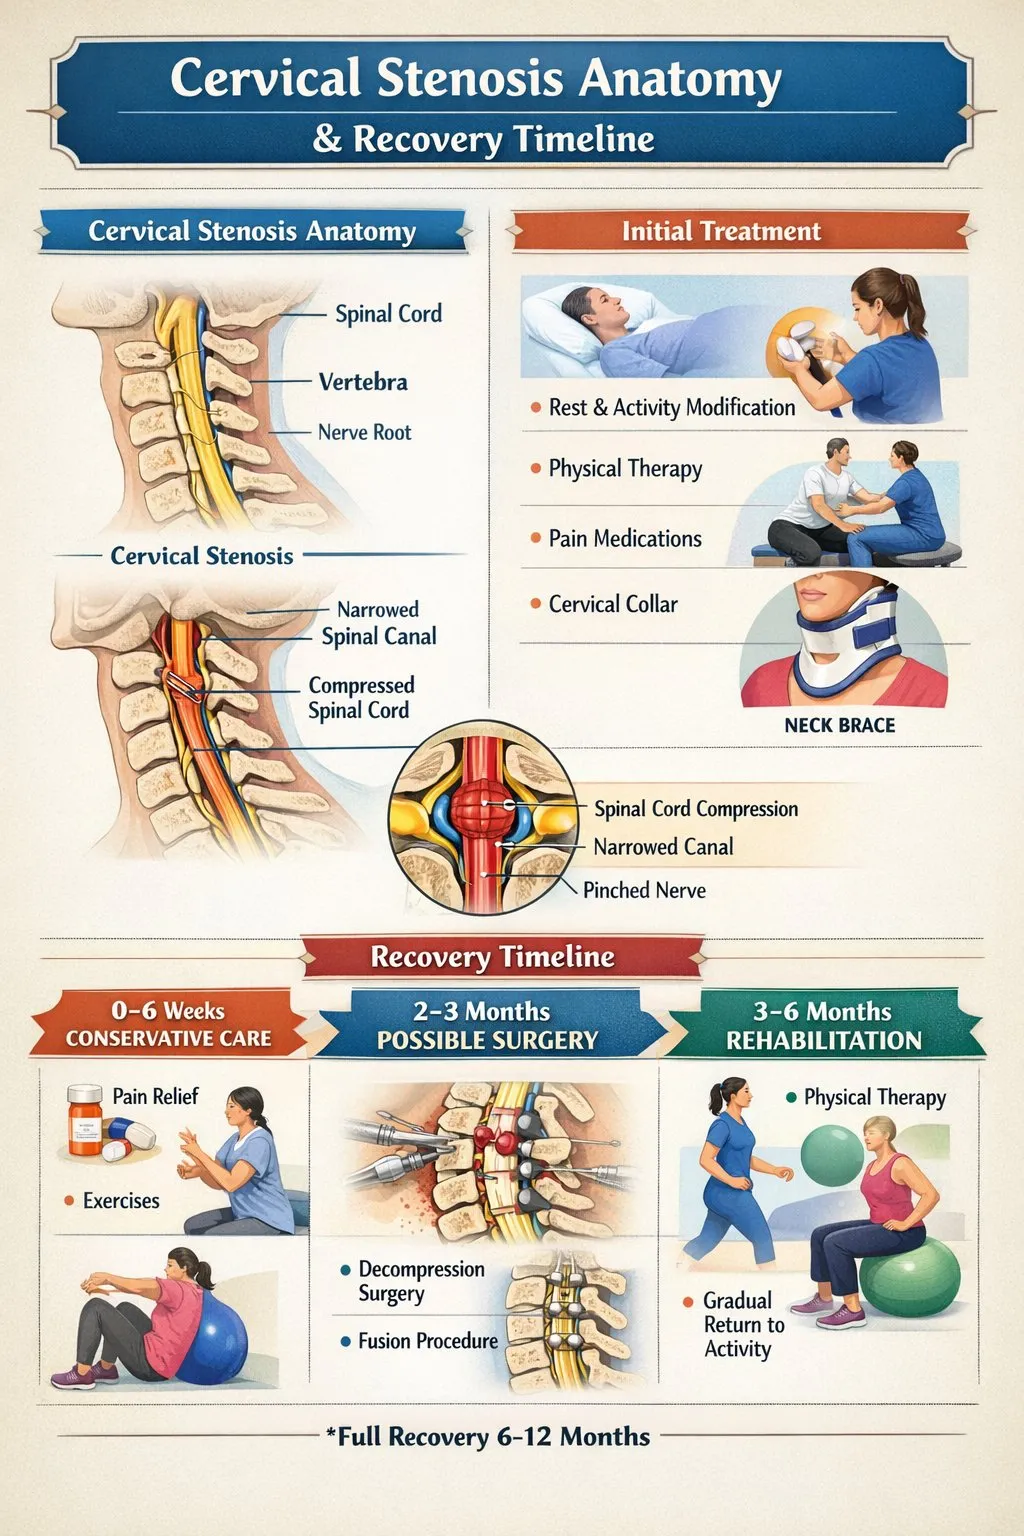
Cervical spinal stenosis narrows the spinal canal, which means the neural structures inside have less room to move. When the neck extends, that space shrinks further. Patients often come in with pain that shoots down one arm, numbness in specific fingers, and symptoms that get worse with overhead work or looking up. The first decision isn't what exercise to prescribe—it's whether the patient's symptoms are primarily central, radicular, or mixed, because each pattern responds differently to the same movements. I had a patient last year who had imaging confirming moderate C5-C6 stenosis but presented with bilateral forearm pain and mild grip weakness. Standard extension-based testing worsened everything. I discovered the real driver wasn't the central canal narrowing alone—it was a concomitant uncal foraminal component at C5-C6 on the right side that I caught only after doing a modified Spurling's at different angles. That changed the entire approach for her. We didn't start with traction or cervical repositioning exercises. We started with position-specific symptom localization.
What the Cervical Stenosis Physical Therapy Protocol Actually Looks Like in Practice
A typical first visit takes 45 to 60 minutes. You spend about ten minutes on history and red flag screening. Radiculopathy red flags—bowel or bladder changes, saddle anesthesia, progressive weakness—get you calling for an MRI referral immediately. If you're seeing someone with known stenosis who reports new leg symptoms or gait changes, that's myelopathy territory and PT is not the first line. The rest of the session goes into movement testing. I recommend beginning with active range of motion in all planes, noting where symptoms peripheralize versus centralize. A patient whose arm pain moves toward the shoulder and neck during flexion is showing a centralization response. That's your green light to build around flexion-biased mechanics. If symptoms spread further down the arm during any direction, stop and reconsider the diagnosis. Manual therapy comes next if there's no contraindication. I use gentle grade I-II oscillations at C2-C6 to reduce protective muscle guarding before introducing movement. I do not use high-velocity low-amplitude thrusts in these patients. The risk-benefit ratio doesn't support it when the spinal canal is already compromised. Soft tissue work on the suboccipitals, levator scapulae, and upper trapezius is more useful and carries far less risk. A typical 10-minute manual segment will reduce resting tone enough that the subsequent exercises actually land.
Therapeutic Exercise Progression
Most protocols I've seen online list exercises without specifying dosage, and that's the main reason they fail in the clinic. Here's what actually works and in what order: Phase one, weeks one to two: Cervical retraction exercises in sitting or supine. Five sets of ten repetitions held for three seconds each. The goal is to reduce forward head posture without irritating the nerve root. Patients with stenosis often can't hold a full retraction initially because it reproduces symptoms. In that case, partial retractions within a pain-free range are acceptable. I tell them to prioritize symptom centralization over range of motion. A patient who retraces 60 percent of their range with no arm symptoms will improve faster than someone who retraces 90 percent and gets worse arm pain. Phase one also includes scapular setting exercises. Prone Y raises, prone T raises, and isometric scapular retraction holds. These don't treat the stenosis directly but they change the load distribution across the cervical spine. A patient with weak scapular stabilizers puts more strain on the cervical extensors, which increases compression in the already narrowed canal. Fixing the scapular component usually cuts cervical load by about 15 to 20 percent during daily activities.
Get the Full Details
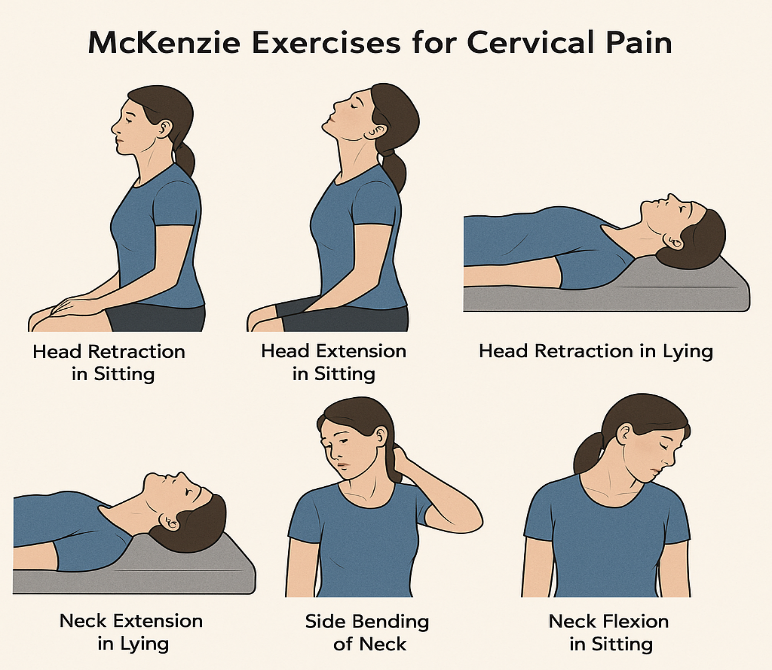
Phase two, weeks two to six: Deep cervical flexor training. This is where most programs stall because patients can't activate the correct muscles. The craniocervical flexion test with a pressure biofeedback unit helps. Target resting pressure is 22 to 24 mmHg, building to 30 mmHg over six weeks. Hold each contraction for ten seconds. Ten repetitions, twice daily. If a patient can't achieve 22 mmHg initially, that's normal. I start them at whatever pressure they can hold for five seconds without compensatory swallowing or chin tucking. Nerve gliding exercises for the upper extremity come in during phase two as well. Median, radial, and ulnar nerve flossing, three sets of ten repetitions per nerve, performed slowly with breath coordination. The key detail most protocols miss: the glide should be performed at the edge of tension, not into pain. If the patient feels a sharp zinger, they've gone too far. The symptoms should feel like a mild stretch along the path of the nerve, not reproduction of their baseline radiculopathy. Phase three, weeks six to twelve: Functional integration. This is where you add loaded cervical isometrics, resistance band work for the neck, and gradual return to overhead activity. I introduce a resistance band for resisted cervical flexion, extension, lateral flexion, and rotation. Two sets of twelve repetitions per direction, three days per week. Progress the band color only when the current resistance produces no increase in nighttime symptoms. Nighttime pain is your canary in the coal mine. If symptoms wake them up after you've progressed the band, you've moved too fast.
Aerobic conditioning is part of this phase. Recumbent cycling or walking on an incline treadmill. Thirty minutes, three to five days per week. The recumbent bike is preferable to upright cycling because the upright position increases cervical extension load. I have patients keep their necks in a neutral to slightly flexed position during the entire session.
Patient Education and Home Program
The home exercise component accounts for roughly 80 percent of outcomes in cervical stenosis. The clinic session is where you set up the framework. What actually changes day-to-day happens at home. I give patients a written home program with pictures. Verbal instructions get forgotten within 24 hours. The program includes cervical retractions, deep flexor holds, nerve glides, and scapular exercises. I ask them to perform the entire sequence twice daily. Each session takes about fifteen minutes. I track adherence by having them mark a simple calendar. Patients who complete more than four out of seven days per week show significantly better outcomes by week six compared to those who do it sporadically. Postural modification is equally important. I review their workstation setup, phone usage patterns, and sleeping position. A patient who spends four hours a day looking down at a phone is undoing three weeks of exercise work every single day. The advice sounds cliché because it's repeated constantly, but it's accurate. Neck flexion angle during phone use can reach 50 to 60 degrees, which increases effective cervical load to approximately 60 pounds. That's the equivalent of a seven-year-old sitting on their neck for extended periods.

Sleeping position matters more than most patients expect. I recommend a cervical pillow that maintains neutral alignment. Side sleepers should use a pillow height that keeps the neck level with the mattress. Stomach sleepers need to transition away from that position or use an extremely thin pillow. I've lost count of the patients who report immediate symptom reduction after switching from stomach to side sleeping.
Edge Cases and What I've Learned the Hard Way
Not every cervical stenosis patient responds to the same approach. Here's one specific scenario that threw me off for a while. I treated a 62-year-old male with confirmed cervical stenosis at C5-C6 and C6-C7 who had severe right-sided radiculopathy. Flexion-based exercises centralized his symptoms initially, but by week four his pain had shifted to a diffuse burning pattern involving both arms and his lower neck. Imaging showed no progression of stenosis. The issue was that prolonged flexion positioning, while initially reducing nerve root compression, was creating sustained passive tension in the posterior cervical musculature and ligaments. The extensor muscles had become lengthened and weakened from chronic forward head posture, and the constant flexion hold was overloading the already compromised posterior structures. My workaround was to introduce more neutral spine positioning and reduce the duration of sustained flexion. Instead of five sets of ten retractions held for three seconds, I switched to shorter holds—two seconds—with more frequent position changes. I added isometric holds in neutral and incorporated more phase two scapular stabilization before returning to retractions. His burning pattern resolved within three weeks. The lesson: flexion bias is a tool, not a rule. Monitor for secondary overload patterns.
Another common mistake is rushing into cervical traction. Traction can help some stenosis patients by temporarily increasing intervertebral space and reducing neural compression. But it's not appropriate for everyone. Patients with significant spondylosis and osteophyte formation can experience irritation from the decompression itself. I start with low force—10 to 15 pounds—for five minutes as a test. If symptoms increase during or after the session, I discontinue traction entirely. Manual disc decompression techniques or positional release are better alternatives in those cases.
When the Protocol Fails
Cervical stenosis physical therapy protocol doesn't work for everyone, and pretending otherwise is irresponsible. Here are the scenarios where PT reaches its limits: Progressive myelopathy is the biggest red flag. If a patient develops gait disturbance, balance issues, increased spasticity, or hand clumsiness during treatment, stop the protocol and refer for surgical consultation. No amount of cervical retraction exercises will reverse myelopathic progression. Early surgical decompression in these cases prevents permanent neurological damage. I've seen patients lose fine motor function permanently because the referral happened too late. Severe central canal stenosis with significant cord signal changes on MRI represents another scenario where conservative management has a narrow window. These patients may tolerate short-term PT for symptom relief, but the underlying mechanical compression remains. Expectation management is critical here. I tell patients upfront that PT may reduce their symptoms by 40 to 60 percent in the best case, but it won't reverse the structural narrowing. If symptoms remain functionally limiting after twelve weeks of compliant treatment, surgical consultation is appropriate.
Axial neck pain predominance without clear radicular features sometimes doesn't respond well to the standard stenosis protocol. These patients often have concurrent facet joint arthropathy or discogenogenic pain that requires a different treatment emphasis. I shift toward manual therapy targeting the zygapophyseal joints, cervical mobilization graded III to IV within pain-free range, and a greater focus on motor control rather than pure symptom centralization. The flexion bias approach can actually aggravate facet-mediated pain in some of these patients.
Progress Monitoring
Track outcomes with standardized measures. The Neck Disability Index (NDI) is the standard. A 10-point improvement is considered clinically meaningful. The Numeric Pain Rating Scale tracks symptom intensity. Upper extremity functional score captures functional limitation specific to arm symptoms. Repeat these at baseline, week six, and week twelve. Functional milestones matter more than scores. Can the patient return to overhead work without symptom exacerbation? Can they sleep through the night? Can they complete a 30-minute aerobic session without increased symptoms the following day? These are the metrics that predict long-term success better than any questionnaire. I typically see measurable improvement between weeks three and five. Patients who show no improvement by week four get re-evaluated for alternative diagnoses or contributing factors. Sometimes a thoracic outlet syndrome component, a peripheral nerve entrapment, or a cervical facet referral pattern is masquerading as pure stenosis. The initial presentation can look identical. A thorough differential diagnosis at that point prevents wasting months on the wrong treatment path.

The protocol itself—flexion-biased exercises, deep cervical flexor training, nerve gliding, scapular stabilization, aerobic conditioning—remains consistent across most cases. The adjustments come from patient response. The ones who do well follow the program consistently, modify their daily postures, and progress through phases without skipping ahead. The ones who struggle usually either don't do the home program, progress too quickly, or have a complicating factor that wasn't identified during the initial assessment.

