How to Actually Use a Chain of Infection Diagram Without Getting It Wrong
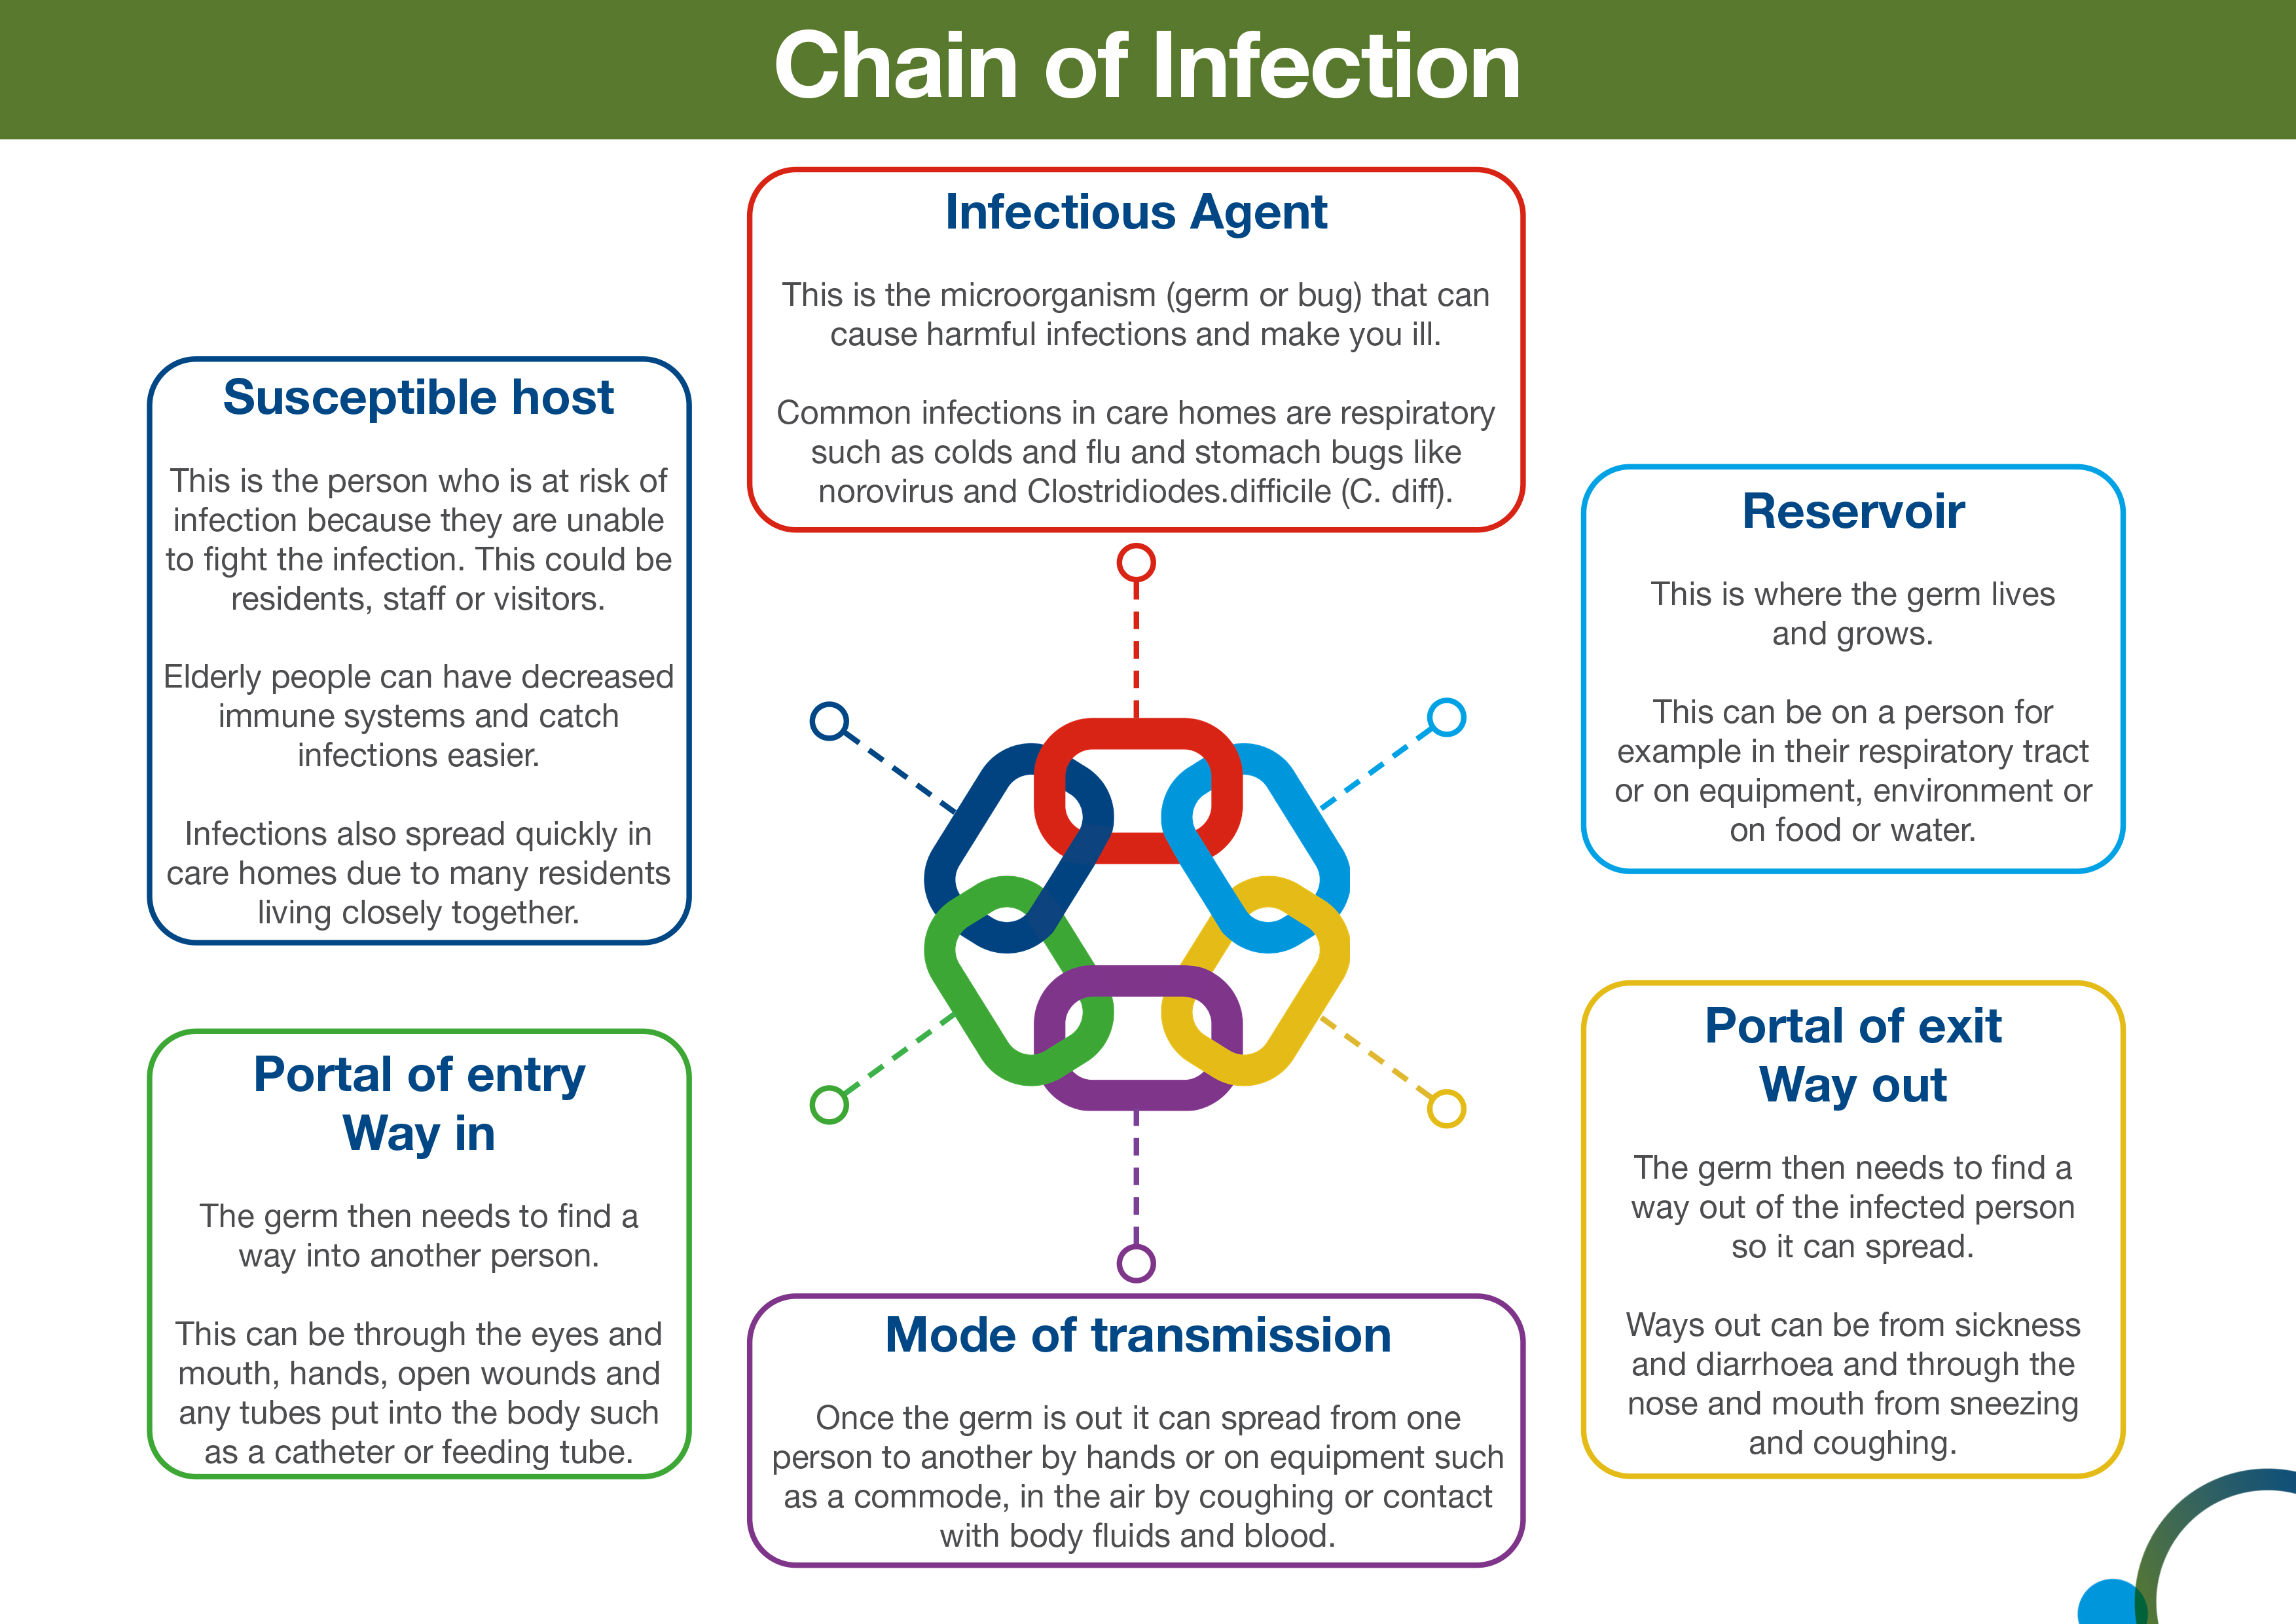
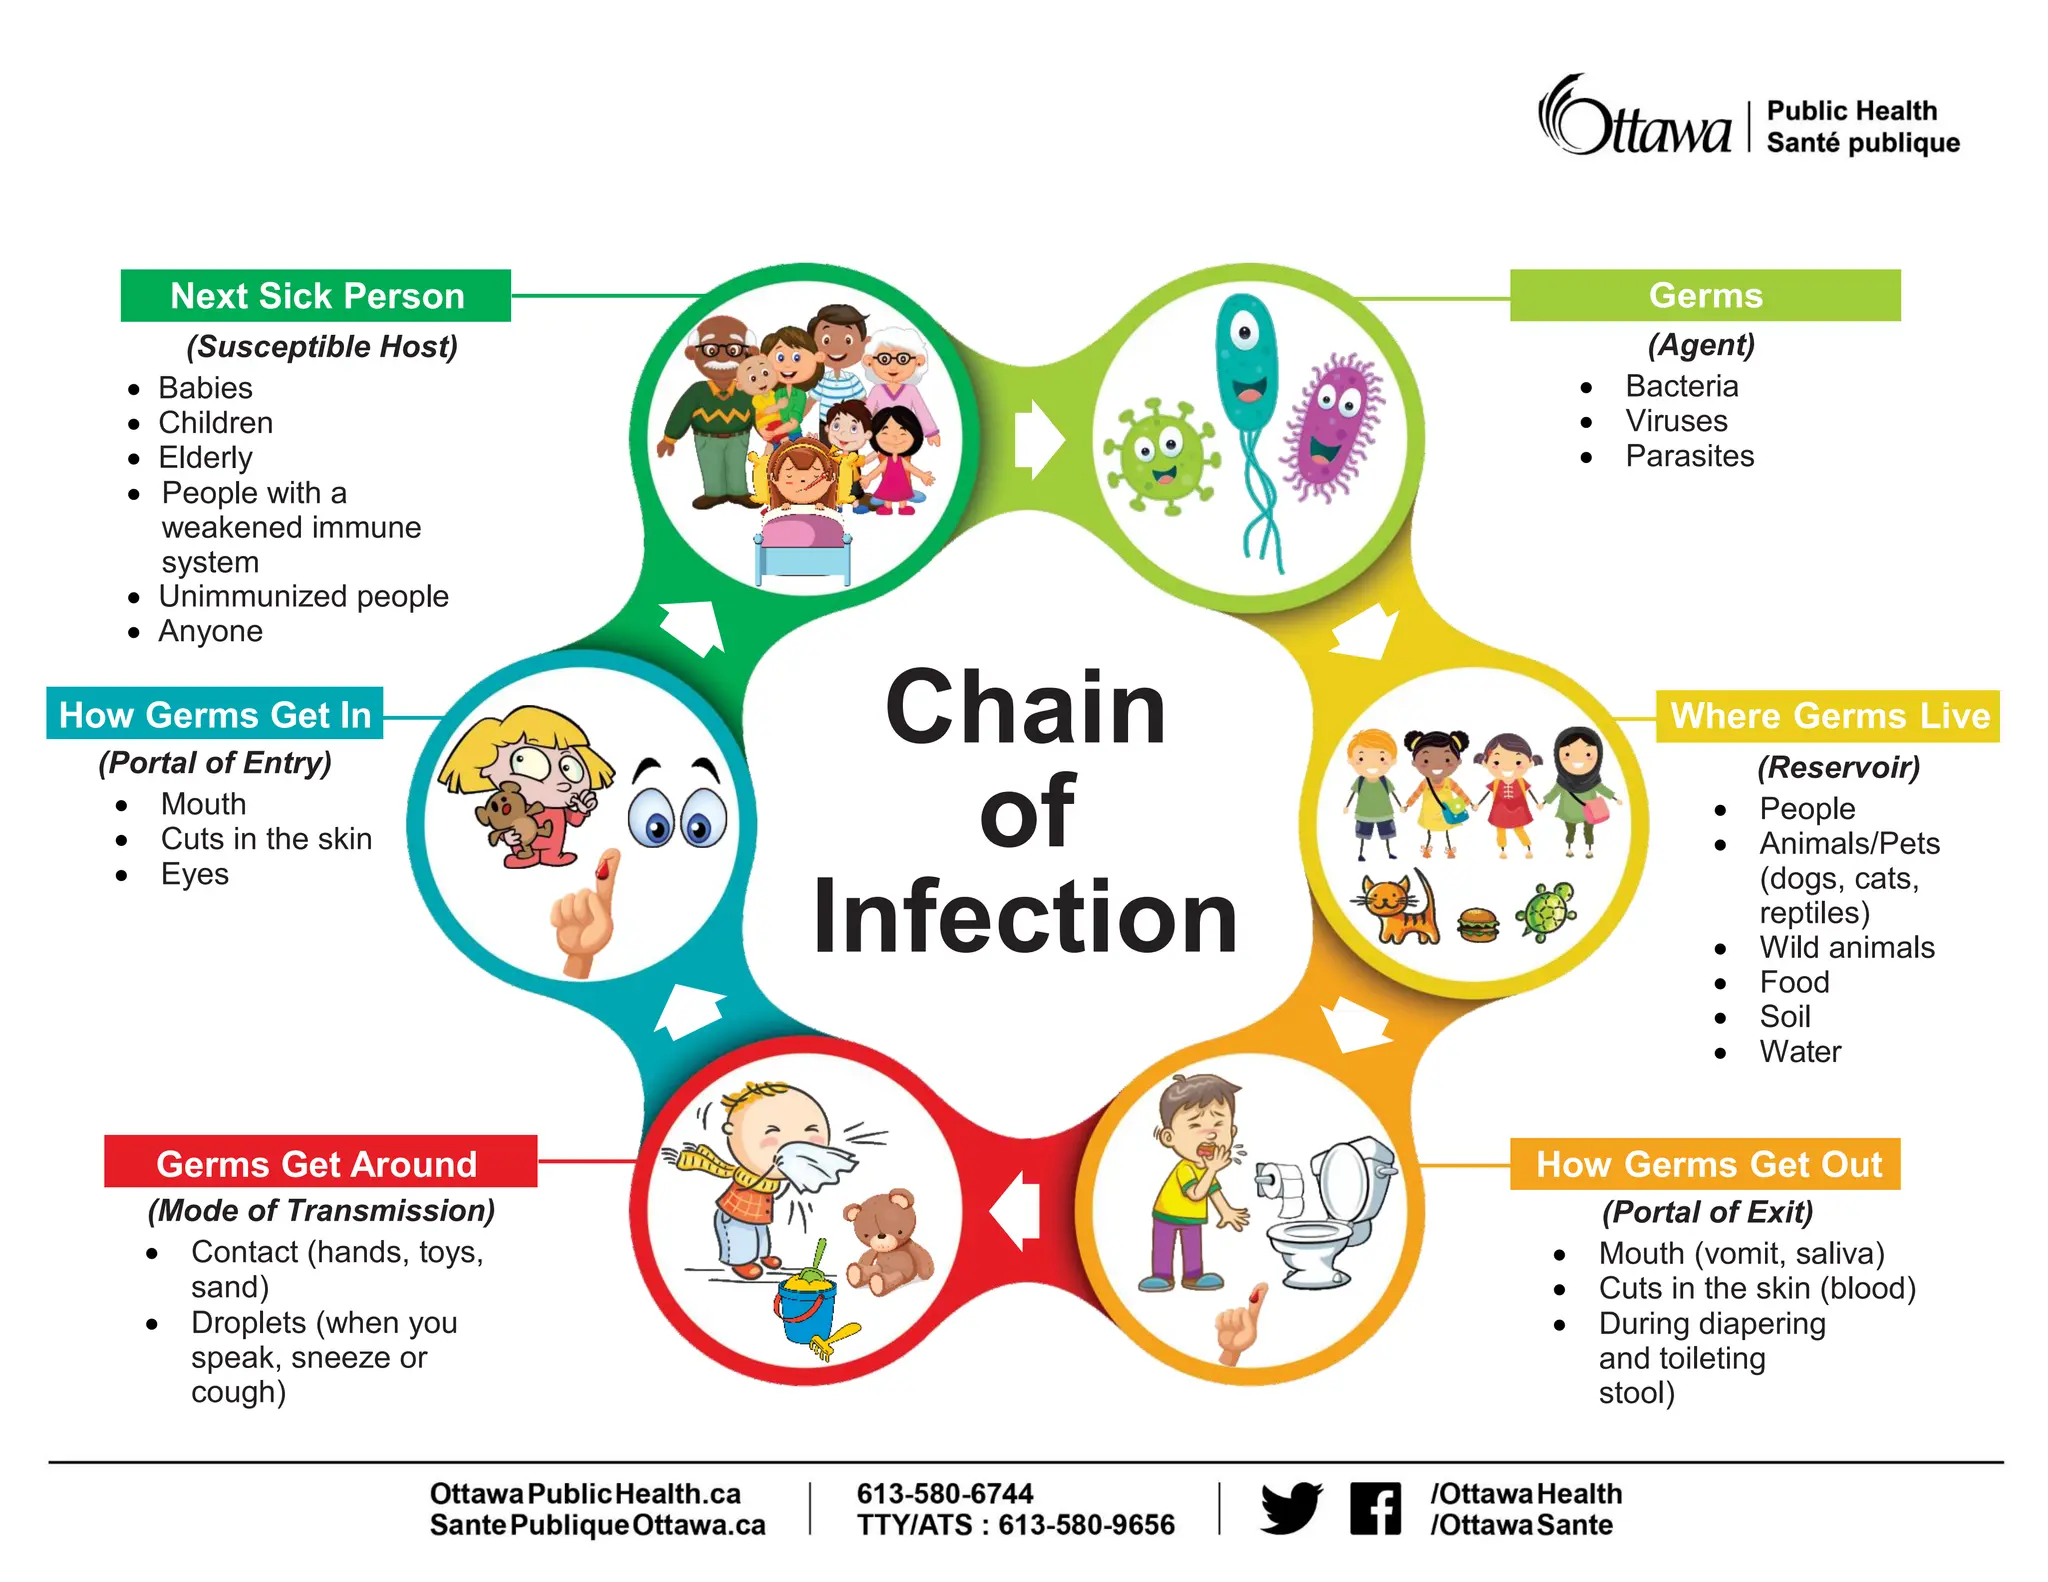
A lot of people treat the Chain of Infection Diagram as just a nursing school poster. It's not. It's a working tool for figuring out where an outbreak actually started, and if you draw it lazily, you'll miss the real transmission route every time. The diagram maps six links: the infectious agent, reservoir, portal of exit, mode of transmission, portal of entry, and susceptible host. Break any single link and the chain stops. That's the theory. In practice, things are messier. I built and reviewed dozens of these for hospital infection control surveys over the years. Here's how to do one that's actually useful.
What the Six Links Mean in Real Practice
Infectious agent is straightforward — bacteria, virus, fungus, parasite. But don't just write "bacteria." Write the specific organism. MRSA and E. coli require completely different containment strategies. A vague label makes the whole diagram useless for decision-making. Reservoir is where the pathogen lives and multiplies. This is where most people slip up. The reservoir isn't always the patient. It can be a ventilator circuit, a sink drain, a wound care tray, or even the hands of healthcare workers who never washed between patients. I once spent three weeks tracking a CLABSI cluster. The reservoir wasn't the central line kit. It was the antiseptic cap on the chlorhexidine bottle sitting at the bedside — contaminated from repeated use, never discarded. The manufacturer's instructions say replace the cap after opening, but nobody does that in a busy unit. The diagram would have caught that if someone had actually traced the reservoir carefully instead of assuming it was the catheter. Portal of exit is how the pathogen leaves the reservoir. Blood, sputum, feces, skin lesions, respiratory droplets. For a water-borne pathogen like Pseudomonas aeruginosa, the portal of exit might be an aerosolized mist from a contaminated sink. That's not obvious. You have to know the organism's biology to draw this right.
Mode of transmission covers direct contact, indirect contact, droplet, airborne, vector-borne, and vehicle-borne. This is the link most people focus on because it's the easiest to intervene on — hand hygiene, gowns, masks, isolation rooms. But targeting only the mode of transmission without identifying the reservoir is like mopping a floor without turning off the faucet. I've seen units do this repeatedly. They enforce hand hygiene compliance at 95% and wonder why surgical site infections keep spiking. The problem was never the hands. It was the pre-op prep solution. Portal of entry is how the pathogen gets into the new host. Broken skin, mucous membranes, invasive devices. Central lines, urinary catheters, endotracheal tubes — these are all portals of entry. An intact skin surface is actually a very effective barrier. Most pathogens can't get in through normal skin. That's why the portal of entry matters so much in healthcare settings. The disease isn't getting in through the skin. It's going straight through a catheter. Susceptible host is anyone the pathogen can infect. But susceptibility isn't binary. It's a spectrum. A patient with a weakened immune system, an open wound, or an indwelling device is far more susceptible than a healthy adult. Age, nutrition, comorbidities, and recent antibiotic use all shift someone up the susceptibility scale. You need to be specific here too. "Elderly patient" tells you nothing. "82-year-old male, neutropenic post-chemotherapy, with a Grade III pressure ulcer" tells you exactly what you're dealing with.
Get the Full Details

How to Draw One That Actually Works
Start with the outcome you're trying to explain. Don't build the chain abstractly. Pick a real case — a specific infection, a specific patient, a specific unit — and work backward from there. Here's what I did last year for a KPC (Klebsiella pneumoniae carbapenemase) outbreak on a medical oncology floor. We had seven cases over six weeks. Standard contact precautions weren't breaking the chain. Something else was happening. I mapped each case individually on the same diagram, color-coding the links. Four of the seven patients had received chemotherapy within the prior 14 days. Two had central lines. All seven had been on the same unit. The common reservoir link was the shared medication preparation area. A contaminated batch of injectable medications was the source, not patient-to-patient transmission. The mode of transmission wasn't contact. It was iatrogenic — a contaminated drug supply. Breaking that one link (removing the tainted medication lot) stopped the outbreak immediately. We didn't need enhanced cleaning or cohorting. We needed a pharmacy recall.
If I'd drawn a generic chain of infection diagram without anchoring it to specific patient data, I would have gone down the wrong path for months.
Common Mistakes That Ruin the Diagram
Assuming the chain is linear. It often isn't. A reservoir can be both a portal of exit and a portal of entry simultaneously. A contaminated surface is a fomite (indirect contact reservoir) and also a portal of entry for the next patient who touches it. The diagram should reflect that overlap, not force everything into neat sequential boxes. Ignoring environmental reservoirs. Water systems are a big one. Mycobacterium abscessus, Legionella, Pseudomonas — they live in plumbing. Square footage of tile, shower heads, faucet aerators, ice machines, humidifiers. If your diagram doesn't account for these, you're missing entire transmission routes. Treating the susceptible host as passive. The host's condition drives everything. A patient on broad-spectrum antibiotics has disrupted normal flora. That changes susceptibility dramatically and opens the door for C. difficile or VRE colonization. The host isn't just a victim at the end of the chain. The host's physiology is part of the chain itself.

Pitfall to avoid: Drawing one master diagram and treating it as the truth. Each infection event may follow a different chain. An MRSA surgical site infection and a norovirus GI outbreak on the same unit will have completely different reservoirs, portals, and modes. Don't conflate them.
Where the Chain of Infection Diagram Fails
It doesn't model co-infections well. When two pathogens are circulating simultaneously and potentially interacting, the single-chain model breaks down. You'd need parallel chains or a network diagram. It doesn't account for incubation periods or asymptomatic carriers. A patient can be an infected reservoir with no symptoms, transmitting through an unrecognized portal. The diagram shows the mechanism, not the timeline. If you need to map when transmission actually occurred, you need an epidemiological curve, not just a chain diagram. For complex outbreaks, consider supplementing with a web-based transmission model or a node-and-edge graph. The chain diagram is a starting point, not a complete analytical tool. It tells you what could be happening, not what is happening. You need case investigations, lab data, and environmental sampling to confirm which links are actually active.
That said, it's still the fastest way to communicate an infection control hypothesis to a team. Takes maybe ten minutes to sketch one that captures the key links. Way faster than waiting for culture results to come back. Use it early and use it often, but verify it with data before you commit resources to an intervention.