What Chapter 10 Blood Anatomy And Physiology Actually Covers
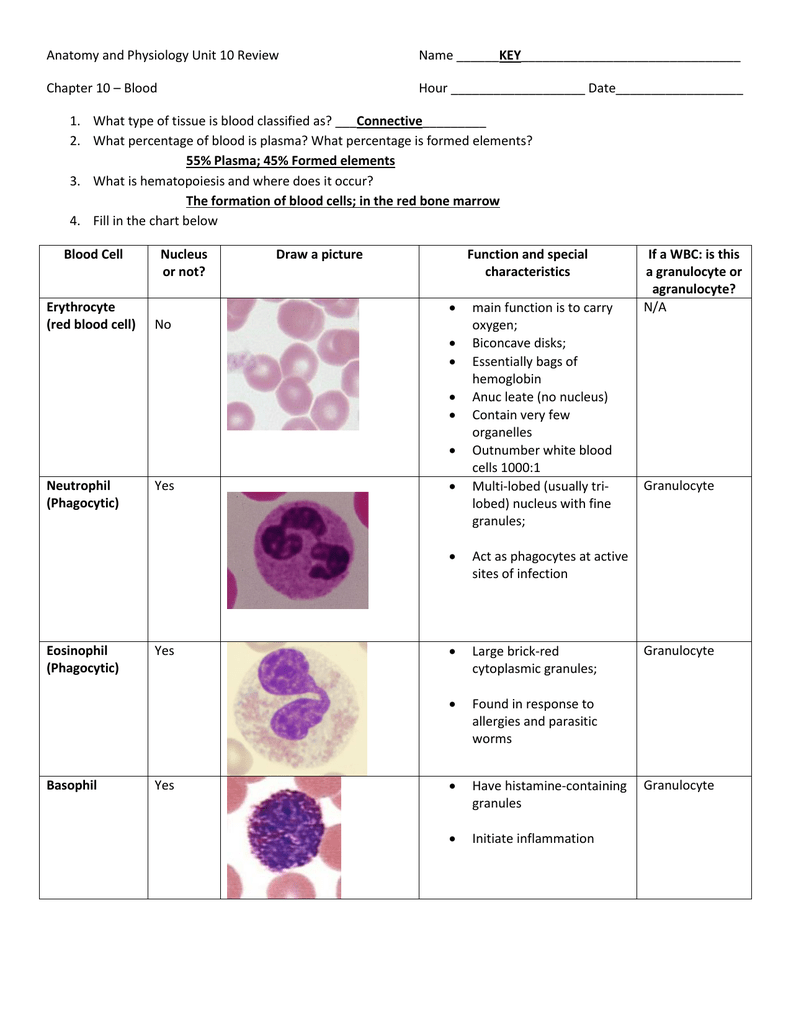
Most college courses break blood into three buckets: plasma, formed elements, and the functional overlap between them. That sounds simple until you're staring at a slide showing basophil granules under oil immersion and trying to remember which leukocyte degranulates during anaphylaxis versus parasitic infection. I've seen students lose points for confusing eosinophils with basophils on lab identification quizzes. It happens because the morphology is similar and the staining varies between prep slides. The chapter typically runs about 40 to 60 pages depending on the textbook. Marieb and Hoehn spend roughly two weeks on it. Saladin moves faster but expects more reading comprehension on your own. You're looking at erythropoiesis, the coagulation cascade, blood typing and transfusion compatibility, and the baseline functions of plasma proteins. That's the surface layer. The stuff professors actually test on is where the edges get fuzzy.
Chapter 10 Blood Anatomy And Physiology: How to Approach It Without Losing Your Mind
Start with hematology basics before diving into the coagulation cascade. Here's why that matters. When I was teaching intro A&P, I noticed students who jumped straight into clotting factors kept mixing up the intrinsic and extrinsic pathways. They'd memorize Factor XII starting the intrinsic route but then write Factor VII as the first step because they'd conflated the diagrams. The fix was making them draw the pathways from memory first, blank page, before opening the book. Takes about 20 minutes and sticks way better than highlighting passages. For the formed elements, focus on what each cell type actually does rather than memorizing percentages. You don't need to recall that neutrophils make up exactly 62% of WBCs. You need to know they're the first responders, they have multi-lobed nuclei, and they live about 6 to 8 hours in tissue. The exact percentage shifts with diet, time of day, and lab equipment. The functional role doesn't. Erythropoiesis is where most students stall out. The kidney releases EPO in response to hypoxia, the bone marrow responds by ramping up RBC production, and iron plays a role you can't skip. I used to tell my lab partners that if you forget everything else, just remember: low oxygen triggers kidneys, kidneys signal bone marrow, bone marrow needs iron and B12 and folate to actually build the cells. Miss any link in that chain and you get anemia, but the type of anemia tells you which link broke. Iron deficiency looks different on a CBC than B12 deficiency. The MCV is the clue. Microcytic means iron problem. Macrocytic means B12 or folate problem.
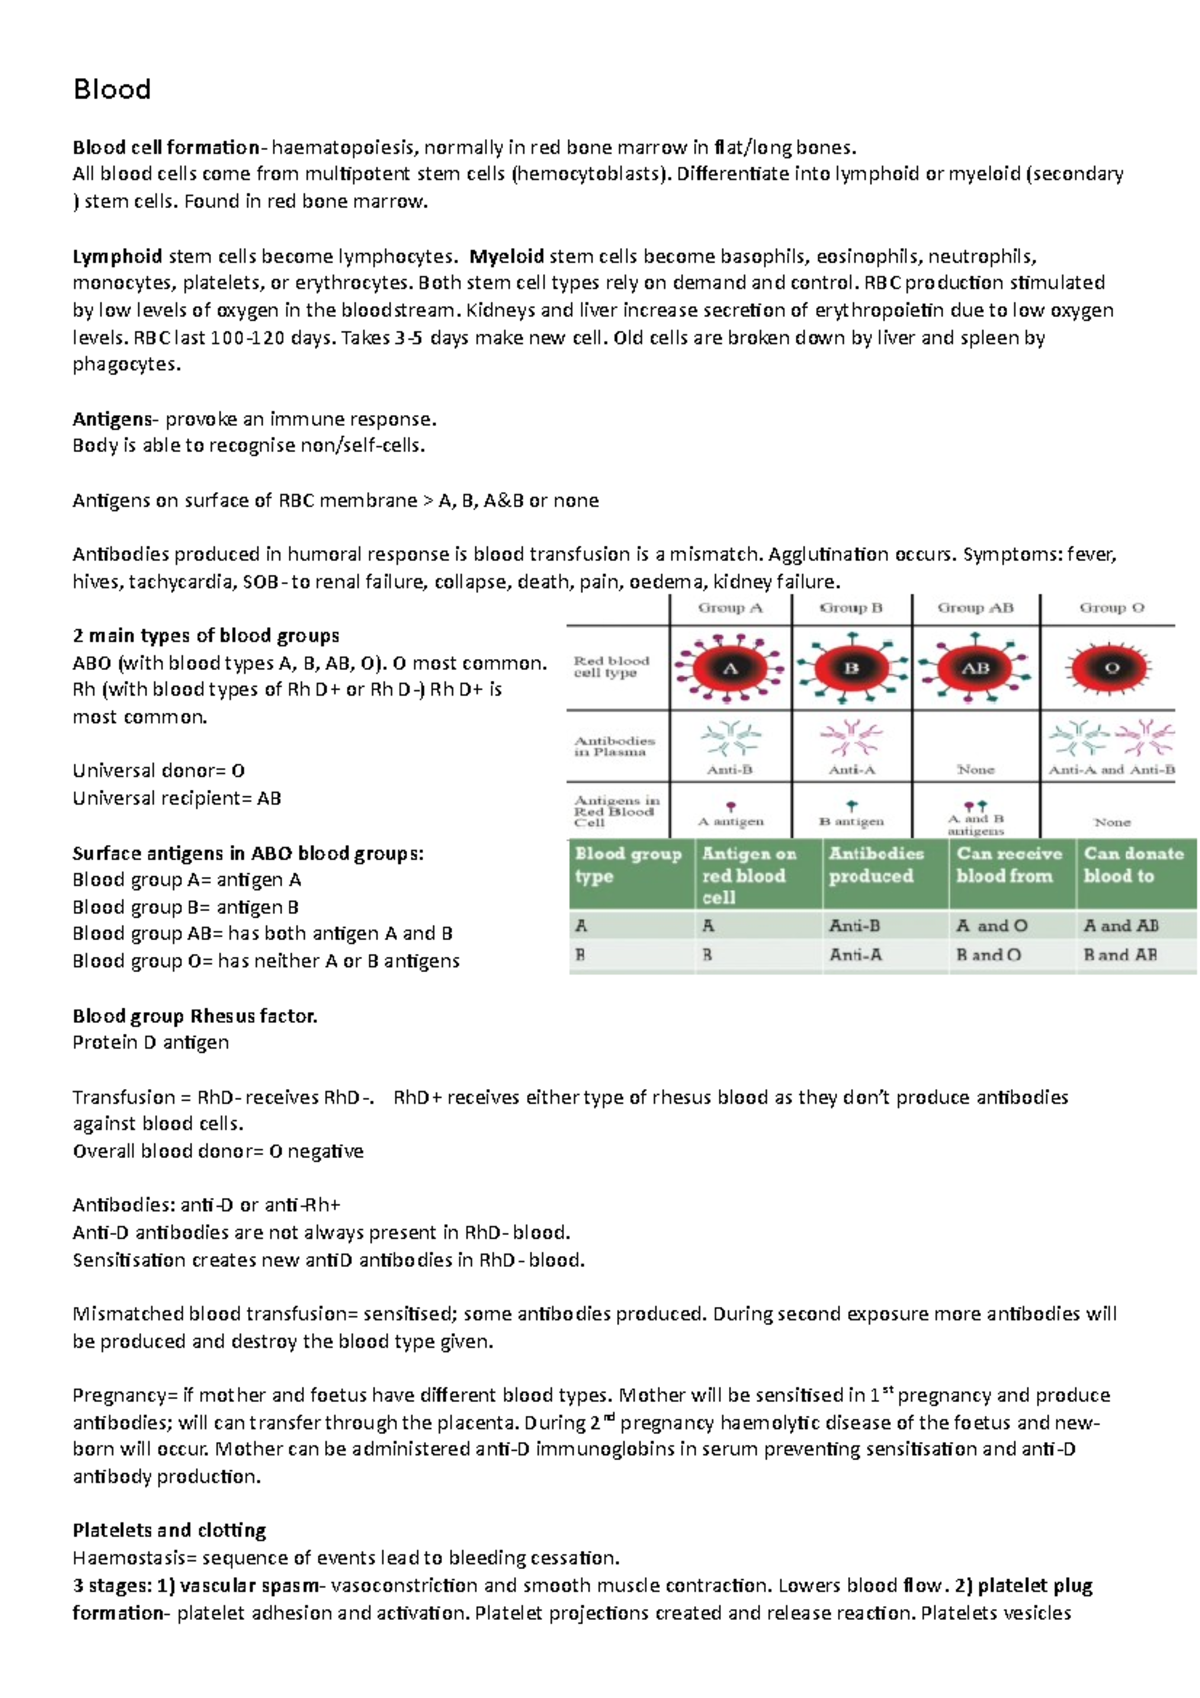
Coagulation is the part everyone dreads. The cascade has fourteen factors. You don't need to memorize every single one. What you do need to understand is that there are two initiation pathways that converge into a common pathway. Intrinsic starts inside the blood vessel with damaged endothelium and contact activation. Extrinsic starts outside with tissue factor released from injured tissue. Both lead to thrombin converting fibrinogen to fibrin. That's the framework. Everything else is detail. Here's a practical tip for studying coagulation. Draw the pathway on index cards. Write the trigger on one side, the sequence on the other. Do it twice. The first time will be a mess. The second time you'll notice you already know where Factor X sits because you've seen it six times without realizing it. Card draws take about ten minutes each and beat re-reading the chapter three times. Blood typing and compatibility comes up on every exam. You need to understand antigens on RBCs and antibodies in plasma. Type A has A antigens and anti-B antibodies. Type B has B antigens and anti-A antibodies. Type AB has both antigens and no antibodies. Type O has no antigens and both antibodies. The Rh factor is separate. Rh positive means you have the D antigen. Rh negative means you don't. Rh incompatibility matters most during pregnancy, not during transfusion. That distinction shows up on test questions constantly.
Get the Full Details

I had a student once who kept mixing up which antibody attacks which antigen. The workaround that finally worked was having her make a simple table with antigens across the top and antibodies in the plasma down the side, filling in where they'd attack each other. Visual mapping beat verbal memorization for her. Probably works for most people in this class. Plasma proteins are another area where surface-level studying falls apart. Albumin maintains osmotic pressure. Globulins handle transport and immunity. Fibrinogen handles clotting. That's the basic breakdown. The nuance is that albumin also buffers pH and transports hormones, fatty acids, and drugs. If a question asks why someone with low albumin develops edema, the answer isn't just "osmotic pressure." It's specifically about colloid osmotic pressure pulling water back into capillaries. The wording matters on multiple choice exams. One thing textbooks don't always emphasize clearly is the difference between hematocrit and hemoglobin concentration. Hematocrit is the percentage of blood volume that's red blood cells. Hemoglobin is the actual protein mass carried in those cells. You can have a normal hematocrit with low hemoglobin if the cells are hypochromic, which happens in iron deficiency. Or you can have a high hematocrit with normal hemoglobin in dehydration because the plasma volume drops and the cells concentrate. They're related but not interchangeable measurements.
When studying for the exam, practice reading actual CBC panels if your professor provides them or if you can find sample reports online. Most intro courses don't test on real lab values, but understanding what elevated platelets or low RBC count look like in context helps you answer scenario-based questions that show up on finals. I found a few sample CBC reports from clinical nursing sites and spent an hour going through them. Those practice sessions translated directly into better answers on case study questions later. Time management matters more than people admit. Chapter 10 usually comes after Chapter 9 on the cardiovascular system, and the concepts overlap heavily. The heart pumps blood, but blood itself is what carries gases and nutrients and immune cells and clotting factors. If you're weak on cardiac output and blood flow regulation, blood function makes less sense. Go back and quickly review cardiac cycle basics before re-reading the blood chapter. It takes about thirty minutes and prevents confusion later. Lab work for this chapter typically involves blood smear identification and sometimes a hematocrit spin. The smear part is tedious but straightforward if you know what to look for. Neutrophils have 3 to 5 lobes. Eosinophils have bilobed nuclei and red-orange granules. Basophils have dark purple granules that obscure the nucleus. Lymphocytes are small with a large round nucleus and thin rim of cytoplasm. Monocytes are the largest with kidney-shaped nuclei. If you can identify those five under a microscope without panicking, the lab grade is mostly secured.
There's no shortcut that covers everything in one session. This material is dense and the connections between systems are real. Spend time understanding the mechanisms, draw out the pathways yourself, and practice applying the concepts to scenarios rather than just reciting definitions. The chapter is foundational for everything that comes after it in the course, so getting it solid now saves real time later.