Cardiac assessment on the floor doesn't work like the textbook diagrams.
I used to carry a laminated card in my pocket that looked like every nursing fundamentals page ever printed. Then I got assigned to telemetry and realized the list was missing half the things that actually matter when you're walking into a room with a patient who looks fine but is about to deteriorate. The cheat sheet I ended up using for the rest of my career was something I built from scratch over about six months of near-misses and chart reviews. The core of a solid Cheat Sheet Cardiac Assessment Nursing isn't a list of normal values. It's a decision tree that tells you what to do when you find something abnormal. Most study guides give you S3/S4 descriptions and a table of potassium levels. That's reference material, not an assessment tool. An assessment tool answers the question "what am I looking at right now and what do I do in the next thirty seconds?"
How I structured my Cheat Sheet Cardiac Assessment Nursing
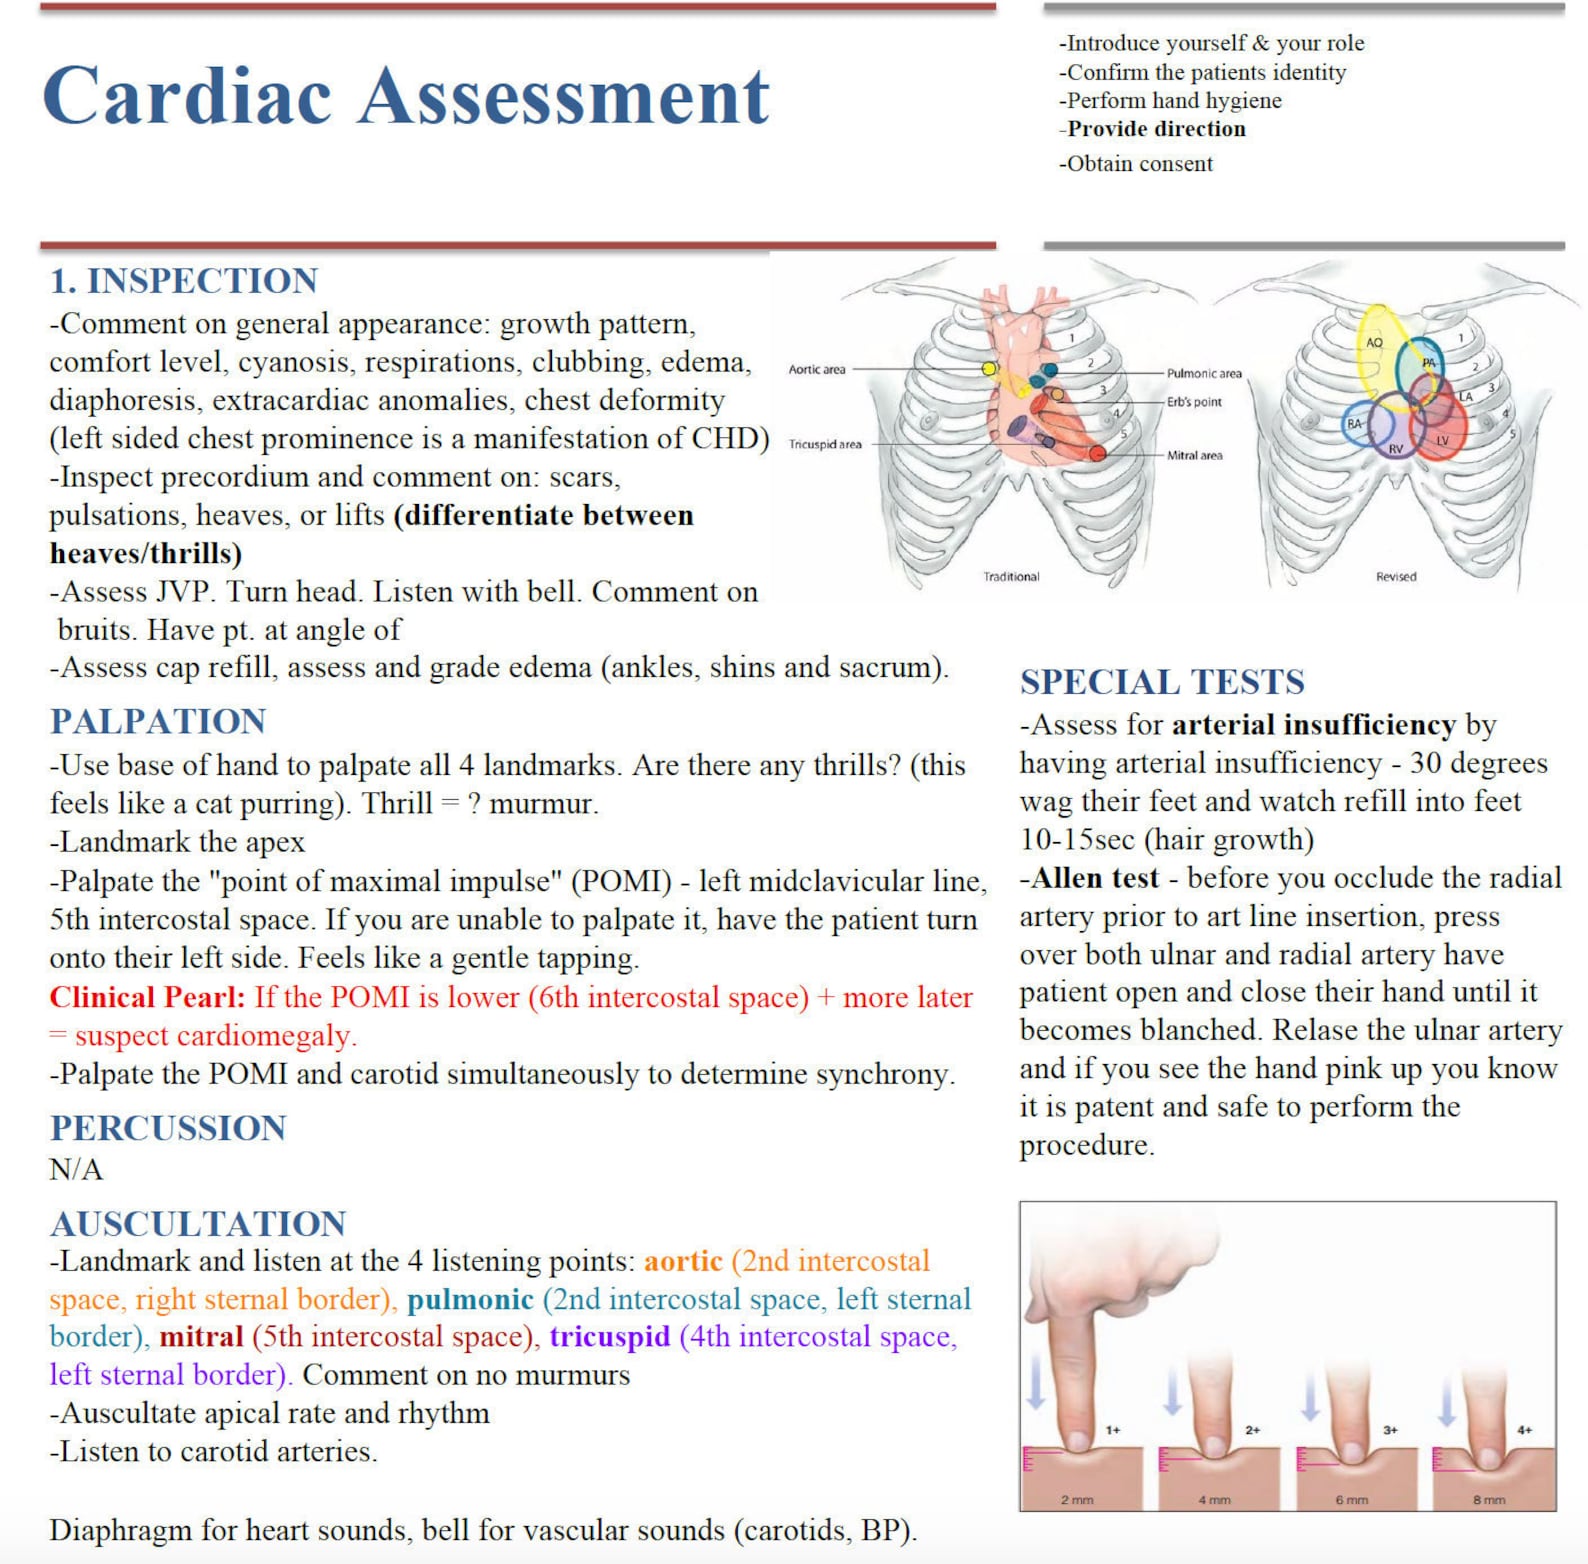
It has four sections. Inspection, palpation, auscultation, and the messy middle where everything connects to the monitor and the chart. I wrote it on index cards because I needed something small enough to fit in a scrub pocket and quick to flip through during a rapid response. The final version was two sides of a single card, written in pen, with corrections scratched out over time. The first section covers what you see before you touch the patient. Look for jugular venous distention at 45 degrees, not sitting up straight. I learned this the hard way on a med-surg floor when I documented normal JVP on a patient who was propped at 90 degrees. He was volume overloaded and my chart read normal. The cardiac surgeon later pointed it out during a sign-out and I felt about two years older. You also scan for peripheral edema, skin temperature, and color. Pale and cool usually means low output. Pink and warm is better but doesn't rule out everything. I stopped documenting "warm and dry" as a default because it's meaningless without a baseline. My cards now force me to write "baseline" or "new" next to every finding.
Auscultation shortcuts that actually work
Most people learn to listen to the aortic, pulmonic, tricuspid, and mitral areas in that order. That sequence is fine for exams. On the unit, you're often standing at the side of the bed with a noisy hallway behind you and a family member asking questions. You need a faster pattern. I use the base-to-apex sweep with the diaphragm, then the bell at the apex last. The key thing beginners miss is that S3 is only pathological in adults over forty. Hearing an S3 in a twenty-two-year-old athlete after a sprint is normal. Hearing it in a seventy-year-old with heart failure history is a red flag. The cheat sheet notes this distinction because I kept flagging benign sounds as emergencies and paging the resident at 2 AM for nothing. Another counter-intuitive point: murmurs don't always get louder when you lean the patient forward. That trick works for aortic regurgitation. Mitral regurgitation gets louder when the patient rolls onto their left side. If you only use one position, you will miss half your murmurs. I put this on the card after catching a moderate MR that had been dismissed on three prior assessments because I'd only listened with the patient supine.
Get the Full Details

The part nobody puts on a study card
Correlation. A heart rate of 110 means something completely different in a post-op mitral valve replacement patient than it does in someone with new-onset atrial fibrillation and a hemoglobin of 7.2. The monitor gives you a number. The assessment gives you context. My card has a small section at the bottom for "known diagnosis and current treatment." I write it in every time. New grad nurses skip this step constantly and then get tripped up when a medication side effect looks like a new arrhythmia. Digoxin toxicity doesn't announce itself with a classic nausea-and-yellow-halos presentation half the time. It shows up as bidirectional ventricular tachycardia or a junctional rhythm that makes no sense on paper.
What this approach leaves out
A one-page cheat sheet cannot cover pediatric assessments, pregnant patients with peripartum cardiomyopathy risk, or the nuances of mechanical valve monitoring. If you're working in a unit that handles those populations, you need a separate reference for each. The card I described works for adult medical-surgical and telemetry floors with stable-to-moderately-unstable patients. It breaks down when you have congenital heart disease or a transplant recipient on complex immunosuppression. Also, handwritten cards degrade. Ink smears during code blues. Laminated versions survive better but are harder to update. I switched to a small notebook with pocket pages after my third card got soaked in saline and became illegible during a shift change. The notebook format lets me cross off obsolete items and add new ones without rewriting the whole thing.
Practical details for building your own
Start with what you actually do during an assessment, not what the textbook says you should do. Write down each step in the order you perform it. Then remove anything you never actually check. My first draft had twenty-two items. The version I used for two years had nine. The omitted items weren't unimportant. They were things I checked indirectly through other means or that didn't change my immediate action. Include abnormal findings paired with the exact intervention or notification step. "S3 present" is a finding. "S3 present, notify provider, check BNP, assess for fluid overload" is an assessment tool. The difference matters when you're tired and running on four hours of sleep. If you want a starting template, look for the AACN Adult Cardiac Critical Care Translation document on cardiac assessment. It's not a cheat sheet but it's a reliable reference framework. I used it as the skeleton and filled in the gaps with unit-specific protocols and my own corrections. Download it, print it, and then stop treating it like the final word. Your patient will teach you what to add faster than any textbook.