What Actually Works When You Need Pharmacology Quick Reference
Most students I talk to treat pharmacology like a memorization marathon. They flash-card their way through half a dozen drug classes, then panic during the exam when a question asks about a beta-blocker's interaction with a calcium channel blocker in a patient who also has COPD. The problem isn't that pharmacology is hard. It's that standard study materials present drugs as isolated facts instead of a system of mechanisms, trade-offs, and edge cases. A Cheat Sheet For Pharmacology Easy approach flips that. Instead of listing every drug under every class, you organize by mechanism first, then branch into the clinical decisions that actually matter. Here is how I built mine during my residency years, and where the common traps are.
The cheat sheet method that actually stuck
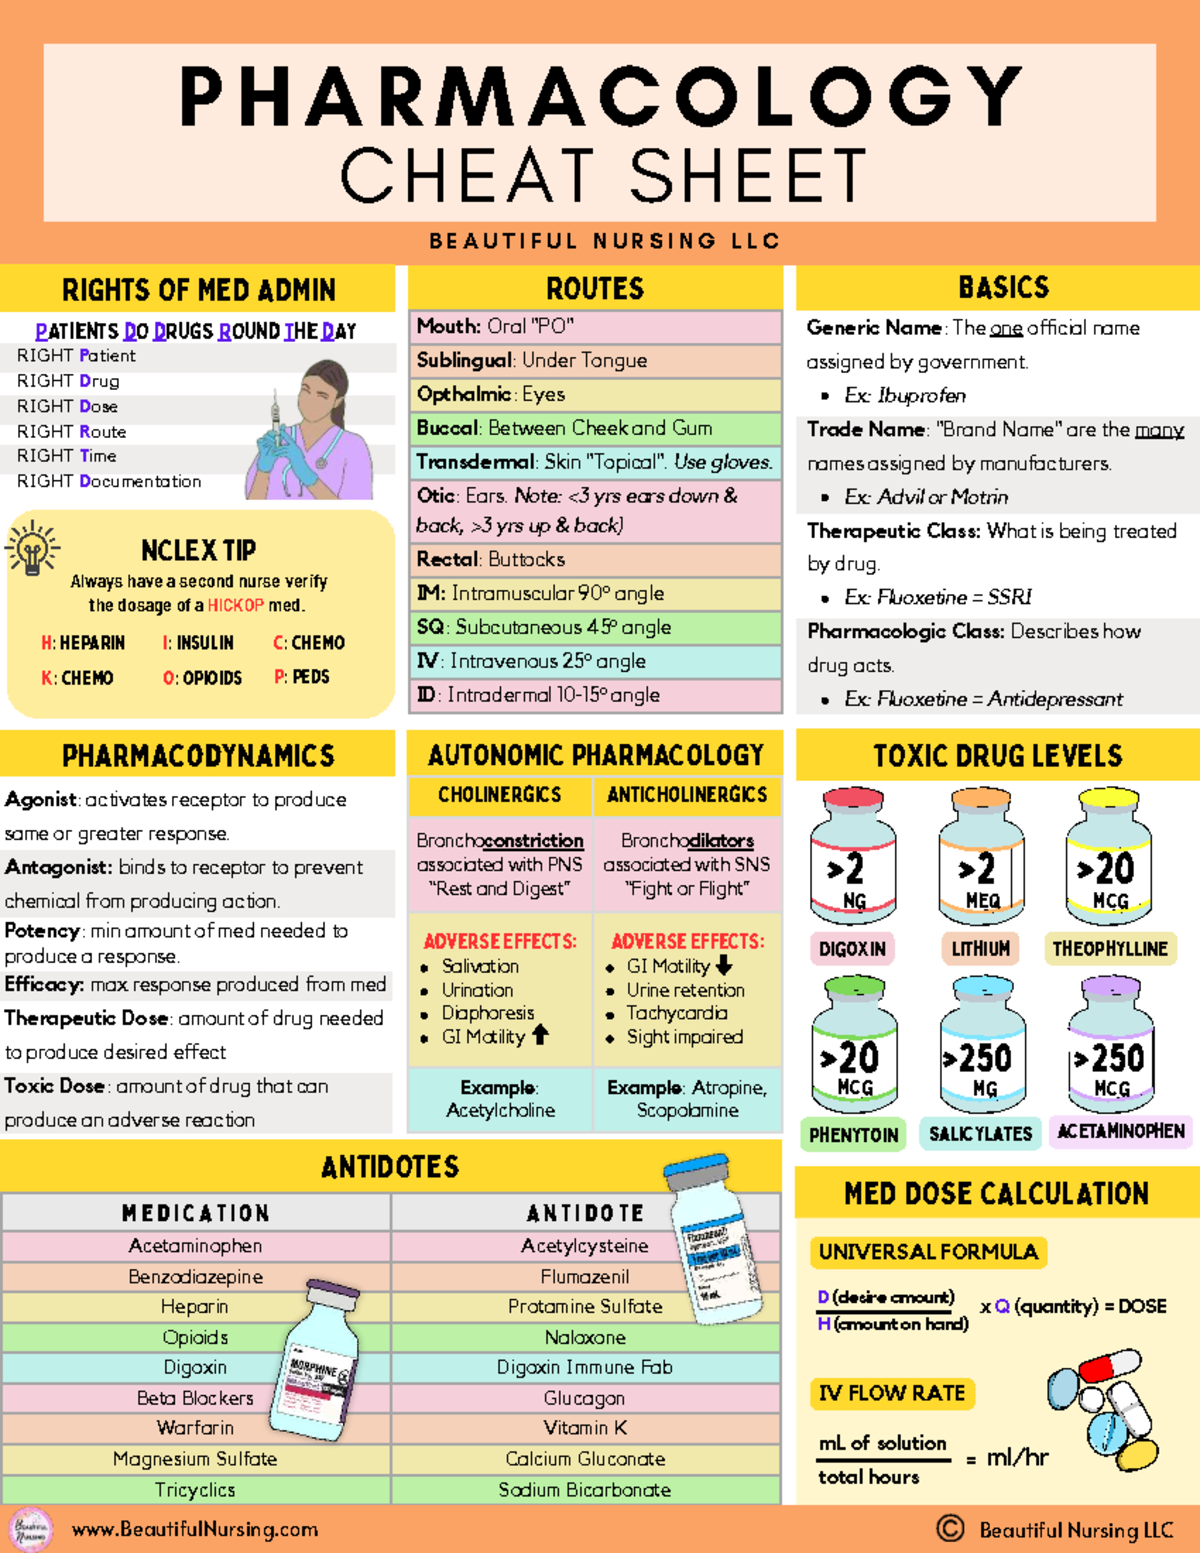
I started with a blank page and wrote down the major receptor families: alpha-1, alpha-2, beta-1, beta-2, muscarinic M1 through M5, nicotinic, H1, H2, D1, D2, 5-HT1A, 5-HT2A, COX-1, COX-2, HMG-CoA reductase, and so on. That took about twenty minutes. Everything else branches from there. Under each receptor, I wrote three lines. Agonist, antagonist, and the one clinical context where you would actually use it. For beta-1, that looked like metoprolol for post-MI rate control, atenolol for hypertension in younger patients, and esmolol as the IV drip you pick when you need to turn the effect off in minutes rather than hours because of its half-life of about nine minutes. That third line is the one most cheat sheets skip, and it is the one that shows up on board questions. For the Cheat Sheet For Pharmacology Easy system, I then added a fourth section: clearance and adjustment. This is where people lose points. Metoprolol is hepatically metabolized via CYP2D6, so a poor metabolizer or someone on a CYP2D6 inhibitor like fluoxetine will effectively double their dose without any change to the prescription. Not knowing that distinction turned a routine hypertension case into a bradycardic crisis in a patient I was following. I learned to always check the primary elimination pathway before writing anything down.
Core Structure That Saves Time
Every sheet I have ever seen that people actually use follows one of two architectures. The first is class-based, which looks like this: ACE inhibitors at the top, then list enalapril, lisinopril, captopril, ramipril with doses and side effects. The second is mechanism-based, which looks like this: block the angiotensin-converting enzyme, and here are the four drugs that do it with the one detail that differentiates them. The mechanism-based layout is slower to build but roughly three times faster to retrieve under pressure. When you are in an exam or a clinical rotation and the question says a patient has a dry cough on their blood pressure medication, you do not need to scan four separate drug pages. You know ACE inhibitors cause bradykinin accumulation, which causes the cough, and you switch to an ARB. That chain takes about three seconds if the pathway is organized in your head the right way. I organized my sheets by starting with the drug class mechanism, then listing representative agents with their distinguishing features only. The distinguishing feature is everything. All beta-blockers block beta receptors. Propranolol is non-selective and crosses the blood-brain barrier, which is why it causes vivid dreams and can unmask asthma. Metoprolol is beta-1 selective at low doses but loses that selectivity above 100 mg, which is why dose matters, not just the drug name.
Get the Full Details
High-Yield Categories and the Details That Actually Get Tested
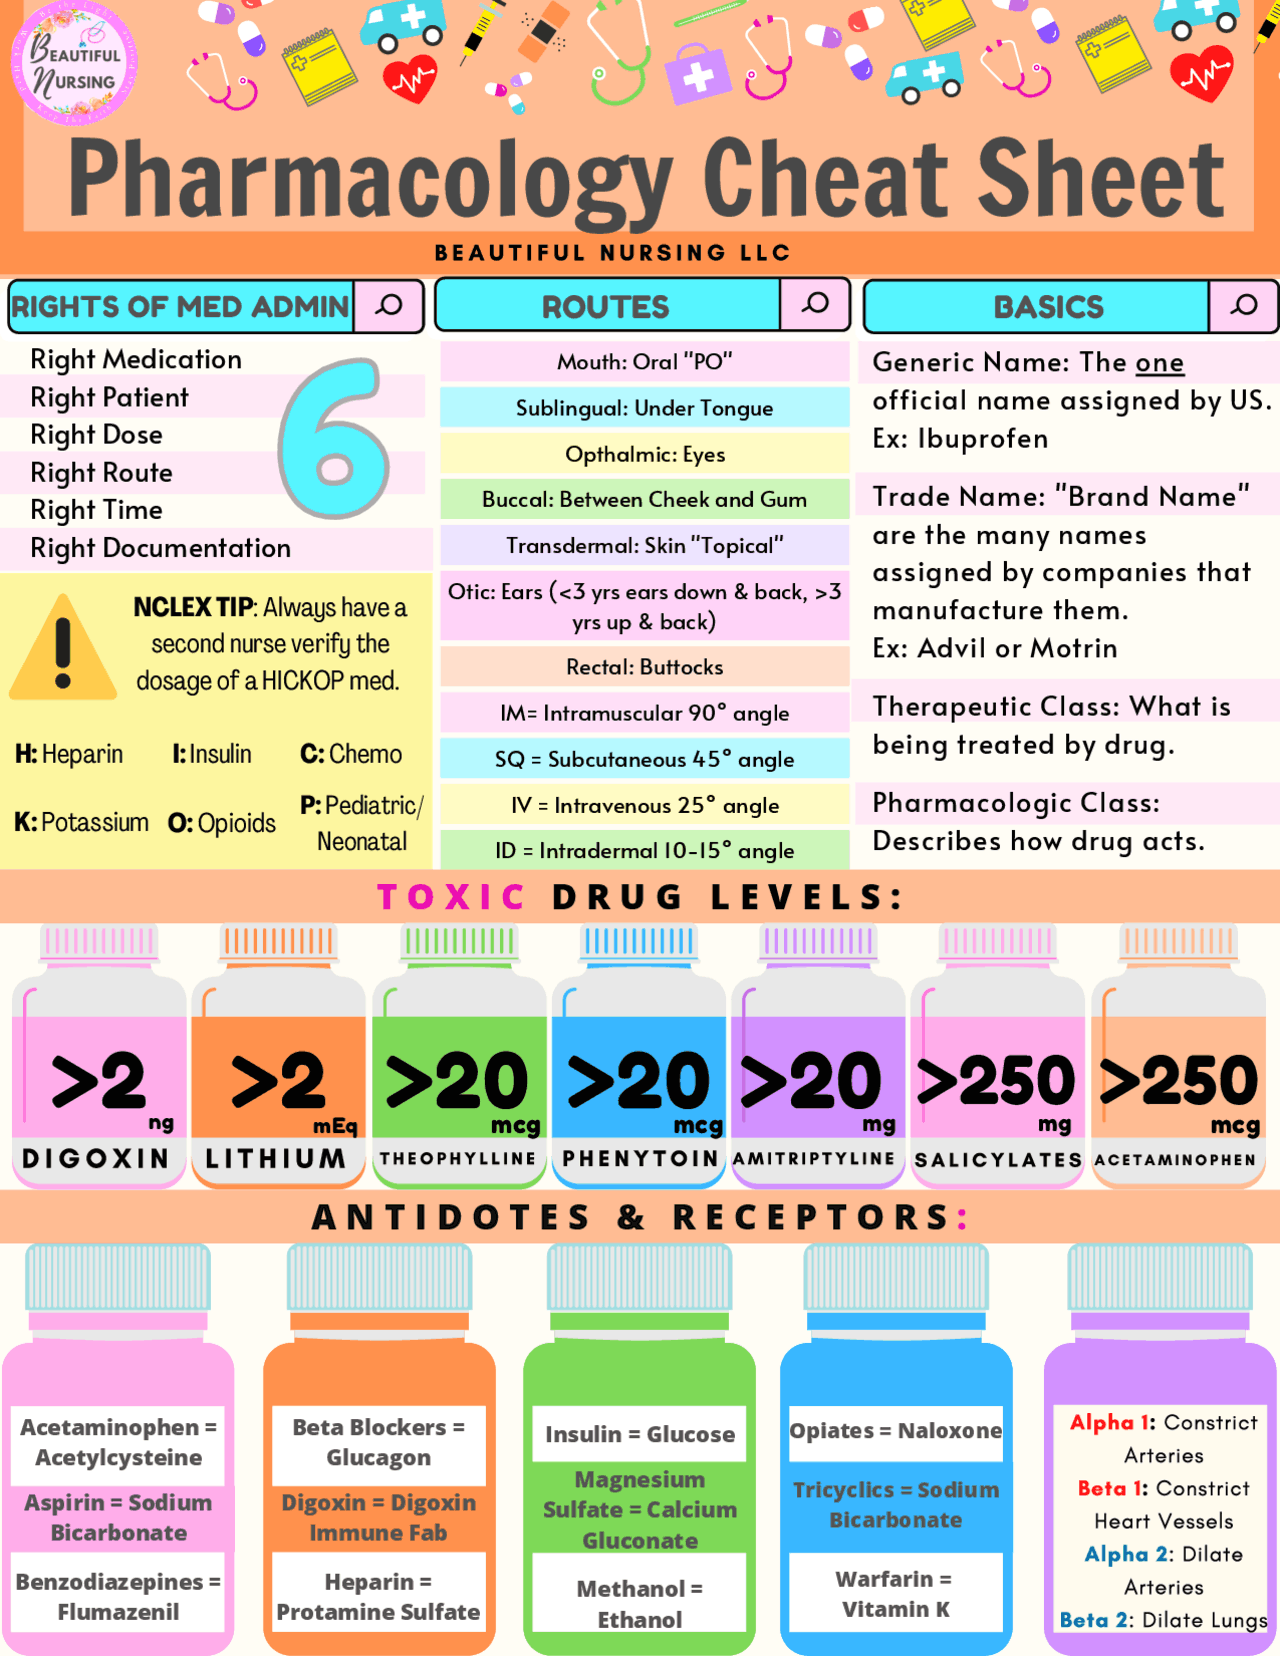
Anticoagulants are where most students stall out. The warfarin mechanism is straightforward: vitamin K antagonist, inhibits factors II, VII, IX, X, plus proteins C and S. What gets tested is the reversal strategy and the monitoring. INR target for atrial fibrillation is 2.0 to 3.0. Reversal with vitamin K takes about six to eight hours for partial effect and twenty-four hours for full effect. If the patient is actively bleeding, you add fresh frozen plasma or prothrombin complex concentrate for immediate effect. Four components in the concentrate, covers factors II, VII, IX, and X. That detail about the timing gap between vitamin K administration and actual anticoagulant reversal is worth more points than any single drug dose. Antibiotics follow a similar pattern. The mechanism is the anchor. Beta-lactams inhibit cell wall synthesis by binding penicillin-binding proteins. The clinical branch is the spectrum and the resistance mechanism. Amoxicillin covers streptococci and some gram-negatives but not pseudomonas. Piperacillin-tazobactam covers pseudomonas and adds a beta-lactamase inhibitor that covers ESBL-producing organisms but not carbapenemases. If a question mentions a KPC or NDM producer, the answer is a carbapenem or newer agent like ceftazidime-avibactam. T azobactam does not cover metallo-beta-lactamases because they use zinc instead of serine at the active site, and tazobactam is a serine-targeting inhibitor. That single biochemical detail separates responders from non-responders in real clinical practice.
Cheat Sheet For Pharmacology Easy organization tips
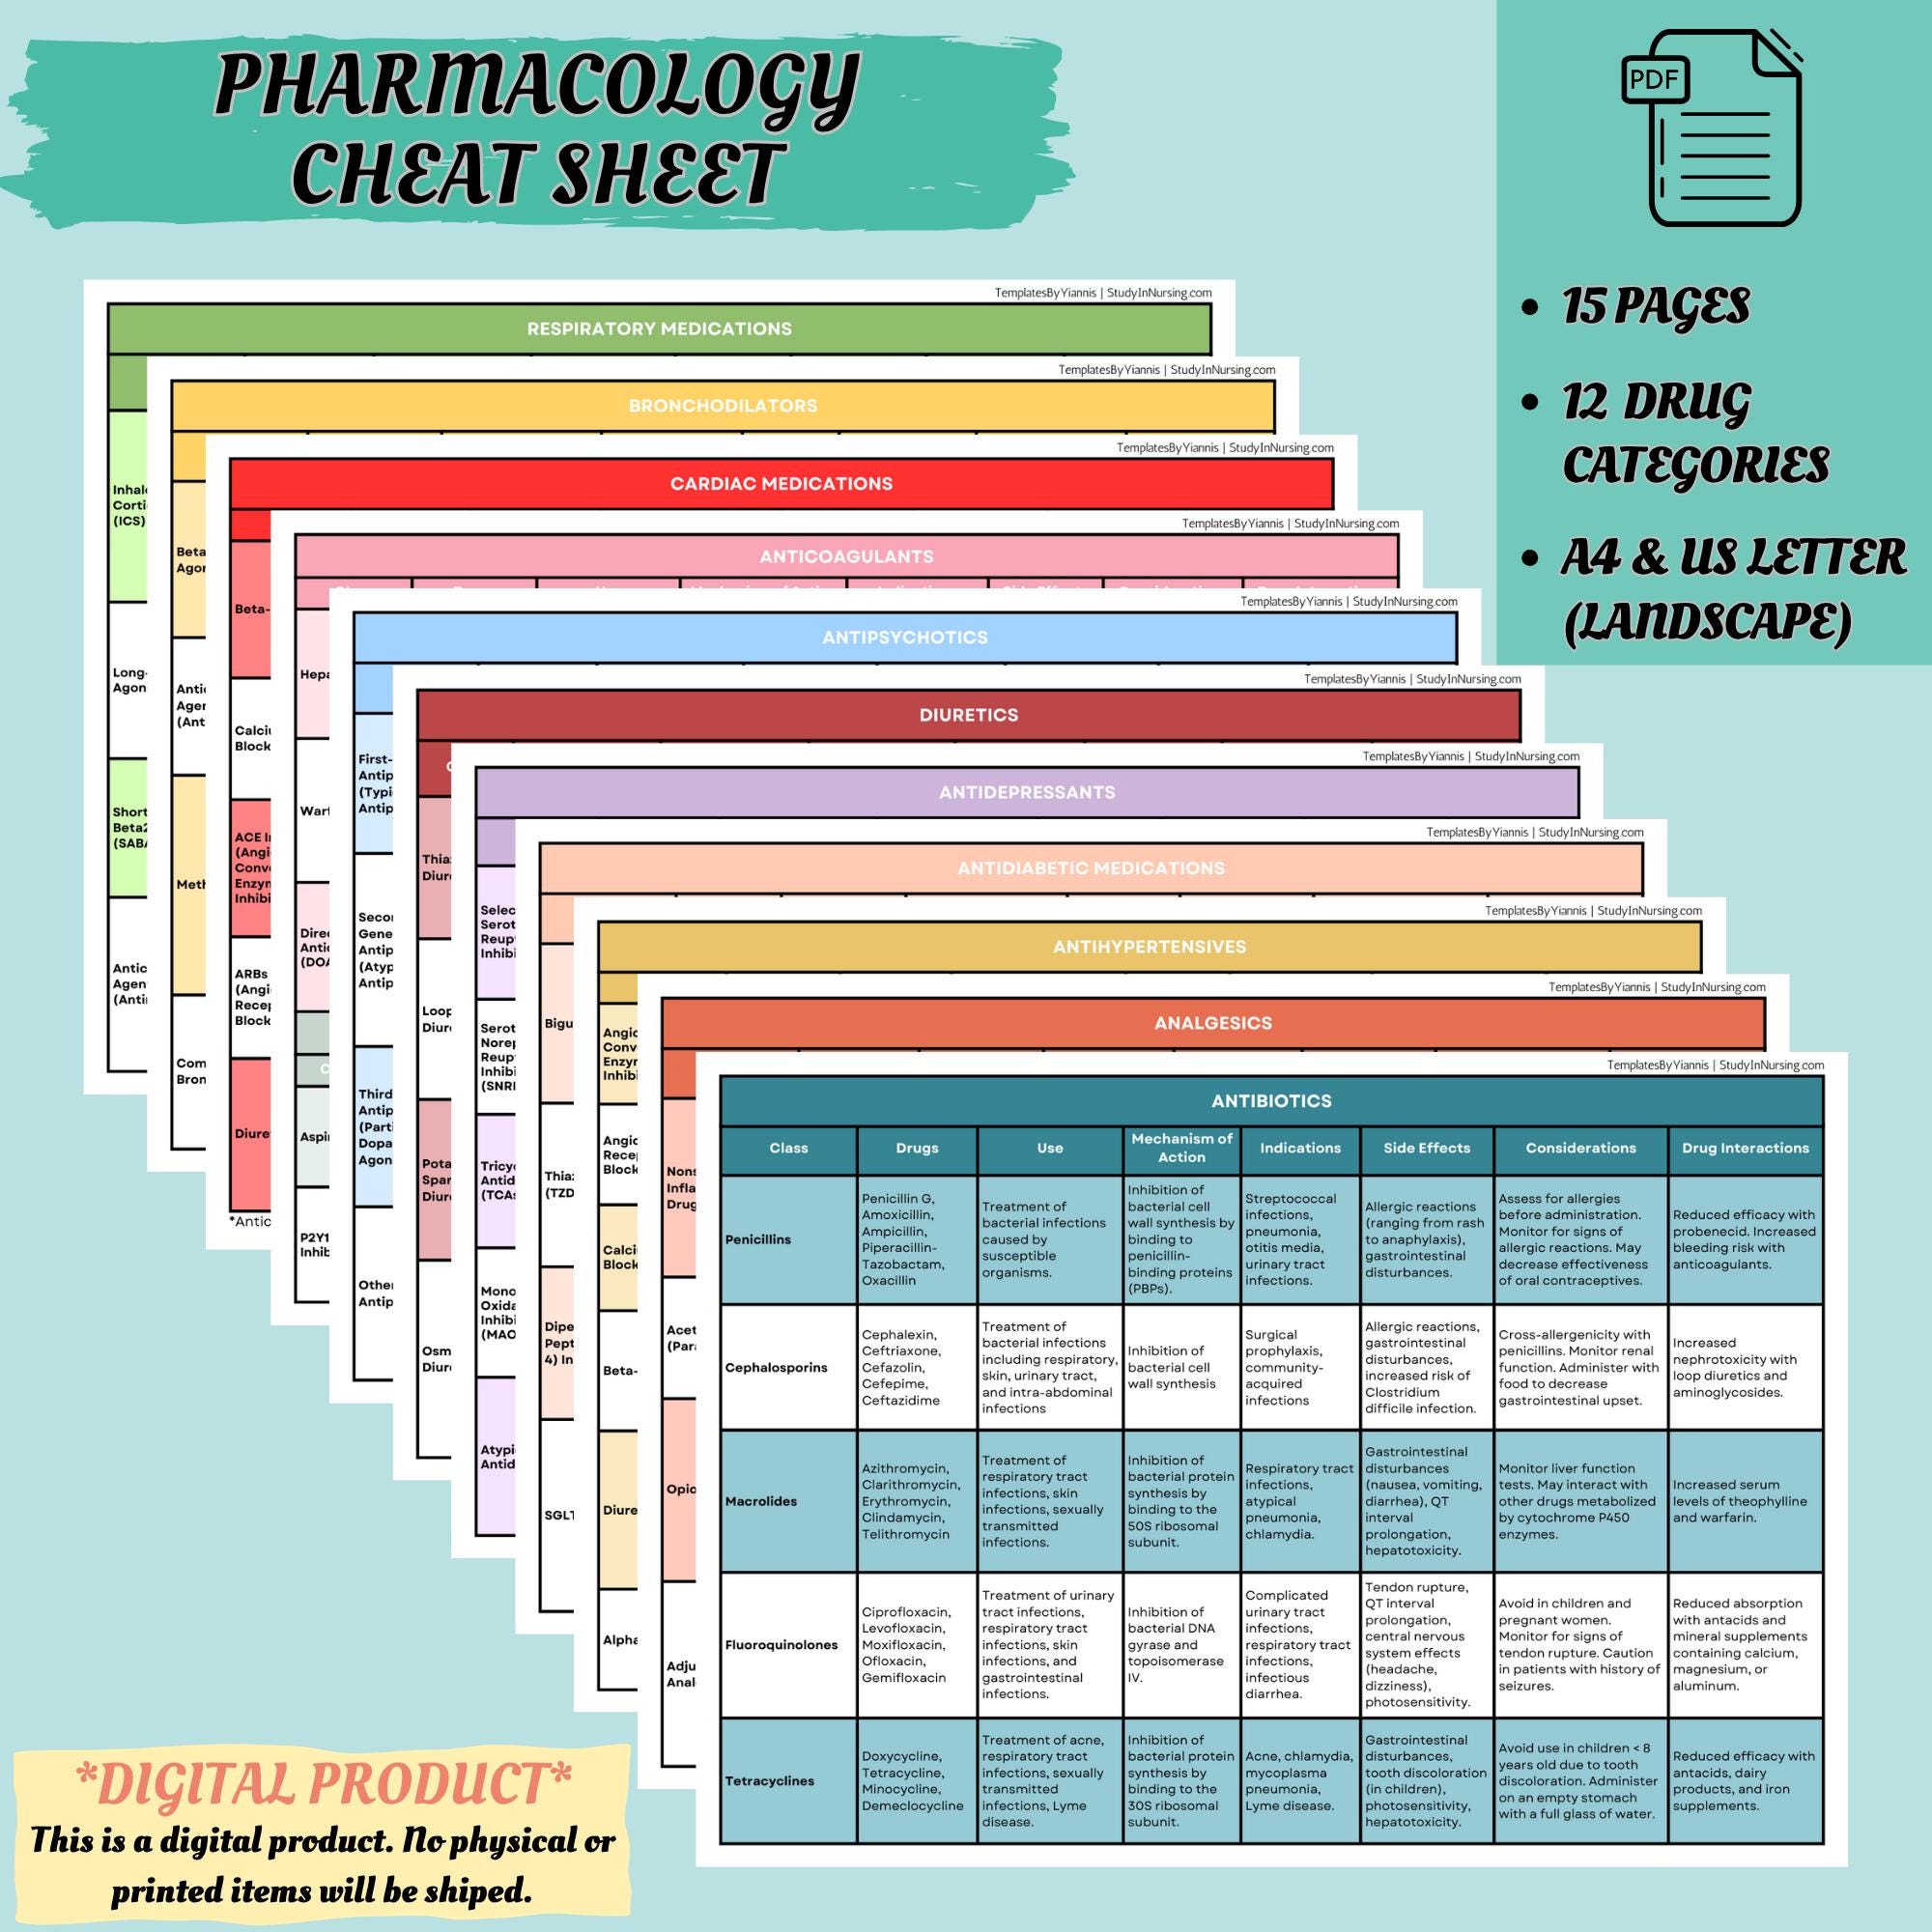
Keep each page to one therapeutic class. Do not combine anticoagulants and antiplatelets on the same sheet just because they both affect bleeding risk. The cognitive load of switching between mechanisms mid-page costs you retrieval speed. One page per class, one sheet per system. My complete set ended up at about twelve pages for the entire pharmacology curriculum, and each page took roughly fifteen minutes to build the first time. Use color coding sparingly. I used red for black box warnings and yellow for dose adjustment notes. Everything else stayed black text. Too many colors turns the sheet into a visual puzzle instead of a reference tool. The red and yellow system took me about five minutes to implement and saved me roughly ten minutes per exam session when I needed to check contraindications quickly. Include at least one clinical vignette per major drug group. Not a full case study, just a one-line scenario that forces you to apply the mechanism. For antiarrhythmics, I wrote: patient with atrial fibrillation and structural heart disease. Which drug do you avoid? The answer is flecainide, a Class IC agent that increases mortality in structural heart disease per the CAST trial. Without that one-line trigger, you might correctly identify flecainide's mechanism but fail to connect it to the clinical contraindication that actually appears on the exam.
Where the Cheat Sheet Approach Breaks Down
This method assumes you already understand the basic mechanism. If you do not know what a G-protein coupled receptor does, organizing drugs by receptor subtype will not help you. The sheet is a retrieval and integration tool, not a primary learning mechanism. I spent about forty hours learning the material the first time through textbooks and lectures, then another six hours building the sheets. The sheets themselves did not teach me pharmacology. They organized what I had already learned into a format I could access under time pressure. Another limitation is that pharmacology is constantly updated. New drug approvals, revised guidelines, safety warnings pulled from the market. My sheets from residency are now seven years old in some sections. The anticoagulant landscape changed significantly with the introduction of direct oral anticoagulants, which displaced warfarin for most non-valvular atrial fibrillation cases. A static cheat sheet will become stale unless you commit to a quarterly review cycle. I update mine every six months, which takes about two hours per update cycle. The biggest pitfall I see students fall into is building the sheet but never using it under test conditions. A beautifully organized reference is useless if you have never practiced retrieving information from it while a timer is running. I simulated exam conditions by covering the right half of each sheet and forcing myself to recall the mechanism, representative drugs, and one distinguishing feature within thirty seconds per entry. This practice took about twenty minutes per sheet and reduced my average question response time from roughly forty-five seconds to twenty-five seconds during actual exams.
Practical Build Walkthrough
Grab a fresh document or a physical notebook. Pick one class. Anticholinergics is a good starting point because the receptor subtypes create natural branching. Muscarinic antagonists: ipratropium for COPD because it is poorly absorbed systemically when inhaled, oxybutynin for overactive bladder because it has antispasmodic properties, scopolamine for motion sickness because it crosses the blood-brain barrier and acts on the vestibular nuclei. Now add the one detail that ties them together and separates them from each other. All three block muscarinic receptors. Ipratropium is quaternary ammonium, which means it does not cross membranes well and stays in the lung. Oxybutynin is tertiary amine, crosses into the bladder smooth muscle. Scopolamine is also tertiary amine but has high lipophilicity, which is why it reaches the central nervous system fast enough to prevent motion sickness symptoms within thirty minutes of transdermal application. That single paragraph contains the mechanism, three drugs, their distinguishing pharmacokinetic property, and the clinical implication of that property. That is the entire unit of knowledge you need to move on. If a question later asks why ipratropium causes less dry mouth than oxybutynin, you already have the answer in that paragraph without flipping to a different page.
I built my complete pharmacology reference using this exact unit method. Each unit is one mechanism, two to four drugs, one distinguishing feature, one clinical implication. The total set came to about one hundred and twenty units across twelve pages. Building it took roughly six hours total, spread across a week. Using it during exam prep cut my review time from about fifteen hours down to roughly four hours for the final pass. The format works because it mirrors how clinical reasoning actually functions. You do not think in drug names. You think in mechanisms and then select the agent whose properties match the patient's constraints. A Cheat Sheet For Pharmacology Easy system that organizes by mechanism first rather than by brand name second is the difference between recognizing a pattern and searching for a fact.