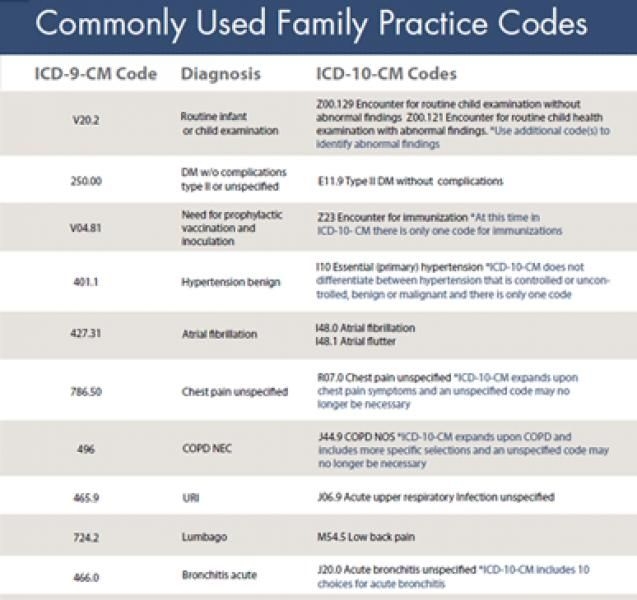
Why Everyone Needs a CPT Code Reference Sheet
CPT stands for Current Procedural Terminology. It is the standardized coding system used across the United States for medical billing and documentation. Physicians, facilities, and coders use these codes to describe every service they provide. The list itself is massive, and trying to memorize it is a recipe for burnout and billing errors. I keep a laminated cheat sheet at my desk. I print a fresh one every year when the updates come out. Without it, I was making mistakes on routine procedures like EKGs and vaccine administrations, which directly affects reimbursement timelines and claim denials.
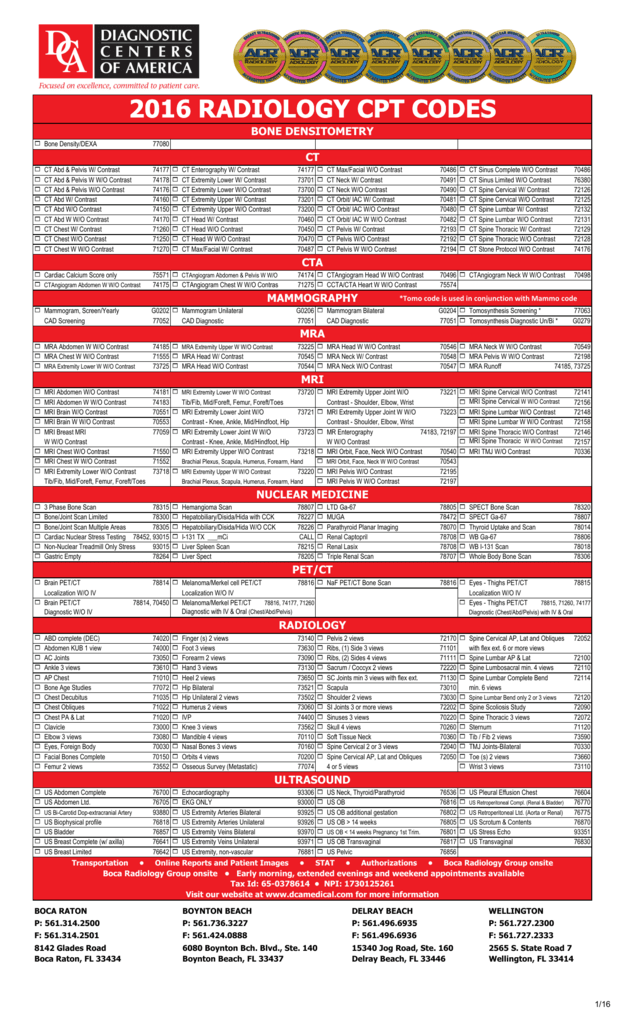
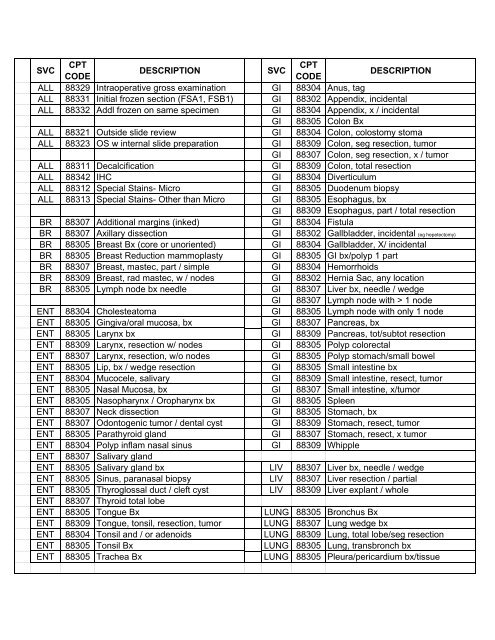
Cheat Sheet Free Printable Cpt Codes List
There are several free printable CPT code lists available online, but you need to pick one that is current. Old sheets cause claim rejections because codes get added, deleted, or revised every January. The AMA (American Medical Association) publishes the official codes, but their full book is expensive. Several legitimate sources offer condensed reference sheets for free. For a quick download, I usually grab mine from sites like the CMS.gov portal or the AAPC free resources section. Some clinics also maintain shared Google Sheets that get updated regularly. Whatever source you use, check the copyright date before you print and hang it up.
How to Use a CPT Cheat Sheet Efficientently
A cheat sheet is not a substitute for understanding the code set. It is a lookup tool for when you are uncertain. Start by pulling up the relevant section of the sheet based on the encounter type. If it is an office visit, look under Evaluation and Management (E/M). For lab work, check the Pathology and Laboratory section. For procedures, find the Anatomical System heading that matches. The most common mistake people make is grabbing the first code that looks right without verifying the modifiers. A 99213 without a modifier can look correct for a standard follow-up visit, but if the patient has a chronic condition requiring extra time and complex decision-making, you need the appropriate modifier or a higher level code. I learned this the hard way when a 47-patient panel got rejected because every single visit was coded as a 99212 when they should have been 99213 with modifier 25 attached to the procedure-driven visit.
Get the Full Details
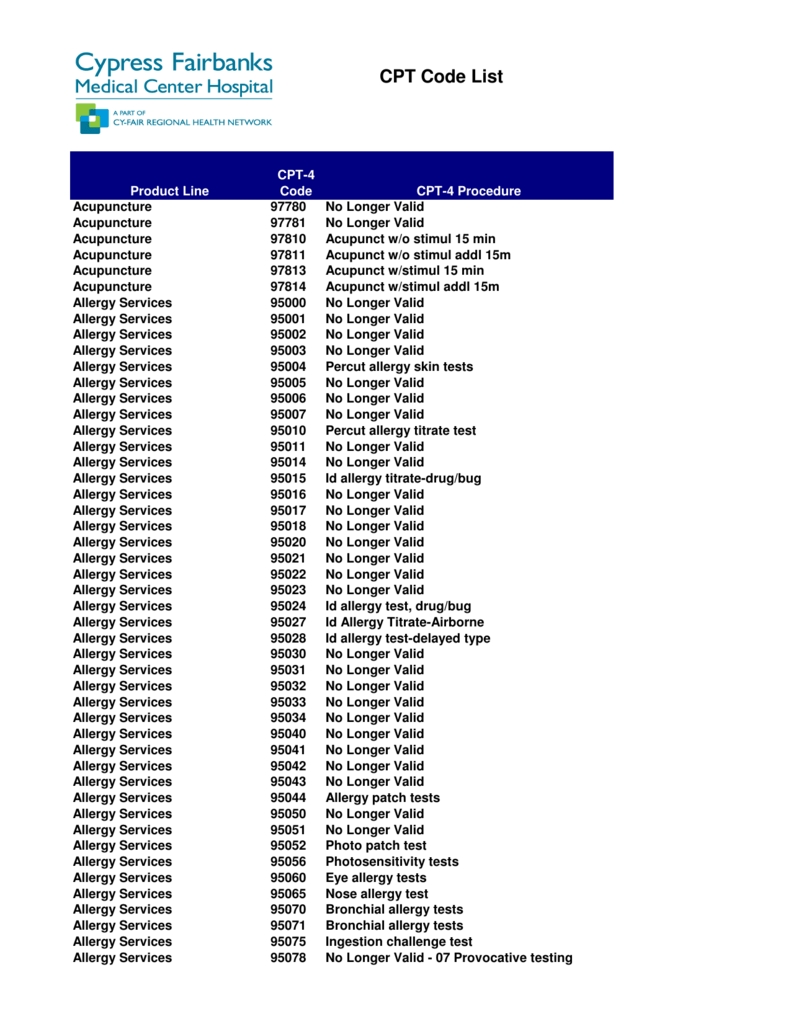
Key Sections on Every Cheat Sheet
Every decent reference sheet breaks the codes into major categories. Understanding these sections saves more time than anything else. Evaluation and Management (99202-99499) This is the bread and butter section. It covers office visits, hospital observations, consultations, and care management. Pay attention to the differences between new patient codes (99202-99205) and established patient codes (99211-99215). The documentation requirements shifted significantly in 2021, so any cheat sheet printed before 2022 is already outdated for E/M coding. The new guidelines focus on medical decision-making or total time spent rather than just the history and physical exam elements.
Medicine Section (90281-99608) This is the sprawling middle section covering everything from vaccines and immunizations to cardiology studies, hematology, and radiology. It is the most frequently referenced part of the sheet because most clinics run through vaccine codes and infusion procedures daily. I always keep a separate sticky note within this section for the 907xx vaccine administration codes since they change frequency and the bundling rules are tricky. If you bill a vaccine administration code alongside a E/M visit on the same day without the right modifier, the claim gets denied about half the time. Surgery Section (10021-69990)
This covers surgical procedures organized by anatomical body system. It is the largest section by far. Most general practices never touch more than 5 to 10 percent of these codes. You only need to familiarize yourself with the ones relevant to your specialty. A family medicine clinic will regularly use skin lesion excision codes, laceration repair codes, and arthrocentesis codes. A dermatologist will go much deeper into excision and destruction codes. Do not waste time studying surgical codes outside your scope. Radiology (70010-79999) Diagnostic imaging codes. These are mostly billed by the performing facility or radiologist. If you order an MRI and refer the patient out, you generally do not bill these codes. Keep them on the reference sheet for when you interpret studies or perform point-of-care ultrasound, which has become much more common in primary care settings over the last few years.
Pathology and Laboratory (80047-89398) Blood panels, urinalysis, microbiology, and toxicology codes. The key thing to remember here is the difference between a panel and individual component codes. A comprehensive metabolic panel (80053) includes ten individual tests. If you bill the individual components alongside the panel, the claim will flag for unbundling. This is one of the most common denial reasons I see at the clearinghouse level. Preventive Services (96121-96127, 98960-98962, 99381-99397)
Well-child exams, preventive cardiovascular screenings, and developmental screenings. These are heavily used in pediatric and family medicine. The preventive visit codes (99381-99397) replaced the old 9920x codes for wellness visits in many payer contracts. Make sure your cheat sheet reflects the current version.
Common Pitfalls That Waste Time
The biggest issue I see is people using a cheat sheet as a crutch instead of a reference. You should know your core codes by heart. A cheat sheet is for the borderline cases and the codes you rarely use. When I spend more than two minutes looking up a code on the sheet for something routine, I am wasting billable time. Another issue is printing sheets that are too large. A full CPT book is over a thousand pages. A cheat sheet should be one to three pages max. If yours is eight pages and you cannot find anything in it, it is not a cheat sheet. It is a burden. I trimmed my personal sheet down to the codes I actually use. I dropped about sixty percent of the entries and could find what I needed in under ten seconds. There is also the problem of payer-specific variations. Medicare, Medicaid, and private insurers sometimes bundle or unbundle codes differently. A code that is payable under Medicare may not be separately reimbursable under a commercial payer. My cheat sheet includes small handwritten notes next to frequently disputed codes to remind me which payers give trouble. This took me about three months of denial tracking to compile, but it has saved me countless hours since.
What the Cheat Sheet Cannot Replace
A printable sheet will not teach you medical necessity, modifier selection, or the documentation requirements for each code. Those are skills you develop through experience and ongoing education. The sheet helps you find the code. You still need to know whether that code applies to the specific clinical scenario and how to document it properly to withstand an audit. I have seen practices get hit with audits because they relied entirely on a free printable sheet from a random website. The codes were wrong. The modifiers were missing. The documentation did not support the level of service billed. The sheet was a starting point, not a guarantee. Always verify codes against the official CPT manual or your billing software before submitting a claim, especially for high-dollar procedures and surgical services. Print one. Tape it to your workstation. Update it every January. Use it as a quick reference while you build actual familiarity with the code set. That is the practical way to use it without creating more problems than it solves.