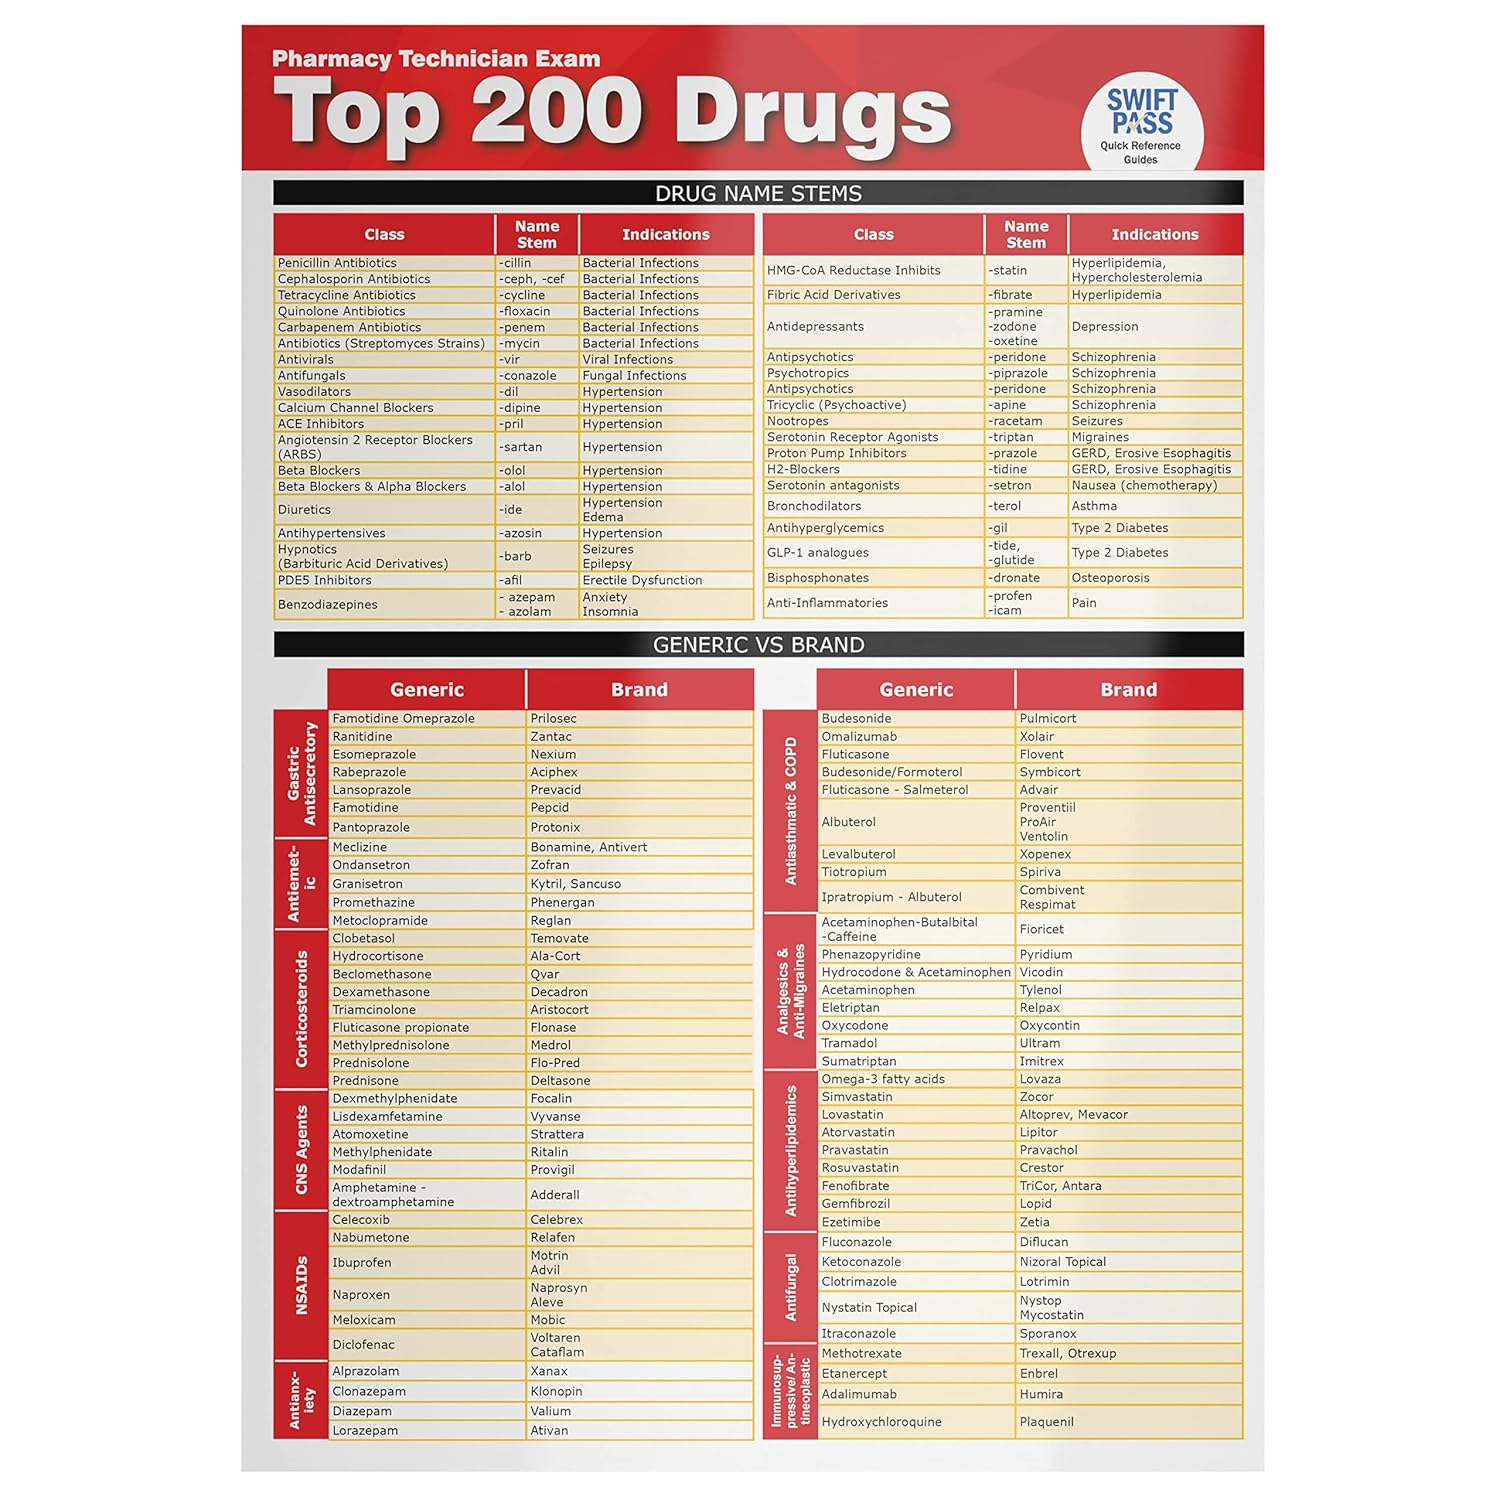
Why Most People Fail When They Try to Memorize These Drugs
People think they can just print out a list of the top 200 drugs, highlight everything in neon yellow, and ace their pharmacology exams. That never works. The problem isn't the volume of information. It's that they treat every drug the same way instead of recognizing which ones actually belong together in your memory. I spent three years in a hospital pharmacy before moving into clinical work, and I've seen students and even some practicing pharmacists get tripped up by the exact same misconceptions. Here's what actually happens when you try to use a Cheat Sheet Top 200 Drugs without the right framework.
Cheat Sheet Top 200 Drugs — How to Actually Use It
Start by separating the list into functional categories instead of alphabetical order. Alphabetical grouping is the single worst way to organize drug memorization because it forces your brain to treat unrelated medications as if they share connections they don't have. Here's the method I actually use: First, grab the list and circle every drug you already know cold. These are usually the ones you've encountered clinically or personally. For me, that was ACE inhibitors, metformin, atorvastatin, and levothyroxine right off the bat. Don't waste time on those yet. The list is meant to compress what you're still struggling with, not to reinforce what's already locked in.
Second, group the remaining drugs by mechanism of action. This is where most people jump straight to memorizing doses and side effects, which is backward. You need to understand why a drug works before you can remember its details. A beta-blocker like metoprolol doesn't share a clinical profile with a calcium channel blocker like amlodipine, even though they both treat hypertension. Grouping them separately prevents catastrophic confusion later when you're reading charts and need to switch between them quickly. Third, assign a priority level to each drug. The top 200 isn't a uniform list. Some of these appear in nearly every patient chart. Others show up once a month at most. I use a three-tier system: Tier 1 drugs demand full detail including mechanism, dose range, major interactions, and monitoring parameters. Tier 2 drugs need mechanism and one or two key clinical pearls. Tier 3 drugs you should at minimum recognize by name and general class. I ran into a specific problem once where a colleague of mine was studying the Cheat Sheet Top 200 Drugs for her NAPLEX prep and kept mixing up enalapril and lisinopril dosing because she had them adjacent to each other on her flashcard deck. She was pulling from a source that listed them alphabetically, so her brain was treating them as the same category even though their half-lives and frequency of dosing differ significantly. The workaround was simple: she rearranged the cards by subclass and added a separate column for renal clearance properties. That one adjustment cut her revision time in half and reduced her error rate on ACE inhibitor questions from about 40% to under 10%.
Get the Full Details

Here's a practical breakdown of the categories you should prioritize: Cardiovascular drugs take up roughly a third of any standard top 200 list. Antihypertensives, anticoagulants, antiarrhythmics, and lipid-lowering agents dominate this section. The common pitfall here is treating all antihypertensives as interchangeable for memorization purposes. They're not. An ACE inhibitor and a thiazide diuretic work through completely different pathways and have entirely different side effect profiles. A patient on lisinopril who develops a cough needs a different management strategy than a patient on hydrochlorothiazide who develops hyponatremia. Antimicrobials form another massive chunk. This is where students usually lose the most time because there are so many classes to sort through. The shortcut is to focus on the four major classes that appear constantly: penicillins, cephalosporins, fluoroquinolones, and macrolides. Vancomycin and metronidazole deserve separate attention because their dosing and monitoring protocols are distinctly different from the rest. Skip the detailed memorization of less commonly used antibiotics until you've locked down the core four classes.
Endocrine drugs, particularly the diabetes medications, deserve careful handling. Metformin, sulfonylureas, SGLT2 inhibitors, GLP-1 agonists, and insulin analogs each have their own learning curve. The trick is understanding that metformin is always first-line unless contraindicated, and the others are added based on specific patient factors like renal function, weight, and cardiovascular risk. Mixing up the mechanisms of SGLT2 inhibitors and GLP-1 agonists is a common mistake that leads to incorrect prescribing decisions in practice. Gastrointestinal drugs are often underrepresented on study lists but appear frequently enough on exams to merit attention. Proton pump inhibitors, H2 blockers, antiemetics, and laxatives each have their niche. The one I see people get wrong most often is distinguishing between ondansetron and promethazine for nausea management. They're both antiemetics but work through different receptor systems and carry different side effect concerns. Ondansetron prolongs the QT interval. Promethazine causes significant sedation and has anticholinergic effects. These differences matter clinically. A note on what this list cannot do for you:
A Cheat Sheet Top 200 Drugs is a compression tool. It is not a substitute for understanding pathophysiology. If you memorize that atorvastatin lowers LDL without understanding how HMG-CoA reductase inhibition works, you will struggle when exam questions ask about drug interactions or patient-specific dosing adjustments. The list shows you what to learn. It does not teach you why. Pair it with active recall practice and clinical scenario questions, not just passive reading. The biggest limitation of any drug cheat sheet is that it becomes outdated quickly. New formulations, black box warnings, and guideline changes happen constantly. A list you print in January might already have relevant changes by June. Always cross-reference with a current source like Micromedex or UpToDate before relying on memorized details for clinical decisions. Studying for exams is one thing. Practicing medicine is another. If you're preparing for a specific exam, check whether your test body provides an official drug list. The NAPLEX, for instance, has its own referenced formulary that sometimes diverges slightly from commercial top 200 lists. Using the wrong reference list means you could spend hours studying drugs that won't appear on your exam in the first place.

For downloading a usable version, most pharmacy review programs and medical education sites offer printable PDFs. The most reliable sources are typically the NAPLEX review materials from established pharmacy schools or clinical pharmacology textbooks like Katzung or Goodman & Gilman's companion guides. University pharmacy department websites also maintain updated lists that tend to be more accurate than random blog posts or social media shares. Build your personal version of the list. Print it, annotate it, redraw the categories in a way that makes sense for your own study pattern. The physical act of rewriting the information forces your brain to process it differently than passive highlighting ever will. I still have my original handwritten version from pharmacology school, covered in corrections and margin notes. It was far more useful than the printed sheets I bought from any commercial review service.
Bottom Line
A Cheat Sheet Top 200 Drugs works when you treat it as a starting point, not a finish line. Group by mechanism. Prioritize by clinical frequency. Verify against current sources. And never let the list replace actual understanding of why each drug exists in the first place.