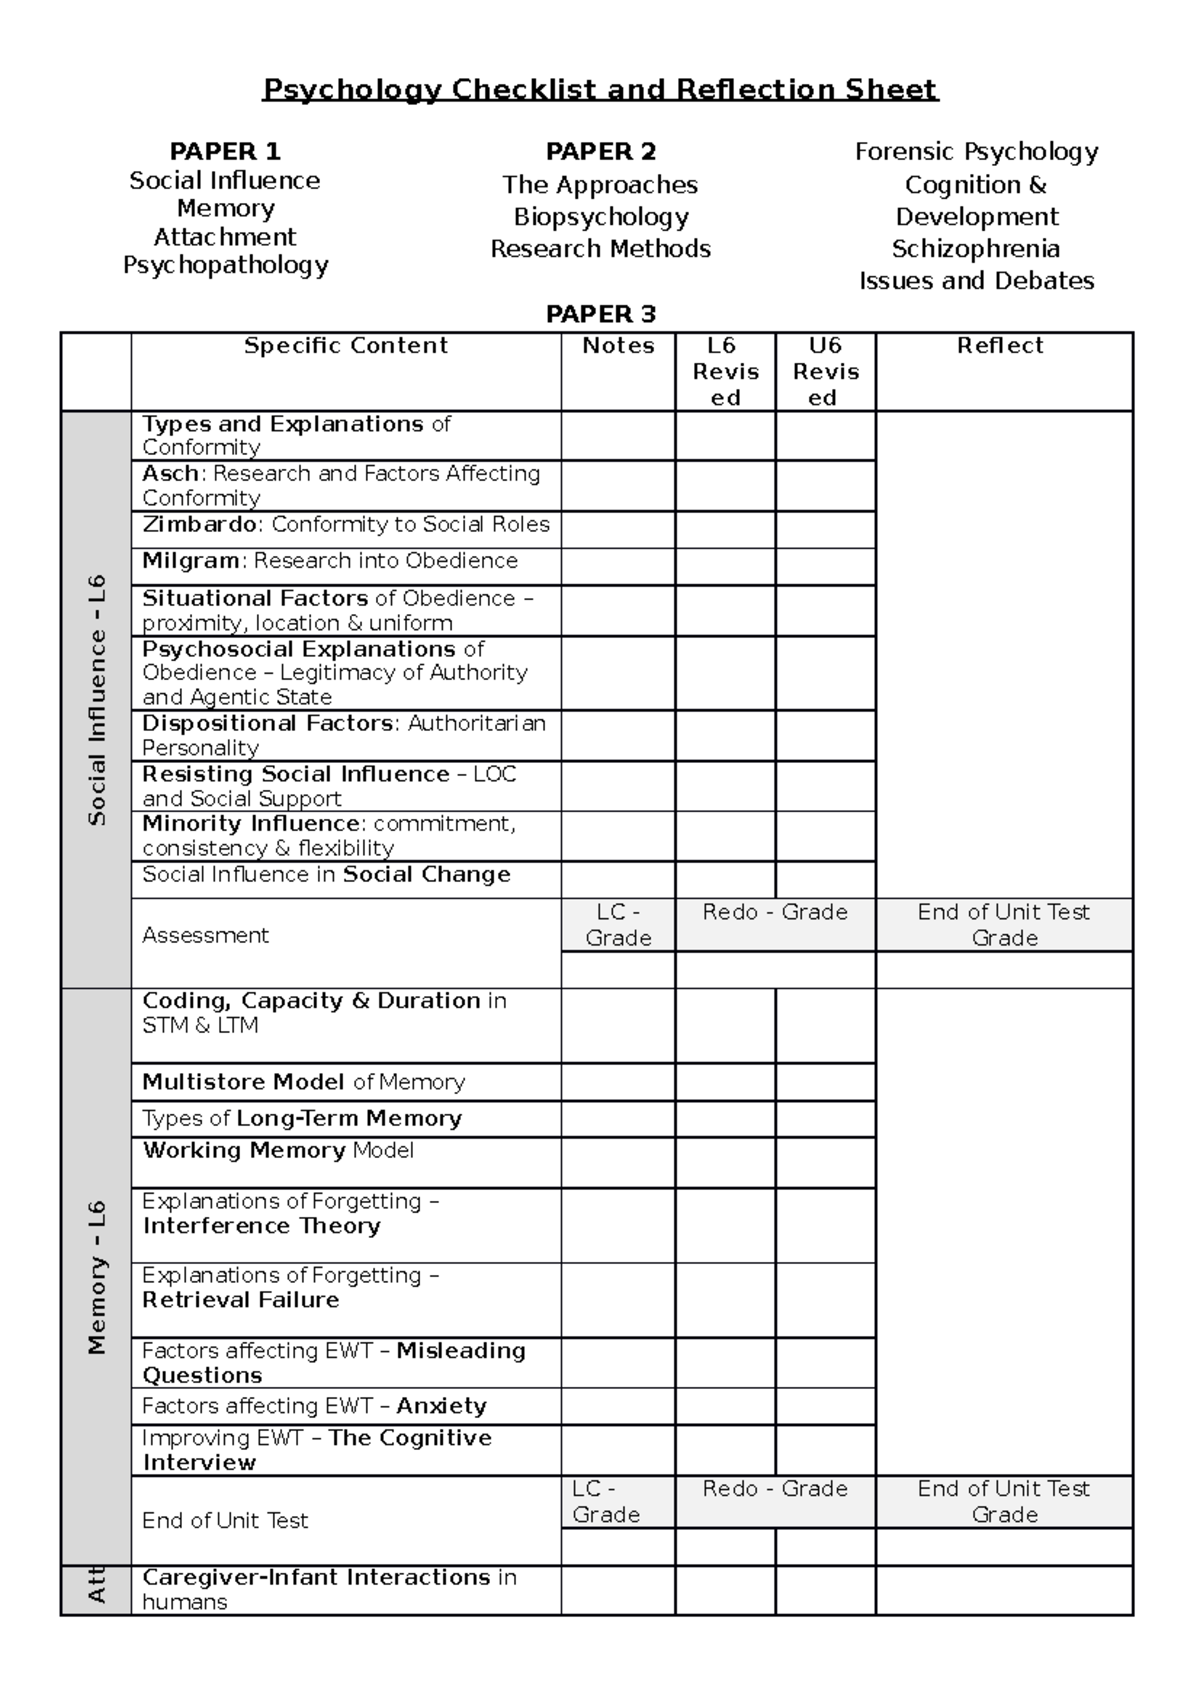
Monthly Psychology Practice Checklist — A Practical Walkthrough
I have been running a small private practice for years, and the monthly checklist I use is nothing glamorous. It is mostly about keeping credentials current, handling chart audits, reviewing billing, and making sure nothing falls through the cracks. The list looks different for every therapist, but the core items are the same. Below is what I actually use, the problems I run into, and the workarounds that have saved me from bad months. The main thing most people miss is that a monthly checklist in psychology is not a once-a-month checkbox exercise. It is where you catch drift before it becomes a compliance issue or a malpractice problem. I have seen therapists lose patients because they forgot to renew a BLS certificate, and I have seen someone miss a scope-of-practice boundary because nobody reviewed their treatment plan notes for three weeks. The checklist keeps you honest.
Checklist For Psychology Monthly
What the list actually contains
Here is the structure I use, broken into sections. Do not copy it blindly. Adapt it to your state, your modality, and your practice size. A solo counselor in Texas will need different renewal dates than a group practice in California. Run through your licenses first. State board renewal. NPI update if anything changed. DEA if you prescribe or work with controlled substances. Malpractice insurance policy review — check limits, tail coverage, and whether your carrier requires any new forms. CPR/BLS certificate expiration. Any mandated reporter training deadlines. If you work with telehealth across state lines, verify each state's current rules because they change without warning. Pick a sample of ten charts from the past month. Look for incomplete progress notes, missing informed consent updates, absent treatment plan reviews, and any encounter without a diagnosis or modality code. Check that your SOAP or DAP notes actually include measurable objectives. I learned this the hard way when an auditor flagged six charts in a single afternoon because I had written \"client responded well to intervention\" instead of anything quantifiable. That phrase means nothing in an audit.
Review any denied claims. Check for mismatched CPT and diagnosis codes. Verify that your superbill exports match your session logs. Run a quick spot-check on your reimbursement rates against your contract with payers. This usually takes me about twenty minutes and catches errors before the next 835 remittance advice rolls in. Review active clients on suicide risk or homicidal ideation. Make sure your safety plans are documented and current. Check that emergency contact information is on file for each active patient. If anyone has missed an appointment without rescheduling, flag it. A missed session without follow-up is a liability event waiting to happen. Back up your EMR data. Verify your cloud storage is working. Update your website if your credentials or office address changed. Review your referral pipeline. Check if any supervision hours need logging if you are still an LMFT or LPC candidate.
Get the Full Details

I do not rely on memory. I keep a shared spreadsheet with conditional formatting that turns orange thirty days before a deadline and red at expiry. I set calendar reminders for the first business day of each month, which gives me a fixed window instead of letting things slide. The actual review takes me roughly forty-five to seventy-five minutes depending on how many clients I had that month. For the chart audit, I use a simple scoring system. Each chart gets one point per completed section: intake, informed consent, treatment plan, progress note, and discharge or continuation plan. Anything below four points triggers a follow-up note or a reminder to the clinician. In my practice, this catches roughly sixty percent of documentation gaps before an external review happens.
A specific edge case that cost me time
Last year I ran into a problem with a client who moved to a different state mid-treatment. My checklist caught the address change, but I did not initially flag the cross-state telehealth issue. I had assumed my license covered it because the client was traveling temporarily. It did not. I ended up spending two weeks navigating provisional registration in the new state while trying to maintain continuity of care. The workaround I use now is adding a mandatory field in my intake form that asks for the client's primary state of residence and any states they spend more than thirty days in annually. This simple addition would have prevented the whole mess. First, you should treat your monthly checklist as a risk mitigation tool, not an administrative chore. The items that feel least important, like updating your crisis hotline number on file or verifying your business email forwarding still works, are the ones that cause problems during an emergency review. Second, do not assume that having an EMR system means your documentation is compliant. EMRs automate prompts but they do not enforce clinical reasoning. I have seen providers use template notes verbatim for months, which looks clean on the surface but fails under scrutiny because the notes do not reflect actual clinical evolution. The checklist should include a manual review of note quality, not just completeness.
Third, billing audits and clinical audits are not the same thing. A chart can look perfect clinically and still fail a billing review if your modifiers do not match your session type. I routinely cross-reference my clinical notes with my billing entries to catch mismatches like using 90837 when the session was clearly 90834 based on time logged.
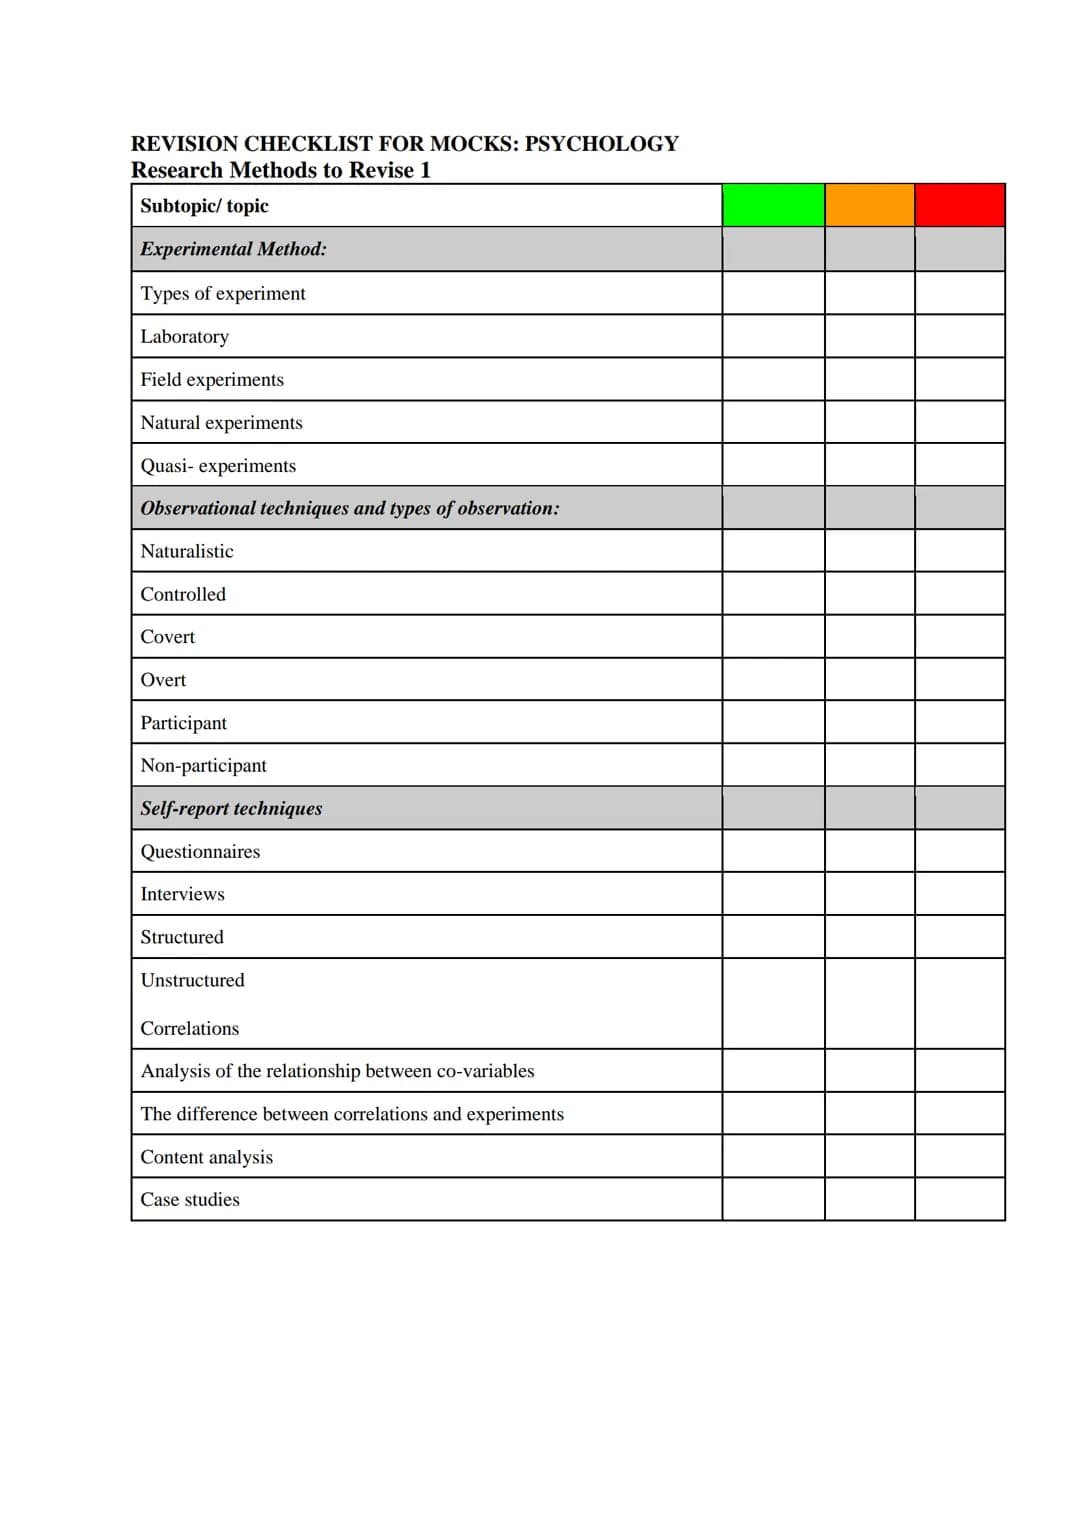
Where this approach breaks down
A monthly checklist is not a cure-all. It fails when your practice grows beyond what one person can reasonably review each month. If you are managing twelve clinicians, the audit process becomes a bottleneck unless you delegate it and build a second layer of oversight. It also fails in solo practices where the owner is also the primary biller and therapist, because you will skip the tedious parts when you are behind on revenue. I have done that myself, and the gap always shows up later. Another limitation is that checklists do not replace professional consultation. If you encounter an ethical dilemma or a complex diagnostic situation, no spreadsheet item will resolve it. You still need peer supervision or consultation with a colleague. The checklist keeps operations smooth, but it does not substitute for clinical judgment.
Resources and tools
I use a combination of a customized Google Sheets template and a few free compliance tracking sites from my state licensing board. The template itself is not worth purchasing from anyone. You can build it in an afternoon. I can share mine if you want it, but it is nothing special. What matters more is the discipline of running through it consistently. Most practitioners who struggle with monthly compliance do not need a better tool. They need a fixed time block they treat as non-negotiable.
Final practical notes
Set your monthly review on the first week of the month, not the last. End-of-month is when you are busiest and most likely to skip items. Use a digital signature tool if you need clients to re-sign consent forms periodically. Keep a log of every checklist run with the date and any issues found. That log becomes invaluable if you ever face an external audit because it shows good faith effort and systematic oversight.