Chelation Therapy For Alzheimers: What Actually Happens When You Try It
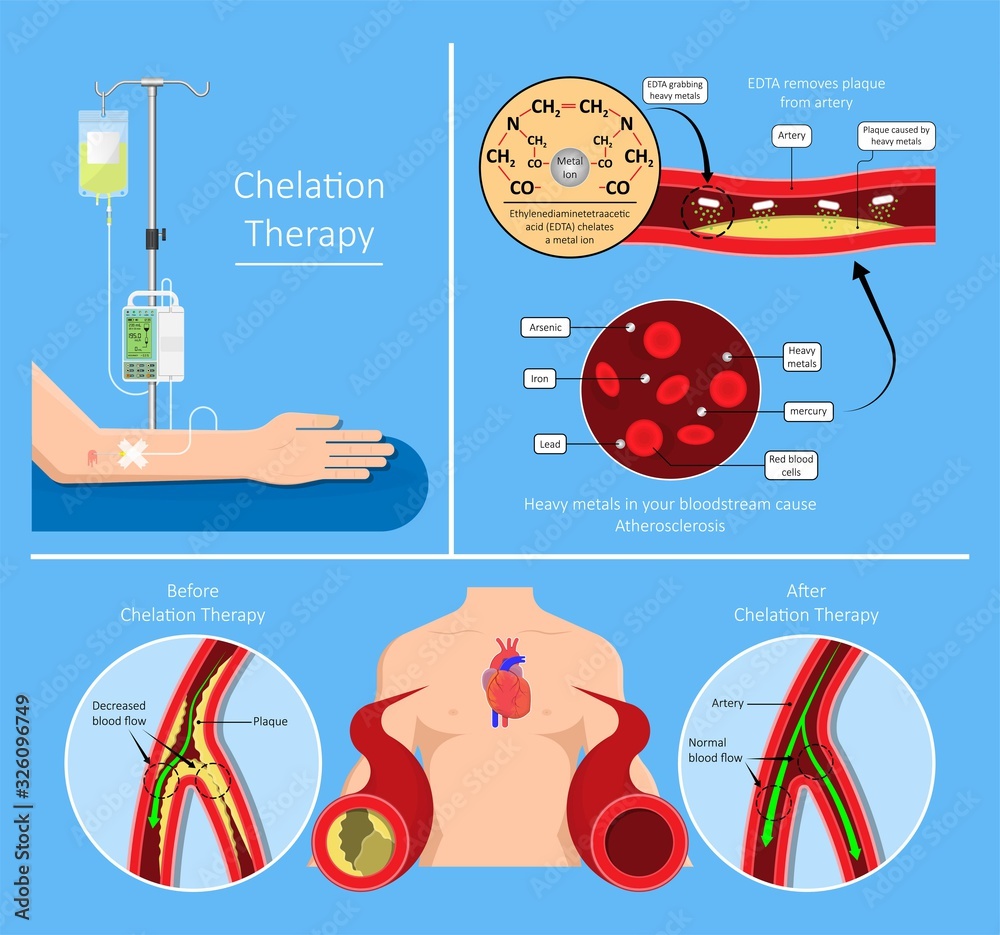
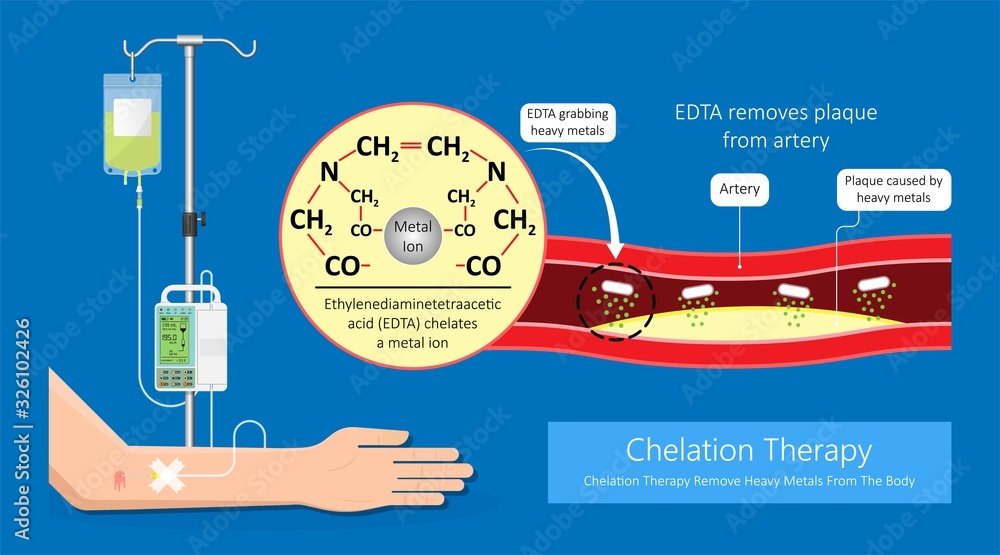
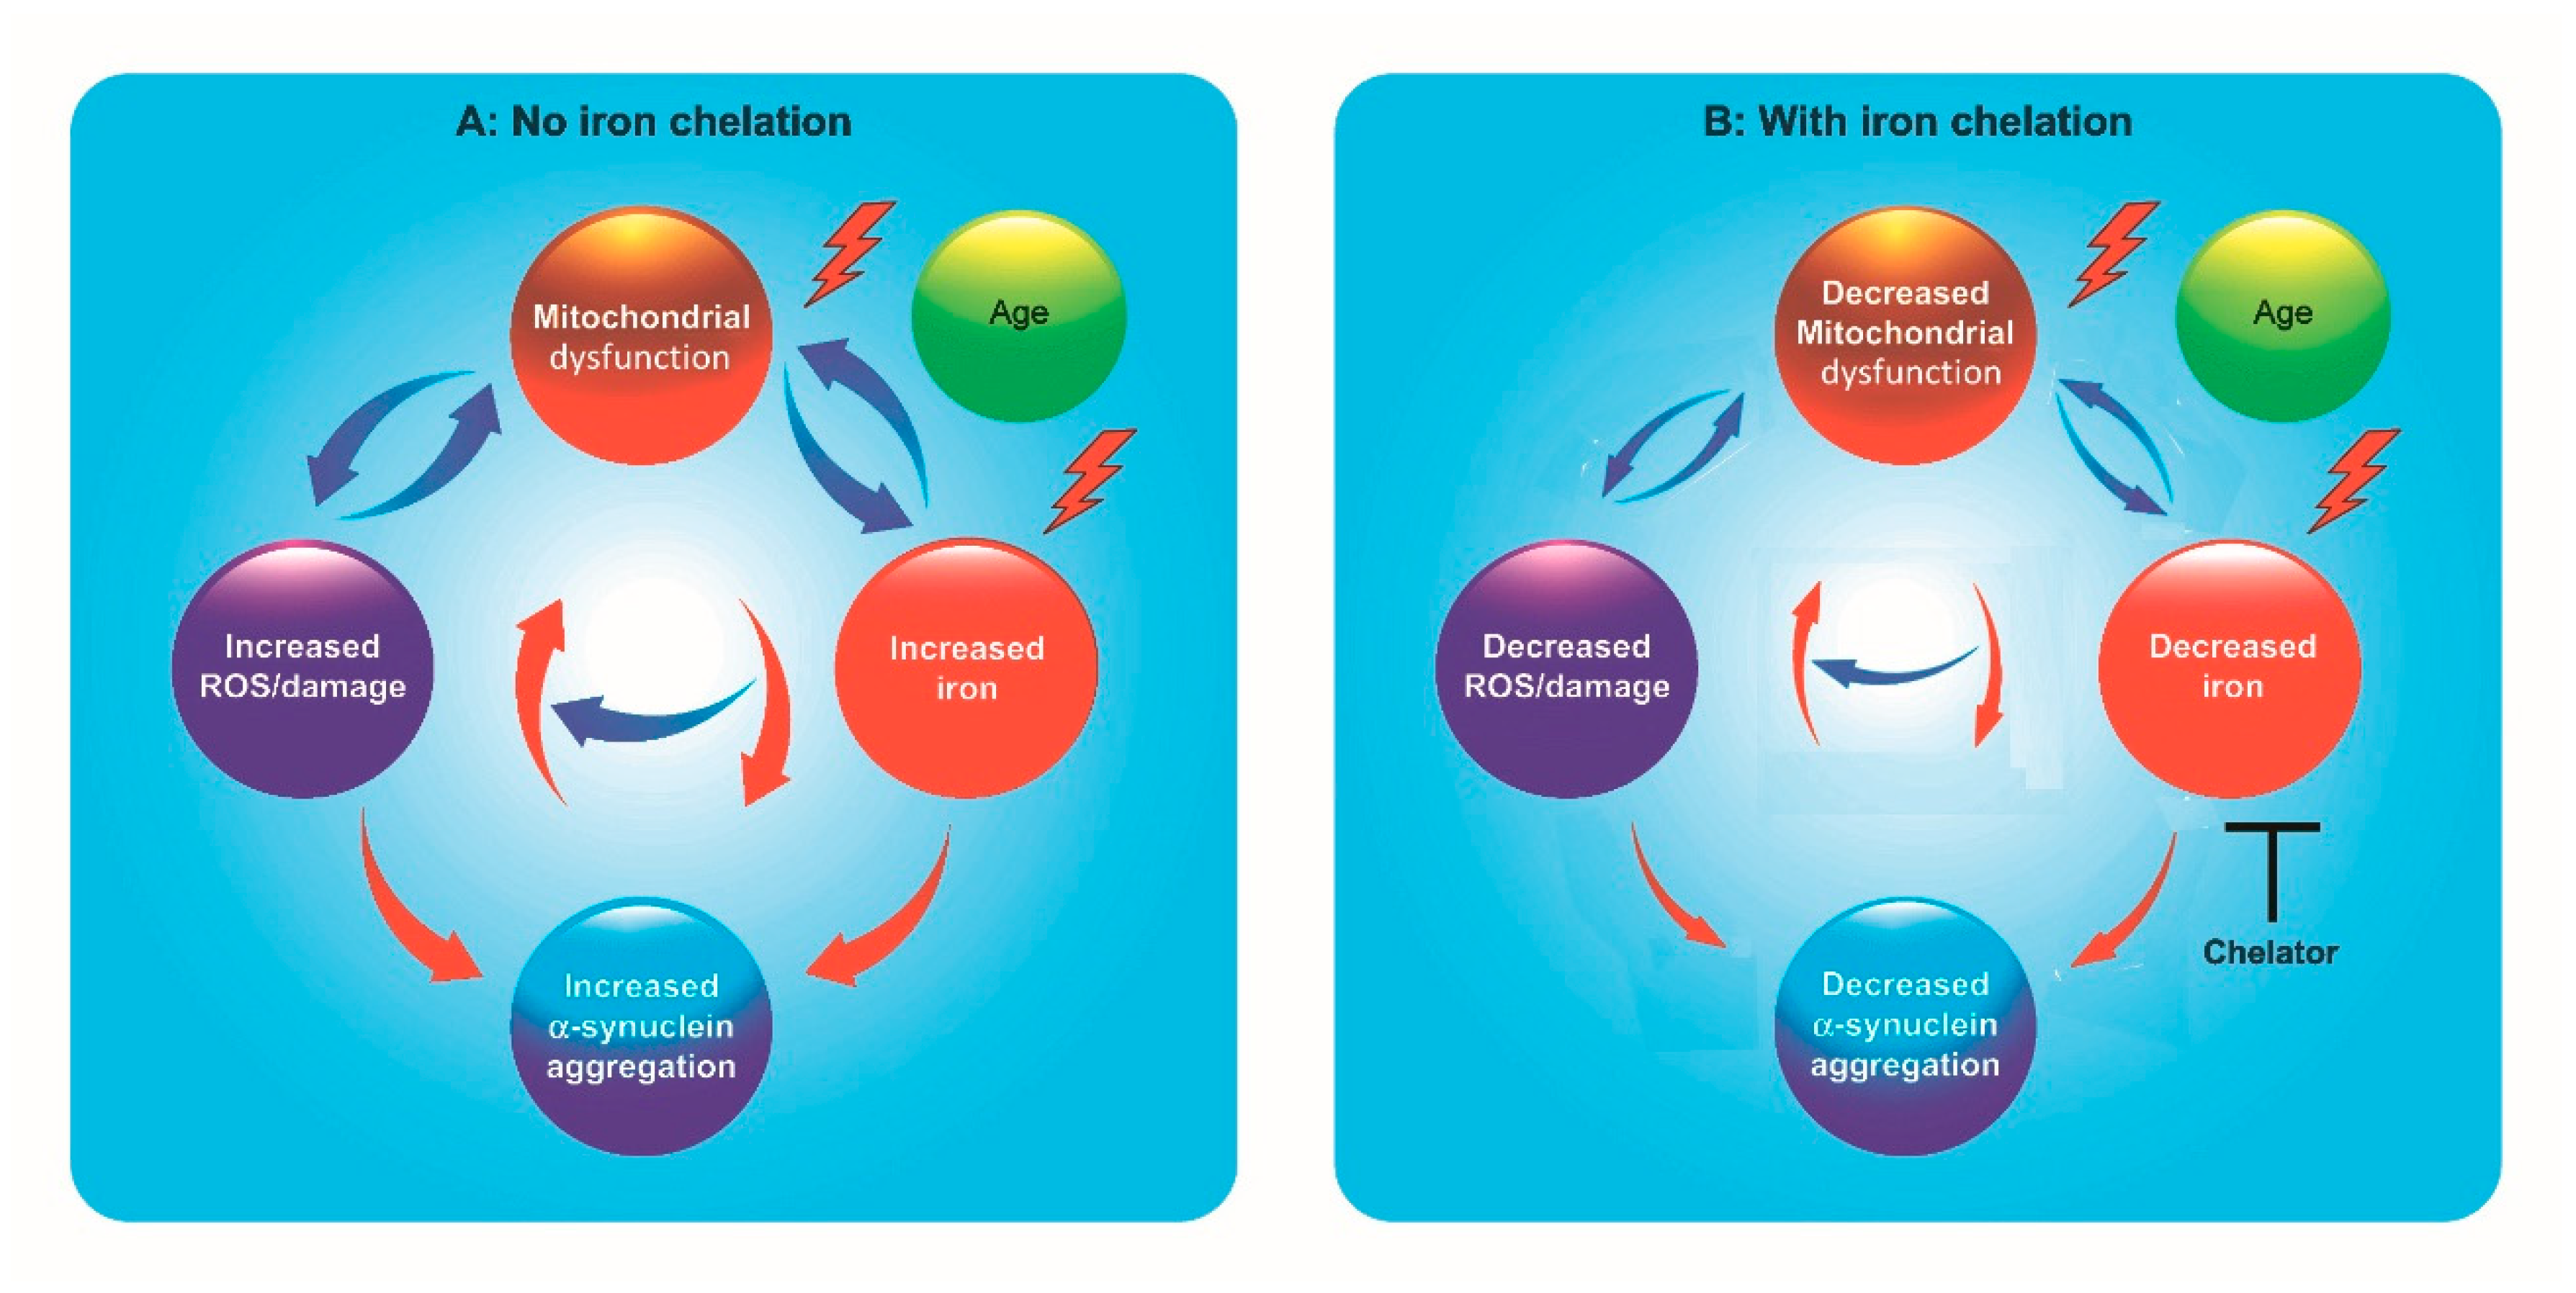
I've watched this topic cycle through patient forums and Reddit threads about six times over the last decade, and every time it resurfaces, the same pattern repeats. Someone reads a paper about aluminum in brain tissue, decides to order EDTA online, and by the end of a month they've accidentally stripped their calcium levels. I'm not here to tell you whether it works or doesn't. I'm here to explain what the actual protocol looks like, what the studies say, and what goes wrong when you ignore the chemistry. Chelation works by introducing a molecule that has a high affinity for metal ions. The classic agent is EDTA (ethylenediaminetetraacetic acid), which wraps around metals like lead, mercury, and yes, aluminum, forming a stable complex that the kidneys can excrete. DMSA and DMPS are alternative agents that are more selective and easier to dose orally. The theory behind using this in Alzheimer's is straightforward: if heavy metals accumulate in brain tissue and contribute to amyloid plaque formation or tau tangle pathology, removing them should slow or reverse cognitive decline.
The Reality of Chelation Therapy For Alzheimers
The reality is messier. The main clinical trial worth knowing about is the CHAT study published around 2009-2011, which looked at intravenous EDTA in patients with mild-to-moderate Alzheimer's. The results were... not enthusiastic. There was a slight cognitive signal in one subgroup, but the overall findings were underpowered and the study was discontinued early due to poor recruitment. Since then, nothing substantial has moved the needle. A few small case reports pop up occasionally, but there is no large-scale evidence that chelation alters the course of Alzheimer's disease. That said, people still try it. Here is how the protocol typically works when done through a practitioner who actually understands what they are doing. Step one is testing. You need a baseline before you start chelating anything. This means a provocation challenge test using DMSA or EDTA followed by a 24-hour urine collection, plus serum mineral panels and renal function markers. Without a provocation test, you are guessing. A standard 24-hour urine panel alone underestimates body burden because it only measures what is freely circulating, not what is sequestered in tissue. The provocation test mobilizes stored metals into the bloodstream so they can be excreted and measured.
Step two is choosing the agent and route. Oral DMSA is the most common starting point because it is safer and easier to manage. The typical dose ranges from 250 mg twice daily to three times daily, depending on weight and tolerability. IV EDTA is more aggressive and requires cardiac monitoring during infusion. It is usually given at 1-2 grams diluted in 500 mL of saline over two to four hours, once or twice a week. The reason IV is preferred in some protocols is that oral EDTA has very poor bioavailability — around 5% or less in adults — which means you need enormous doses to get any systemic effect. That also means oral EDTA mostly chelates gut minerals, which causes diarrhea and nutrient depletion without doing much for brain metals. Step three is supporting the organs of elimination. This is where most people fail. Chelation mobilizes metals into the bloodstream, and they need to exit through the kidneys, liver, and colon. If any of those pathways are sluggish, the metals just circulate and potentially re-deposit elsewhere. I have seen this repeatedly. A patient will start chelation, feel temporarily better as inflammatory metal loads drop, then crash hard three weeks in because their glutathione reserves are depleted and their bile flow is poor. The mobilized metals have nowhere to go and they start causing neurological symptoms again, worse than before. The practical workaround is to support detox pathways from day one. N-acetylcysteine for glutathione, milk thistle or TUDCA for bile flow, and adequate fiber intake to bind metals in the gut. Hydration matters more than you would think. On chelation days, patients should be drinking at least 2.5 to 3 liters of water to keep renal clearance efficient. Without that, you are essentially shuttling toxins into your bloodstream faster than your kidneys can filter them out.
Get the Full Details

Monitoring is non-negotiable. Every two to four weeks you need basic metabolic panels, renal function tests, and a mineral repletion check. EDTA will chelate calcium, magnesium, and zinc along with the target metals. If you are not supplementing magnesium and zinc adequately during a course, you will develop cramps, arrhythmias, and immune dysfunction. I once had a patient who skipped the magnesium supplementation because she felt fine and her legs started seizing during a routine infusion. We stopped the chelation immediately and restored her electrolytes over two weeks. She resumed at half the dose with magnesium running at 400 mg daily in divided doses, and the seizures never returned. There are specific complications that people rarely warn about. Rebound mobilization is one. When you stop chelating after a long course, metals that were sequestered in bone and fat can slowly leach back into circulation over weeks or months. This is why cycles are important — typically three weeks on, one week off, then reassess with repeat provocation testing before deciding whether to continue. Another issue is nutrient stripping. Beyond magnesium and zinc, B vitamins and iron can take hits during prolonged chelation. A basic multimineral taken between doses, not during, helps mitigate this. Who should not attempt this. Anyone with Stage 3 or 4 chronic kidney disease. EDTA is cleared renally and can accumulate to toxic levels. People with Parkinson's disease who are on chelation for heavy metal exposure rather than Alzheimer's need to be extremely cautious — there is some research suggesting chelation might worsen Parkinsonian symptoms by depleting copper and iron that dopaminergic neurons rely on. Pregnant women should absolutely not do this. Chelators cross the placenta and can strip minerals from the developing fetal brain.
The bottom line is that chelation therapy for Alzheimer's remains experimental with weak evidence. It is not recommended by any major neurology guideline. If you or someone you care about is considering it, the responsible path is through a qualified practitioner who can monitor labs, manage side effects, and reassess whether the risk-benefit ratio still makes sense after a few months. Self-prescribing from internet protocols is how people end up in the ER with hypocalcemic tetany, and that outcome is entirely preventable.