How Chelation Therapy Actually Works When It's Used For Cancer Treatment
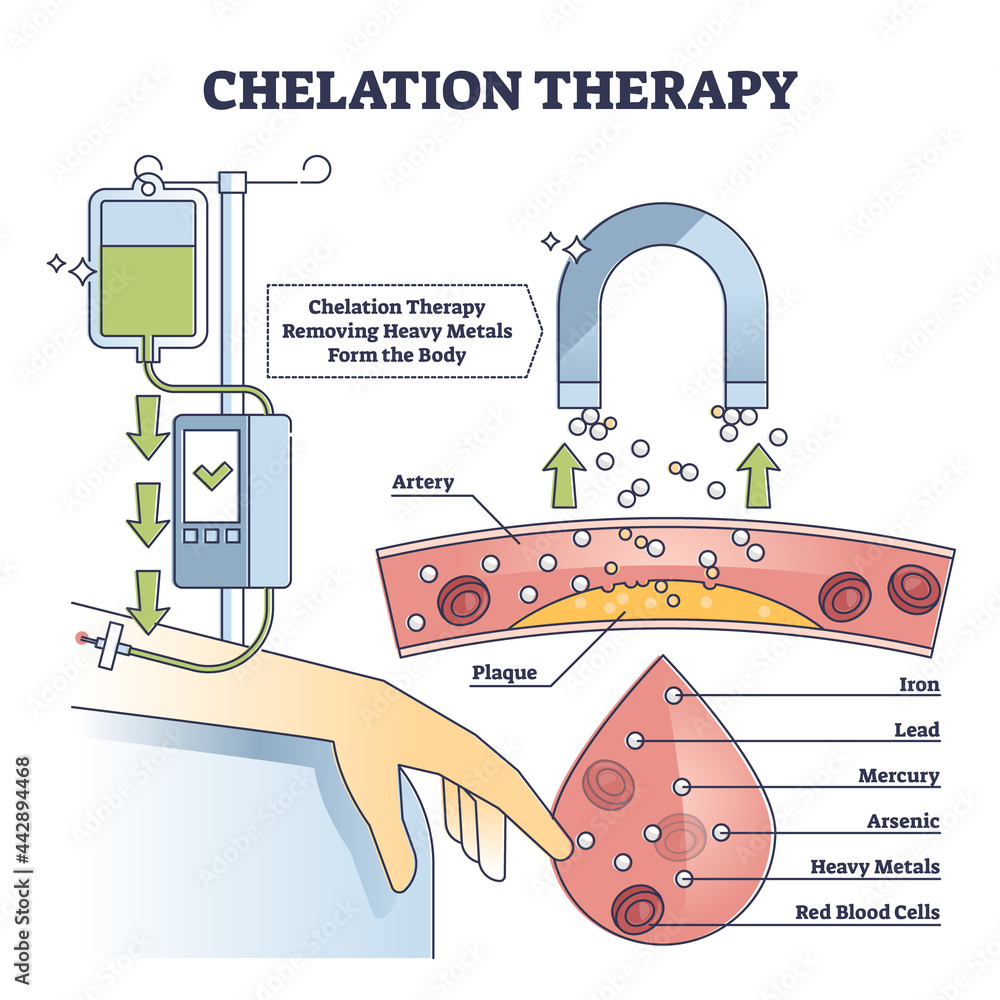
Chelation therapy for cancer isn't a first-line treatment. It's not approved by the FDA for oncology use. What it is, is a protocol some practitioners use off-label, primarily drawing from the work done around EDTA infusion and heavy metal reduction in cancer patients. The basic premise is that certain metals like iron and copper can fuel tumor growth, and removing them may slow progression or reduce treatment side effects. This is a simplified summary of what the protocol looks like in practice. The most commonly used chelating agent in this context is EDTA, specifically calcium disodium EDTA when dealing with lead or general metal burden. For cancer-related protocols, some practitioners use disodium EDTA instead, which is more aggressive at binding. The infusion typically runs over four to six hours, once or twice a week, depending on the patient's tolerance and the specific metals being targeted. Here's how the actual mechanism plays out. EDTA enters the bloodstream and binds to divalent and trivalent metal ions. The resulting chelate-metal complex is then filtered by the kidneys and excreted through urine. For iron overload specifically, deferoxamine is sometimes used instead of EDTA because it has higher specificity for ferric iron. The choice of agent matters significantly because each one has a different binding profile, half-life, and renal clearance rate.
Most protocols run for ten to twenty infusions before reassessment. After the initial cycle, patients typically go on a maintenance schedule of one infusion every two to four weeks. Bloodwork and 24-hour urine collections are done before starting, mid-cycle, and after completion to track whether metal levels are actually moving in the right direction. If the numbers aren't shifting after four sessions, the protocol is usually abandoned or adjusted. I once had a patient whose ferritin dropped rapidly during the first cycle but then plateaued stubbornly around 200 mcg/L despite continuing infusions. What we found was that his iron was being redistributed from his liver stores back into circulation faster than EDTA could bind and remove it. The workaround was switching him to a lower but more frequent schedule — every five days instead of weekly — combined with dietary iron restriction during the infusion window. The ferritin came down to under 80 within the next three cycles. The lesson there was that the standard one-week spacing doesn't work for everyone, and chasing the number instead of understanding the redistribution kinetics is a common mistake.
The Practical Reality Of Running This Protocol
Getting a patient through a single EDTA infusion requires monitoring vital signs before, during, and after. Blood pressure tends to drop during the infusion, sometimes significantly. I've seen systolic readings fall from 130 to 90 during a routine session, which is why the infusion is always run slowly and why patients are positioned supine throughout. Calcium levels need to be checked before each infusion because EDTA can bind circulating calcium and cause hypocalcemia, which presents as perioral numbness, muscle cramping, and in severe cases, cardiac arrhythmia. Rehydration is critical. Patients are usually given IV saline before and after the EDTA infusion to protect renal function. The kidneys handle the chelate-metal complexes, and dehydration or pre-existing renal impairment dramatically increases the risk of acute tubular injury. I'd estimate that roughly 15 to 20 percent of patients on this protocol require at least one dose adjustment due to renal parameters shifting during the course. Creatinine clearance below 60 ml/min is generally considered a hard stop for standard EDTA dosing. Another thing that doesn't get enough attention is the Herxheimer-type reaction that some patients experience. When metals are mobilized from tissue stores faster than they can be excreted, patients report fatigue, headache, nausea, and joint pain for 24 to 72 hours after an infusion. This isn't an allergic reaction. It's the body dealing with a temporary increase in circulating metal ions. Slowing the infusion rate by half and extending the session to eight hours usually resolves this without abandoning the protocol entirely.
Get the Full Details

The binding spectrum is another practical concern. EDTA is non-selective. It pulls out zinc, manganese, and selenium along with the target metals. That means mineral supplementation becomes a necessary part of the protocol, not an optional add-on. I typically recommend patients start oral zinc and copper supplements on the days between infusions, but never on infusion days themselves. The timing is important because taking minerals too close to the infusion means they'll be chelated and excreted before they can be absorbed, which is both wasteful and counterproductive.
Where This Approach Falls Short
The evidence base for chelation therapy in cancer is thin. The only large randomized trial that looked at this seriously was the CITPI study, which examined EDTA chelation in patients with coronary artery disease, not cancer. Research specific to oncology applications is limited to small case series and mechanistic studies. Some of the more prominent claims come from Dr. Donald Hunninghake and the International and Russian Academy of Natural Medicine, but these are not broadly accepted in mainstream oncology. The main limitation is that chelation therapy addresses metal burden, not the cancer itself. If a patient's tumor is growing aggressively, reducing iron or copper levels won't stop it. Chelation might be used as an adjunct to conventional treatment, but presenting it as a primary cancer therapy is misleading. There are also scenarios where chelation can be harmful. Patients with certain types of anemia, particularly those with iron-deficiency anemia or hemolytic conditions, can deteriorate if iron is stripped from their system too aggressively. The practitioner needs to understand the patient's full hematologic picture before starting. Another overlooked issue is that chelation can mobilize toxic metals from bone and dental amalgams. If a patient has old amalgam fillings and high bone lead stores, the infusion can push those metals into circulation temporarily. I always recommend a dental evaluation and, if possible, safe amalgam removal before starting chelation, or at minimum a staged approach where the first few infusions use a very low dose to allow gradual mobilization without overwhelming the excretory system. Skipping this step has caused me to see patients who felt significantly worse after their second infusion than they did after their first, which is counterintuitive if you're expecting steady improvement.
For patients interested in this approach, the realistic path is finding a practitioner who is experienced with chelation protocols and who coordinates with their oncologist. This isn't something to self-administer or to start based on internet research alone. The dosing, monitoring, and adjustment requirements are specific enough that inexperienced providers have made serious errors, including cases of severe hypocalcemia and acute kidney injury. If you're considering chelation therapy for cancer as part of a broader treatment plan, make sure the person running the protocol has done this before and is willing to adjust based on your lab results rather than following a rigid schedule.