Chelation Therapy and Erectile Function: What Actually Happens
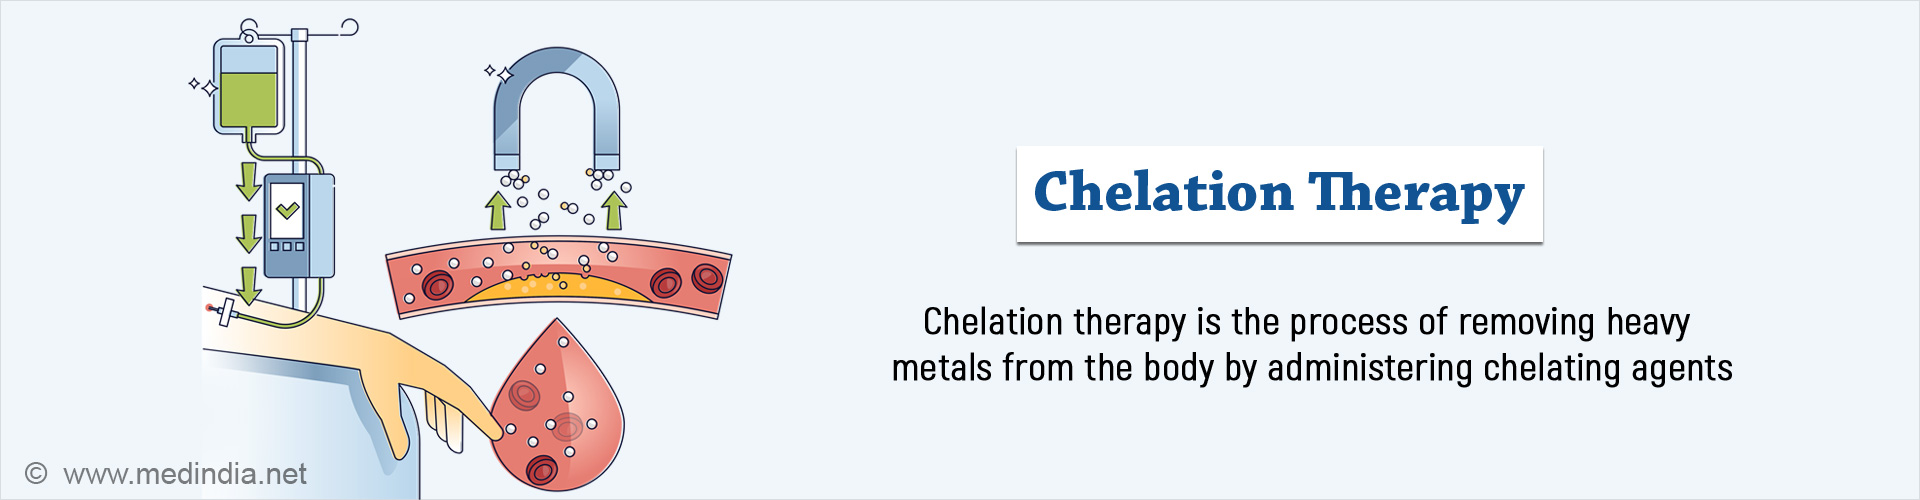
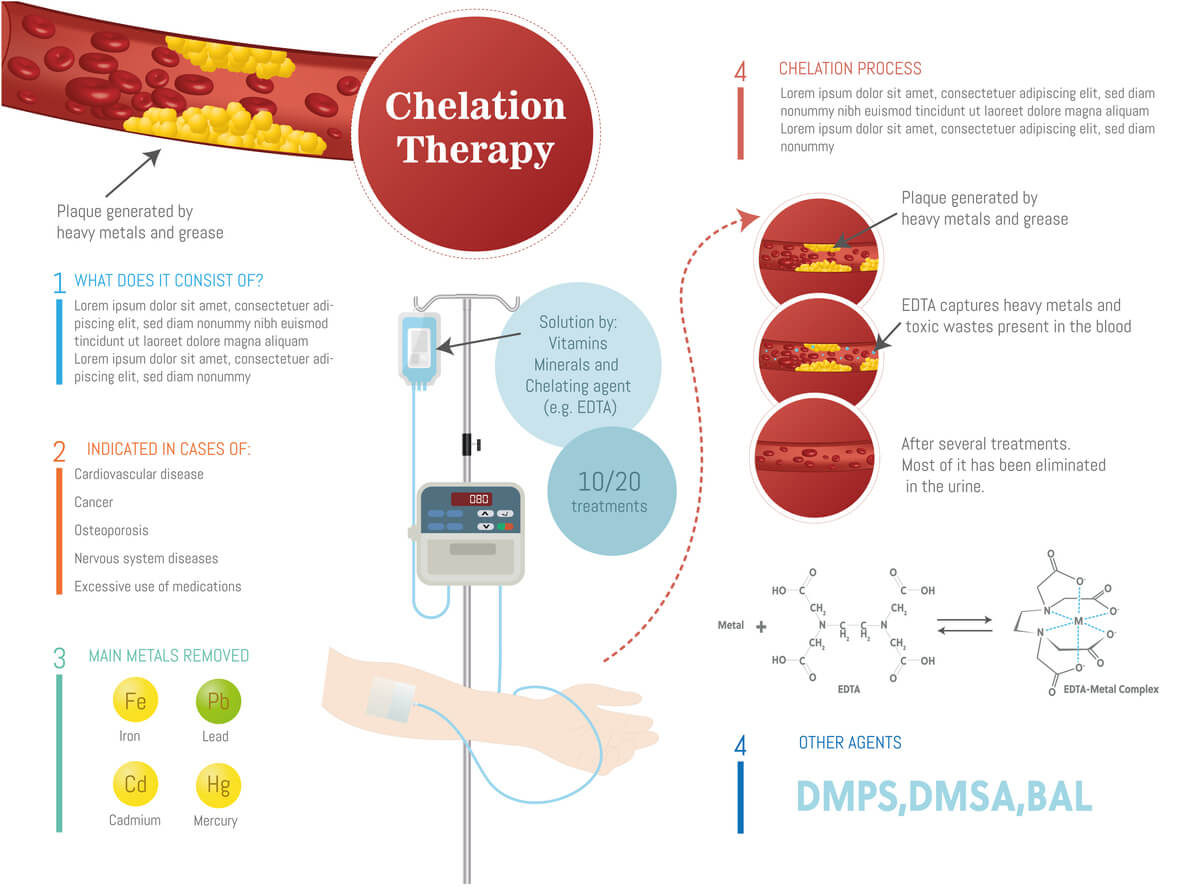
The idea of using chelation therapy for ED started circulating a few years ago, mostly from people trying alternative approaches after standard treatments didn't work for them. The premise is straightforward enough: heavy metals like lead and cadmium can damage blood vessels and nerves involved in erectile function, so removing them through chelation might improve blood flow and restore function. In practice, the evidence is thin and the application is messy. Standard chelation for ED typically involves EDTA (ethylene diamine tetra acetic acid) administered intravenously over a series of sessions. A typical protocol looks like 20 to 30 infusions, each lasting about two to three hours, spaced two to three times per week. The theory is that EDTA binds to heavy metals in the bloodstream and carries them out through urine. Some protocols add antioxidants like magnesium and B vitamins to the infusion mix to counteract oxidative stress, which is another factor in vascular damage related to ED. The key thing most sources skip is that this is not a quick fix. I've seen people commit to the full course and notice improvements somewhere around session twelve or fifteen, if at all. Blood flow changes are gradual because you're essentially trying to repair endothelial function over months, not days. If you have significant vascular damage from diabetes or long-term smoking, the results are usually much more modest than people expect going in.
I ran into one specific case that stuck with me. A guy in his late forties had been on tadalafil regularly with diminishing returns. His heavy metal panel showed elevated cadmium and borderline lead. After the first ten infusions he reported zero change, then suddenly around session fourteen his morning erections came back for the first time in two years. The problem was his insurance covered maybe six sessions, so he dropped off the protocol there and lost the momentum. The workaround I'd suggest if you're in that position is finding a clinic that offers package pricing or doing the blood work upfront to confirm elevation before committing resources. You do not want to go through half a course and then wonder why it did nothing.
The Nuances Most People Miss
First, chelation does not work for every type of ED. If your issue is primarily hormonal, psychological, or related to nerve damage from things like pelvic surgery, removing heavy metals won't move the needle. The therapy is specifically targeting a vascular-mechanism type of dysfunction. Getting a proper workup with testosterone levels, penile Doppler ultrasound, and a heavy metal panel before starting is non-negotiable. I've seen too many people skip straight to the infusion chair without confirming what they're actually treating. Second, the type of chelator matters more than most clinics admit. EDTA is the standard for vascular cases, but DMPS and DMSA are sometimes used for specific metal profiles. Using the wrong chelator for your particular metal burden can be ineffective or even redistribute metals to other tissues. A proper practitioner should be checking your urinary challenge test results between sessions to see what's actually coming out and adjusting accordingly. There's also a real risk here that nobody likes to talk about. Chelation removes essential minerals along with toxic ones. Zinc, magnesium, calcium, and iron can all drop significantly during a course. I always recommend supplementing strategically between sessions and rechecking mineral panels every five or six infusions. Without that, you can end up with new problems like muscle cramps, fatigue, or actually worse cardiovascular function from mineral depletion.
Get the Full Details
What the Evidence Actually Says
The PubMed records on this topic are sparse and low quality. There's no large randomized controlled trial specifically on chelation therapy for ED. The closest supporting data comes from studies on chelation and peripheral arterial disease, which show some improvement in vascular function, and from occupational health studies linking heavy metal exposure to erectile dysfunction. That's an inference chain, not direct evidence. If someone tells you chelation is a proven treatment for ED, they're overstating what exists. That said, for the subset of patients with confirmed heavy metal burden and vascular-mediated ED, the anecdotal reports are consistent enough that several integrative medicine clinics have adopted protocols. It's not fringe in those circles, but it's also not standard urology practice. Most urologists will tell you to exhaust PDE5 inhibitors, vacuum devices, injections, and implants before considering anything this experimental.
Practical Details If You Decide to Proceed
Find a licensed IV therapy clinic or integrative medicine physician. Make sure they're doing baseline and follow-up heavy metal testing, not just running infusions blindly. Cost runs roughly two hundred to five hundred dollars per session depending on your location and whether insurance covers any of it, which is rare for this application. Budget for at least fifteen sessions to give it a fair shot. Track your response using something simple like a weekly morning erection log and a standard IIEF questionnaire at session zero and then again at session fifteen and thirty. Combining chelation with lifestyle changes during the course makes a real difference. Exercise, especially cardio, improves endothelial function independently. Smoking cessation is probably the single most impactful thing you can do alongside the treatment. Alcohol reduction helps too since heavy drinking accelerates both heavy metal accumulation and vascular damage. One more thing worth noting: if your ED is related to an underlying condition like diabetes, hypertension, or low testosterone, treating that condition will give you more bang for your effort than chelation alone. This therapy addresses one piece of a larger puzzle. Don't let it become a substitute for standard medical care when standard care is exactly what you need.