Understanding Chelation Therapy for Parkinson's Disease
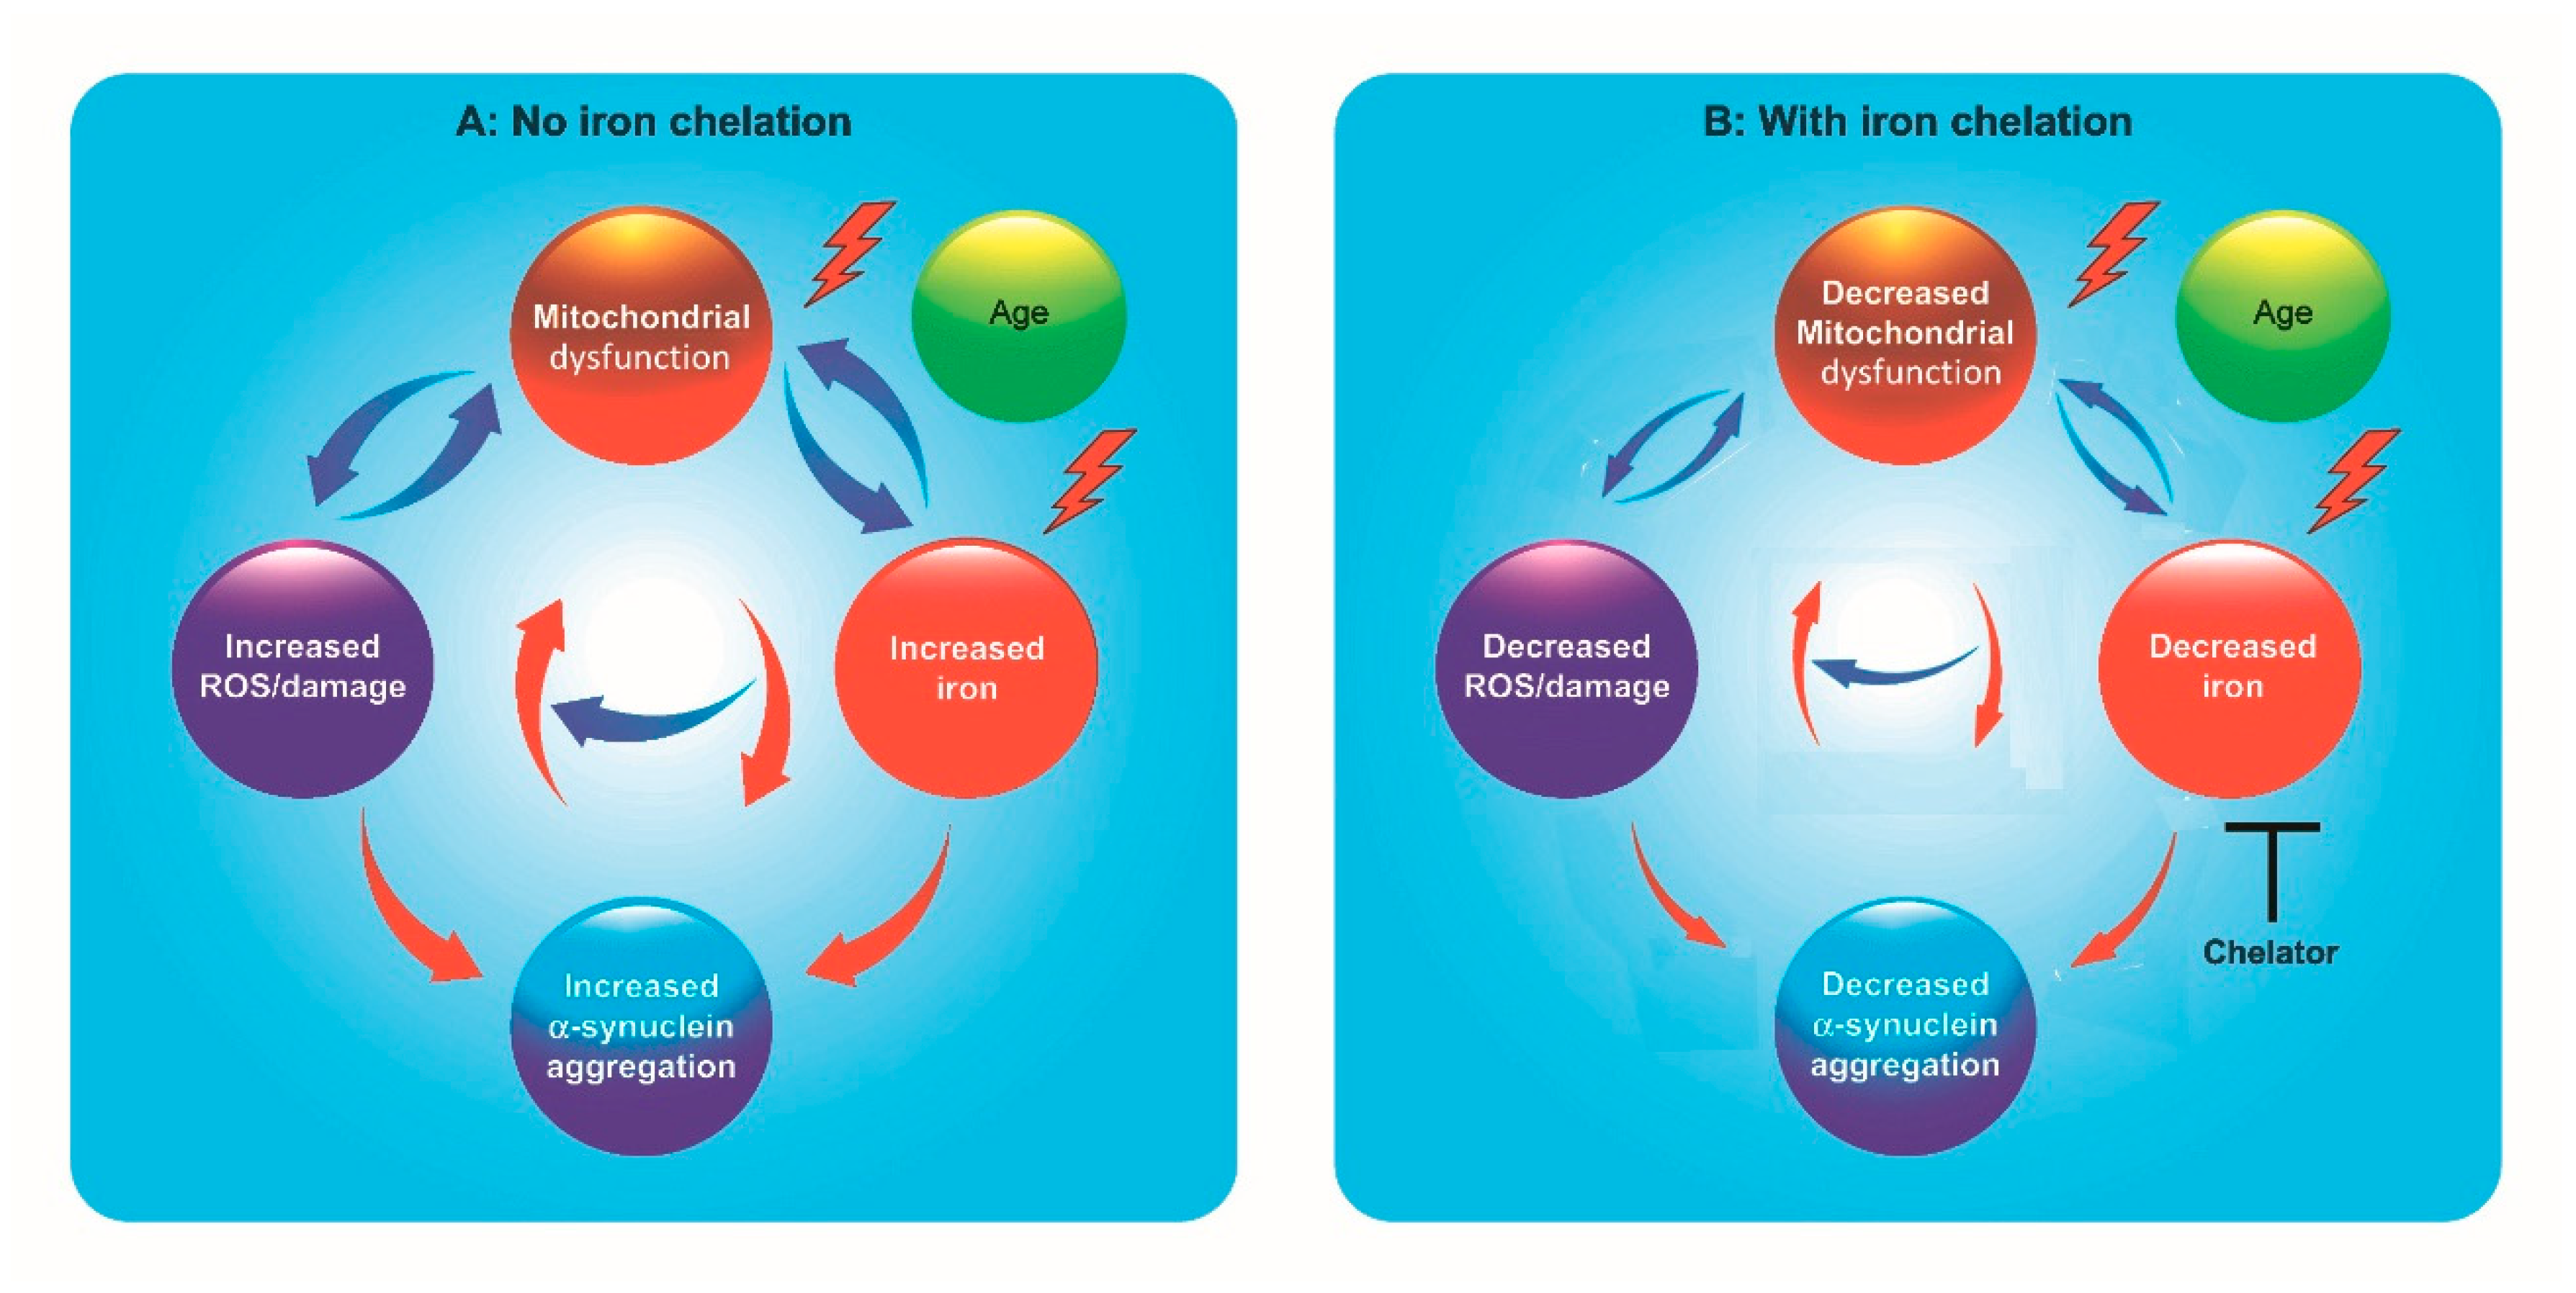
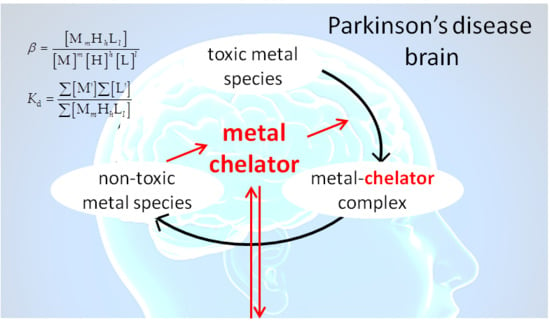
Chelation therapy for Parkinson's isn't one single treatment. It's a concept built around using metal-binding compounds to reduce abnormal metal accumulation in the brain, particularly iron and possibly copper or. The mainstream interest centers on iron because post-mortem studies consistently show elevated iron in the substantia nigra of Parkinson's patients, and iron catalyzes oxidative damage through Fenton chemistry. The logic is straightforward, even if the clinical results have been messy. The two main chelators you'll see discussed are deferiprone and deferoxamine. Deferiprone is an oral iron chelator originally developed for thalassemia patients who need regular blood transfusions. Deferoxamine is given intravenously or by subcutaneous infusion, usually overnight. Neither is FDA-approved for Parkinson's, but both have been investigated in clinical trials specifically for this purpose. A 2018 trial published in Movement Disorders looked at deferiprone in Parkinson's patients and reported that the chelator reduced brain iron levels visible on MRI and produced modest improvements in motor scores. The effect size was small, and the study was relatively short-term. A later multicenter trial had similar findings — measurable iron reduction, questionably meaningful clinical benefit. The research isn't conclusive, and it's not close to standard care.
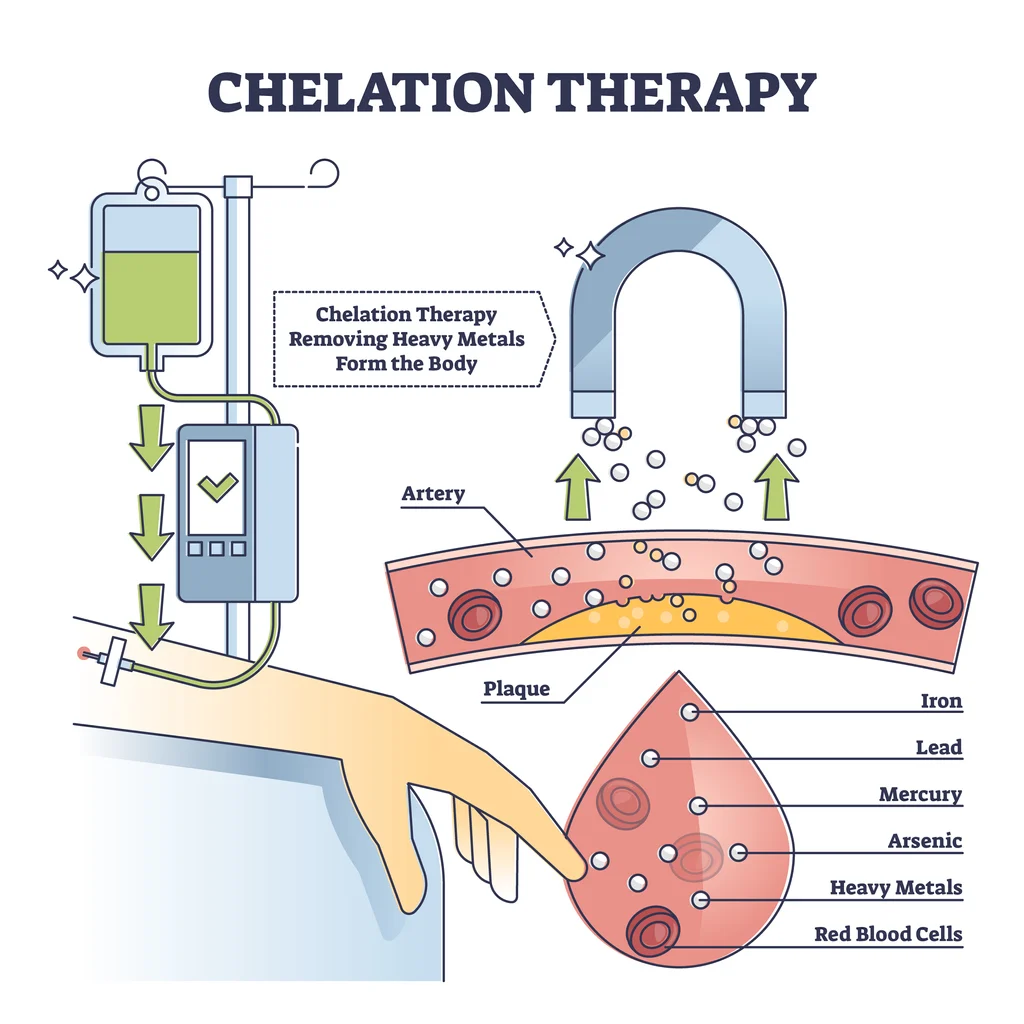
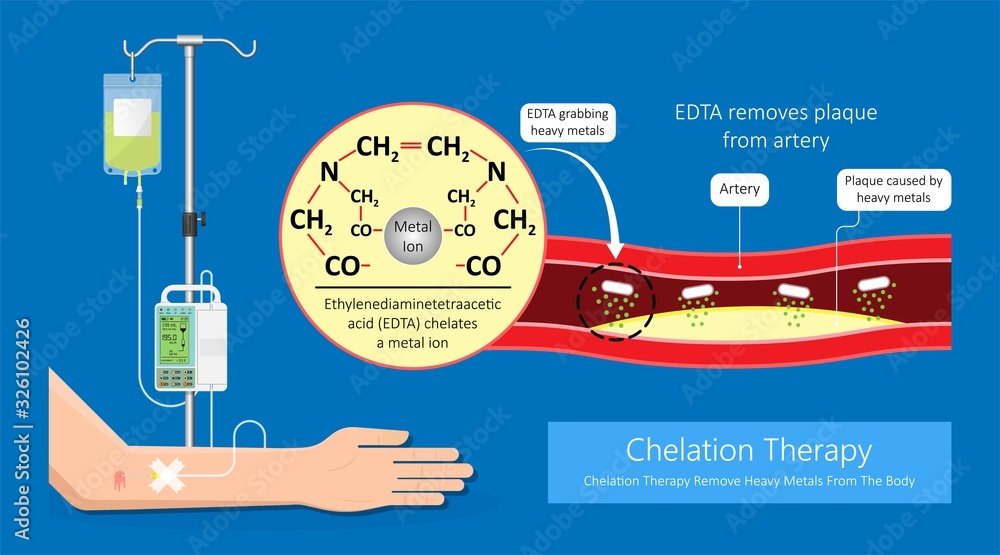
EDTA chelation, the kind people usually think of when they hear "chelation therapy," targets systemic heavy metals like lead and mercury. There is essentially no credible evidence it helps Parkinson's specifically. The mechanism doesn't align. EDTA doesn't cross the blood-brain barrier effectively, and the iron accumulation in Parkinson's is intracellular within dopaminergic neurons, not free circulating metal. People who push EDTA for Parkinson's are mixing two completely different conversations.
The Practical Side Nobody Talks About
If you're actually considering iron chelation for Parkinson's, the first thing you need to understand is that this is off-label and requires hematology-level monitoring. Deferiprone carries a risk of agranulocytosis — a dangerous drop in neutrophils. In the trials, patients needed weekly blood counts. I worked with a movement disorder neurologist who managed a patient on deferiprone and had to stop the drug cold after the patient's ANC dropped to under 500. That's an emergency situation. She had him on prophylactic antibiotics for two weeks until his counts recovered. This isn't something you manage with a prescription and a quarterly lab draw. Deferoxamine requires a portable infusion pump worn for eight to twelve hours overnight, every day. The logistics are rough. GI side effects are common with both agents. And here's the counter-intuitive part that most patients don't anticipate: chelating iron doesn't just affect the brain. Systemic iron depletion triggers increased hepcidin and reduces available iron for other processes, including red blood cell production. Several trial participants became anemic enough to need iron supplementation, which basically fights against the treatment. You're simultaneously depleting and replacing iron, which makes the whole approach harder to interpret and manage. Another issue most people miss is that MRI-visible brain iron isn't the same as the pathological iron species driving neurodegeneration. The ferrihydrite and hemosiderin deposits seen on susceptibility-weighted imaging may represent downstream damage rather than the primary driver. Chelating that iron might slow further accumulation without reversing existing damage. That distinction matters because it sets realistic expectations for what this therapy can and cannot do.
Get the Full Details

What the Evidence Actually Supports
Iron chelation in Parkinson's sits somewhere between "promising mechanistic rationale" and "unproven clinical intervention." The trials show biological activity — brain iron does decrease. Whether that translates into disease modification is the open question, and we don't have a definitive answer yet. The most rigorous data to date suggests possible modest symptomatic benefit at best, with no demonstrated halting of progression. For someone considering this route, the practical path is through a movement disorder specialist at an academic medical center. They can determine whether you're a candidate based on your iron burden on MRI, your blood counts, and your overall clinical picture. Self-sourcing deferiprone online is a real risk — the compound is available from some international pharmacies without a US prescription, and the quality control is unpredictable. I've seen forum posts from people who ordered it themselves and got variable results, partly because the compound degrades differently depending on storage conditions and manufacturing batches. The bottom line is that this therapy exists, it has a plausible mechanism, and it has shown signals in clinical trials, but it is not an established treatment for Parkinson's disease. It's also not a backup plan to replace dopaminergic medications. Anyone considering it should treat it as experimental and go in with full knowledge of the monitoring requirements and the side effect profile. The people who do best with this approach are the ones who go in with realistic expectations and a monitoring plan that's already in place.