What You Actually Need From Chemistry in Nursing School
Most nursing students hit a wall around the second semester of general chemistry and decide they just hate science. That isn't true. You don't need to love chemistry. You need to understand the parts that show up repeatedly on the job and on the licensing exam, and then stop worrying about the rest. The gap between what your professor thinks is important and what you'll actually use in clinical practice is enormous, which is why so many students feel like the whole class was a waste until they reach pharmacology. The first thing I learned the hard way was that molarity calculations are the single most tested concept, and they're also the single most likely to cause a medication error if you don't have them automatic. I've watched a student spend forty-five minutes relearning dimensional analysis because the professor never actually taught it in the context of IV drip rates. You don't need organic synthesis mechanisms. You need to convert grams to moles, moles to liters, and then back again without pulling out a notebook every time.Chemistry For Nursing Students
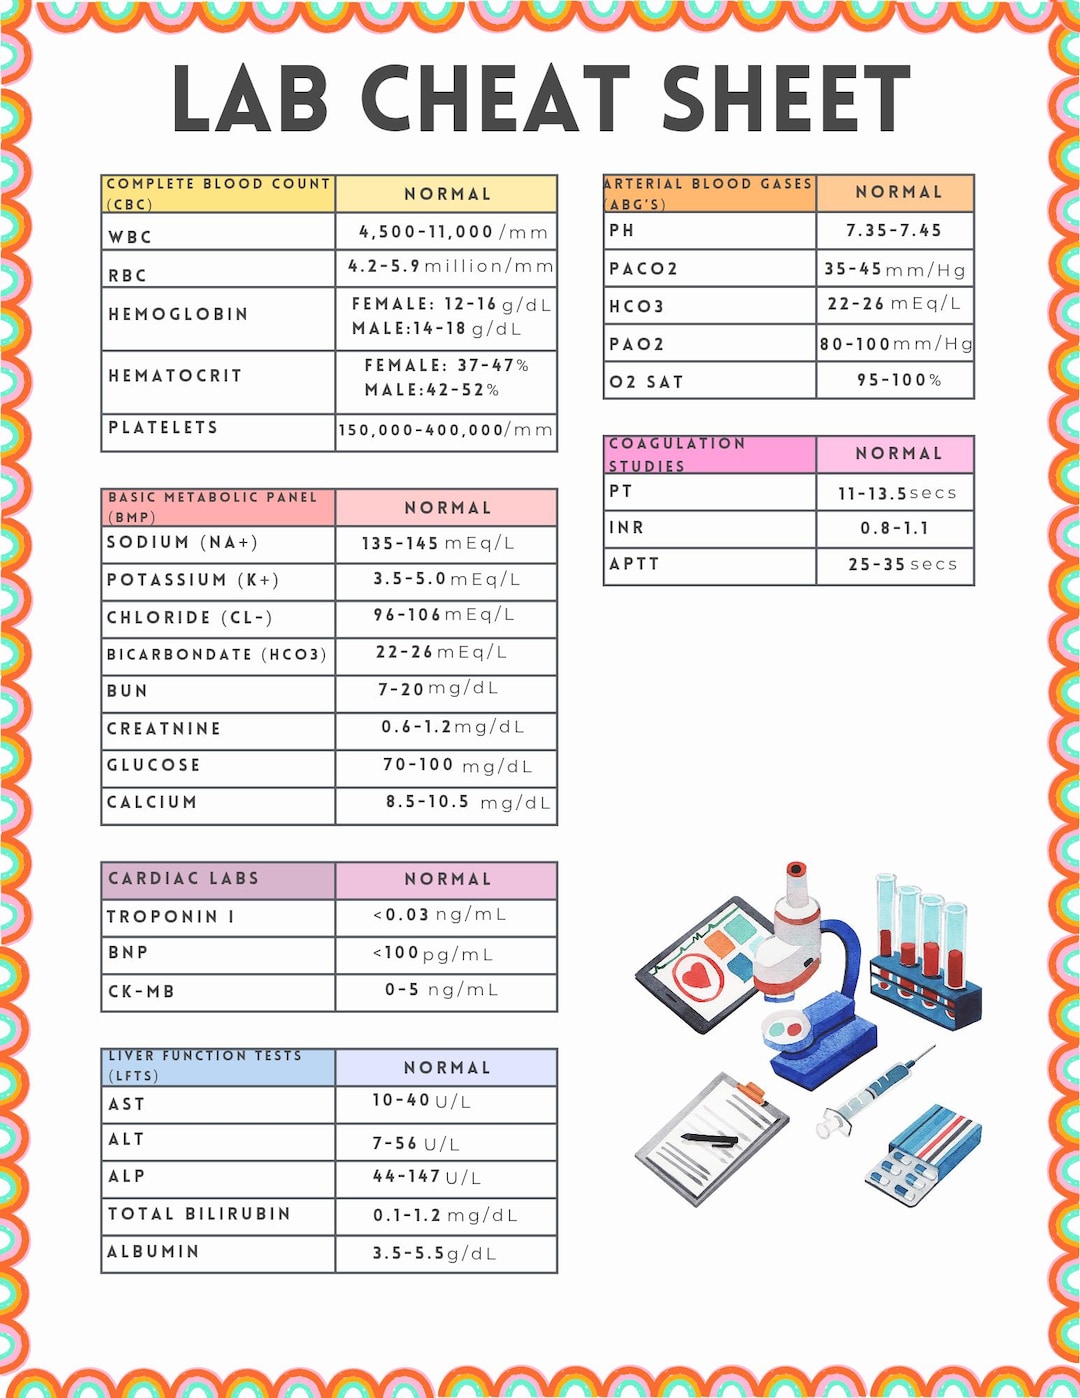
The curriculum is built around solutions, acids and bases, and stoichiometry. Those three areas account for roughly ninety percent of the chemistry-adjacent problems you'll encounter in nursing. Everything else — gas laws, thermodynamics, nuclear chemistry — is there to satisfy a general education requirement. It will not appear on NCLEX. It will not appear on your floor. I worked as a clinical instructor for several years and I can tell you exactly what breaks when students don't understand pH well enough. A patient comes in with severe metabolic alkalosis from vomiting, and their arterial blood gas shows a pH of 7.58. The new grad stares at the number and panics because they remember the pH scale from lecture but they've never actually had to think about what happens when hydrogen ion concentration drops below 40 nanomoles per liter. They call the attending. The attending asks a simple follow-up question about chloride replacement and the student freezes. This is the exact moment where chemistry stops being abstract and starts being dangerous. The fix is to practice pH problems with actual clinical numbers rather than clean textbook values. Real patients don't have pH of exactly 7.40. They have 7.31, 7.49, 7.56. Get comfortable with the mess.
Dimensional Analysis Is Non-Negotiable
Stop trying to memorize formulas. Formula memorization fails the moment a problem varies even slightly from the template you studied. Dimensional analysis — the factor-label method — works regardless of how the question is phrased because it's based on unit cancellation rather than pattern matching. Write out every conversion factor you need, arrange them so the unwanted units cancel, and multiply across the top and divide by the bottom. It takes longer on the first attempt but it becomes faster than any shortcut within two weeks of consistent practice. Here's a concrete example that comes up constantly: calculating a heparin drip. The order reads 1,200 units per hour. The IV bag contains 25,000 units in 500 mL of normal saline. You need the flow rate in milliliters per hour. Set it up as 1,200 units divided by 1 hour, multiplied by 500 mL divided by 25,000 units. The units cancel cleanly. You get 24 mL per hour. That's it. Do this type of problem thirty times and you won't second-guess it during a code. Another area that trips people up is converting between mass and volume for liquid medications. If a order says 0.5 grams of a drug and the supply comes as 250 mg per 5 mL, you need to convert grams to milligrams first — that's a factor of 1,000 — and then set up the ratio. Students who skip the gram-to-milligram step consistently get answers that are off by a factor of a thousand. That isn't a minor error. That's a lethal dose.
Buffer Systems and Blood Gases
The bicarbonate buffer system is the only acid-base topic that matters clinically, and even then you only need a functional understanding rather than a full derivation of the Henderson-Hasselbalch equation. The equation itself is: pH = 6.1 + log(HCO3- / (0.03 × PCO2)) You don't need to derive it. You need to know that when PCO2 goes up, pH goes down, and when bicarbonate goes down, pH goes down. That relationship alone lets you interpret nearly every ABG you'll see on the floor. Respiratory acidosis means the problem is in the CO2. Metabolic acidosis means the problem is in the HCO3-. The compensatory mechanisms follow logically from there. I once had a student correctly identify a mixed disorder — respiratory acidosis with concurrent metabolic acidosis — simply by checking whether the compensation matched the expected range, which came from practicing these calculations rather than memorizing definitions.
Get the Full Details

Isotonic Solutions and Osmolarity
This is another area where the textbook explanation and clinical reality diverge. Normal saline is labeled 0.9% NaCl, which means 0.9 grams per 100 mL. That works out to roughly 154 mEq/L of sodium and 154 mEq/L of chloride. The total osmolarity is about 308 mOsm/L, which is close enough to plasma that we call it isotonic. D5W is technically isotonic in the bag but becomes hypotonic once the glucose is metabolized. That distinction matters when you're choosing fluids for a dehydrated patient with altered mental status. Picking D5W because it's labeled isotonic is a mistake I've seen cause real harm. I worked with a nurse who administered a rapid infusion of D5W to a patient with cerebral edema and didn't understand why the patient's sodium dropped. The chemistry was simple — free water crossed into brain cells — but the conceptual gap was in osmolarity, not in math. If you understand osmolarity as a force rather than as a number to plug into a formula, you'll make better fluid choices.
What to Study and What to Skip
For a nursing student, here's the practical breakdown. Master these topics thoroughly: molarity and dilution calculations, dimensional analysis for medication dosing, pH and the pH scale, the bicarbonate buffer system, isotonic hypertonic and hypotonic solutions, and basic stoichiometry as it applies to solution concentrations. These are the things that recur in pharmacology, med-surg, and critical care. You can safely skim: organic reaction mechanisms, thermochemistry, gas laws beyond the ideal gas equation, nuclear chemistry, and spectroscopy. Your professor may assign readings on these and give you problems to solve. That doesn't mean you need to master them. Do the homework to get the grade, but don't spend extra study time on concepts that won't reappear.
A Specific Problem I Encountered
During my time as an instructor, I had a student who could solve every equilibrium problem correctly but couldn't calculate a proper IV flow rate under time pressure. The disconnect was that her chemistry class taught equilibrium in a vacuum — closed systems, clean numbers, no urgency — while her skills lab required her to perform the same arithmetic with a stopwatch running and a mannequin involved. She'd freeze and second-guess unit cancellations she'd done perfectly on paper. The workaround was straightforward. I had her practice IV calculations using actual clinical scenarios with messy numbers — 1.5 mg/kg/min instead of clean round doses, weight in pounds that needed conversion, concentration given in unusual ratios. She did five problems per day for two weeks, timing herself on each one. By the third week, her speed had improved dramatically and the anxiety dropped because her brain had built a reliable procedural pattern rather than relying on last-minute derivation. This isn't a theoretical suggestion. I tracked her performance and her error rate went from roughly one mistake per five problems to zero over that period.

Common Pitfalls to Avoid
The most frequent mistake is confusing mass percent with molarity. A 5% dextrose solution doesn't mean 5 moles per liter. It means 5 grams per 100 mL. Students who conflate these two concepts make systematic errors in every calculation that follows. The second mistake is ignoring significant figures until the final answer. In nursing, significant figures matter less than accuracy, but rounding too early in a multi-step calculation can push your result outside a safe dosing range. Keep extra digits through the intermediate steps and round only at the end. A third pitfall is treating normal ranges as fixed boundaries. A potassium level of 5.1 isn't automatically hyperkalemic in every context. A patient on dialysis may have a baseline that runs higher. Chemistry gives you the reference ranges, but clinical judgment determines whether a number is actually abnormal for that specific patient. Don't let a textbook range override what you know about the person in the bed.
Resources That Actually Help
The Khan Academy chemistry course covers the foundational material efficiently if you need a refresher. For nursing-specific applications, the Davis's Drug Guide and the Nursing Drug Reference include concentration information that reinforces the chemistry concepts you're studying. The NCLEX review books by Saunders or Kaplan have dedicated sections on calculation practice that align with what you'll see on the exam. Online calculators exist for IV drip rates and molarity conversions, but using them during study habits creates a dependency that breaks during tests where calculators aren't allowed. Practice without one until the arithmetic feels automatic. If you want a structured problem set, the American Association of Colleges of Nursing publishes calculation worksheets that mirror the style of nursing program assessments. They aren't perfect but they're closer to actual exam questions than most textbook end-of-chapter problems, which tend to be artificially clean. The messier the practice problems, the better prepared you'll be.
Bottom Line
Chemistry for nursing students isn't about becoming a chemist. It's about building enough quantitative fluency to handle medication calculations safely and to understand the physiological processes that depend on acid-base balance and osmolarity. Focus your energy on the areas that matter clinically, practice until the math is reflexive, and don't waste time on topics that won't reappear in your career. The students who succeed aren't the ones who memorize every equation. They're the ones who understand what the numbers mean when they're looking at a patient.