Recognizing and Managing Persistent Air Leaks After Chest Tube Insertion
An air leak after chest tube placement is one of those things that sounds straightforward until you're standing over the patient watching the water seal chamber bubble every time they breathe and you realize it's been happening for six days straight. You learned the basics in training. A chest tube goes in, air or fluid comes out, the lung re-expands, the bubbling stops, you clamp and remove. In practice it's more complicated than that. At its simplest, a chest tube air leak means air is moving from the pleural space or airways into the drainage system continuously or with respiration. You see it as bubbling in the water seal chamber. The leak can be intermittent, occurring only with coughing or forced exhalation, or it can be continuous throughout the respiratory cycle. That distinction matters because it changes what's causing the problem and how urgently you need to act. I had a patient once who had a persistent air leak for eleven days after a VATS bleb resection. The operative report said everything looked fine. The lung was fully expanded on X-ray. But the water seal was bubbling steadily. We went through the standard checklist twice. No kinks in the tubing. No obvious disconnections. Suction was at negative 20 centimeters of water. The leak just wouldn't stop. Eventually we did a bronchoscopy and found a small bronchopleural fistula at the resection margin that the surgeon had missed. It sealed on its own after we placed the patient on prolonged low-level suction and kept them NPO for a few days. Took about three more weeks total but we avoided another surgery.
The Practical Approach to Evaluating a Persistent Leak
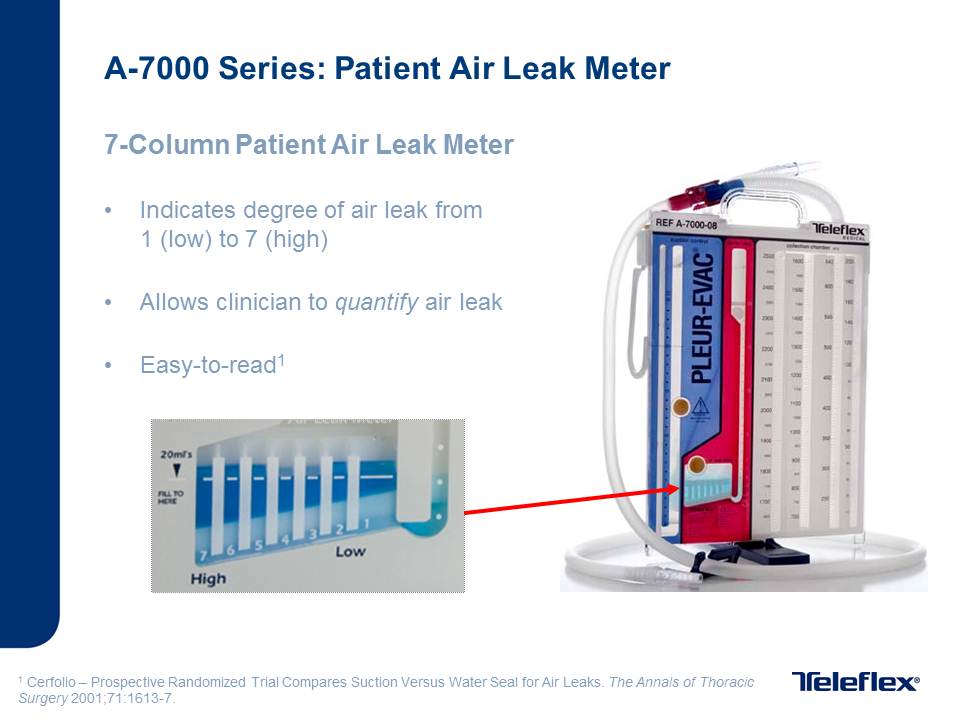
Start by confirming the leak is real and not an artifact. Check the connections. Make sure the tubing isn't cracked or loose at the Y-connector. Turn up the room lights. Look at the chest tube insertion site for subcutaneous emphysema, which suggests air is tracking along the tube tract rather than through the pleural space. Palpate the neck and chest wall. If you feel crepitus, that changes your thinking about where the air is going. Then check the patient. Are they oxygenating adequately? Is the lung expanded on imaging? These two questions determine whether you're dealing with a manageable leak or something that needs intervention. A patient who is stable with a good lung expansion and a small air leak can often be watched. A patient with persistent pneumothorax despite a functioning chest tube needs a different plan. One thing beginners miss is that the amount of bubbling doesn't always correlate with the size of the leak. I've seen trivial leaks that bubble like a jacuzzi when the patient coughs and barely whisper-bubble at rest. The flowmeter on some drainage systems can give you a quantitative measure in millilititers per minute, but most units in regular use don't have that. Don't rely on visual estimation alone. Document the pattern. Note whether it's continuous or only with certain maneuvers. This information is what the pulmonologist or thoracic surgeon needs when you call them at 2 AM.
Management Strategies Based on Leak Duration and Severity
For a standard post-operative leak, the expectation is that it resolves within four to seven days. The first week is conservative management. Maintain suction at negative 10 to 20 centimeters of water. Keep the patient upright. Encourage pulmonary hygiene. If the lung stays expanded and the leak is decreasing, you wait. Most of these resolve without escalation. When the leak persists beyond the first week, you're in the persistent air leak category. At this point the considerations shift. The patient needs to be evaluated for bronchopleural fistula, incomplete lung expansion due to trapped lung, or underlying parenchymal disease that won't heal on its own. A high-resolution CT scan with the chest tube in place can show whether there's a visible fistula or if the lung is simply not reaching the chest wall. Trapped lung is a common cause that people forget about. The lung is encased in fibrous pleural tissue and can't expand to seal the leak. No amount of suction will fix that one. For leaks that are persistent but the lung is fully expanded, endobronchial valves are an option. They're placed bronchoscopically and allow air to escape during exhalation but prevent entry during inhalation. The success rate is roughly seventy percent for appropriate candidates. Not every hospital has the capability. Blood patch via the chest tube is another approach that some centers use, though the evidence base is thin. Autologous blood injected into the pleural space can form a clot over the fistula in select cases. It's not a reliable standalone treatment but it's worth considering before jumping to surgery.
Get the Full Details

If conservative measures fail and the patient is a surgical candidate, re-operation to revise the resection site or perform a pleurodesis is the next step. I've seen surgeons hesitant to go back in too early because they figure the leak might still close. That's reasonable up to about ten to fourteen days. Beyond that, the fistula tract starts to epithelialize and spontaneous closure becomes less likely. At that point waiting longer usually just means a longer hospital stay and more complications from the indwelling tube.
Common Pitfalls That Prolong Air Leaks Unnecessarily
The first pitfall is excessive suction. Some teams crank suction up to negative 30 or even 40 centimeters of water thinking it will help the lung adhere faster. It often does the opposite. High suction can keep a small fistula open by pulling air through it with each breath. Negative 20 is plenty for most situations. If you're not getting improvement at that level, increasing suction won't help. The second pitfall is premature clamping. You see a decrease in bubbling and think the leak has sealed. You clamp the tube to test it. The patient develops a tension pneumothorax within hours. Never clamp a chest tube with a known air leak unless you're doing it for an intentional short trial under direct observation with imaging available. And even then, keep the clamp at the bedside, not in the hall closet. A third pitfall is assuming the drainage system itself is the problem when it's actually the patient. I once spent two hours troubleshooting a drainage system that was bubbling constantly, only to realize the patient had a severe cough variant asthma exacerbation driving massive airway pressures. The leak would have resolved if we'd treated the underlying bronchospasm instead of replacing tubing and checking connections. Sometimes the answer is nebulizers and steroids, not a new chest tube.
There's also the issue of tube position. A tube that has migrated or is malpositioned against the mediastinum rather than in the apical collection space won't effectively drain air even if it's patent. A simple CT or at least a well-positioned X-ray can clarify this. Repositioning the tube or placing a second one is sometimes necessary. It's not a failure of management, it's a recognition that the first tube isn't doing its job.

When to Escalate and When to Wait
Escalation is warranted when the air leak is causing tension physiology, when the lung remains collapsed despite adequate suction, when there's evidence of infection around the tube site, or when the leak has persisted beyond two weeks without signs of improvement in a surgical candidate. In those cases, involve thoracic surgery early. Don't wait until the patient has been on a chest tube for three weeks and then scramble to find someone to take over. Waiting is appropriate when the patient is clinically stable, the lung is well-expanded, the leak is gradually decreasing, and there's no sign of complications. Document the trend. Measure the leak if your system allows it. Repeat imaging at reasonable intervals. Most persistent leaks that will resolve do so within the first two weeks. The patients who don't improve by then are the ones who need a definitive intervention. The thing about chest tube air leak management that no one tells you in residency is that a lot of it is pattern recognition and patience. You learn to read the bubbling, the imaging, the clinical trajectory. The formulas and algorithms cover the edge cases poorly. The edge cases are where the actual work happens.


