Connecting a Chest Tube to Wall Suction
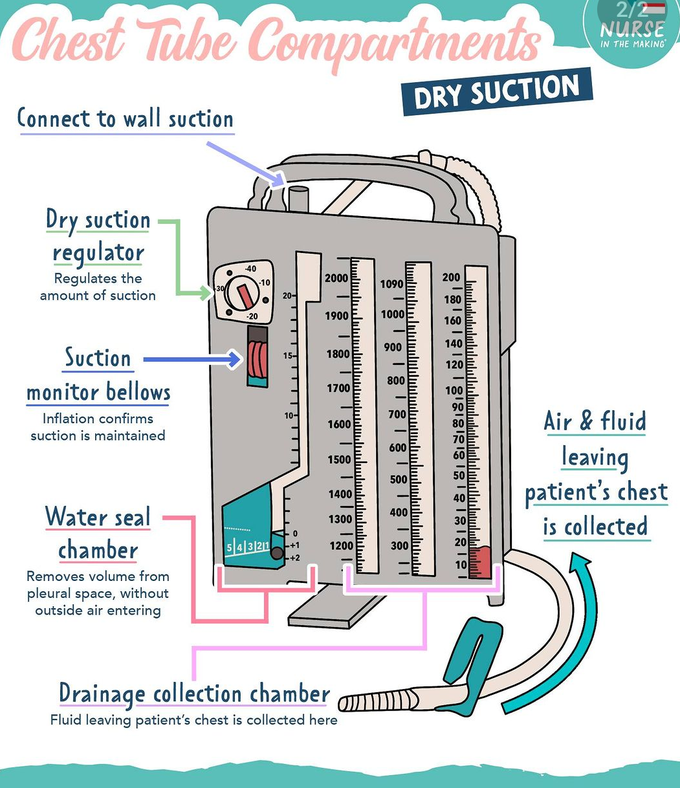
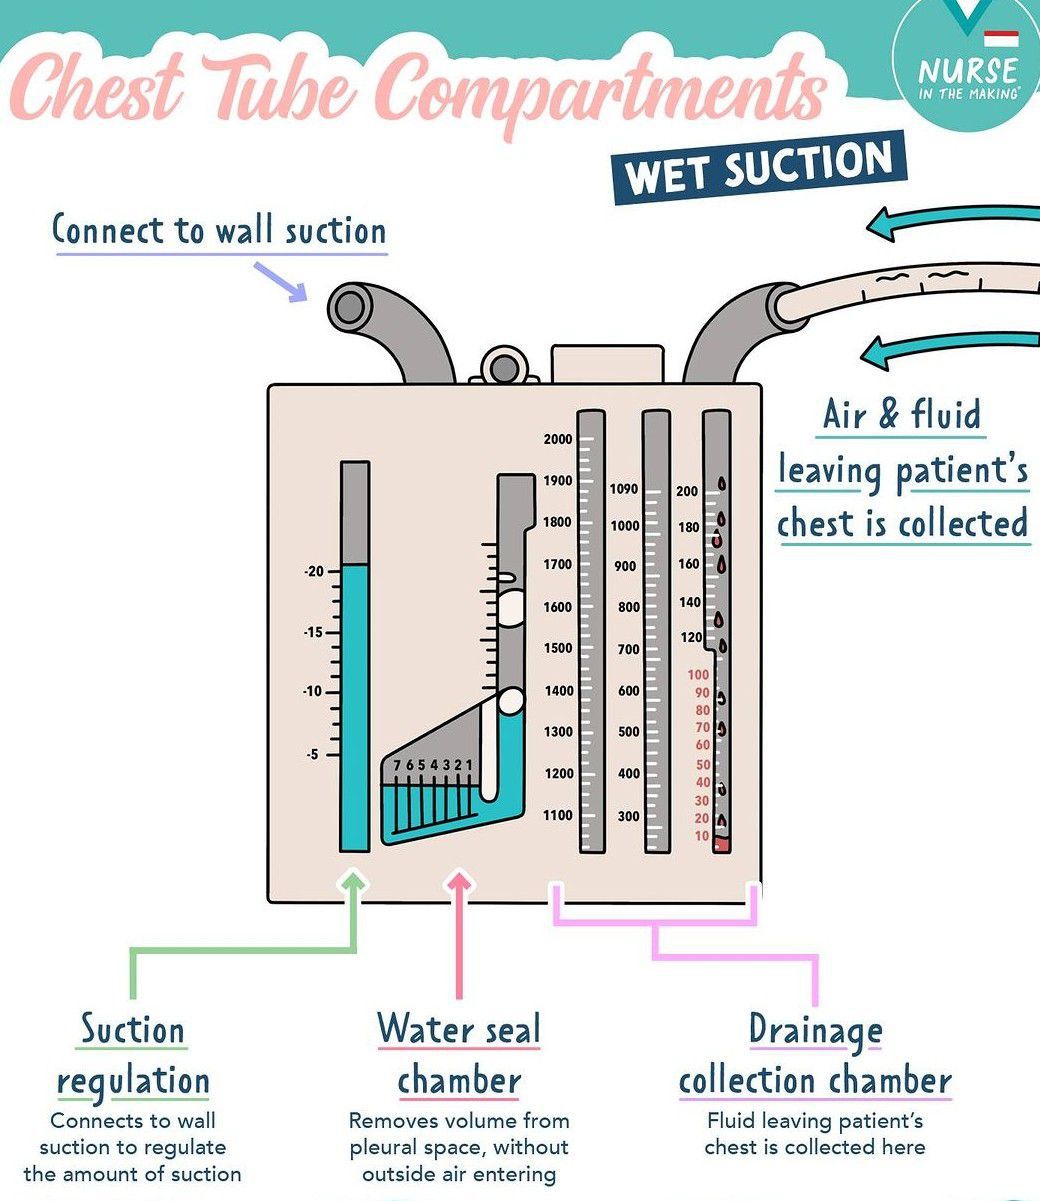
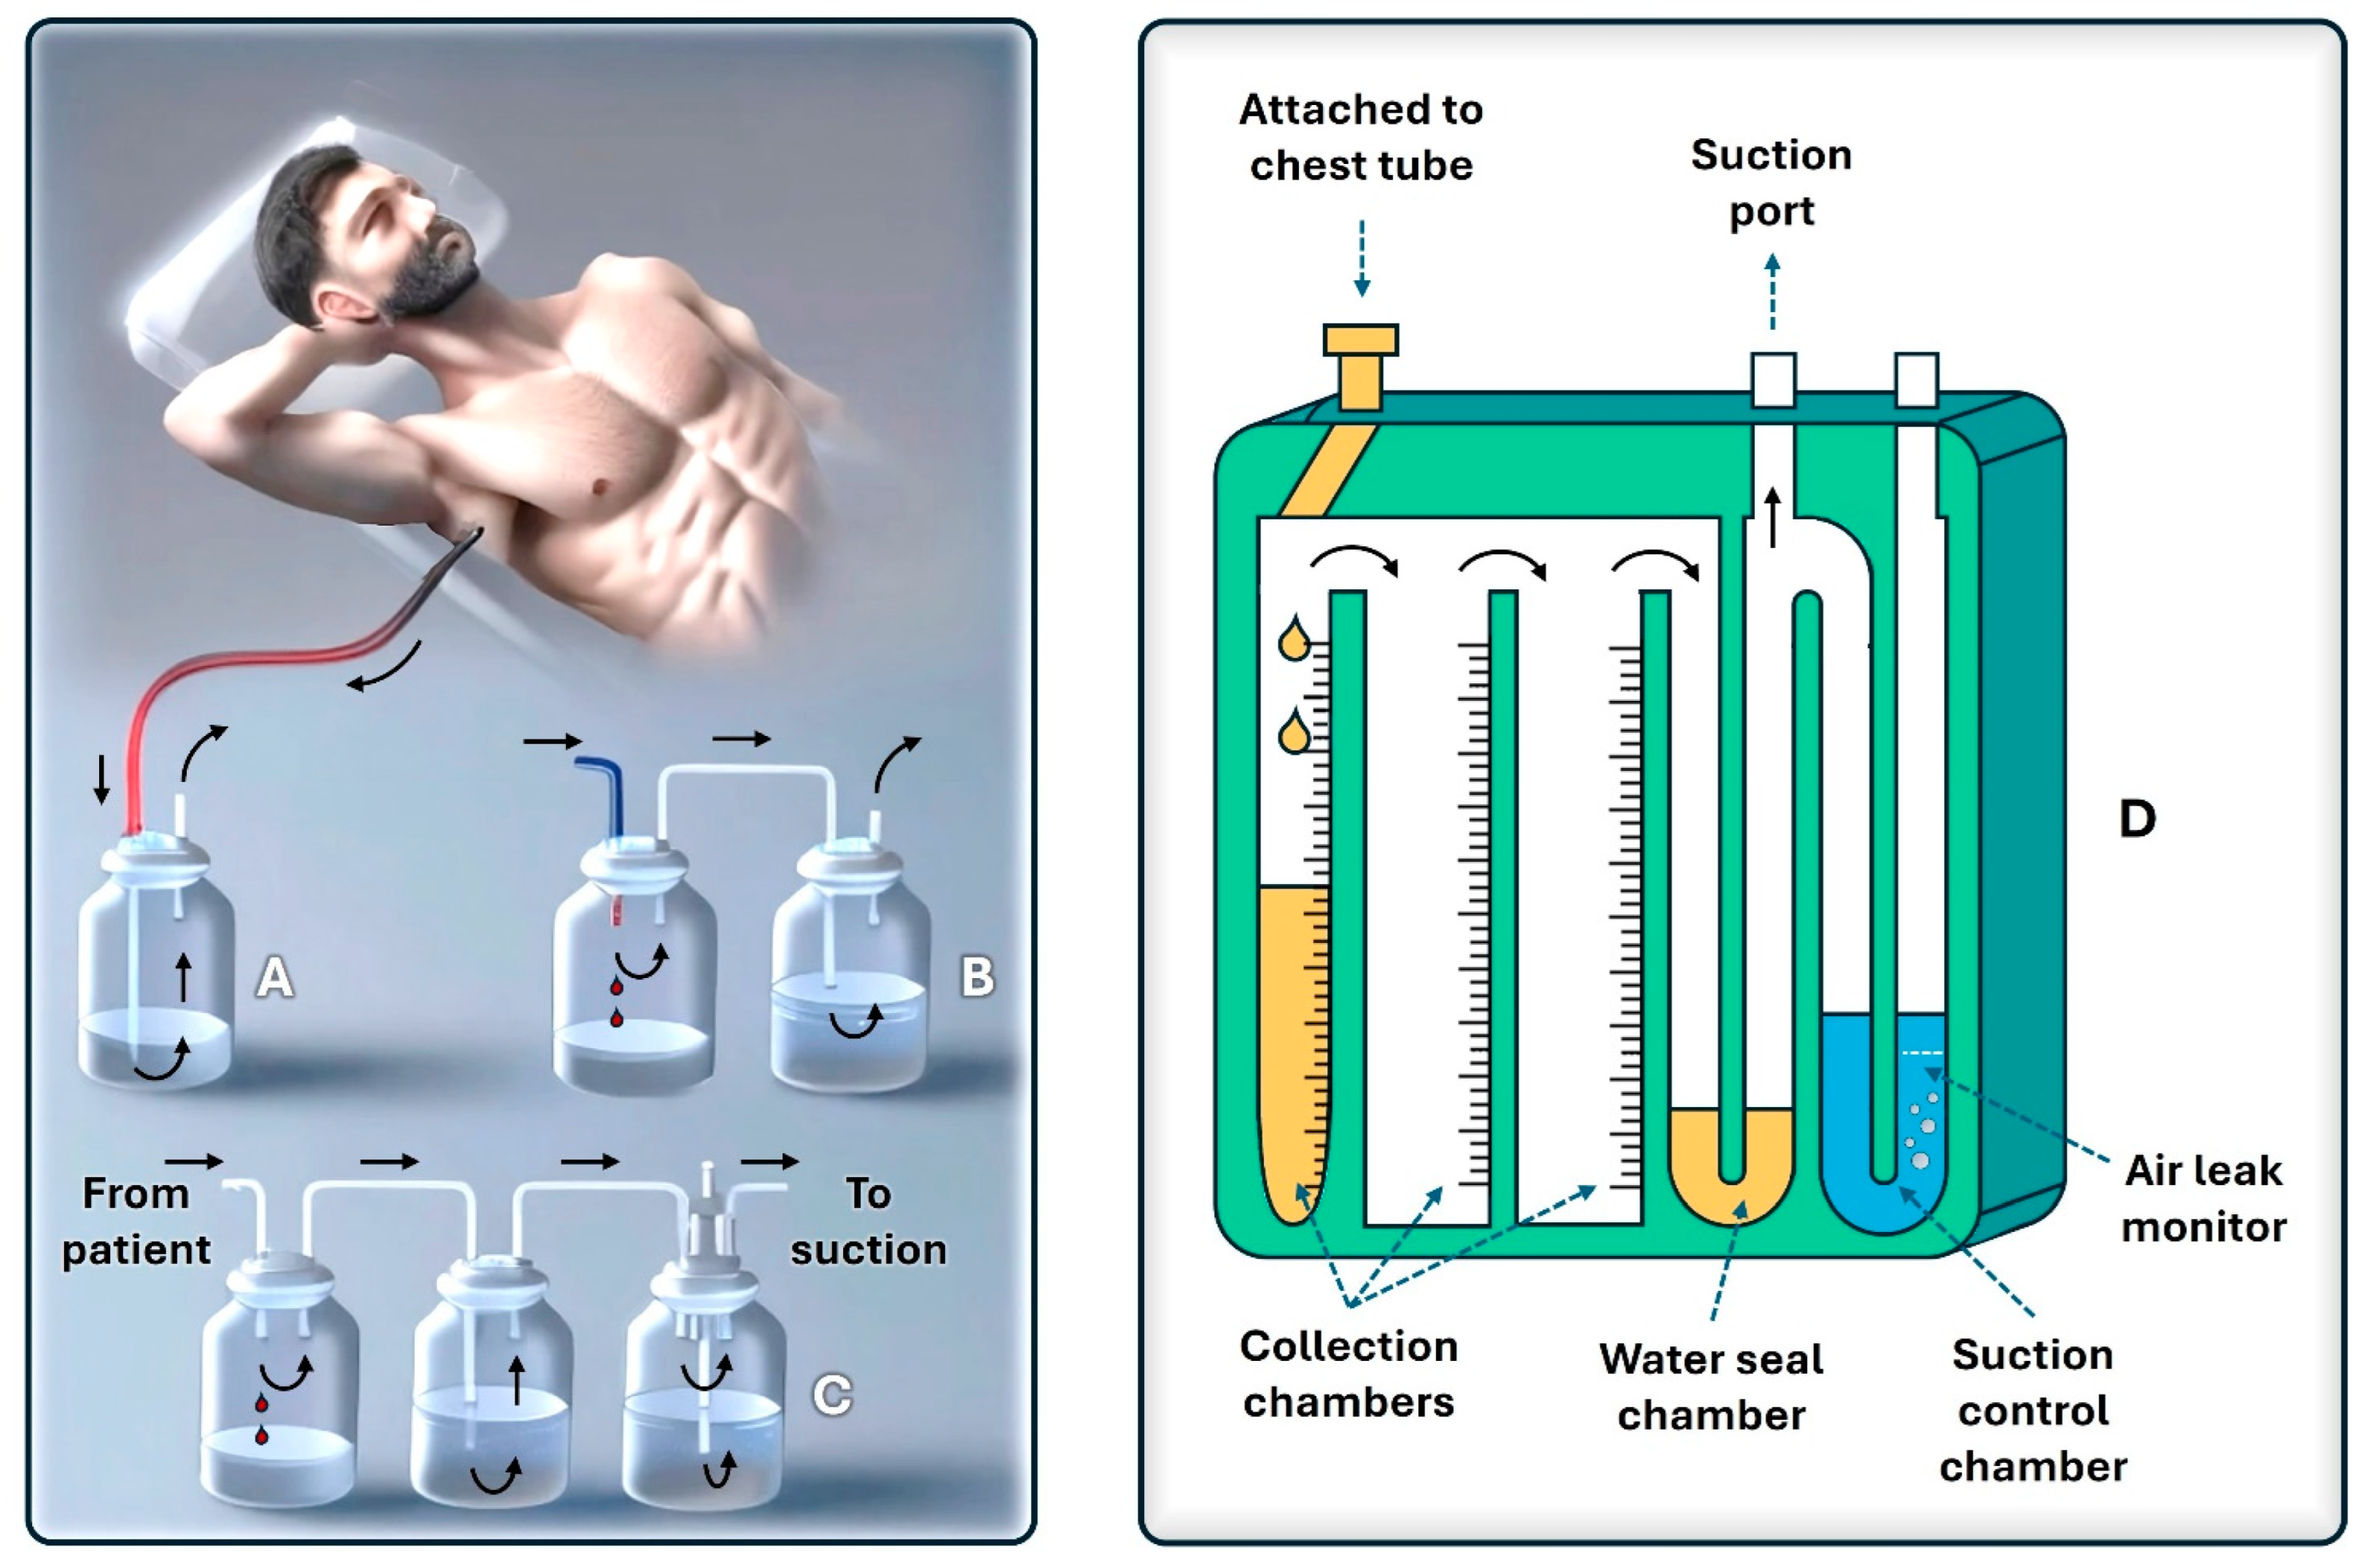
When a patient gets a chest tube placed for pneumothorax, hemothorax, or post-op drainage, the next step is often attaching it to suction. This is not a complicated procedure if you understand the system, but there are enough failure points that people mess it up regularly. I have seen nurses and residents struggle with this more than I care to admit. A chest tube drainage system typically has three chambers: the collection chamber for fluid, the water seal chamber that acts as a one-way valve, and the suction control chamber. The water seal chamber is the most critical part. You should see gentle bubbling in there during exhalation if the lung is still not fully expanded, or no bubbling if the air leak has resolved. Everything downstream of that goes to suction.
Proper Chest Tube To Suction Technique
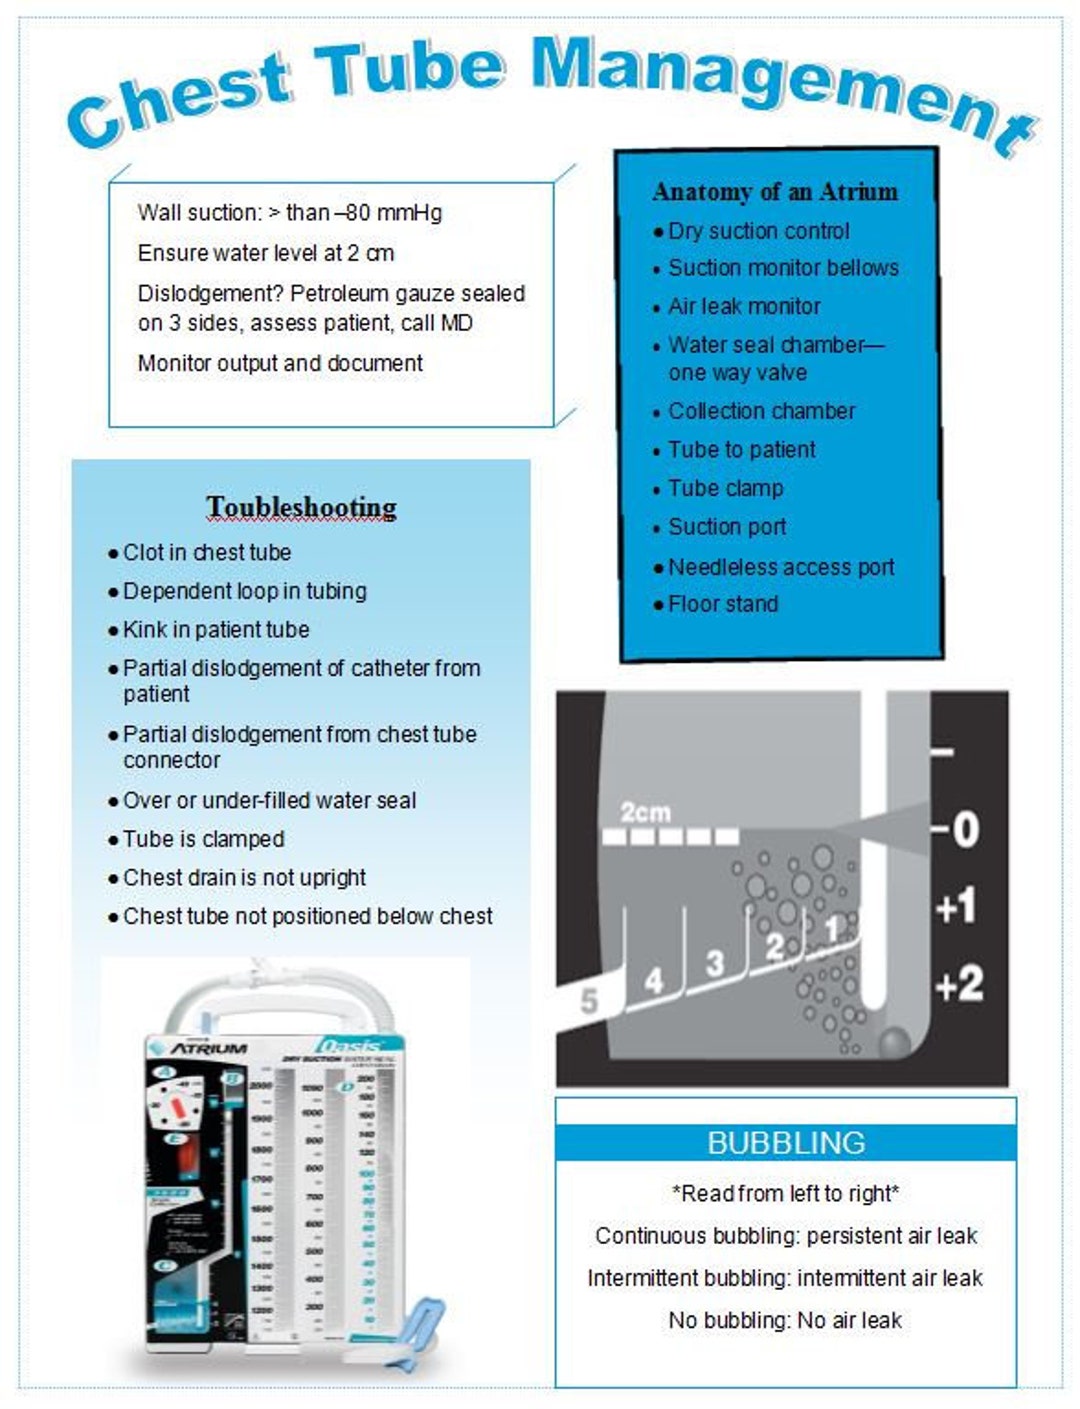
Here is how I actually do it at the bedside. First, verify the order and confirm the physician's target suction setting. Most adult chest tubes run at 20 cmH2O, sometimes 40 depending on the indication. Pediatric and adolescent settings are lower. Check the water seal chamber first to make sure it has the correct fluid level marked on the side. The water level should sit between the 2 cm and 3 cm marks. If it is too low, add sterile water. If it is too high, you will restrict drainage. Next, clamp the tubing between the patient and the drainage unit. This is important because you do not want to accidentally introduce air into the pleural space while you are manipulating the line. Open the port labeled for suction connection on the drainage system. This is usually a smaller luer-lock or quick-connect port near the top, separate from the water seal chamber. Connect the suction tubing from the wall outlet to this port. Turn the wall suction dial to your prescribed setting and then unclamp the patient tubing slowly. The bubbling in the suction control chamber should become continuous and gentle. That means the suction is working through the water seal. If you see vigorous, chaotic bubbling, you have a leak somewhere in the system. Check every connection point from the patient dressing back through the tubing to the drainage unit. I once spent twenty minutes chasing a false air leak alarm only to find that the cap on the drainage port was cracked. It looked fine until I ran my thumb over it. Replace the entire drainage unit if you suspect a micro-crack in any plastic component.
What Most People Get Wrong
The biggest mistake I see is ignoring the water seal chamber when adjusting suction. People treat the suction control chamber like the primary regulatory device. It is not. The water seal chamber determines whether air can enter or escape the pleural space. If you cranking suction up without watching the water seal chamber, you can create excessive negative pressure and damage lung tissue. I have seen cases where someone set suction to 40 because the bubble was weak, not realizing the water seal had already drained down to 1 cm. Correcting the water level first would have fixed the problem without touching the suction dial at all. Another common error is clamping the chest tube for too long during the connection process. You should never clamp a chest tube connected to a water seal system for more than a few seconds unless you are specifically assessing for an air leak. Extended clamping converts a decompressed pneumothorax into a tension pneumothorax. I had a resident clamp the tube to attach suction tubing and walk away to get supplies. He was gone about four minutes. The patient became tachycardic and hypotensive. We had to insert a needle decompression before the tube was even reconnected. Four minutes. Do not leave the tube clamped unattended.
Get the Full Details
When Suction Is Not the Answer
Not every pneumothorax needs suction. A small, stable, primary spontaneous pneumothorax often resolves with oxygen therapy and observation alone. Adding suction in those cases just increases the risk of prolonged air leak and tissue trauma. The evidence base supports conservative management first. Suction becomes necessary when the pneumothorax is large, symptomatic, secondary to underlying lung disease, or persistent after initial observation. In post-thoracotomy cases, suction helps the lung re-expand against the chest wall, which is mechanically different from treating a simple air leak. There is also a scenario where suction will actively harm the patient. If there is a bronchopleural fistula, applying strong suction can keep the fistula open and prevent healing. In those cases, we run the system on water seal alone at low or zero suction and wait for spontaneous closure or surgical intervention. I learned this the hard way with a patient who had a persistent air leak after a wedge resection. Her pulmonologist ordered suction at 20, and within hours her air leak doubled. We switched to water seal only and the leak improved significantly over the next two days. Communication with the team matters here.
Monitoring and Troubleshooting
Once the tube is connected, check the system every hour initially. Document the amount and character of drainage, the bubbling pattern in both chambers, and the patient's respiratory status. If drainage suddenly stops, do not assume the lung is fully expanded. Milk or strip the tubing only if ordered and if there is thick bloody material that might be obstructing flow. Modern evidence questions the safety of this practice because it generates high negative pressures. Gentle hand compression of the tubing toward the patient is safer and usually sufficient. If you notice continuous bubbling in the water seal chamber, that indicates an active air leak. Document the rate. If it is less than 2 liters per minute, many clinicians will continue with suction and watch for spontaneous resolution. Rates above that threshold may require intervention. If the bubbling is intermittent and only happens with coughing, that is a smaller leak that often resolves on its own. The suction canister should be changed when it reaches the fill line, usually around the two-third mark. Do not wait until it is full. Overflow can introduce contaminants and disrupt the seal. Empty the canister by tilting it carefully into a larger collection container, keeping the tubing pointed downward the entire time to avoid splashing. Record the volume and character before discarding. The drainage amount and color change over time gives you information about whether bleeding is ongoing or resolving.
Disconnection Scenarios
If the drainage system breaks or disconnects from the patient, immediately clamp the tube close to the insertion site. Then place the patient in a supine position on the affected side if possible. This traps any air and limits the size of the pneumothorax. Apply an occlusive dressing to the insertion site if you have one available. Replace the entire drainage system with a new sterile unit. Do not try to reconnect the old unit. I have seen this happen when patients pull on their tubing during transport or when nursing staff is rushed during shift change. It happens more often than anyone wants to admit. When the physician decides the chest tube is ready for removal, they will typically clamp it first and observe the patient for several hours to ensure no recurrent pneumothorax develops. Some protocols skip clamping and go straight to removal if the drainage is minimal and there is no air leak. Follow your institution's protocol. Never remove a chest tube yourself unless you are the designated provider. The whole process of setting up chest tube to suction usually takes ten to fifteen minutes if you are familiar with the equipment and the patient is stable. It feels slower when you are doing it for the first time and second-guessing every connection. That is normal. The key is understanding why each step exists rather than treating it as a rote checklist. Once you understand the physiology behind the water seal and the suction control, the procedure becomes much less intimidating.