Working With Labeled Chest X-Ray Data
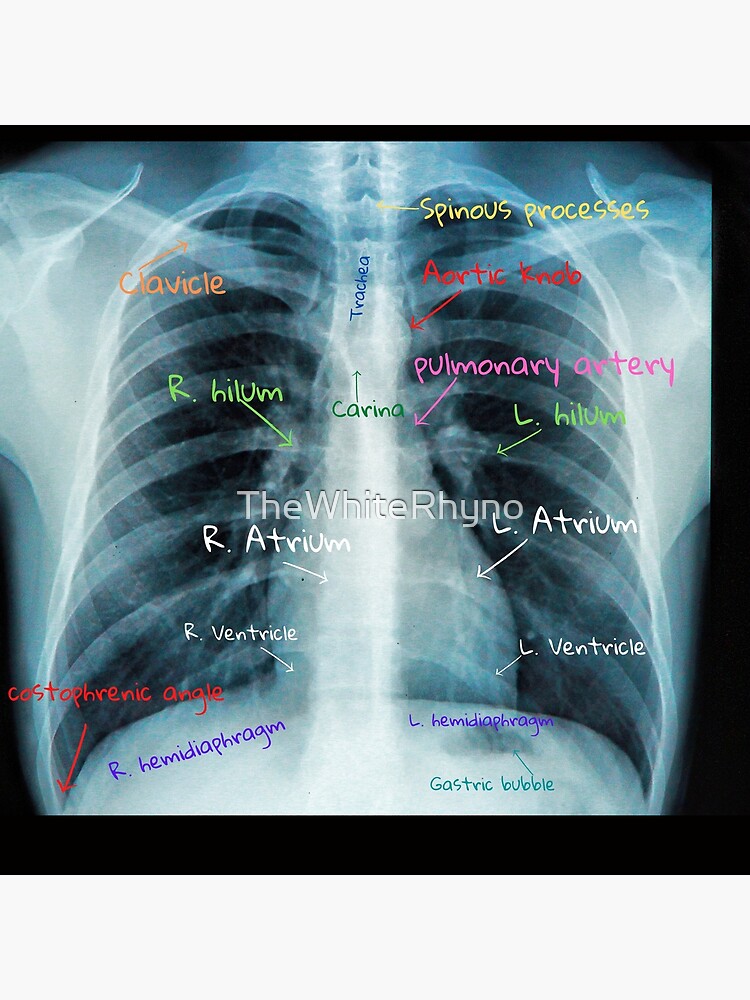
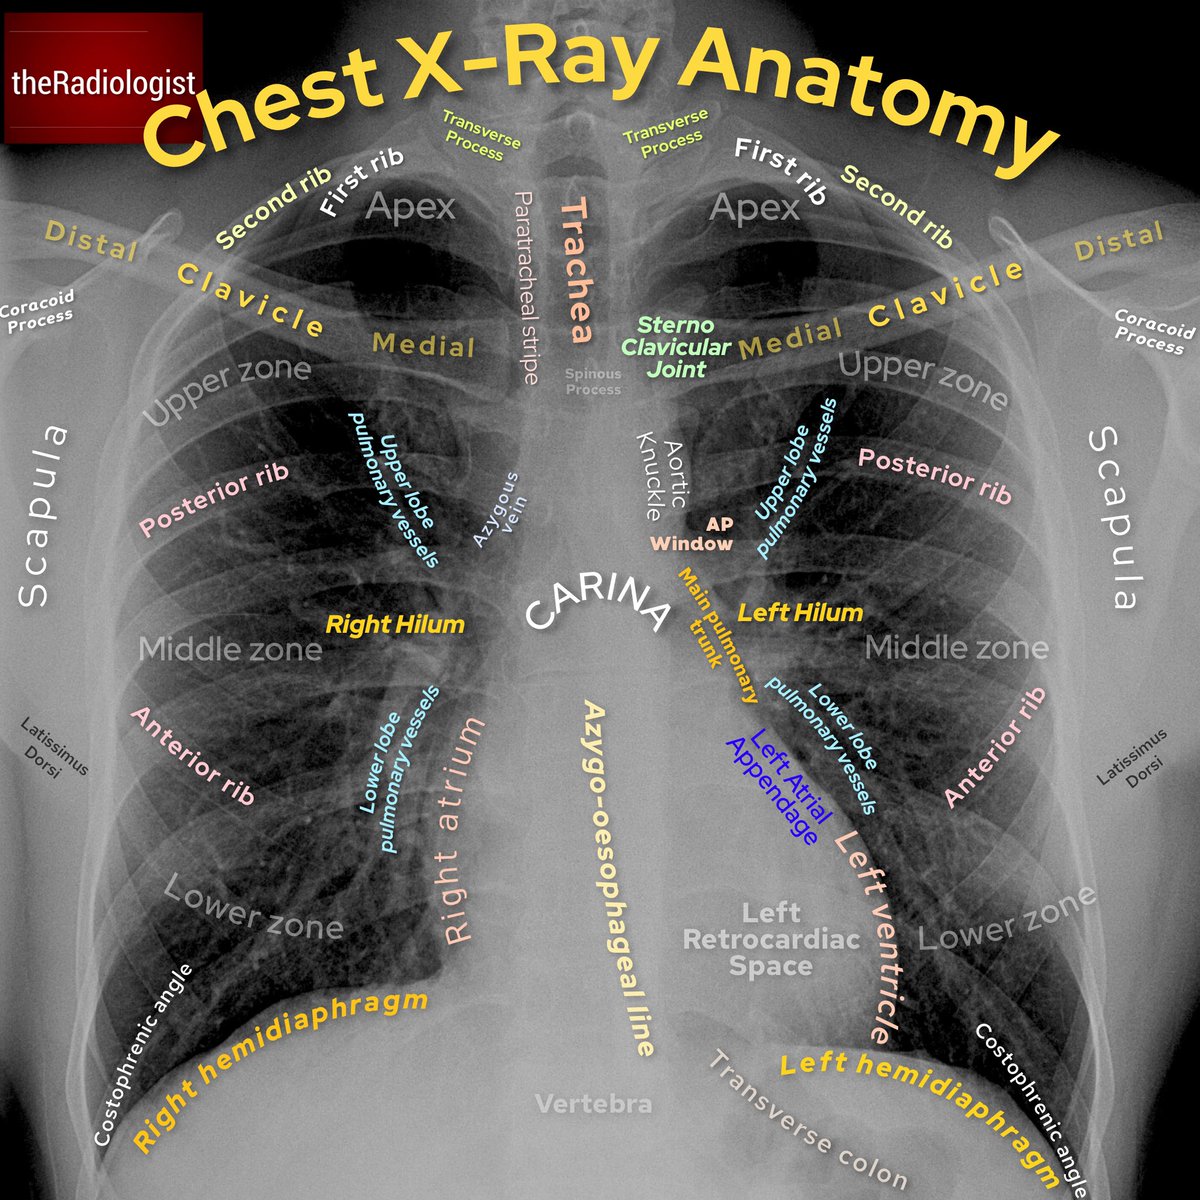
Chest X-ray with labels is just a dataset where each image has annotations attached — bounding boxes around pathologies, segmentation masks for organs, or class labels like pneumonia, atelectasis, or pleural effusion. That's it. The reason people get confused is because there are dozens of these datasets now and they're not all created equal. When I first started pulling together training data for a pneumothorax detection model, I spent a week wrestling with the CheXpert dataset. The labels in CheXpert are notoriously noisy because they're extracted from radiology reports using NLP pipelines. You'll see entries marked as "uncertain" alongside positive and negative findings, and if you just treat them as binary labels, your model will learn garbage. The workaround I used was to filter for only clearly positive and clearly negative cases, then augment the uncertain ones as a separate class during training. It wasn't ideal, but it gave me something usable without spending weeks manually relabeling.
Where to Find Chest Xray With Labels
The main repositories are MIMIC-CXR, CheXpert, NIH's ChestX-ray14, and RSNA Pneumonia Detection Challenge dataset. MIMIC-CXR requires passing a CITI ethics course and signing a data use agreement, which takes about two weeks. CheXpert is faster to access but needs approval through Stanford's institutional review. ChestX-ray14 is the most straightforward — open download, 112,000 images with 14 disease labels. RSNA is specifically for pneumonia and uses bounding boxes, which makes it more useful if you're building object detection models rather than classification models. For beginners, I'd start with ChestX-ray14. It's the least friction to get working. But be aware that the labels come from report mining, not radiologist annotation, so false positives in the label set are common. A significant chunk of those "normal" images probably have minor findings that got missed by the extraction pipeline.
The Practical Side of Using These Datasets
Everyone talks about downloading the data. Nobody mentions the preprocessing step that eats half your weekend. Chest X-rays come in DICOM format. You need to convert them to something your training pipeline can handle — PNG or JPEG works fine for most architectures. I use SimpleITK for this. The issue is that DICOM files contain embedded metadata about windowing and scaling that gets lost in conversion. If you're training on raw pixel values without respecting the original Hounsfield-like normalization, your model learns the scanner calibration artifacts instead of the actual pathology. Here's what actually works: rescale the pixel intensities per-image based on the min and max values found in the DICOM header, then clip to the meaningful range. For lung imaging, a standard approach is to focus on the range between -1000 and 400 Hounsfield units if the modality supports it, or just percentiles on the image itself. I typically use the 1st and 99th percentile for clipping and linearly map to [0, 1]. This handles the variation between different hospital PACS systems better than a fixed window. Another thing people miss is that Chest X-ray with labels often contains duplicate patients across training and test splits. The official splits from most papers handle this, but when you pull raw data yourself, you need to deduplicate by patient ID. I once trained a model that seemed to hit 98% accuracy on validation and realized two months later it was just memorizing individual patients because the same person appeared in both sets. Check your patient IDs before you split.
Get the Full Details

A Note on Quality
These datasets are useful for prototyping and benchmarking. They are not production-ready. The label quality varies wildly between datasets. The image acquisition protocols are inconsistent — different hospitals, different machines, different positioning. A model trained on ChestX-ray14 will not generalize to images from a different geographic region without fine-tuning. I've seen this happen repeatedly. If you need something more reliable for a clinical application, the approach is to build your own labeled dataset with radiologist annotation. It costs money and takes time, but the labels are actually usable. Alternatively, you can fine-tune a model pretrained on one of these datasets using your own limited labeled data, which tends to work better than training from scratch on small proprietary datasets. The RSNA Pneumonia dataset is probably the best quality labeled dataset currently available because the annotations are pixel-level bounding boxes drawn by radiologists, not extracted from reports. If your use case is pneumonia detection or any task involving localization, that's the one to start with. Just be aware it's single-disease, so it won't help you build a general chest X-ray classifier.
A quick reference: - NIH ChestX-ray14: 112k images, 14 labels, report-mined, good for baseline models - CheXpert: 224k images, 14 findings, uncertain labels included, requires Stanford approval
- MIMIC-CXR: largest volume, free-text reports with structured labels, requires CITI certification - RSNA Pneumonia: 30k images, bounding boxes, single disease, radiologist-labeled That covers it. Pick the dataset that matches your task, check for patient overlap before splitting, normalize your intensities properly, and don't expect it to work perfectly out of the box.