Understanding Normal Ranges for Kids
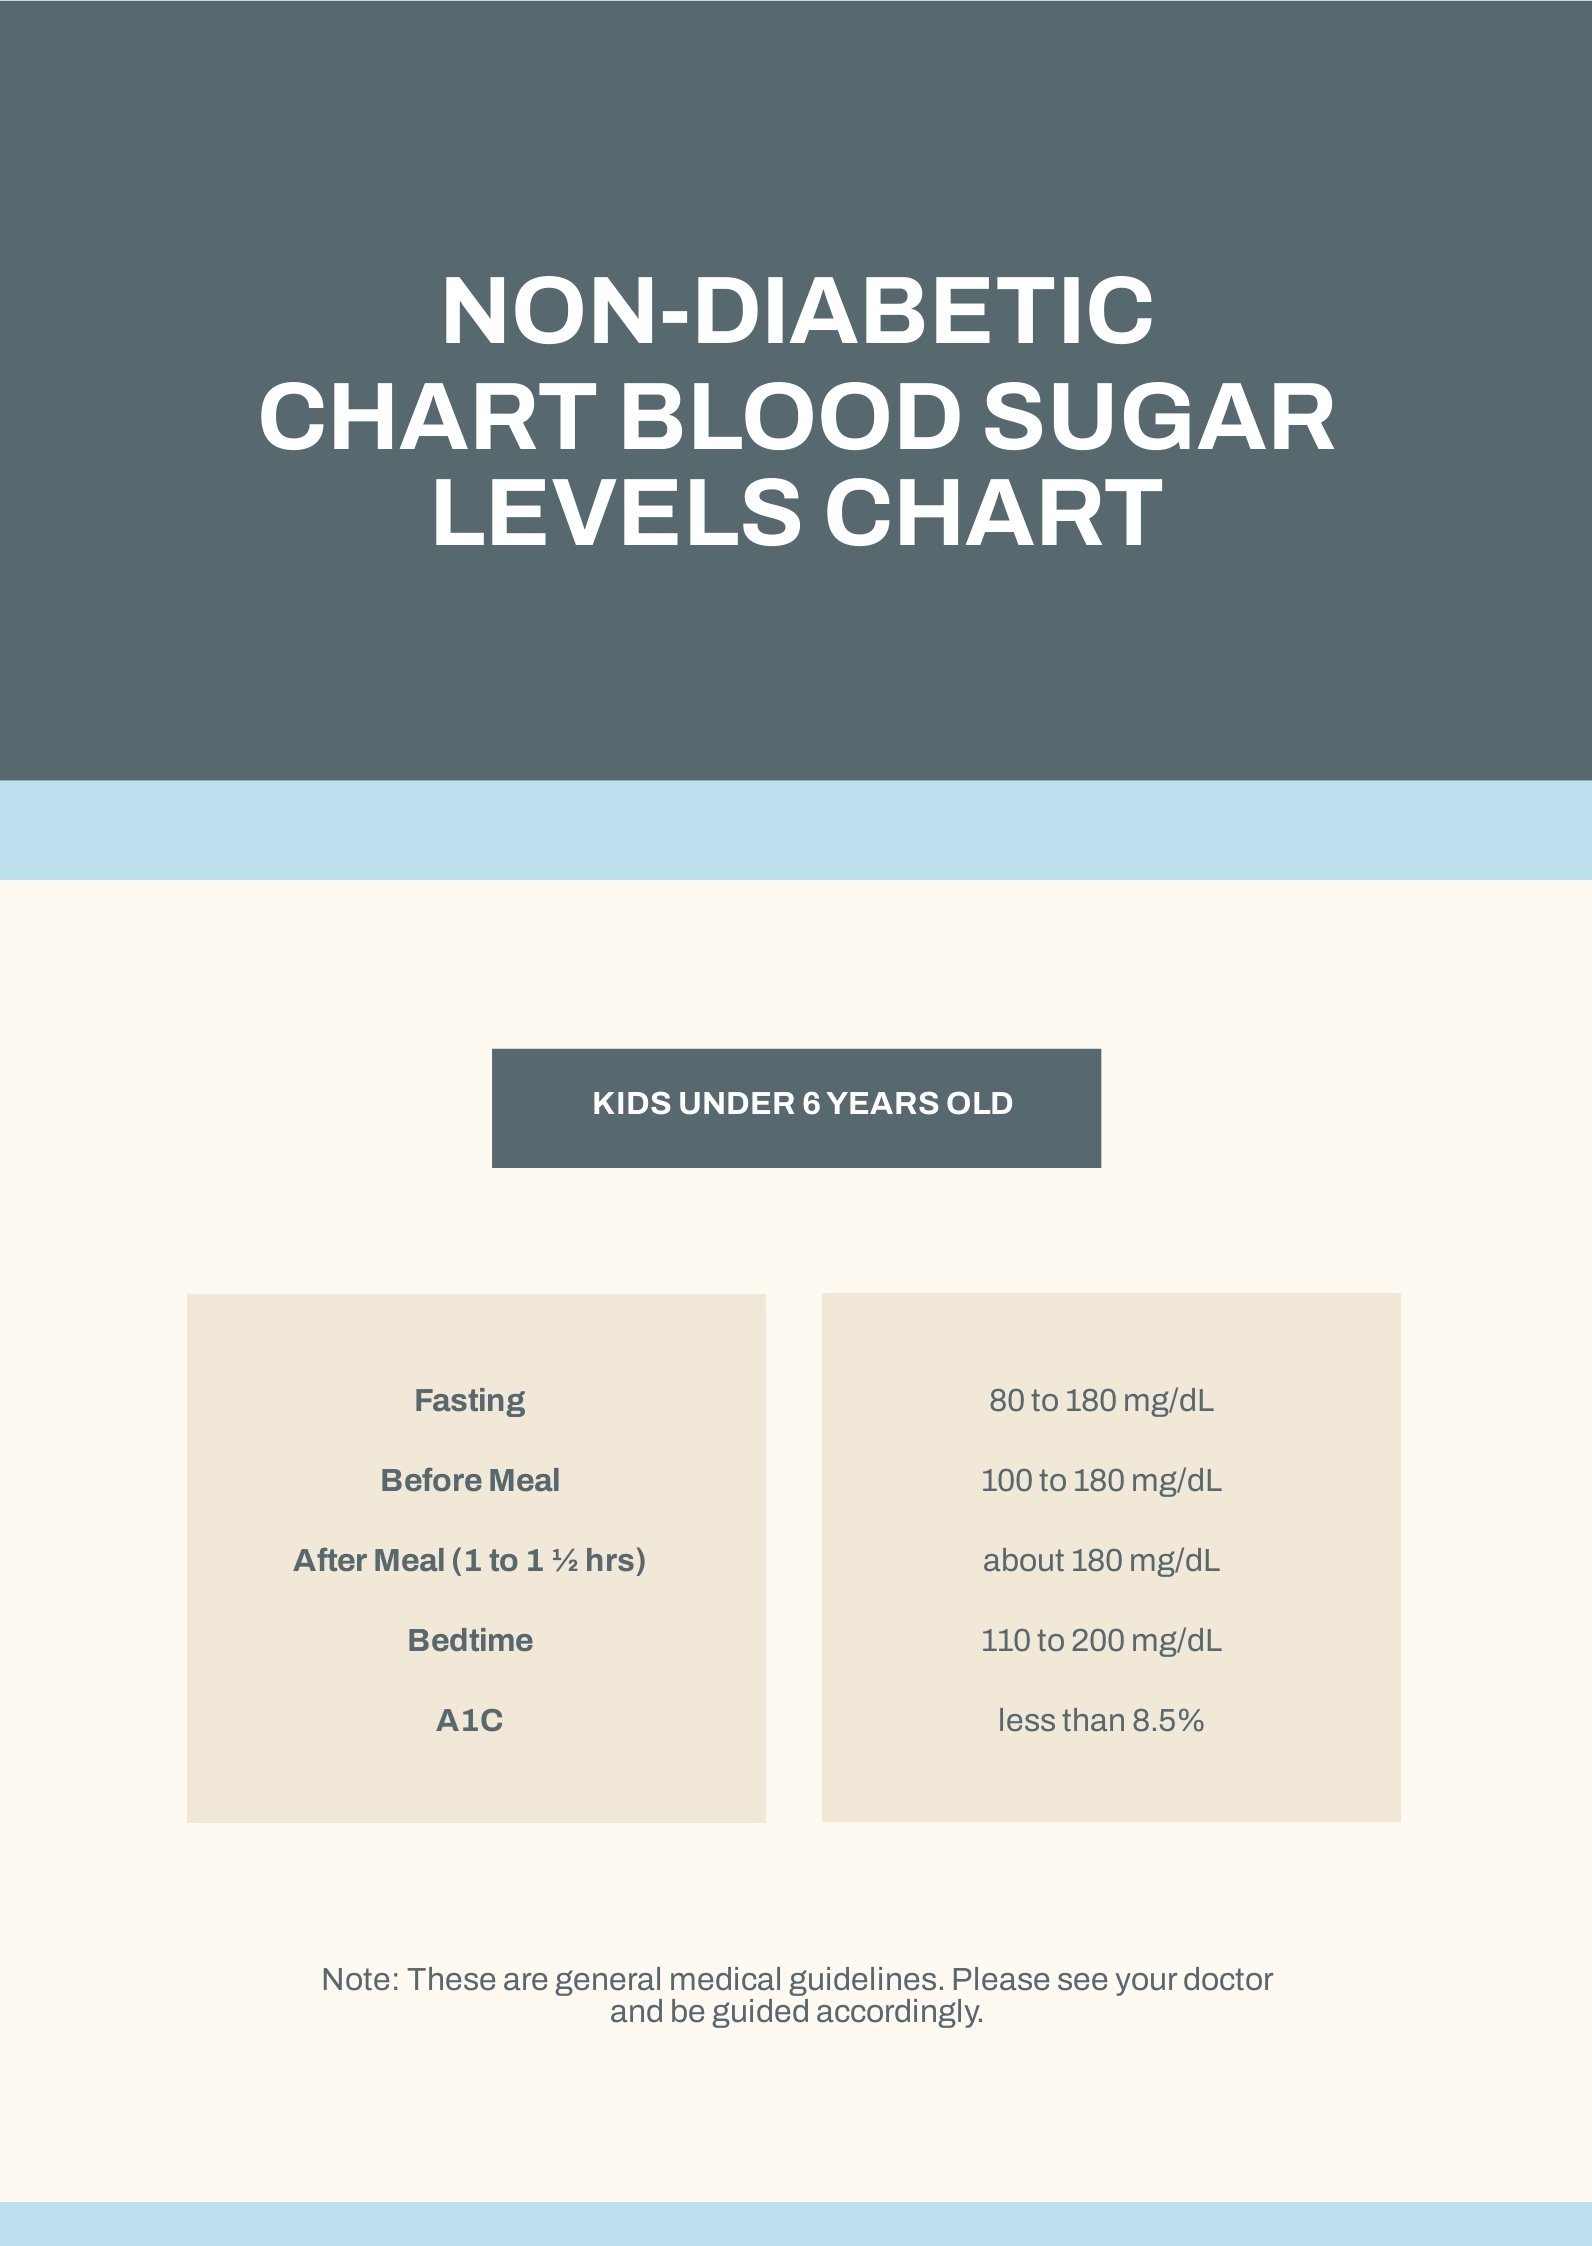
Most parents get handed a glucose chart at diagnosis and spend the next week obsessing over every digit. The numbers matter, but they don't mean the same thing as adult targets. A child's body handles glucose differently, and the ranges reflect that. Here is what the actual numbers look like across different ages and situations. Below is a simplified breakdown you can pin to the fridge or save on your phone. Fasting (before eating):
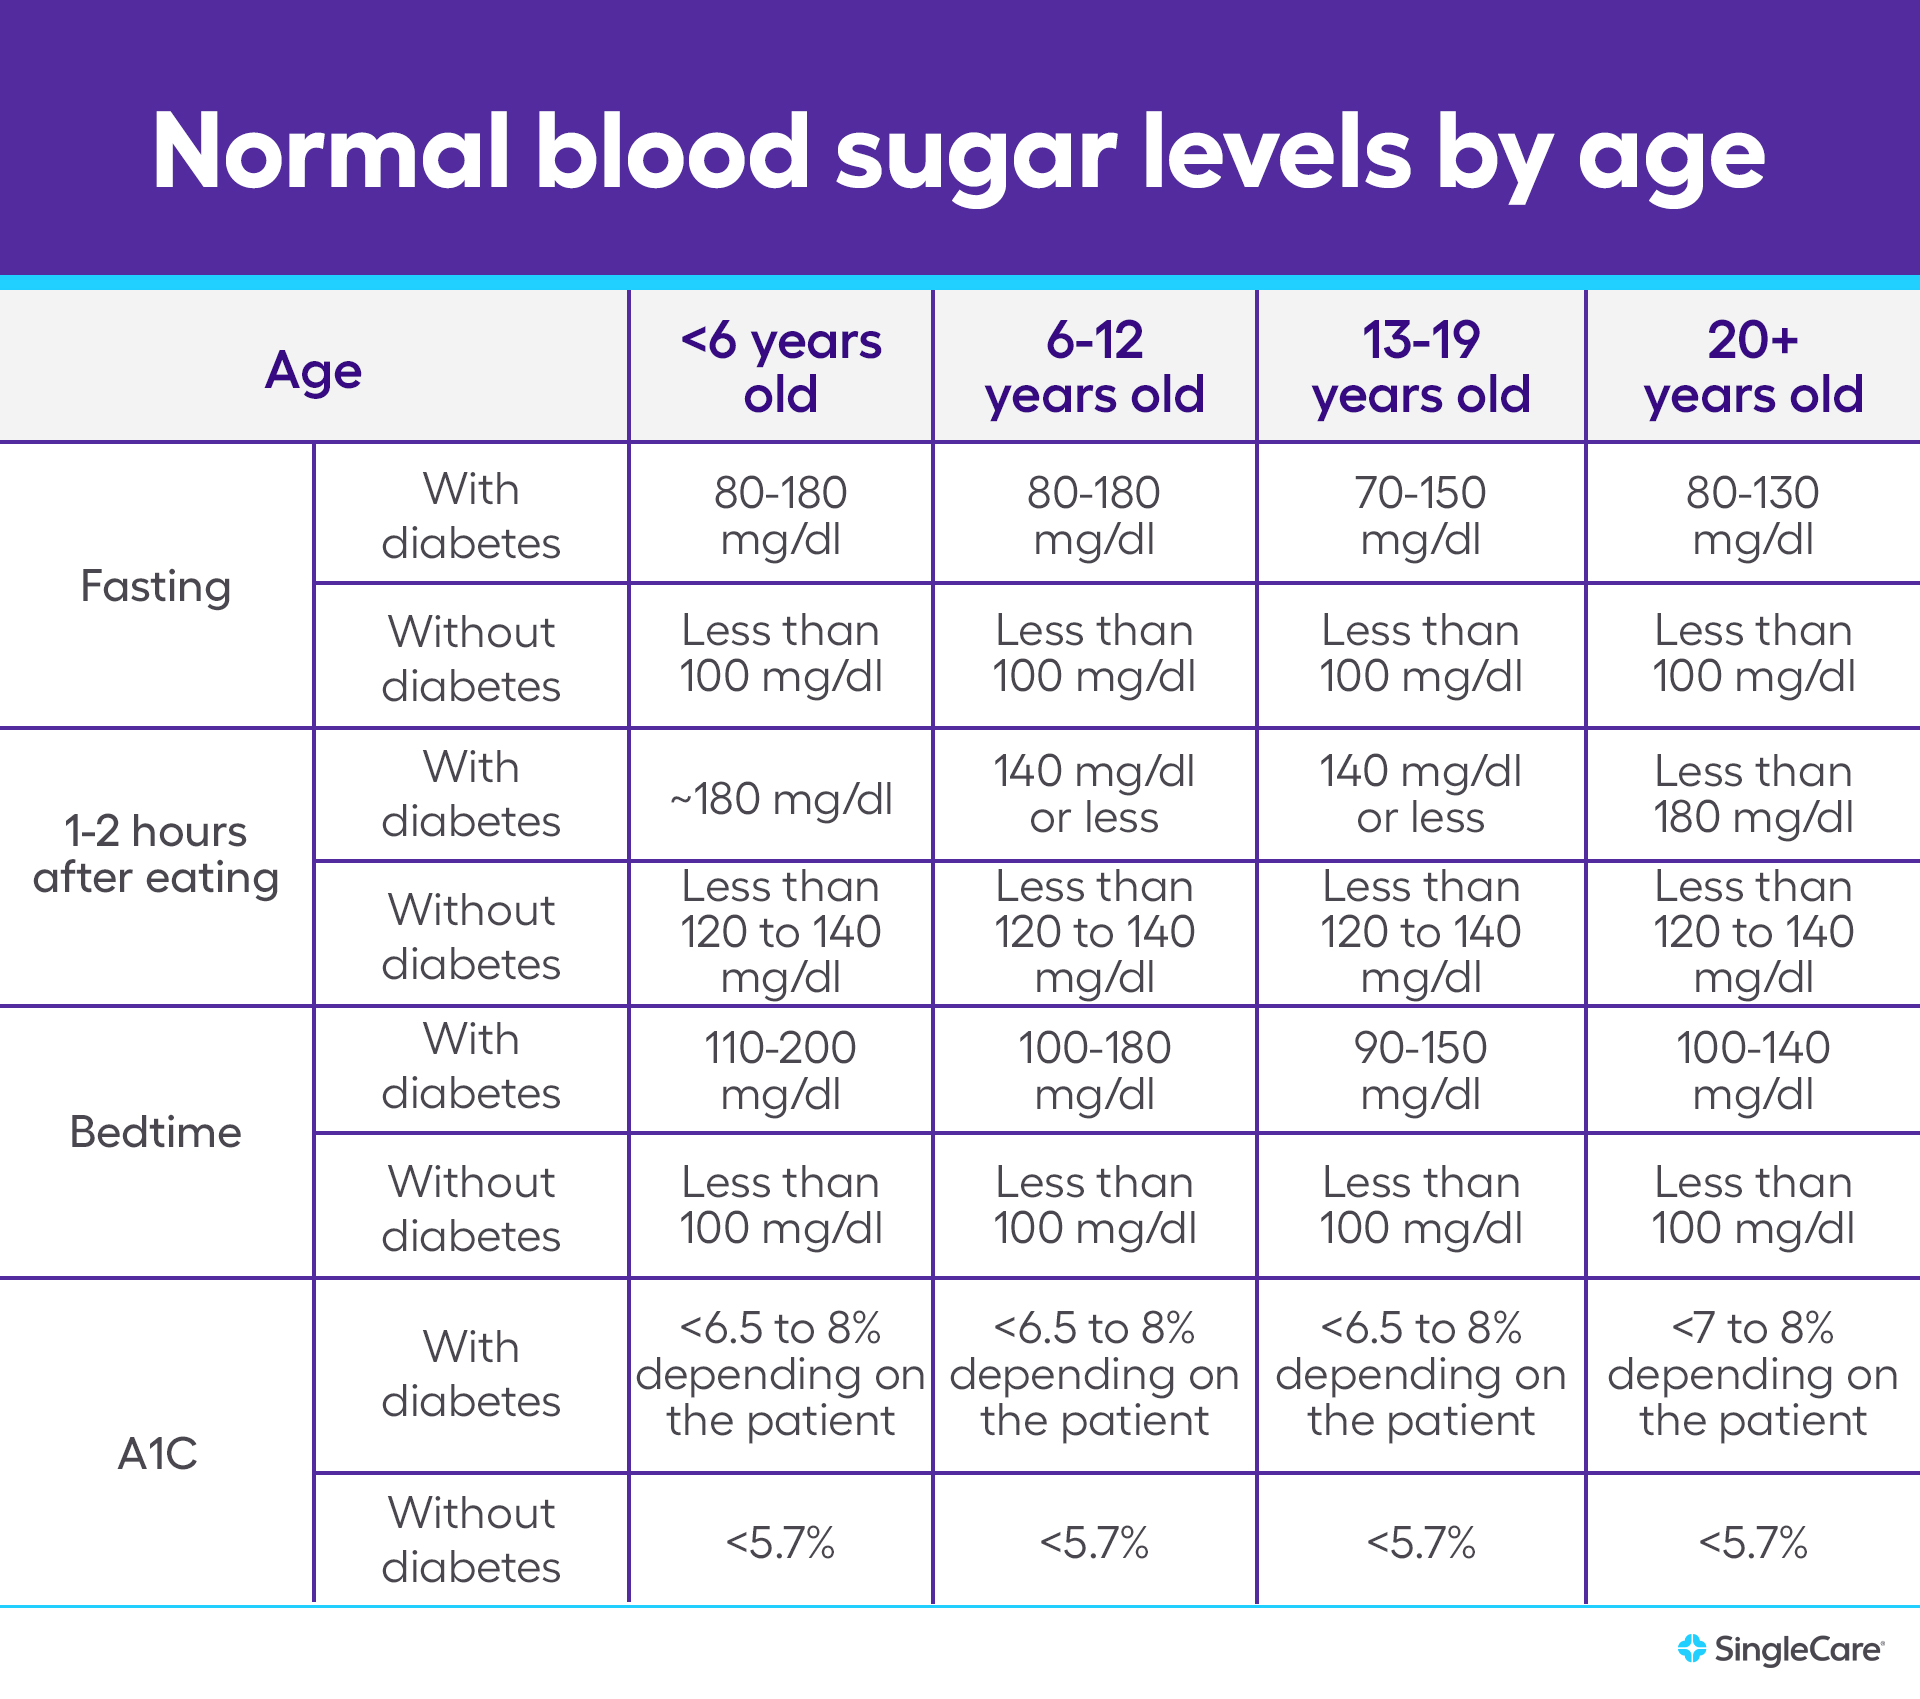
Ages 0-6 years: 80-180 mg/dL Ages 6-12 years: 80-140 mg/dL Ages 12-18 years: 80-130 mg/dL
Before meals (pre-prandial): Same ranges as fasting above. One to two hours after starting a meal (post-prandial):
Get the Full Details
Ages 0-6 years: less than 180 mg/dL Ages 6-12 years: less than 140 mg/dL Ages 12-18 years: less than 140 mg/dL
At bedtime: Ages 0-6 years: 100-200 mg/dL Ages 6-12 years: 100-180 mg/dL
Ages 12-18 years: 90-150 mg/dL These are general targets from pediatric diabetes guidelines. Your child's endocrinologist may adjust them. Some kids run higher safely. Others need tighter control. The chart on paper is not the law.
How to Use This in Real Life
Reading the numbers is the easy part. The hard part is interpreting them in context. A reading of 200 mg/dL at 3 PM on a school day means something completely different than a reading of 200 mg/dL right after your kid just finished a candy bar at a birthday party. Context changes everything. I spent three years managing type 1 diabetes in a nine-year-old. The first year was a constant exercise in second-guessing. I thought every number outside the box was an emergency. It wasn't. The body does weird things that have nothing to do with insulin dosing. Here is one specific problem that almost broke me. My kid had consistent morning highs between 220 and 280 mg/dL every single day for about six weeks. I adjusted the basal rate, switched the bedtime snack, tried a different injection site, even questioned whether the pump was actually delivering. Nothing moved the number. Then I realized the dawn phenomenon was hitting hard because of growth hormone surges during a growth spurt. His feet went from size 3 to size 5 in four months. That changes insulin needs dramatically. The workaround was splitting the evening rapid-acting dose into two smaller doses and adjusting the overnight basal in half-unit increments. It took about two weeks to find the right balance. The numbers dropped to range without any major changes to his daytime routine.
Common Mistakes People Make
The biggest mistake I see is treating the chart as absolute truth. Kids are not small adults. Their glucose variability is higher because their metabolism runs faster and their activity levels are unpredictable. A child who burns through carbs during soccer practice will crash harder and faster than an adult would in the same situation. That is physiology, not poor management. Another mistake is obsessing over single readings. One high number does not mean the whole day was off. One low number does not mean the dose was wrong. You need trend data over days, not moments. If your meter has a trend arrow feature, pay attention to it. It tells you where the glucose is heading in the next fifteen to thirty minutes, which is often more useful than the current number. There is also a tendency to blame the insulin when the problem is actually absorption. Injection site rotation matters more than most parents realize. Lipohypertrophy, those small lumps under the skin from repeated injections in the same spot, can reduce insulin absorption by up to fifty percent in severe cases. I discovered this when my kid's post-meal numbers spiked despite correct carb counting and dosing. We rotated sites aggressively for two weeks and everything normalized. Just saying to check the skin.
When to Worry and When to Breathe
Low blood sugar under 70 mg/dL is the real concern. Below 54 mg/dL is medically significant hypoglycemia and needs immediate action regardless of symptoms. If your child is unconscious or unable to swallow, do not put food or drink in their mouth. Use glucagon if you have it prescribed and call emergency services. This is non-negotiable. High blood sugar above 240 mg/dL with ketones present requires a different response. Check for ketones using urine strips or a blood ketone meter if you have one. Moderate to large ketones with sustained high readings usually means your child needs a correction dose and possibly extra fluids. If ketones are high and vomiting starts, that is a hospital visit, not a home management situation. Diabetic ketoacidosis develops faster in young children than in adults. I learned this the hard way at 2 AM when a reading that seemed manageable turned into an ER trip within four hours because we missed the ketone sign. For numbers between 70 and 240, most of the time the right answer is to monitor and adjust gradually rather than react aggressively. Overcorrecting a high reading often causes a reactive low later, which then causes a rebound high. That cycle wastes everyone's sanity.

Practical Tools That Actually Help
A simple spreadsheet or logbook beats a fancy app if the app is not being used consistently. I tracked every reading, every dose, every meal, and every activity for two years. The pattern recognition that came from reviewing that data weekly saved more corrections than any single adjustment ever would have. The log showed me that Tuesdays consistently ran higher because of a stress response to a weekly school event, something I would never have connected from daily glances at the numbers. If you use a continuous glucose monitor, learn the difference between time in range and average glucose. They tell different stories. A kid can have a good average but spend a lot of time swinging between highs and lows, which is harder on the body than stable numbers in the upper range. Time in range above 70 and below 180 for at least seventy percent of the day is a common pediatric target, but again, this varies by individual. The charts and numbers here are starting points. Work with your pediatric endocrinologist to tailor them. Keep a log. Watch for patterns over days, not minutes. And for the love of everything, stop punishing yourself for numbers your kid's body does not want to cooperate with. This is a marathon, not a sprint, and the people who survive it without burning out are the ones who accept that variability is normal.