Measuring Spines for a Living
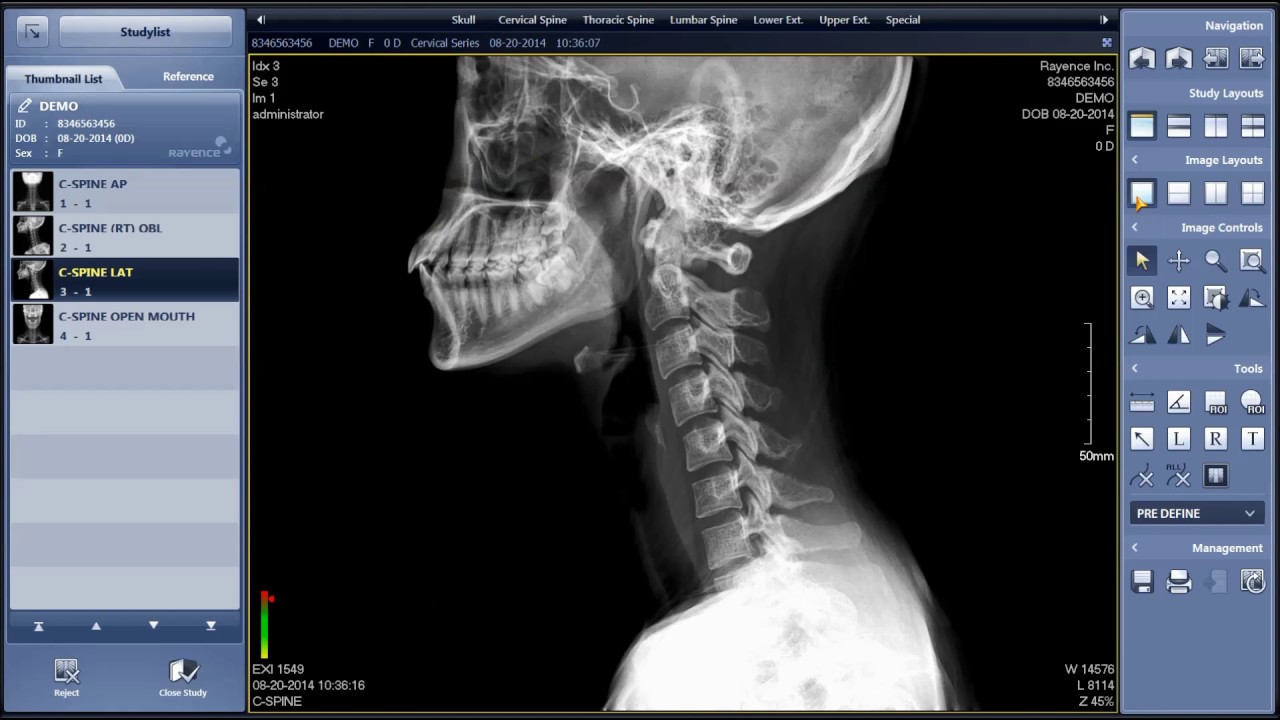
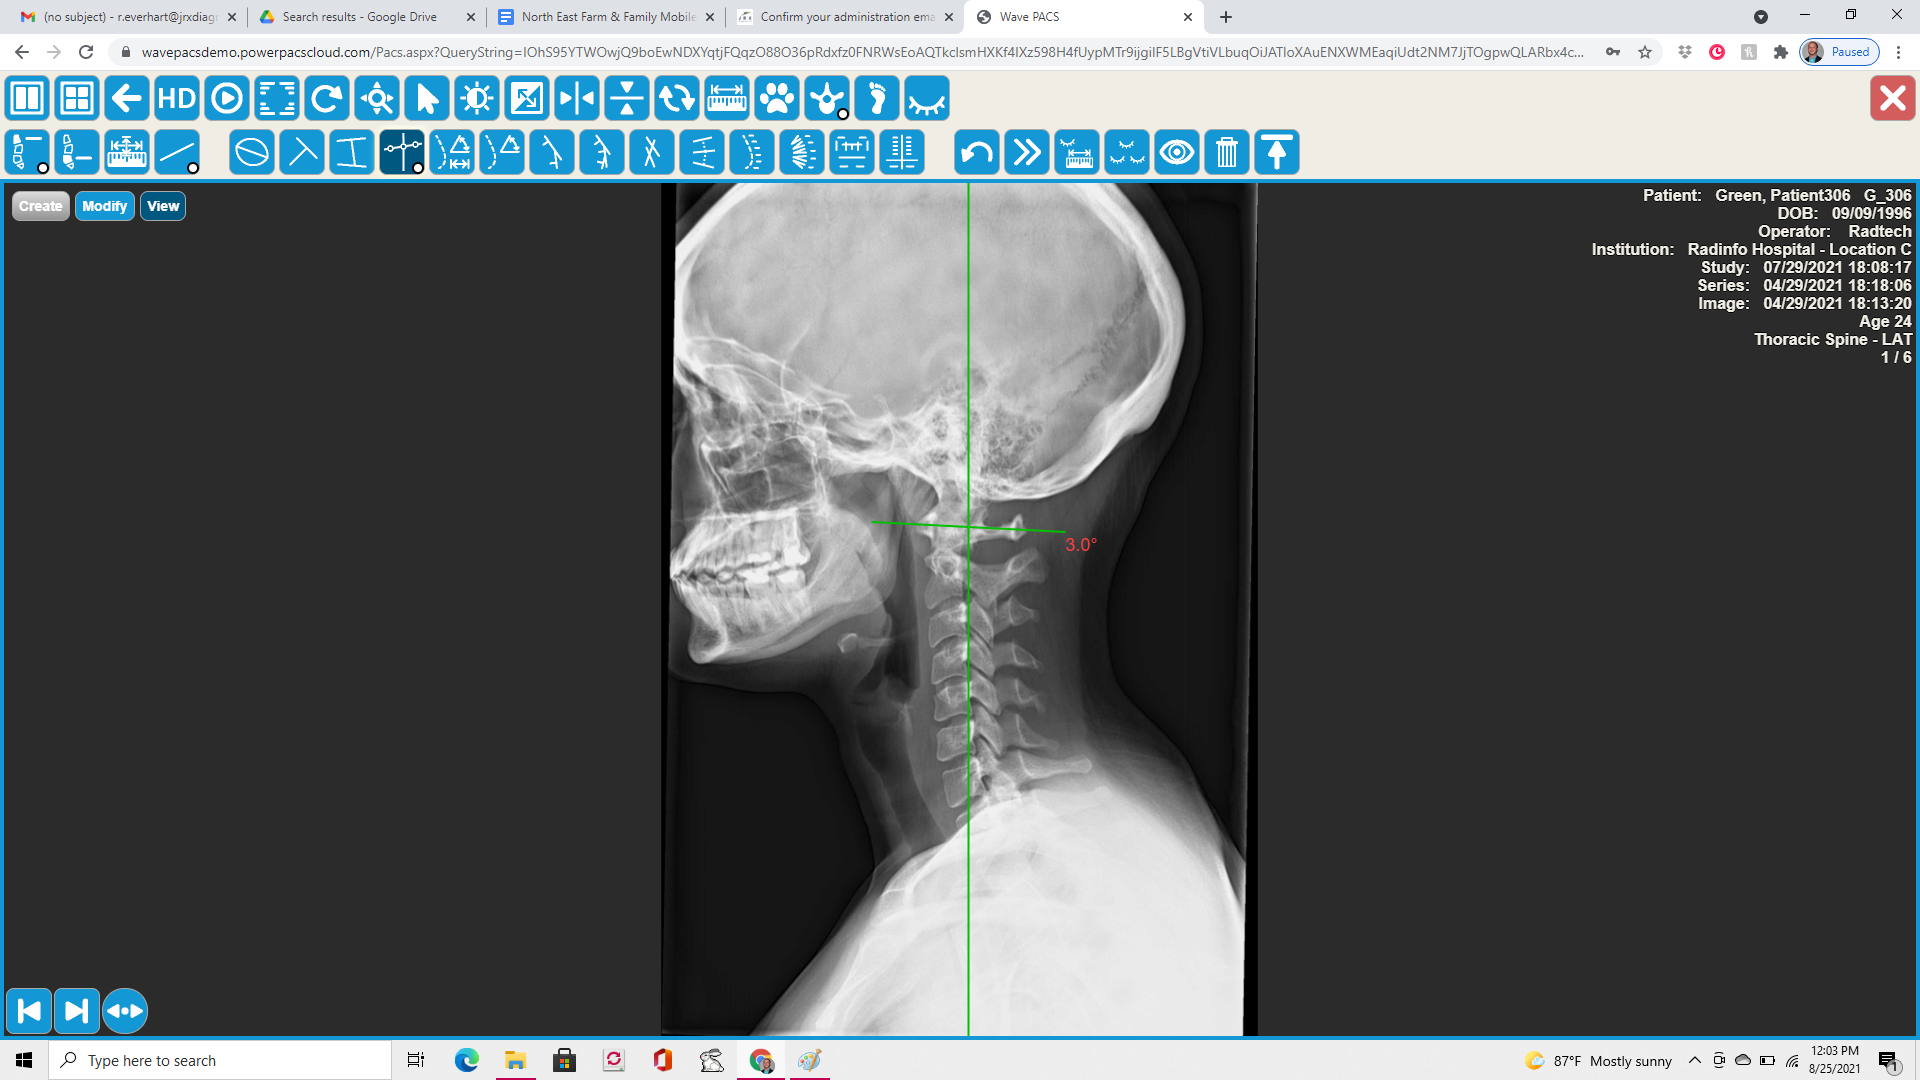
Most chiropractors who rely on X-ray analysis end up with three or four different programs on their computer, none of them talking to each other, and a workflow that takes longer than it should. I've spent about a decade doing this, and the short version is that Chiropractic X Ray Analysis Software exists in two flavors: full DICOM workstations that cost real money, and lightweight angle-measurement tools that are free or cheap and do exactly what you need if your images aren't terrible. The core task is always the same. You open a PA and lateral cervical or lumbar series, mark vertebral endplates, and the software spits out Cobb angles, vertebral lists, and rotational grades. Done. The problem is that "done" rarely happens in under twenty minutes unless your image quality is consistently good and your labeling technique is already second nature.
Choosing Chiropractic X Ray Analysis Software
I use a combination of SpineView for routine cervical and lumbar analysis and CliniView when I need full-spine standing radiograph measurements. Both are Windows-based and accept standard DICOM files. If you're on macOS, you're dealing with either web-based solutions or virtual machines, and that adds a layer of friction most people don't account for until after they've already bought the software. Here's what actually matters when you're picking a tool. First, does it handle landmark placement the way your hand wants to do it? This sounds trivial. It isn't. If placing an inferior endplate marker requires three clicks and a modifier key every time, you'll avoid using the software on complex cases and fall back to manual protractor methods anyway. Second, does it export measurements in a format your practice management system will accept? If you're writing reports by copy-pasting angles into a Word template, that's fine. If you're billing insurance and need structured data, this gap will bite you. Third, and this is the one nobody mentions: does the software preserve your original image without modifying the pixel data? Some older programs create modified DICOM derivatives when they apply landmarks or annotations. Your PACS will reject those files on export, and you'll spend an afternoon renaming and reimporting images. I learned that the hard way with an early version of DynaRead. The software worked great for measurement but corrupted the original DICOM header during annotation save operations. I switched to keeping a read-only copy of every original scan and only annotating a working duplicate. It adds a click or two but it prevents a cascade of file management headaches.
How the Actual Workflow Looks
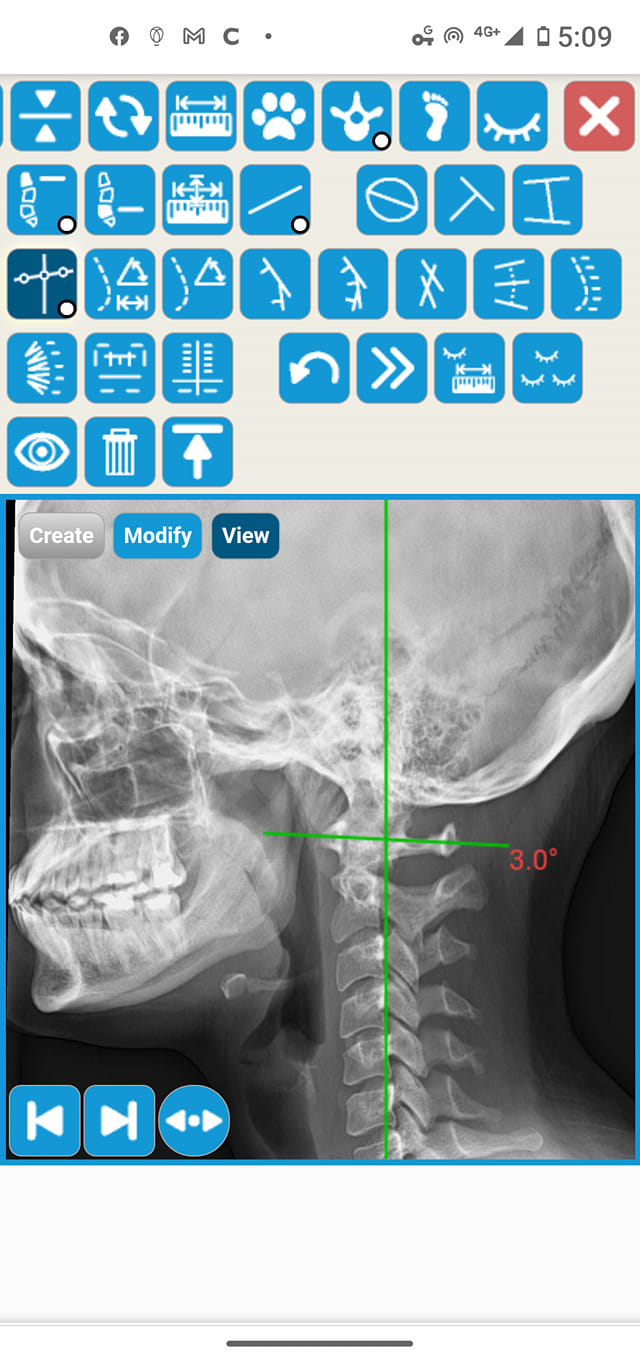
You import the DICOM series, usually by dragging a folder into the application or using the built-in file picker. The software loads all frames. You select the views you want to analyze — typically AP and lateral — and you start marking. The marking protocol for Cobb angle measurement follows the standard radiographic definition: you identify the most tilted superior endplate of the upper vertebra and the most tilted inferior endplate of the lower vertebra in the curve, draw lines along those endplates, and measure the angle between them. The software does the trigonometry. For vertebral list measurements, you drop perpendiculars from the midpoint of the vertebral body to the midline of the spinal canal and record the displacement in millimeters. Rotational grading, usually Perdriolle or Nash-Moe, requires marking pedicle positions relative to the vertebral body outline. Each of these steps is point-and-click. The time investment is in getting the marks precise enough to be defensible if another clinician reviews your work. I keep a reference sheet at my workstation with the standard landmarks for each region. Cervical Cobb angles use C2 through C7. Lumbar uses L1 through L5. Thoracic is L1 to T12 for full-spine studies. Having this visible cuts decision time down significantly, especially on busy days when you're processing twelve to fifteen cases in a row and your brain starts blending one region into the next.
Get the Full Details
The Edge Case That Almost Made Me Quit
About three years ago I ran into a persistent issue with lateral cervical measurements in patients who had significant degenerative changes. The software's automatic endplate detection — which works fine on healthy spines — kept snapping to the anterior osteophyte margin instead of the actual endplate. This inflated vertebral body height measurements and threw off any angular calculations that depended on vertebral dimensions. I was getting Cobb angles that looked clinically wrong compared to my manual readings, and I couldn't figure out whether it was a software bug or a calibration problem. The workaround was to disable the auto-detect feature entirely and place landmarks manually using the posterior-inferior and posterior-superior corners of the vertebral bodies as anchors rather than trying to trace the endplate lines directly. It's slower, maybe forty-five seconds per vertebra instead of fifteen, but the measurements are accurate. I also adjusted the magnification compensation setting in the software preferences because the patient's lateral cervical images had been taken with different source-to-image distances across the series, and the software wasn't correcting for that properly. Once I disabled auto-magnification and set a fixed SID of 72 inches for the entire series, the measurements stabilized.
Pitfalls That Waste Time
Rotation on the PA view is the most common source of error, and it's also the most ignored. When a patient isn't positioned symmetrically, the spinous processes drift away from the midpoint between the pedicles, and the Cobb angle you measure will be artificially widened. Most software won't warn you about this. You have to check the interpedicular distance symmetry and the spinous process alignment yourself before trusting the numbers. I've seen cases where a 4-degree rotation produced a Cobb angle reading that was off by nearly 8 degrees. That's enough to change a treatment decision. Another issue is inconsistent image labeling. Some imaging centers label the top of the image as "superior" and others assume the anatomical position regardless of how the DICOM file was saved. If your software orients the image upside down and you mark landmarks accordingly, your angles will be numerically correct but directionally wrong. I now verify the orientation on every new case by checking that the dens of C2 appears above C3 on the lateral view and that the clavicles are equidistant from the spinous processes on the PA cervical. Takes ten seconds and prevents embarrassing report errors. Image quality varies wildly between facilities. Portable X-rays taken at the bedside for hospitalized patients often have excessive scatter, poor contrast, and magnification artifacts that make landmark placement unreliable. I don't trust measurements from portable films for formal analysis. I note the limitation in the report and recommend a follow-up with properly positioned radiographs when the patient can be transported. No software can compensate for a fundamentally poor image.
A Note on Limitations
Chiropractic X Ray Analysis Software is not a diagnostic tool. It's a measurement and documentation tool. The software will give you angles and distances. It won't tell you whether those angles are clinically significant, whether they correspond to symptoms, or whether your adjustment plan should change based on a 3-degree difference in Cobb angle measurements taken two weeks apart. That judgment is yours. Software also can't replace proper radiographic positioning. If your technologist or referring facility consistently produces rotated or lordotic films, no amount of measurement precision will save your data. I've sent correction letters to three imaging centers in the past two years about positioning inconsistencies. It's awkward but it improved my measurement reliability significantly. If you're just starting out and don't want to invest in a full DICOM workstation, Sagra Soft's free tools or the built-in measurement functions of RadiAnt DICOM Viewer can handle basic Cobb angle work. They're less polished than dedicated chiropractic software but they're functional and they don't lock you into a subscription. I used RadiAnt for about a year before moving to SpineView, and the transition was mostly about having automated angle calculation and saved templates rather than any fundamental improvement in measurement accuracy.

The bottom line is that the software handles the math. You handle the technique, the positioning checks, and the clinical interpretation. Get those three right and the tools are fine. Get them wrong and you'll be second-guessing every number the program gives you.