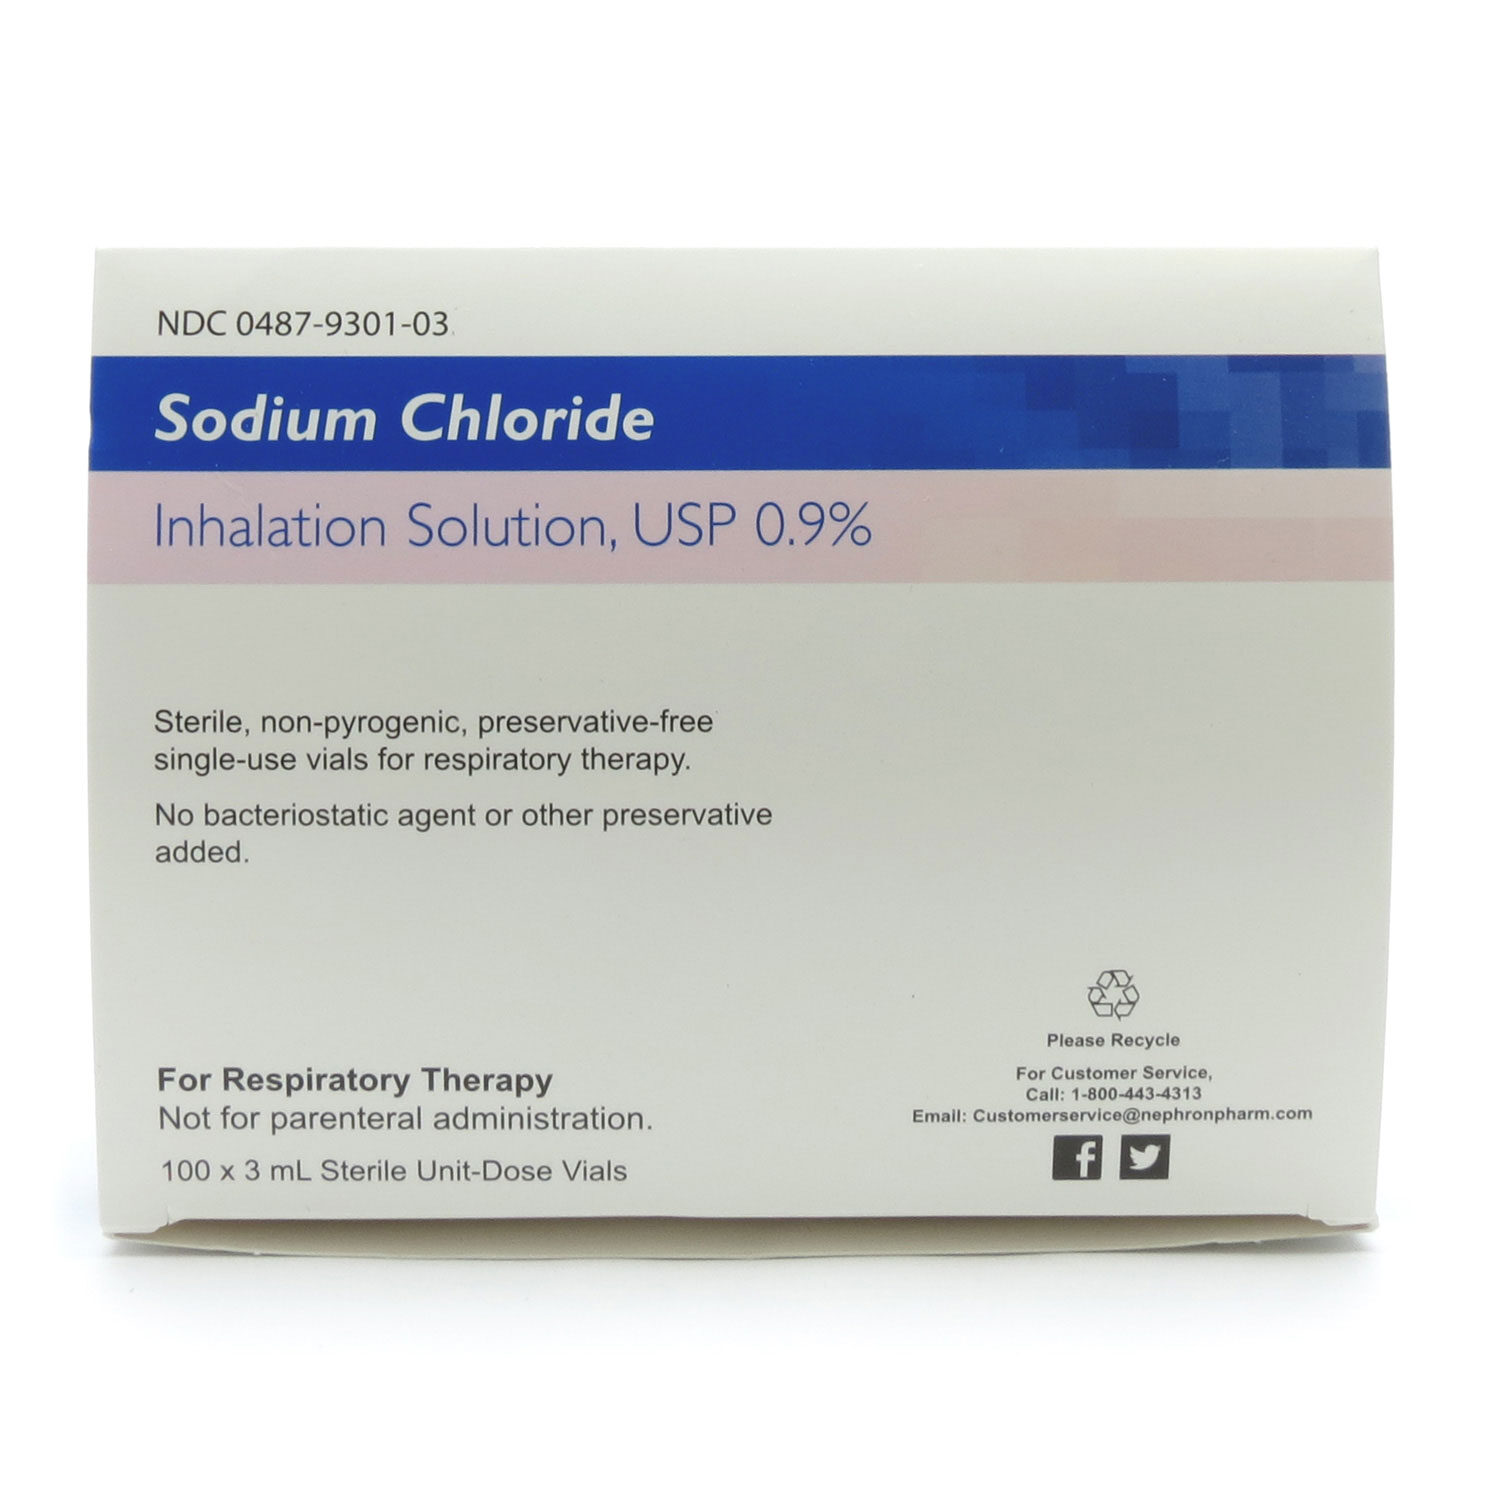
What Chloride 9 Inhalation Solution Actually Is
It is 0.9% sodium chloride in water, sterile, intended for nebulization. Same concentration as normal saline. The "9" refers to the percentage. Nothing fancy about it. You breathe it into your airways, usually for humidification or to thin secretions before suctioning or post-procedure recovery. I have dealt with this in clinical settings for years. Patients get it through a jet nebulizer or an ultrasonic one. The volume you typically administer is 3 to 5 milliliters per treatment. Anything above that and you are just wasting product and making the patient cough more than necessary. The machine handles the rest.
Where to Get Chloride 9 Inhalation Solution
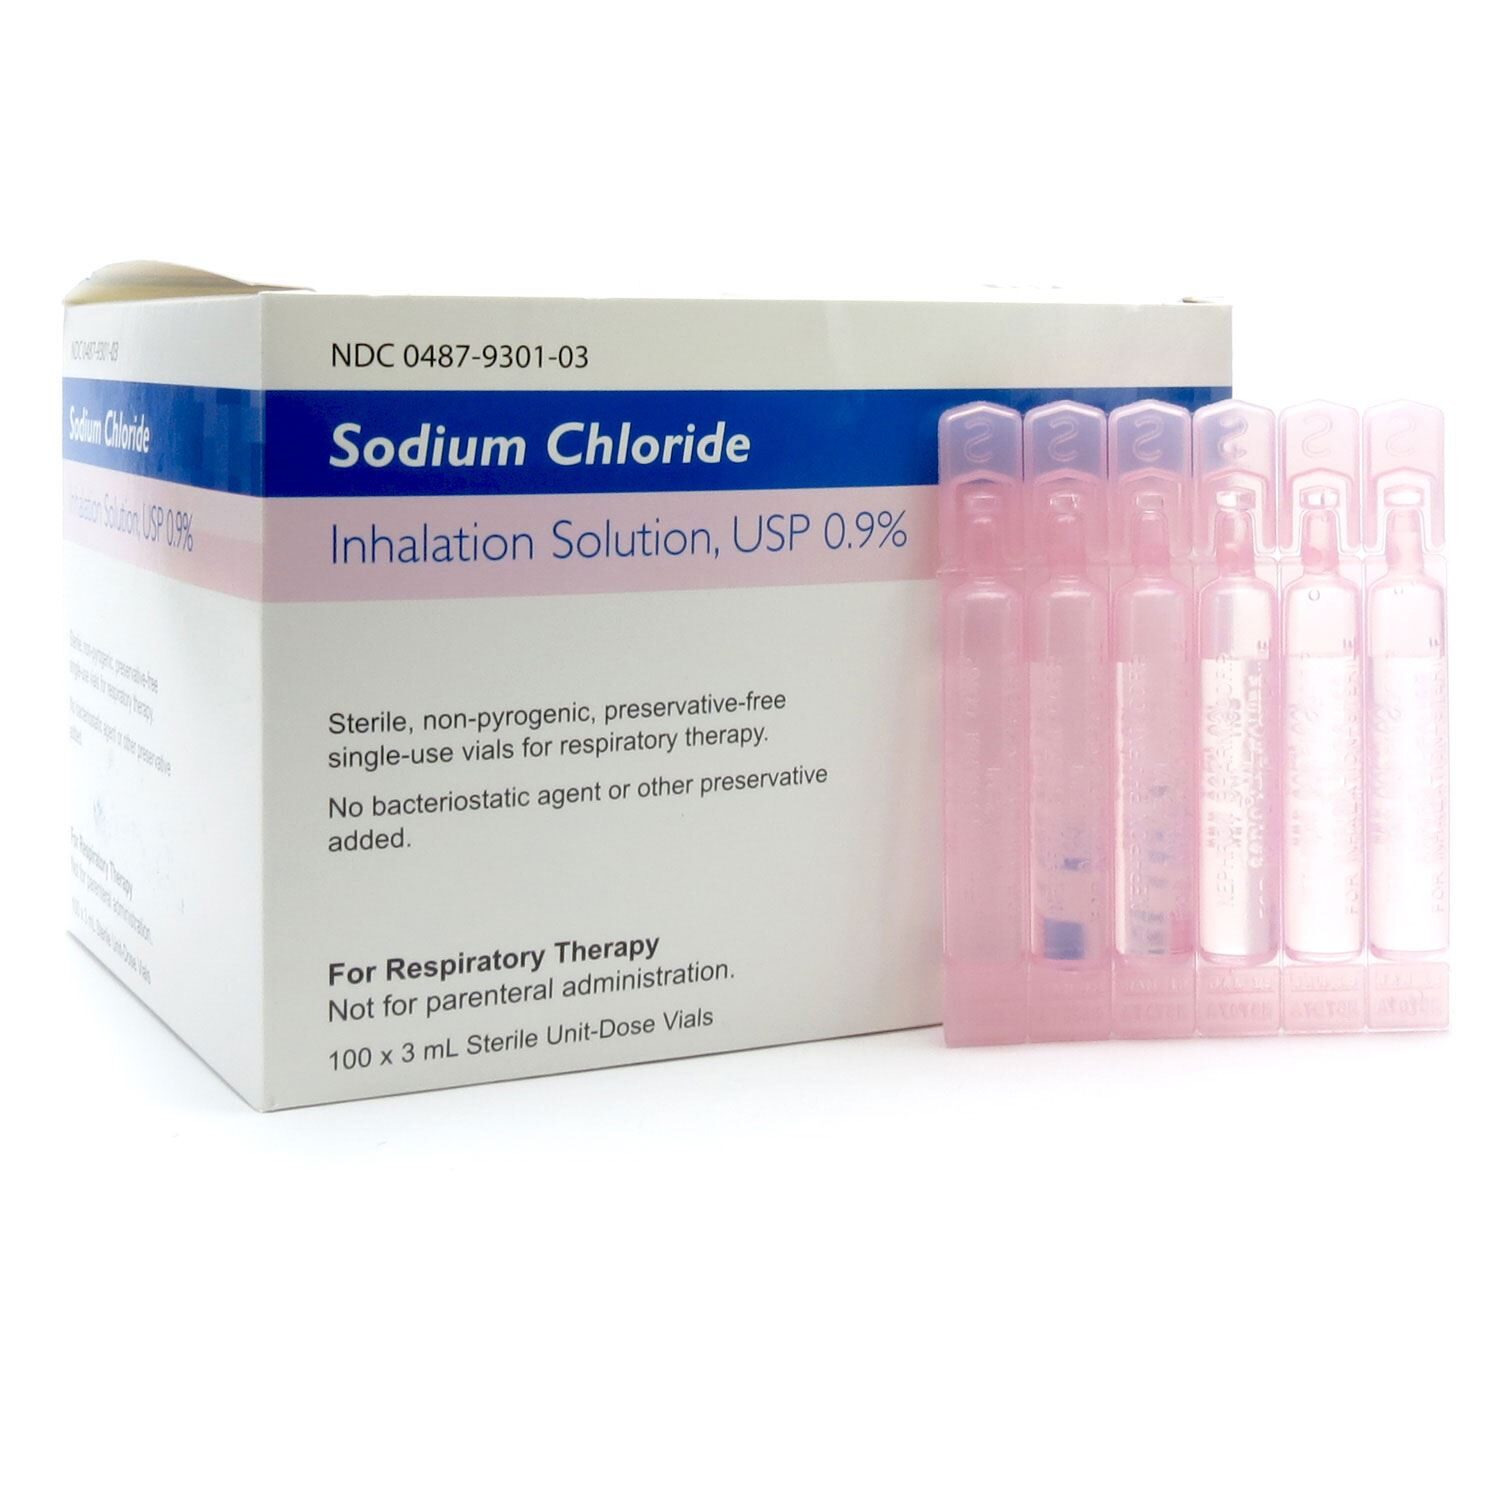
You can order it from most medical supply companies. Amazon has units that ship fast. WebMD Shop, Medical Direct, even your local pharmacy will sometimes carry it under a store label. The brand doesn't matter much since the formulation is standardized. Just make sure it is labeled for inhalation use. Do not substitute ophthalmic saline or wound irrigation fluid. Those have different preservative profiles and particulate standards. One thing I noticed right away when I first started using this: the single-dose vials are actually better than the multi-dose bottles. Multi-dose containers get contaminated faster once you start poking them with nebulizer cups repeatedly. The single-use 3 mL vials seal themselves after each opening. I switched entirely to those after a few respiratory therapist colleagues pointed out the infection risk. Made sense.
How to Use It Properly
Open a single-dose vial right before you need it. Do not pre-open a bunch and store them. Once that seal is broken, the clock starts. The manufacturer typically gives you 24 hours if you have to keep the remainder, but I never trust that. I throw it out after one use. It costs more but saves headaches later. Pour the entire 3 mL into the nebulizer cup. Attach the mouthpiece or mask depending on what the patient needs. Set the compressor to about 2 to 4 liters per minute flow. You want a steady mist, not a furious spray. Patients tend to hyperventilate if the output is too aggressive, which leads to dizziness and sometimes bronchospasm. Breathe normally through the mouthpiece for about 5 to 10 minutes. If they are on oxygen simultaneously, you may need to adjust the setup. The nebulizer can disrupt oxygen delivery accuracy, so check the flow rates. Some clinics just switch to room air during the treatment to avoid this variable.
Get the Full Details
Chloride 9 Inhalation Solution and Common Mistakes
Here is where people mess up. They add other medications directly to the saline in the cup without checking compatibility. Saline is inert, but mixing it with certain bronchodilators or mucolytics can change the osmolarity enough to irritate the airways. Albuterol is fine mixed in. hypertonic saline combined with other drugs is where problems start. I ran into a specific issue last year that took me a while to figure out. A patient was getting recurrent throat irritation after each treatment, and I could not pinpoint the cause. The saline itself was pristine. The nebulizer was clean. Eventually I traced it to the residual volume in the cup. Older jet nebulizers leave about 1 to 1.5 mL of liquid behind after the treatment stops. That last bit becomes hyper-concentrated as water evaporates, and the patient ends up breathing in a slurry that is significantly saltier than 0.9%. The throat irritation was literally from a chloride concentration spike in those final seconds. The workaround was simple but not obvious unless you have been doing this long enough to notice the pattern. I switched to low-residual nebulizer cups and added a quick burst of compressed air through the mouthpiece at the end of the treatment to push out the remaining liquid. No more irritation. Saved me from switching that patient to a completely different treatment protocol over what amounted to a equipment issue.
When This Does Not Work
Chloride 9 Inhalation Solution is not a medication. It does not treat infections, reduce inflammation, or open airways on its own. If someone is relying on it to manage asthma or COPD symptoms without their actual prescription inhalers, that is a problem. It is supportive care at best. Useful for wetting dry airways, helping clearance of thick mucus, or as a carrier for other nebulized drugs. Not a standalone treatment for anything significant. Also, patients with cystic fibrosis or severe bronchiectasis often do better with hypertonic saline rather than the 0.9% version. The higher concentration draws more water into the airway surface liquid and improves mucociliary clearance. The 0.9% solution is too mild for those conditions and can actually feel counterproductive because it does not create enough osmotic pull. In those cases, switching to 3% or 7% saline makes a real difference. I saw this firsthand with a pulmonology shift where several CF patients complained the standard saline was barely helping them clear their secretions. Once we moved them to the hypertonic options, cough efficacy improved noticeably within the same session. Storage is another thing people ignore. Keep it at room temperature. Do not freeze it. Do not leave it in a hot car. The sterility holds up fine under normal conditions, but extreme temperatures can degrade the packaging seals over time. Clear plastic vials will also discolor if exposed to direct sunlight for extended periods. That is a quality control red flag. If the liquid looks cloudy or has particles, discard it regardless of the expiration date.