Understanding Choroid Plexus Cysts in Prenatal Imaging
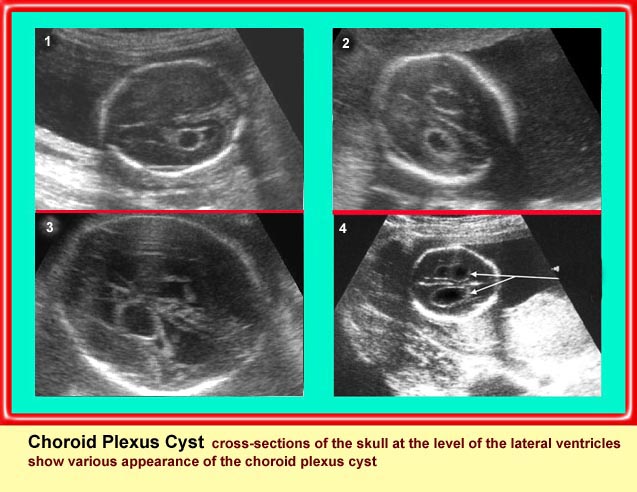
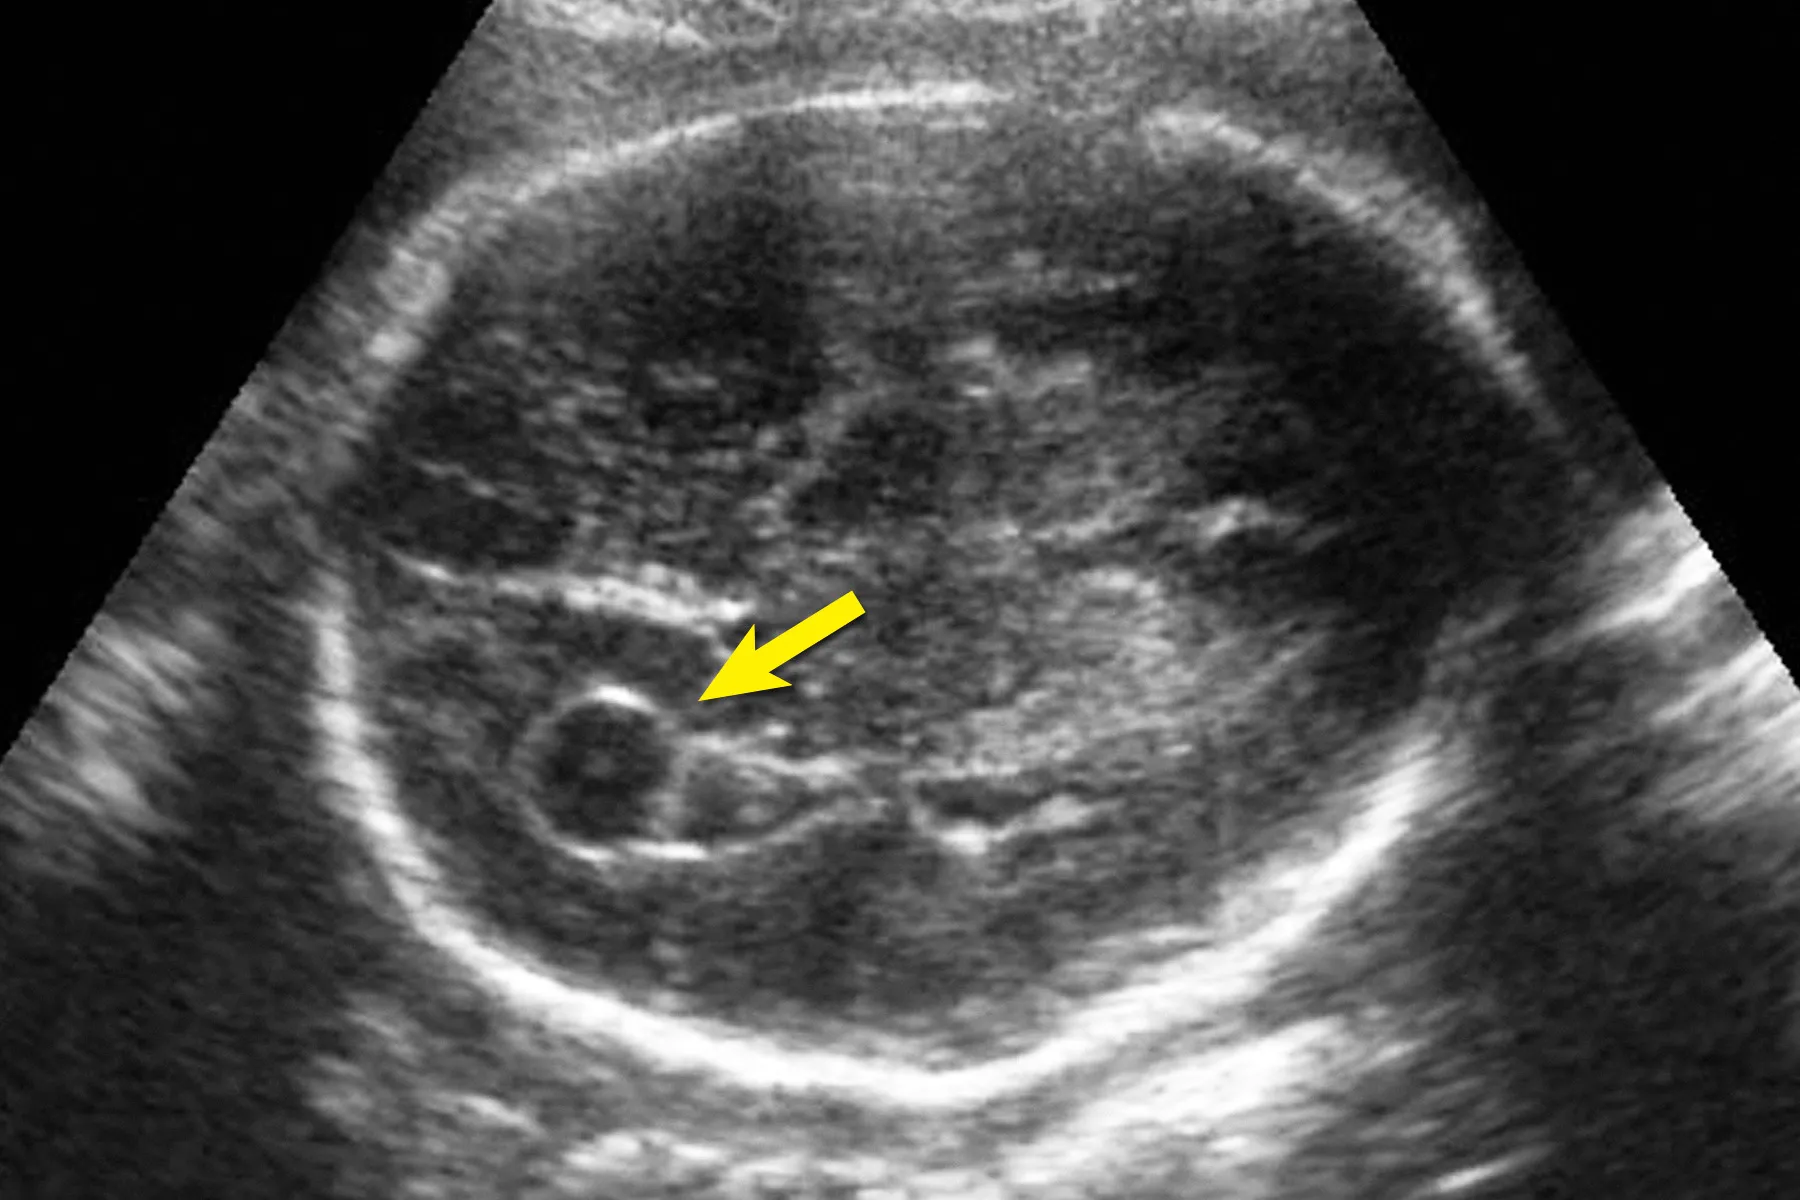
Prenatal ultrasound techs flag choroid plexus cysts (CPCs) all the time. They show up as small anechoic spots in the choroid plexus, usually between 16 and 24 weeks gestation. Most of the time, they are completely isolated and disappear on their own. That is the boring truth of it. I ran into this repeatedly during my time reading ultrasounds. One case sticks out: a Level II scan at 20 weeks showed a 4mm CPC in a fetus with no other soft markers. The parents were told to get amniocentesis. I pushed back and suggested a detailed anatomy scan plus cell-free DNA screening first. The cfDNA came back normal, the repeat scan at 24 weeks showed the cyst was gone, and they avoided an invasive procedure. Not every lab follows that logic though. Some still default to amnio just because a CPC is present.
The Choroid Plexus Cyst And Autism Connection
Let me be straight about this. The established medical literature does not support a direct link between isolated choroid plexus cysts and autism spectrum disorder. What the research actually shows is a connection between CPCs and trisomy 18 (Edwards syndrome) when they are multiple or accompanied by other structural findings. Trisomy 18 itself can have neurological sequelae, but that is a different pathway than a simple CPC. Here is what most parents don't get: an isolated CPC detected before 24 weeks resolves in roughly 90 percent of cases by the third trimester. When it resolves, there is no ongoing risk. Even persistent CPCs without additional anomalies have not been linked to later neurodevelopmental conditions like autism in longitudinal studies.
How CPCs Are Actually Evaluated in Practice
Standard workflow when a CPC is found: If the CPC is single, isolated, and found in a low-risk patient, the residual risk of an underlying aneuploidy is negligible. I have seen too many patients sent for unnecessary genetic amniocentesis because a single CPC triggered an anxiety-driven algorithm. It happens regularly in some practices. The internet connects dots that medicine does not. A parent reads about CPCs and trisomy 18, then finds studies about developmental outcomes in trisomy 18, and somehow lands on autism. The chain of reasoning is flawed but understandable under stress. What is not understandable is the number of websites selling fear disguised as information.
Get the Full Details
One counter-intuitive point: I have encountered cases where a CPC was the only sonographic finding in a fetus that later tested positive for a microdeletion on chromosomal microarray. This is rare, but it means a single CPC is not a guarantee of normal genetics, even when aneuploidy risk is low. The workaround I use is offering expanded carrier screening and cfDNA as intermediate steps before jumping to diagnostic testing, reserving amnio for cases with additional markers or abnormal screens.
What The Data Actually Says About Developmental Outcomes
Large cohort studies following children with prenatal CPCs into childhood show no difference in autism diagnosis rates compared to the general population. The base rate of autism is about 1 in 36 children. Children with isolated CPCs fall right into that number. Nothing more, nothing less. Some older papers from the late 1990s suggested a slight association, but those studies had small sample sizes and did not control for confounding variables like maternal age or concurrent aneuploidy. The methodology was not rigorous by modern standards. More recent meta-analyses have effectively closed that door.
Red Flags That Change The Equation
CPCs become clinically relevant when they appear alongside: In these scenarios, the CPC is not the problem. It is a marker that something else may be going on. The CPC itself is biologically inert. It is fluid trapped in the choroid plexus tissue, likely from normal physiological involution of that structure during fetal development. It does not cause brain damage, does not press on neural tissue, and does not interfere with development. I wish more providers would communicate this clearly. Most do not have the time or training to explain it well. They list the cyst, mention the trisomy 18 association in a vague way, and let the patient's imagination fill in the gaps. That is where the anxiety comes from, not from the cyst itself.
Practical Takeaways
If you are dealing with a CPC finding, get the full picture before making any decisions. Request a complete anatomy survey. Ask whether additional soft markers are present. Discuss cell-free DNA testing if you have not already had it. If everything else is normal and the cyst is single, you are in the high-probability resolution category. Watchful waiting is the standard recommendation, not intervention. Follow-up scans at 24 to 28 weeks confirm whether the cyst has resolved. In my experience, showing patients the actual ultrasound image and pointing out the normal appearance of the brain structures around the cyst reduces anxiety faster than any explanation I could give. Visual evidence carries weight when words do not. The Choroid Plexus Cyst And Autism association is essentially a myth built on loose interpretive chains. The science does not support it, and the clinical guidelines reflect that. Isolated CPCs are a common incidental finding. They resolve. They do not predict autism. That is the straightforward answer that most people searching this topic need to hear.