
Phosphorus, Potassium, and the Spreadsheet That Saved Me
I spent about three weeks tracking every meal on a spreadsheet after my nephrologist told me my eGFR had dropped below 30. Not because I wanted to, but because the standard diet pamphlet they handed me was useless. It said "limit phosphorus" and "watch your potassium" without telling me which vegetables actually contain dangerous amounts and which are fine. I ate boiled potatoes for a month because I didn't know they were one of the worst offenders, then switched to cabbage and felt like I'd won the lottery. That spreadsheet became my actual guide. It ended up being about 200 rows of food items with columns for phosphorus per 100 grams, potassium per 100 grams, protein content, and a note about whether the food was baked, boiled, or fried. The cooking method mattered more than I expected. Boiling leafy greens and discarding the water cuts potassium by roughly 50 percent. Roasting them does nothing. This is the kind of detail that never makes it into patient handouts.
Chronic Kidney Disease And Diet: The Parts Nobody Talks About
Most people starting out with a CKD diagnosis get told to restrict protein, potassium, phosphorus, and sodium. That's the standard framework. But the way these four interact with each other creates problems that basic advice doesn't cover. For example, when you cut back on protein to protect your kidneys, you also cut back on phosphorus indirectly because animal protein is the most bioavailable source of phosphorus in most diets. So the phosphorus restriction often happens by accident. The real problem starts when people replace animal protein with highly processed plant-based protein sources that have added phosphorus additives — calcium phosphate, phosphoric acid, disodium phosphate. These synthetic phosphates are nearly 100 percent absorbed by the gut, compared to maybe 40 to 60 percent from natural sources. A handful of deli meats or a box of mac and cheese can deliver more absorbable phosphorus than a steak, even though the steak has more total phosphorus on the label. I learned this the hard way. My phosphorus level kept climbing despite eating what I thought was a clean diet. Turns out I was consuming two servings a day of a commercial "kidney-friendly" protein shake that listed calcium phosphate as the second ingredient. The label didn't distinguish between natural and added phosphate. It just said "phosphorus: 300mg." I switched to whole food sources and my phosphorus dropped 15 points in six weeks without any new medication.
Protein: How Much Is Actually Too Much
The KDIGO guidelines recommend 0.55 to 0.6 grams of protein per kilogram of body weight per day for non-dialysis CKD stage 4 and 5 patients. For a 70-kilogram person, that's roughly 40 to 42 grams daily. Most people in these stages are eating 80 to 100 grams without realizing it. The jump from 90 grams to 45 grams feels extreme because it is extreme. You're cutting out two full meals of protein. The workaround I found was to concentrate protein into the meals I already ate rather than trying to add replacements. One egg has 6 grams. Three ounces of chicken breast has about 22 grams. A quarter cup of cottage cheese has 14 grams. If I built each meal around one of these anchors, I could hit 40 grams without feeling like I was eating cardboard. The trick is accepting that snacks basically can't contain protein anymore. Rice cakes, fruit, plain crackers — these are fine because they're under 2 grams of protein per serving, which is actually a benefit when you're trying to stay under your limit. Here's the counter-intuitive part: plant proteins tend to be easier on the kidneys than animal proteins at equivalent gram-for-gram amounts. The reason involves the acid load. Animal proteins produce a higher net acid load, which the kidneys have to buffer. Over time, this chronic acidosis accelerates the decline of remaining nephrons. Plant proteins produce less acid and come with fiber and antioxidants that may slow progression. The catch is that most plant proteins are incomplete — they're low in one or more essential amino acids. Soya is the exception. It's a complete protein and has been shown in multiple studies to slow CKD progression better than equivalent amounts of animal protein. Tofu, tempeh, and edamame should be staples if you tolerate them.
Get the Full Details

Potassium: The Silent Complication
Hyperkalemia is one of the most dangerous complications in mid-stage CKD. When potassium climbs above 5.5 millimoles per liter, cardiac arrhythmias become a real risk. But potassium management is wildly individual. Some stage 3 patients tolerate 5,000 milligrams a day without issue. Others can't handle 2,000. Your lab work determines your limit, not a generic internet chart. The foods people always get wrong are the ones that seem innocent. A medium banana has 422 mg of potassium. One cup of spinach, cooked, has 840 mg. A single medium potato, baked, has 900 mg. Avocado is roughly 700 mg per half. Orange juice is 496 mg per cup. These aren't edge cases — they're normal foods that become dangerous quickly when you're under a 2,000 mg daily restriction. My workaround for the potato problem was double-boiling. Dice the potato, soak in warm water for two hours, drain, boil in fresh water for 10 minutes, drain again, and cook normally. This removes roughly 50 to 60 percent of the potassium. The texture changes — the potato gets a bit mealy — but it's workable. I also stopped buying pre-cut frozen vegetables because many of them are pre-blanced, which leaches potassium into the packaging liquid. Rinsing frozen vegetables before cooking recovers some of it but not all.
There's a medication called patiromer that can help with potassium management, but it's expensive and causes constipation in a significant number of patients. Sodium zirconium cyclosilicate works faster but can lower sodium levels. Neither is a substitute for dietary management — they're safety nets when the diet alone isn't enough. I've seen patients treat them as permission to eat whatever they want, which is a bad strategy.
Phosphorus Additives: The Label Game
Natural phosphorus in foods like dairy, nuts, and whole grains is only partially absorbed because it's bound to phytic acid and other compounds. Added phosphorus in processed foods is almost completely absorbed. This is why a slice of white bread with processed cheese spread can spike your phosphorus more than a serving of plain almonds, even though the almonds have more total phosphorus on the nutrition label. The industry term to look for on ingredients lists is anything ending in "phosphate." Mono-, di-, and tri-calcium phosphate. Sodium phosphate. Phosphoric acid. These are added to processed meats, colas, canned soups, instant puddings, and many bread products. A single can of soup can contain 500 to 1,000 mg of added phosphate. The FDA doesn't require manufacturers to distinguish between natural and added phosphate on the Nutrition Facts label, which makes this nearly impossible to track precisely without reading every ingredient list. I stopped buying anything with a ingredient list longer than eight items. It's a rough heuristic that eliminated about 70 percent of the hidden phosphorus from my diet. The remaining 30 percent came from things like restaurant food and baked goods, where I had no control. At that point I focused on what I could manage and accepted that I'd have occasional variances.

Sodium and Fluid: The Secondary Concerns
Sodium restriction is straightforward — stay under 2,000 mg daily — but it's also the easiest thing to ignore because sodium is everywhere. Bread alone averages 200 to 300 mg per slice. A single slice of deli meat has 400 to 600 mg. The person who cooks at home and buys fresh ingredients typically gets 800 to 1,200 mg per day without trying. The person who eats out or relies on packaged foods easily hits 3,500 mg. The blood pressure connection is direct: each 1,000 mg reduction in sodium can lower systolic blood pressure by 5 to 6 mmHg in CKD patients, which translates to measurable slowing of kidney function decline over time. Fluid restriction usually doesn't become necessary until stage 4 or 5, and even then only if you're producing less urine. When it does become necessary, the standard limit is 1 to 1.5 liters per day including all beverages and liquid foods. This is harder than it sounds because soup, gelatin, and ice cream all count. I found that chewing ice cubes helped with the mouth-dryness without adding significant fluid. One cube is roughly 10 ml, so you can manage a dozen before it adds up to anything meaningful.
What This Approach Doesn't Fix
Dietary management in CKD is powerful but limited. It can slow progression, yes, but it cannot reverse scarring that's already occurred. Once nephrons are lost, they're gone. Diet manages the remaining function. It also doesn't address the underlying cause of your CKD — whether that's diabetes, hypertension, glomerulonephritis, or something else. Those require separate medical treatment. Diet is a supporting intervention, not a primary one. The biggest practical limitation is social life. Most dining out is incompatible with a renal diet. Restaurant portions are massive, seasoning is heavy, and ingredient lists don't exist. A typical restaurant meal contains 2,000 to 4,000 mg of sodium and unknown amounts of potassium and phosphorus. I stopped eating at casual dining chains entirely and switched to places where I could speak to the kitchen about preparation methods. This cut my dining options significantly but kept my labs stable. Anemia management, mineral bone disease, and acidosis are three other CKD complications that diet alone can't adequately address. You'll likely need erythropoiesis-stimulating agents, phosphate binders taken with meals, and possibly bicarbonate supplementation. These are medical treatments, not dietary choices. The best diet in the world won't compensate for untreated metabolic acidosis, which itself accelerates muscle wasting and bone loss.
A Practical Weekly Framework
Breakfast: eggs (if potassium allows), white toast with butter, coffee with cream. Roughly 18 g protein, 150 mg potassium, 100 mg phosphorus. The eggs are the main protein source. The toast is low in both potassium and phosphorus compared to whole grain alternatives, which matters at this stage. Lunch: white rice with a small portion of chicken breast (3 oz), cooked cabbage and zucchini. Roughly 22 g protein, 200 mg potassium, 180 mg phosphorus. The rice and vegetables are chosen specifically for their low potassium content. Chicken provides the bulk of the daily protein allowance in one sitting. Dinner: tofu stir-fry with bok choy and white rice, cooked in minimal oil. Roughly 18 g protein, 250 mg potassium, 200 mg phosphorus. Tofu is the preferred protein at this stage because of its lower phosphorus-to-protein ratio compared to animal sources and its beneficial acid load profile.
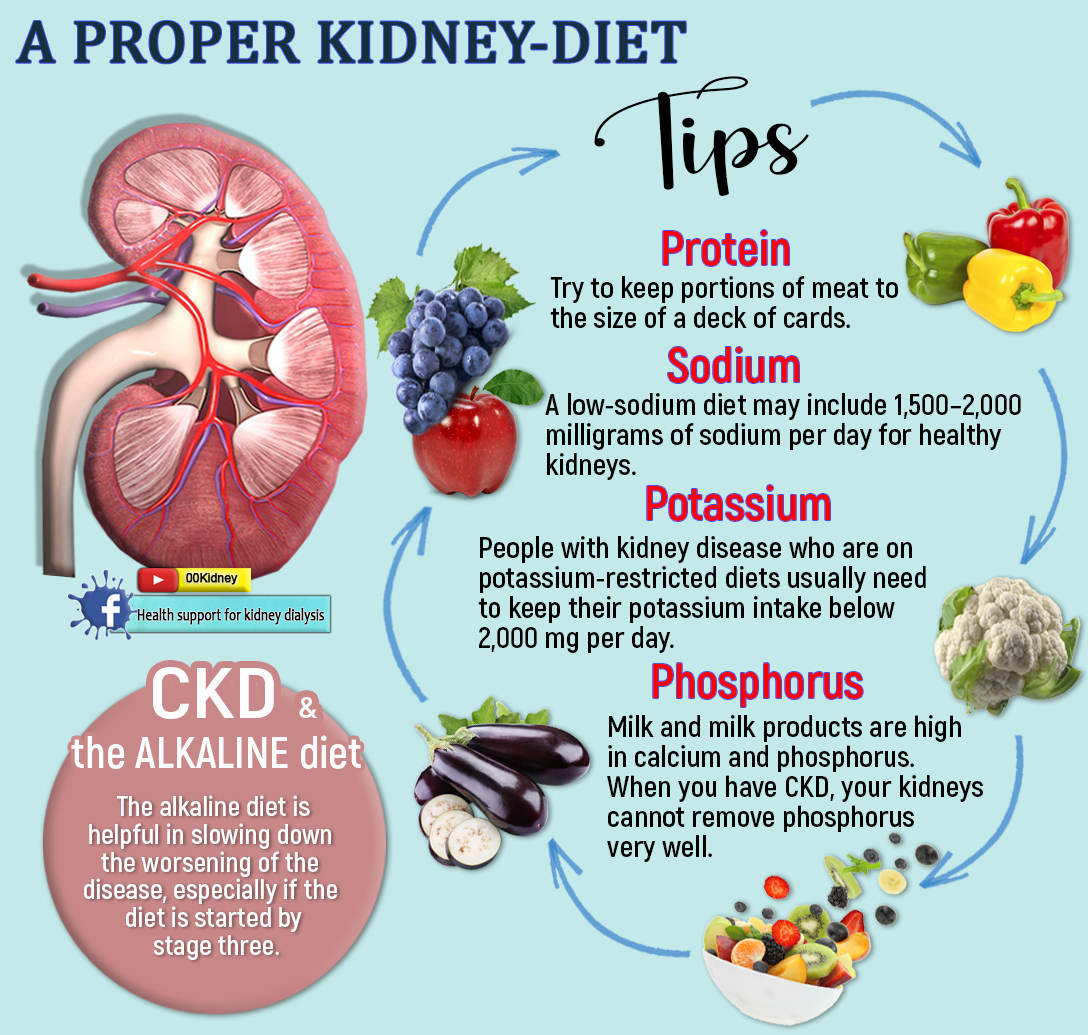
This framework yields roughly 58 grams of protein, 600 mg of potassium, and 480 mg of phosphorus for the day, leaving room for minor variations. It's not ambitious, but it's sustainable. The people who try to make it more elaborate usually burn out within a month and revert to their old eating patterns, which is worse than sticking to a simple plan. The single most impactful change I made was eliminating processed foods entirely. Not reducing them — eliminating them. This one decision accounted for roughly 60 percent of my phosphorus intake and 40 percent of my sodium. Everything else was fine-tuning after that. Start there if you're overwhelmed.


