
Managing Chronic Renal Failure Through Diet
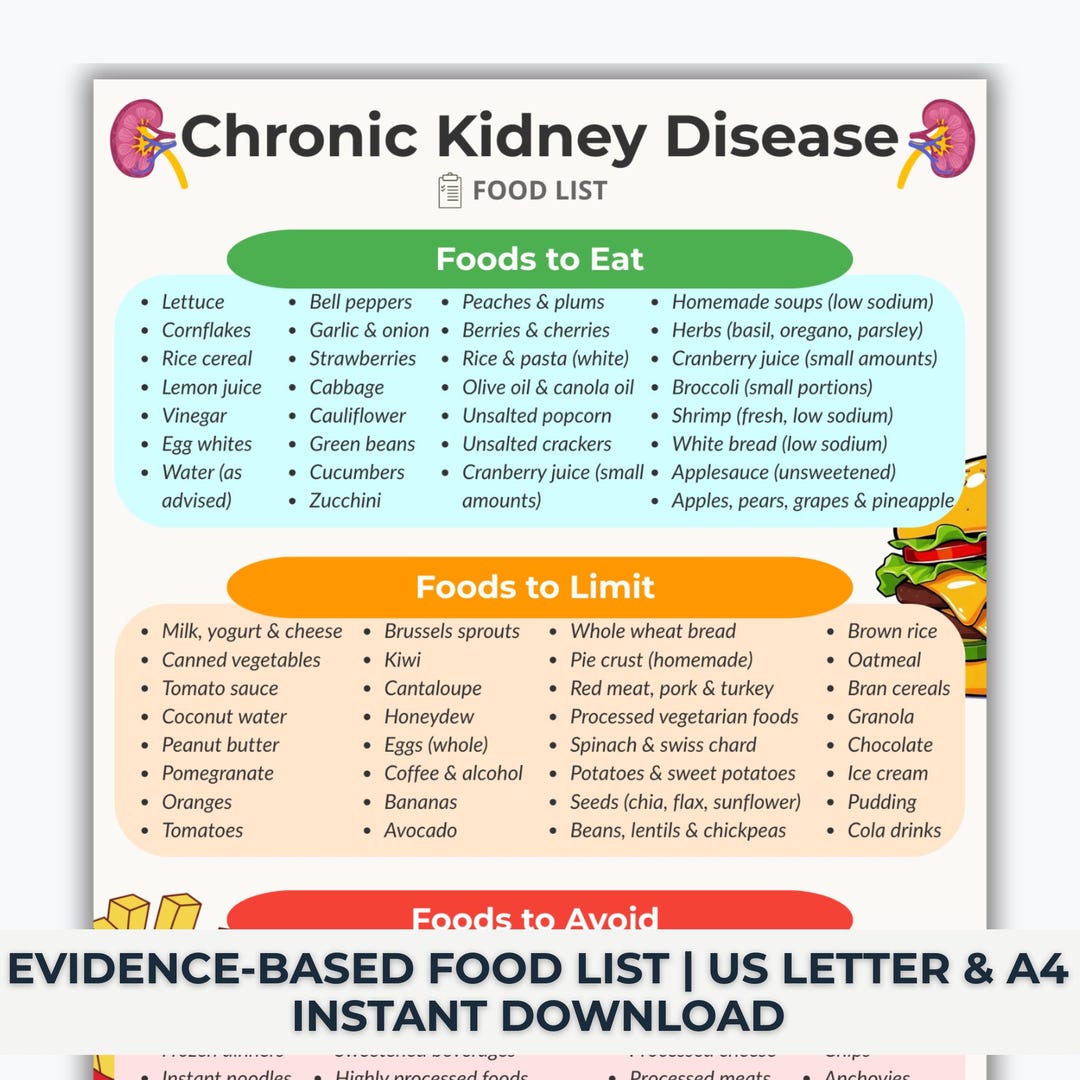
The diet for advanced kidney disease comes down to four main restrictions: potassium, phosphorus, sodium, and protein. Most patients struggle with potassium first because it hides in places people don't expect. A single large banana has about 960 milligrams. Two medium baked potatoes have roughly 1,300 milligrams between them. The standard target for someone with stage 4 or 5 CKD is under 2,000 milligrams per day, sometimes lower depending on blood work. Phosphorus is the second common problem area. Dairy, nuts, seeds, and dark colas are the usual suspects. But the more dangerous source is phosphate additives in processed foods. The body absorbs about 90 to 95 percent of added phosphates compared to only 40 to 60 percent from natural sources. Reading ingredient lists for anything with "phos" in the word — phosphate, phosphoric acid, pyrophosphate — will catch most of the problem. Many patients don't realize this distinction until their phosphorus levels stay high despite avoiding cheese and milk.
Practical Chronic Renal Failure Diet Plan Considerations
Sodium restriction typically lands somewhere between 1,500 and 2,000 milligrams daily. This isn't just about avoiding the salt shaker. A single cup of canned soup can contain 800 to 1,200 milligrams. Bread, deli meat, and frozen dinners are also major contributors. The reason this matters goes beyond blood pressure. Excess sodium drives thirst, which leads to fluid overload, which means more restrictive fluid allowances and more swelling and shortness of breath between dialysis sessions for those already on treatment. Protein is where things get complicated and where most guidelines cause confusion. In pre-dialysis CKD stages 3 through 5, the recommendation is actually to restrict protein to roughly 0.5 to 0.6 grams per kilogram of body weight. This slows the accumulation of uremic toxins and delays the need for dialysis. A 70-kilogram person would be eating around 35 to 42 grams of protein per day. That is very little. Most people find it difficult to maintain muscle mass at that level without careful planning. Once dialysis starts, the recommendation flips completely. Hemodialysis and peritoneal dialysis both strip amino acids and small peptides during each treatment. The KDOQI guidelines call for 1.0 to 1.2 grams per kilogram daily for dialysis patients. Going from a restrictive pre-dialysis diet to a higher protein target after starting treatment requires a deliberate shift that many patients and even some clinicians miss. Staying at the old low-protein numbers after dialysis begins accelerates malnutrition and muscle wasting, which is a significant predictor of hospitalization and mortality in this population.
I worked with a patient who came off dialysis temporarily due to a transplant workup and stayed on the higher protein intake out of habit. Within three months her nitrogen balance was positive, her albumin improved, and she felt substantially stronger. When she returned to the lower pre-dialysis target after the transplant evaluation paused, she noticed fatigue returning within weeks. It was a clear demonstration that these numbers aren't abstract — they change based on where you are in the disease trajectory.
Get the Full Details

Vegetable Management and the Leaching Question
High-potassium vegetables don't have to be eliminated entirely if you know how to prepare them. Soaking sliced potatoes in warm water for at least two hours and boiling them in a large volume of water removes roughly 50 to 60 percent of the potassium. The same technique applies to sweet potatoes, carrots, and beets to some degree. Leafy greens like spinach and Swiss chard are harder to manage this way because the potassium is distributed throughout the leaf structure, and boiling them concentrates what remains into the cooking water, which most people don't drink anyway. The counter-intuitive part is that leaching works best for root vegetables and worst for mushrooms and tomato-based products. A cup of cooked mushrooms has about 840 milligrams of potassium, and leaching removes very little of it. Tomato paste and sauce are concentrated sources — half a cup of tomato paste contains roughly 800 milligrams. Many patients who successfully manage potassium through vegetable modification still get surprised by red sauce and mushroom dishes because those sources don't respond to the same prep techniques. Here is something I ran into repeatedly that isn't well documented in patient handouts. Patients who leach all their vegetables tend to lose water-soluble vitamins along with the potassium. Vitamin C and B-complex vitamins leach right out with the potassium. Over months, this can create a secondary deficiency on top of the usual renal vitamin issues. I started recommending that patients leach only the highest-risk vegetables — potatoes, sweet potatoes, squash — and leave lower-potassium options like bell peppers, cabbage, and onions mostly unmodified. It keeps the diet more nutritionally complete while still staying under the potassium target. It also makes the food actually taste better, which sounds trivial but matters enormously for long-term adherence.
Fluid Management and Hidden Sources
Fluid restriction is usually between 1,000 and 1,500 milliliters per day for dialysis patients, or for non-dialysis patients who have developed significant fluid retention. The challenge is that fluid isn't just what you drink. Ice cream, gelatin, soups, and high-water-content fruits like watermelon and oranges all count toward the daily limit. A half-cup of ice cream is roughly 120 milliliters of fluid. A bowl of oatmeal prepared with water instead of milk adds another 240 milliliters that people often forget to log. Salty food makes thirst worse, which creates a cascade. More sodium leads to more drinking, which leads to more interdialytic weight gain, which means more aggressive ultrafiltration during dialysis, which increases the risk of cramping, hypotension, and cardiac stress. It is a compounding problem. Controlling sodium is effectively a fluid control strategy even when the diet sheet lists them as separate items.
Supplements and What to Avoid
Multivitamins for kidney disease exist, and they are generally recommended because the restricted diet plus dialysis-related losses create gaps. The renal-specific formulas like or Renvela multivitamin variants are formulated without the fat-soluble vitamins in excess amounts that could accumulate. Standard over-the-counter multivitamins may contain vitamin A levels that build up to toxic ranges when kidney function is severely reduced. This is one of the few places where the "more is better" assumption is actually dangerous. Potassium supplements and salt substitutes containing potassium chloride are contraindicated in almost all CKD stages 4 and 5. Salt substitutes sound like a sodium reduction strategy but they replace sodium with potassium in roughly equal molar amounts. A single teaspoon can deliver 500 to 700 milligrams of potassium. Patients who use these substitutes without adjusting their diet often present with hyperkalemia emergencies. This is a preventable situation that shows up in the ER regularly.
When the Diet Doesn't Work Anymore
There is a limit to what diet can do. Once potassium consistently runs above 5.5 despite dietary restriction, phosphate binders and sequestrants become necessary regardless of how well the diet is followed. Dietary modification alone cannot overcome impaired excretion when GFR drops below 15 in most cases. The diet helps reduce the load, but it cannot replace renal function. Some patients resist medications because they want to control things through food alone, and that is understandable, but it is important to be direct about the ceiling of what diet can achieve at this stage. Another practical limitation is social and economic. Fresh low-potassium vegetables, lean proteins, and specialty renal formulas cost more and require more storage and preparation time than processed alternatives. A patient working two jobs and cooking for a family on a tight budget will not sustain a perfect renal diet. The goal is reasonable adherence, not perfection. Missing a target here and there over a month is far less harmful than burning out completely and abandoning the plan altogether. Tracking intake using an app or a simple notebook for the first two weeks gives you actual data instead of guesses. Most people significantly underestimate how much potassium and phosphorus they are consuming. Once you see the numbers, the adjustments become concrete rather than abstract. That is usually the turning point where the diet stops feeling like a list of restrictions and starts functioning as a practical tool.



