Clavicle Fracture Rehab Is Not What Most People Expect
Most people who deal with clavicle fractures end up with chronic shoulder stiffness, weak rotator cuff mechanics, and scapular dysfunction that never fully resolves. This happens because the standard advice is essentially to wait until the bone heals and then figure out the shoulder later. By that point, months of disuse have already caused adhesive changes and motor control patterns to degrade. The reality is that Clavicle Fracture Physical Therapy is a structured process that needs to begin almost immediately after the injury stabilizes, but most patients don't receive clear instructions on what that actually looks like. I've worked with enough of these cases to know that the difference between a full recovery and a chronic problem often comes down to one specific detail: how well the scapula is being retrained to move again.
Clavicle Fracture Physical Therapy: The Practical Breakdown
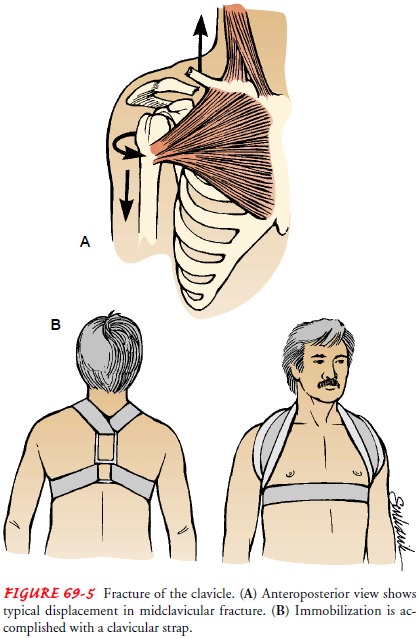
Let me be direct about the timeline. A mid-shaft clavicle fracture, which is the most common type, follows a rough healing curve. Weeks one through two are about protection and pain management. The fracture is unstable, callus formation hasn't started yet, and the priority is keeping inflammation under control. During this phase, you're doing very little beyond finger walking, wrist motion, and maybe a small amount of pendulum movement if your clinician clears it. Some protocols are even more conservative than that. Weeks three through six mark the soft callus stage. This is where the actual rehab work begins in earnest. Once there is enough biological healing happening that the bone can tolerate gentle stress, you move into active range of motion. The goal here is restoring glenohumeral mobility without putting dangerous load on the fracture site. You're working on forward flexion, external rotation within a safe arc, and initiating scapular retraction and depression drills. By weeks six through twelve, you should have enough callus consolidation to start introducing light resistance and progressive loading. This is the strengthening phase, and it is where most people make mistakes because they either rush it or don't progress systematically enough. The bone is still remodeling and will continue to do so for up to a year, but the tissue should handle controlled mechanical load at this point.
After twelve weeks, if healing has progressed normally, you transition into functional training and sport-specific or work-specific drills. Full return to impact activities or heavy overhead lifting can take anywhere from four to eight months depending on the individual and the severity of the original fracture. Here is something that tends to surprise people. The scapulothoracic rhythm is almost always disrupted after a clavicle fracture. The clavicle serves as a strut that positions the scapula in space relative to the rib cage. When it is fractured, the whole chain of muscular control around the scapula shuts down partly due to pain inhibition and partly due to neural adaptation. You can restore full shoulder flexion through sheer effort, but if the scapula is not tracking properly, overhead movements will remain painful and mechanically inefficient. This is not optional to address. It is the central problem. I ran into a particularly stubborn case a few years back with a patient who had a healed mid-shaft clavicle fracture and absolutely no bony tenderness anymore. Range of motion was technically full. He could lift his arm above his head without complaint. But he could not hold a proper push-up position and his serratus anterior was essentially offline. His scapula winged aggressively during any resisted protraction. Every standard scapular stabilization drill I had him do was failing because his brain had not re-established the motor pattern. He was literally unable to fire the serratus correctly despite the muscle being anatomically intact.
Get the Full Details
The workaround was surprisingly simple but took about three weeks of consistent repetition before I saw the change. I stopped giving him traditional rows and scapular retractions and instead had him do wall slides with a towel wrap around his upper arms, keeping constant light contact with the wall throughout the entire movement. The constraints forced his scapula to stay in contact with the thorax while he actively worked through the scapular upward rotation and posterior tilt pattern. Within two weeks he could hold a modified push-up against the wall without any winging. Within three weeks, floor push-ups were clean. The muscle was never the issue. The neuromuscular connection was. This is worth emphasizing because it is a common pitfall in rehabilitation programs. Clinicians and patients focus entirely on restoring passive and active range of motion in the glenohumeral joint while ignoring the scapular stabilizers. You can end up with a shoulder that moves through the full arc but does so with poor biomechanics, leading to subacromial impingement patterns, rotator cuff overload, and recurrent pain. The scapula needs targeted retraining with specific exercises, not just general shoulder mobility work. Another counter-intuitive point that rarely gets discussed is the role of pectoralis minor tightness after clavicle fractures. Patients spend weeks in a sling with their arm adducted and internally rotated. The pec minor shortens and becomes hypertonic. When they finally start mobilizing the shoulder, this tight muscle pulls the scapula into excessive protraction and anterior tilt, which directly interferes with normal scapulothoracic mechanics. Stretching the pec minor early in the rehabilitation process, before aggressive strengthening, often makes a noticeable difference in how smoothly the scapula moves during overhead activities.
There are also cases where physical therapy hits a ceiling and no amount of exercise will solve the underlying issue. If a clavicle fracture heals with significant shortening, say more than one and a half to two centimeters, the lever arm mechanics of the entire shoulder girdle change. Deltoid abduction efficiency drops, and the patient may simply lack the mechanical advantage to perform overhead tasks effectively regardless of how well they rehab. In these situations, continuing aggressive physical therapy without addressing the structural problem is largely wasted effort. Surgical consultation with an orthopedic specialist familiar with clavicle reconstruction or possible osteotomy may be the more appropriate next step. Another limitation of physical therapy approaches is that they assume a relatively predictable healing trajectory. In reality, certain patient populations heal slowly. Smokers take significantly longer to form callus. Patients with diabetes, osteoporosis, or nutritional deficiencies may have delayed union. Starting an aggressive loading protocol too early in these cases can actually disrupt the healing process rather than support it. Follow-up imaging and clinical assessment should dictate progression, not an arbitrary calendar. For patients who went through surgical fixation with a plate and screws, the early phase is somewhat more protected, which allows motion to begin sooner in some cases. But the principles remain the same. The hardware does not fix the neuromuscular deficit. It just provides a stable environment for the rehab to proceed. Scapular control, pec minor mobility, and gradual progressive loading are still the critical components.
One practical note on the strengthening phase. Isometric exercises are genuinely useful early on because they activate the musculature without creating shear forces across the healing bone. A simple isometric shoulder abduction press against a wall, held for thirty seconds and repeated several times, can maintain muscle activation during the transition period. It is not glamorous but it is effective and low risk. As you move into more dynamic strengthening, external rotation and scapular retraction with resistance bands are foundational. The rotator cuff, especially the infraspinatus and teres minor, tends to atrophy rapidly after this type of injury and needs dedicated attention. Skipping this step and jumping straight into heavier compound movements is a common error that leads to shoulder impingement symptoms down the line. The timeline I described is a general framework. Individual protocols vary based on fracture displacement, whether surgery was performed, patient age, and underlying health factors. The key takeaway is that passive waiting is not a rehabilitation strategy. Active, progressive, and specifically targeted therapy beginning as soon as the bone allows is what separates a full recovery from a lifetime of shoulder dysfunction. Most patients who follow through on the scapular work and don't skip the early stages end up with outcomes that are substantially better than the statistics suggest.