A Working Guide to the Co-OP Approach in Occupational Therapy
Most people who first hear about the Co-OP model assume it is just another activity-based intervention. It is not. It is a problem-solving framework that changes how an occupational therapist thinks about treatment from the first session, and it changes what the client brings to each session. I have used it with children, adults, and seniors across outpatient clinics, schools, and home care settings. It works well when you respect its structure. It falls apart quickly when you treat it as a flexible vibe rather than a defined protocol. The Co-OP, short for Cognitive Orientation to daily Occupational Performance, was developed by Carol Missiuna and Winnie Dunn at Western University. It is an evidence-based, client-centered occupational therapy approach that targets the cognitive strategies people use when learning and performing daily tasks. The core idea is simple: people do not struggle because they lack strength or coordination alone. They struggle because they lack a reliable internal process for figuring out how to approach a new or difficult activity. The method centers on the Plan-Do-Check cycle. Before any task begins, the client plans what they will do and predicts what might go wrong. During the task, they execute while staying aware of their own thinking. Afterward, they check whether their plan worked and adjust. This is not a one-time exercise. It is repeated across many different activities until the cognitive strategy becomes automatic.
What makes Co-OP distinct from other OT approaches is the heavy emphasis on verbal self-guidance. The therapist teaches the client to talk through each step using phrases like "What is my goal?" "What do I need?" "Let me try this." Over time, that external chatter internalizes into silent problem-solving. That is the whole point. The therapist is not teaching a specific motor skill. The therapist is teaching the meta-cognitive habit of approaching unfamiliar tasks with a structured plan.
How It Works in Practice
I started every Co-OP session the same way. I asked the client what they actually wanted to be able to do. Not what insurance would cover. Not what looked good on a care plan. What they wanted. This matters more than most new therapists realize. Co-OP is inherently client-driven, and if the goal is not genuinely meaningful to the client, the Plan-Do-Check cycle becomes a mechanical exercise that produces no carryover. From there, I broke the goal into observable steps and worked through them one at a time. For example, a child struggling with handwriting did not get general fine motor exercises. We sat down and picked one specific goal: writing their name legibly on a lined page. I asked them to plan how they would do it. They said they would hold the pencil and write slowly. We tried it. They wrote the name. We checked. The letters were too large and uneven. I did not immediately correct them. I asked what they noticed. They said they did not look at the lines between the letters. That single moment of self-assessment is the entire model in action. The trick most people miss is the ratio of therapist talk to client talk. In a standard pediatric OT session, the therapist might speak sixty percent of the time. In a Co-OP session, the therapist should speak less than thirty percent. You are not instructing. You are scaffolding their thinking. If you find yourself explaining how to do the task, you have already failed the method.
Get the Full Details

Another practical detail that people overlook is the importance of the visual workspace. The client needs to see both their plan and their product simultaneously. I always made sure the goal sheet, the planning worksheet, and the completed attempt were all visible on the table. When the workspace was cluttered or the plan was hidden in a folder, the Check phase collapsed because the client could no longer compare their intention with their outcome.
Edge Cases and What Happens When the Model Stretches
Co-OP was originally designed for typically developing children with developmental coordination disorder and kids with mild learning differences. The research base is strongest for ages six to twelve. I have pushed it into other populations, and some adaptations work while others do not. I ran into a specific problem with a nonverbal adolescent with autism who had significant expressive language delays. The Plan-Do-Check cycle requires verbal self-guidance, and this client could not produce the necessary phrases. I initially tried substituting picture cards for each step of the plan, but the process became so slow that motivation dropped within three minutes. The workaround was to use a tactile sequencing system instead. I gave him small blocks representing each step of the task. He arranged them physically before attempting the activity. The Plan phase became a motor arrangement rather than a verbal one. It was slower than I would have liked, but it gave him the same cognitive structure. I documented this deviation carefully and adjusted the fidelity rating accordingly. With older adults recovering from stroke, another issue emerged. Some clients had severe apraxia and could not access the motor plan even when they understood the strategy cognitively. Co-OP assumes a baseline of motor execution ability. When that baseline is impaired, the cognitive scaffolding has nothing to build on. In those cases, I shifted to a modified approach that combined Co-OP principles with constraint-induced movement therapy elements. The planning and checking remained, but the execution support changed significantly. I am honest about this limitation in my documentation and with referral sources.
Common Pitfalls That Ruin a Co-OP Session
The first pitfall is goal selection. New therapists often pick goals that are too broad. "Improve handwriting" is not a Co-OP goal. "Write my full name on a lined sheet without prompting" is. Vague goals produce vague planning and vague checking. The specificity of the goal directly determines the effectiveness of the entire cycle. The second pitfall is premature independence. Co-OP trains clients to eventually need less therapist support, but that transition has to be gradual. I have seen therapists pull back too quickly and expect the client to self-direct the Plan-Do-Check without any prompting. Most clients cannot do this yet. The fading of therapist prompts should happen over weeks, not sessions. I typically use a prompt hierarchy that moves from verbal cues to visual cues to independent execution, and I track which level each client is at for each activity. The third pitfall is treating Check as a passive review. Check is not the therapist telling the client whether they did it right. Check is the client evaluating their own performance against their original plan. If the therapist is doing the evaluating, the model breaks. I have caught myself doing this multiple times, especially when a client seemed stuck. The correct move is to ask questions, not give answers. "What did you notice?" works better than "You forgot to look at the lines."

Implementation and Documentation
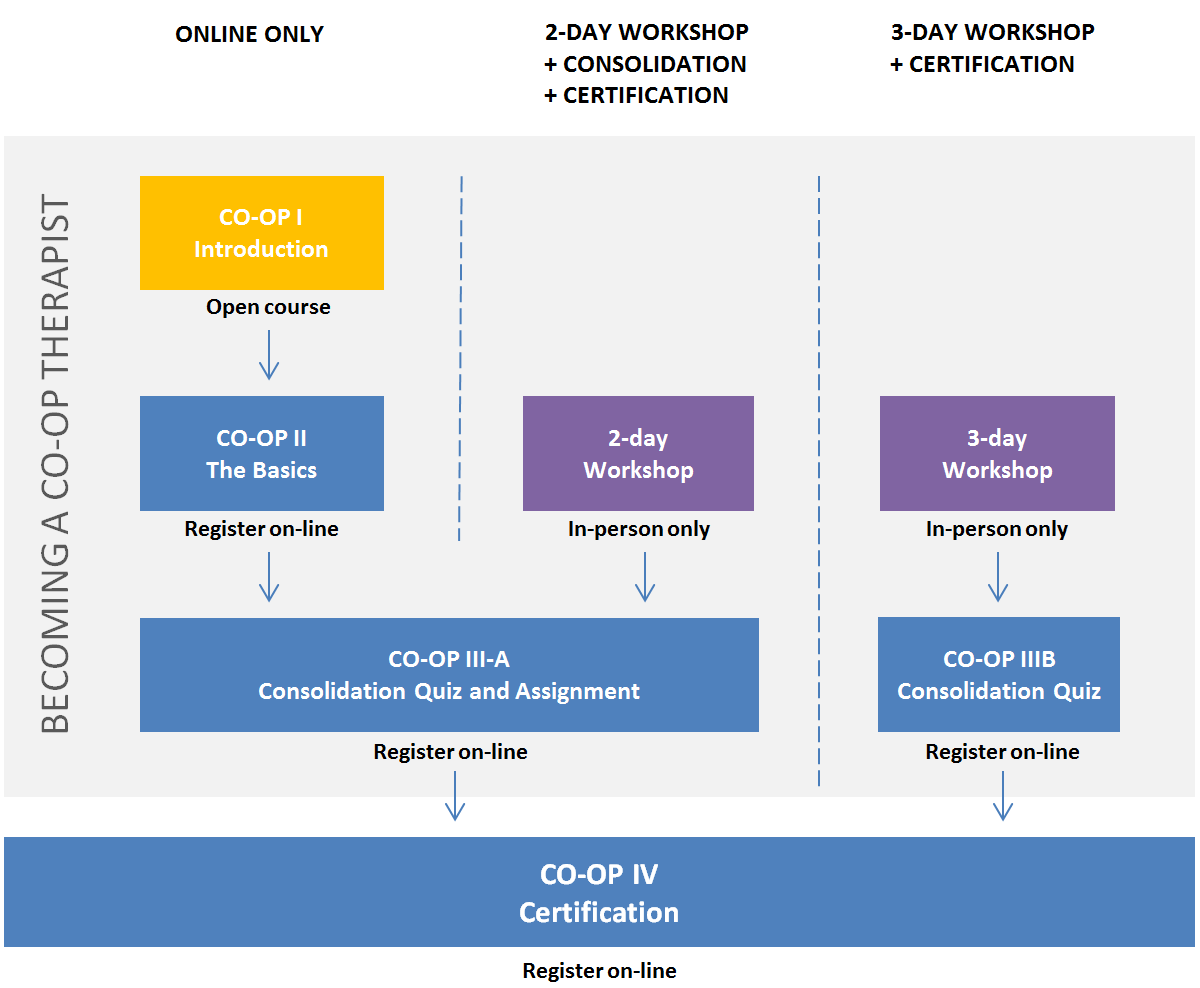
If you want to use Co-OP in your practice, you need formal training. The Co-OP Certified Practitioner program requires a documented number of direct therapy hours using the model, supervised case reviews, and a fidelity assessment. Skipping the certification and attempting Co-OP based on a workshop alone will produce inconsistent results. I learned this the hard way after my first year of trying to adapt the approach without proper supervision. My documentation was sloppy, my fidelity ratings were inconsistent, and my client outcomes did not improve past baseline. For documentation, Co-OP requires tracking the goal, the plan the client generated, the execution, the client's self-assessment during Check, and the carryover to other contexts. Standard SOAP notes do not capture this well. I switched to a modified format that includes a separate Plan-Do-Check field for each session. It takes about two extra minutes per note but makes the progress data much clearer for interdisciplinary teams and insurance reviews.
Co Op Model Occupational Therapy: Who It Helps and Who It Does Not
Co-OP has strong evidence for children with DCD, mild cerebral palsy, and specific learning disabilities affecting daily performance. It has emerging evidence for traumatic brain injury and early-stage dementia in adult populations. It does not have strong evidence for acute psychiatric conditions, severe intellectual disability, or advanced neurodegenerative disease where cognitive scaffolding itself is the primary deficit. In those cases, environmental modification or compensatory strategy training may be more appropriate. Co-OP is not a universal solution. It is a specific tool for a specific type of problem. The method also depends on the client having sufficient working memory and attention to engage in the planning and checking phases. Clients with significant attention deficits may benefit from shortened sessions or heavy environmental structuring before the cognitive component can be introduced effectively. I typically assess cognitive capacity separately from motor capacity and adjust the pacing accordingly. This usually means the first two to three sessions are spent on cognitive readiness rather than task performance. I have found that Co-OP integrates reasonably well with other models when used properly. Pairing it with sensory integration strategies for clients who also have sensory processing challenges is common and effective. Combining it with task-oriented training for neurological populations requires more careful sequencing. The cognitive piece must come first in those cases, or the motor repetition overrides the problem-solving component and the client reverts to old patterns.
The model is also surprisingly compatible with telehealth delivery, though with caveats. Remote Co-OP sessions require the client to have a organized workspace at home and someone available to assist with setup. The Plan-Do-Check cycle is still feasible, but the therapist loses some observational data that is normally picked up from proximity. Video quality and camera angle matter more than you would expect. I recommend a fixed camera position that captures the client's hands and the workspace throughout the session. Cost and time are real constraints. A full Co-OP intervention typically runs eight to twelve sessions per goal, with weekly frequency, and each session lasts forty-five to sixty minutes. That is not trivial in most healthcare systems. Reimbursement varies by region and payer. Some insurers recognize Co-OP under standard occupational therapy codes. Others require additional justification. I always verify coverage before starting the intervention and document the evidence base clearly in prior authorization requests. This usually prevents denial disputes later. The model demands consistency across providers. If a client sees multiple therapists, they need to receive the same Co-OP framework from everyone. In school-based settings, this often means coordinating with the classroom teacher and related service providers. I have seen Co-OP fail in those environments simply because the classroom staff was not reinforcing the same planning language. A brief training session for support staff costs about twenty minutes and dramatically improves outcomes.
There is also the question of client buy-in. Some clients, particularly adolescents, resist the structured nature of the approach. They perceive it as childish or overly simplistic. I address this by framing it explicitly as a problem-solving tool used by athletes and surgeons, not as a therapy exercise. How you present the model in the first session influences engagement for the entire duration. It is a small thing that most therapists do not think about until they see a client disengage. Overall, Co-OP is a reliable method when applied correctly, and it produces measurable improvements in task performance and independence. It is not easy to implement well, and it is not appropriate for every client or every setting. The training investment is real. The fidelity requirements are strict. But for the right population with the right goals, it changes how a client approaches difficulty in ways that standard motor-based interventions do not.