How to Actually Run a Couple Through a CBT Framework
The first session with a couple where both people are convinced the other is the problem is exhausting. They will talk past each other. They will interrupt. They will reframe every statement into evidence against the other person. If you try to be empathetic to both sides in the traditional narrative therapy way, you end up with two parallel monologues and zero progress. I stopped doing that years ago. Cognitive Behavioral Conjoint Therapy (CBCT) takes standard CBT protocols and applies them directly to the dyad. Instead of individual cognitive restructuring followed by couples work, you do the cognitive work in the room with both people present. The target behaviors are interactions. The cognitive distortions are interpersonal. It is significantly faster than traditional insight-oriented couples therapy and the outcome data backs that up.
Where Cognitive Behavioral Conjoint Therapy actually fits
CBCT is not the same as Emotionally Focused Therapy or the Gottman Method. EFT runs on attachment theory and aims for emotional accessibility. Gottman is heavily assessment-driven with communication skills training. CBCT runs on Beckian cognitive model principles adapted for dyads. You are looking at automatic thoughts, intermediate beliefs, and core schemas as they manifest in conflict between two people. The main protocols people use are from the work of Robert Leahy, Deborah Furman, and Susan Johnson's earlier CBT-informed protocols. Leahy's approach in particular is quite structured. You identify the conflict sequence, map the thoughts that drive each partner's reaction, and then systematically test those thoughts against evidence while both people watch. Here is the practical setup. You need a whiteboard or large paper. Both chairs facing you slightly angled toward each other. A timer if you are tracking thought records. That is it. Most protocols call for 12 to 20 sessions. Research typically shows meaningful change in the 8 to 12 session range for moderate cases. Severe comorbid depression or untreated substance use in either partner drops that effectiveness noticeably.
Running the Session
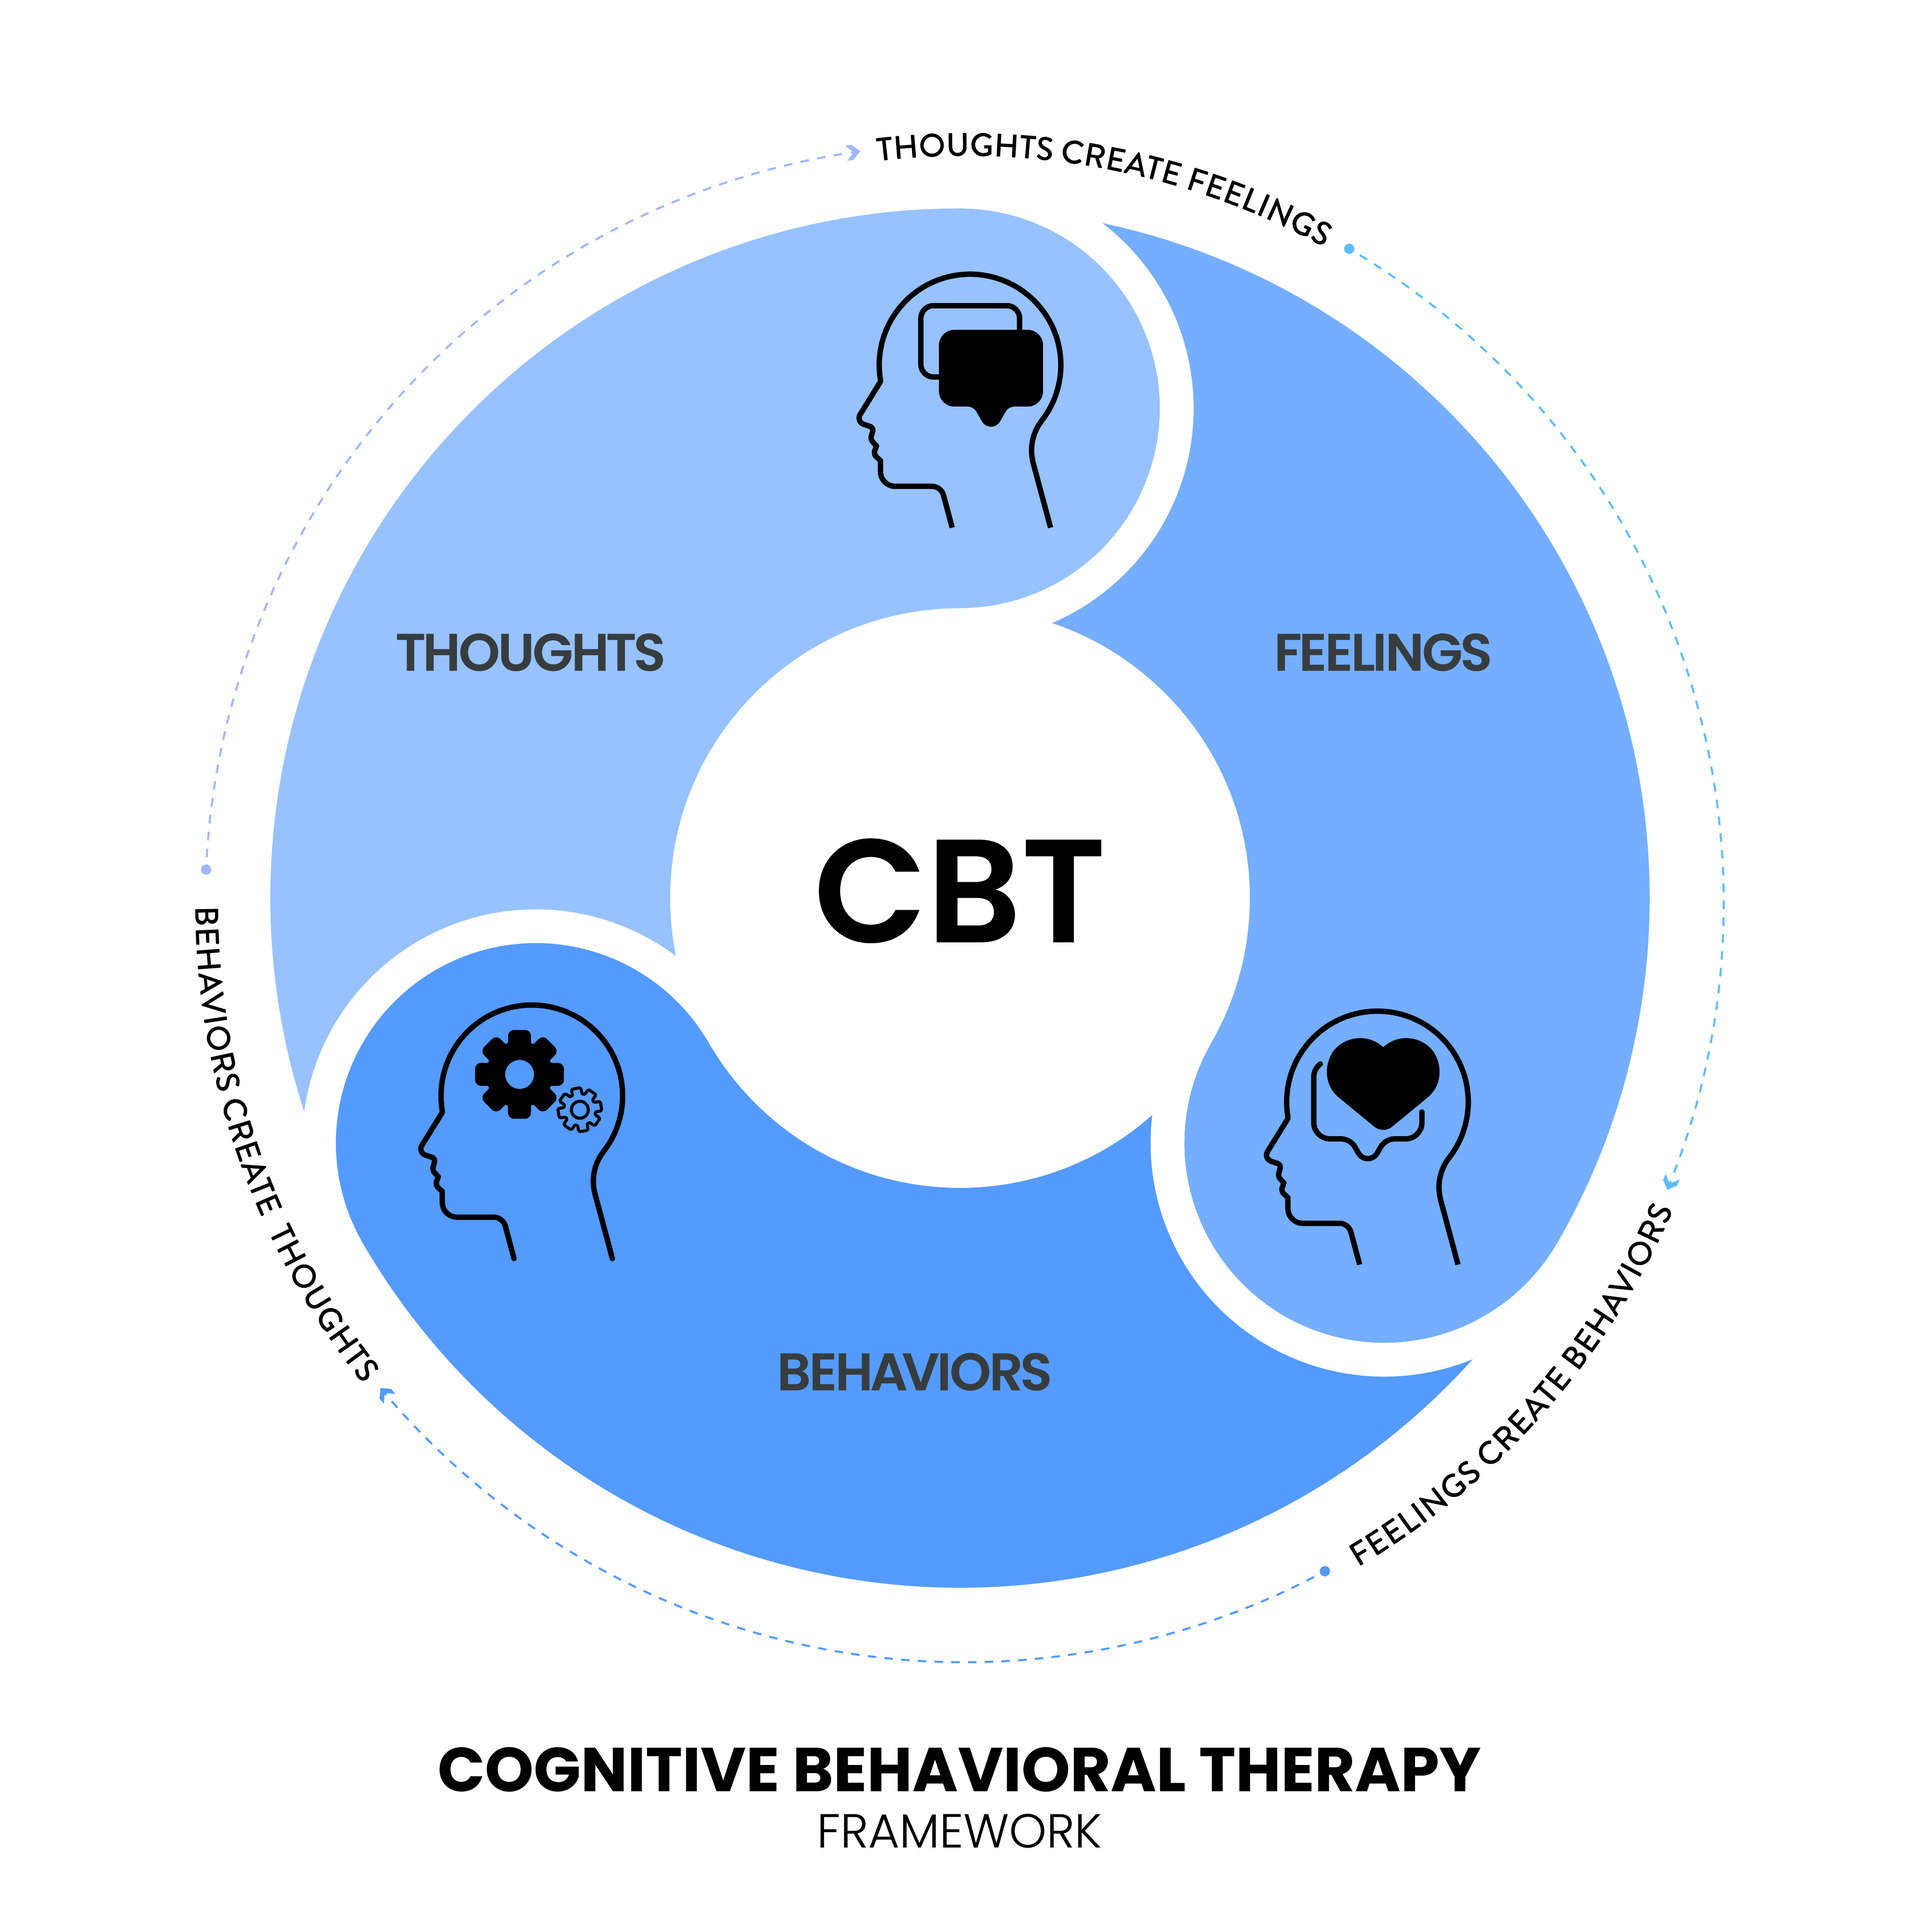
Start with a joint assessment. Not separate assessments. Do a behavioral chain analysis together. Pick one recent argument. Have them reconstruct it minute by minute. This is where most therapists skip ahead too fast. The chain reveals the triggers, the automatic thoughts, the emotional responses, and the behavioral outputs for each person. Map the interaction cycle. Partner A does X, which Partner B interprets as Y, which leads to Partner B's response Z, which Partner A experiences as W. Write it on the board. This visualization does more work than three hours of empathic reflection. They can literally see the loop. Then move to cognitive restructuring. But here is the thing most beginners get wrong. You do not restructure one person's thoughts and then the other's. You restructure the transaction. You ask the couple to examine whether the interpretation of the partner's behavior is supported by evidence, whether there are alternative interpretations, and whether the belief is helping or hurting the relationship. The standard Socratic questioning works, but you apply it to the dyadic level.
Get the Full Details

Behavioral experiments come next. Assign tasks that test the dysfunctional assumptions. If one partner believes "If I ask for time together he will see me as needy and pull away," the experiment is to ask directly and observe what actually happens. You debrief in the next session with both people present.
A specific edge case that broke my initial protocol
I had a couple where the wife had significant OCD symptoms and the husband had avoidant attachment traits. The standard CBCT cycle analysis kept collapsing because her rituals were not conflict responses. They were compulsion-driven. His withdrawal was not a mechanism in the usual sense. It was genuine overwhelm that no amount of cognitive reframing would touch in the moment. The workaround was to run a modified protocol. I kept the conjoint sessions for the relational patterns but added a separate exposure and response prevention framework for her OCD components and treated his avoidant patterns with a different behavioral assignment structure. The conjoint work on their interaction cycle still happened. It just was not the entirety of the treatment. Most textbook CBCT presentations do not cover this combination well. If you are working with OCD or significant personality pathology, you need to integrate before you try to run a pure CBCT protocol.
Common Pitfalls
The biggest mistake is treating CBCT like individual CBT with two people in the room. The dyadic element is not decorative. When you restructure a thought, the partner's reaction to that restructuring is data. If your intervention makes the other person defensive, you have missed something about the relational context. Watch the second person's face constantly. Another pitfall is moving too quickly to solutions. Couples come in wanting relief. They want you to tell them what to do. Resisting that impulse is hard but necessary. Cognitive restructuring takes time. Without it, behavioral contracts become manipulative. Communication skills become performance. The underlying schemas keep driving the bus. There is also a structural limitation that is worth stating bluntly. CBCT requires both partners to have sufficient cognitive capacity and emotional regulation to engage in metacognition during conflict. If one partner is in acute crisis, actively abusing substances, or has significant intellectual disability, conjoint CBT is not the right starting point. Individual work or stabilization first. Forcing conjoint CBT in those scenarios tends to increase dropout and sometimes worsens the relationship climate.

Materials and Resources
Leahy's "Cognitive Therapy Techniques: A Practitioner's Guide" has the most detailed conjoint CBT chapter available. Furman and Rhoades published a manualized protocol in the Journal of Marital and Family Therapy. For self-assessment tools, the Dyadic Adjustment Scale and the Cognitive Emotion Regulation Questionnaire give you baseline measures before you start. There are no official download links for proprietary CBCT manuals since those are published through APA and other academic publishers. You can find free worksheets based on the general CBT model from the Beck Institute website that you adapt for dyadic work. Thought records, behavioral activation schedules, and schema diagrams all transfer reasonably well with minor modifications for two-person dynamics. The approach is not a cure-all. It works best for couples with moderate distress, good enough insight, and no active crisis. The couples who benefit most are the ones who are frustrated but still invested. The ones who are already disengaged or where there is ongoing infidelity tend to need other modalities first. Knowing which couples are good candidates matters more than knowing the technique itself.