What Actually Happens When You Try CBT for Memory Problems
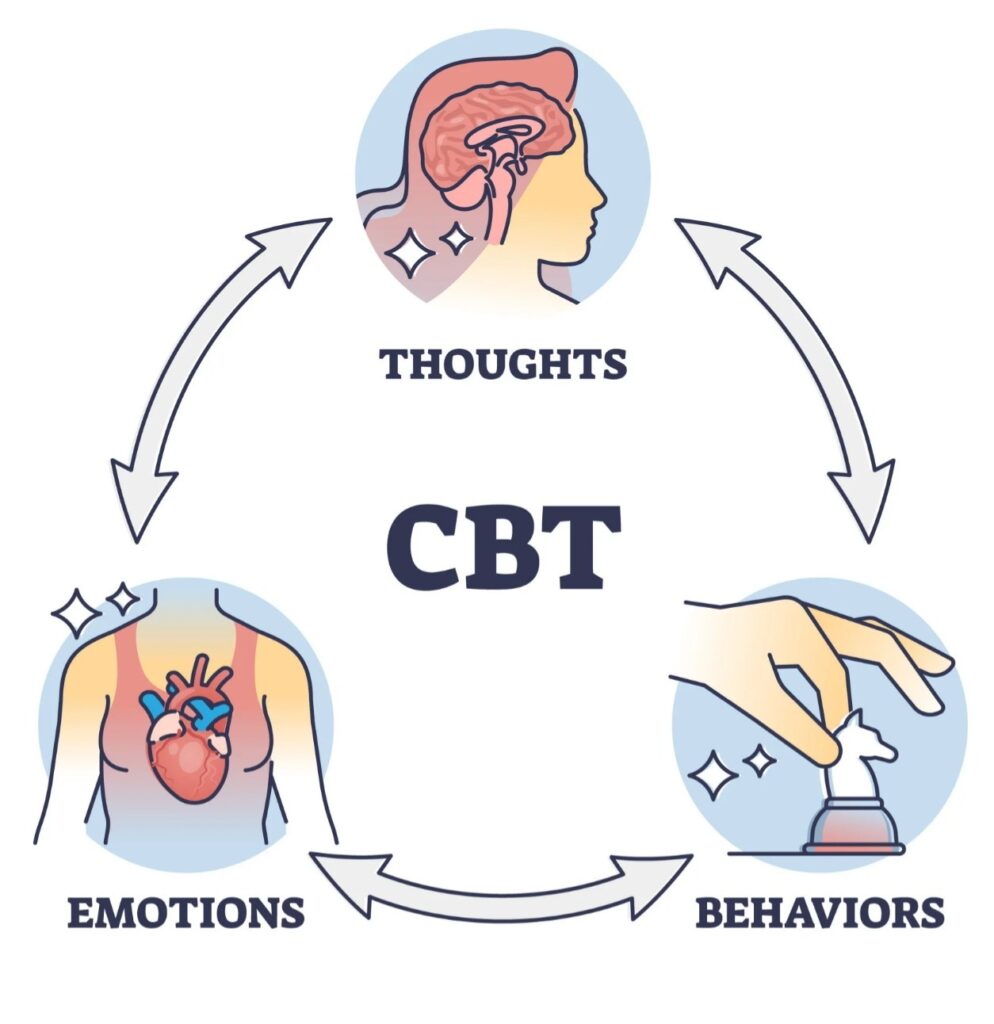
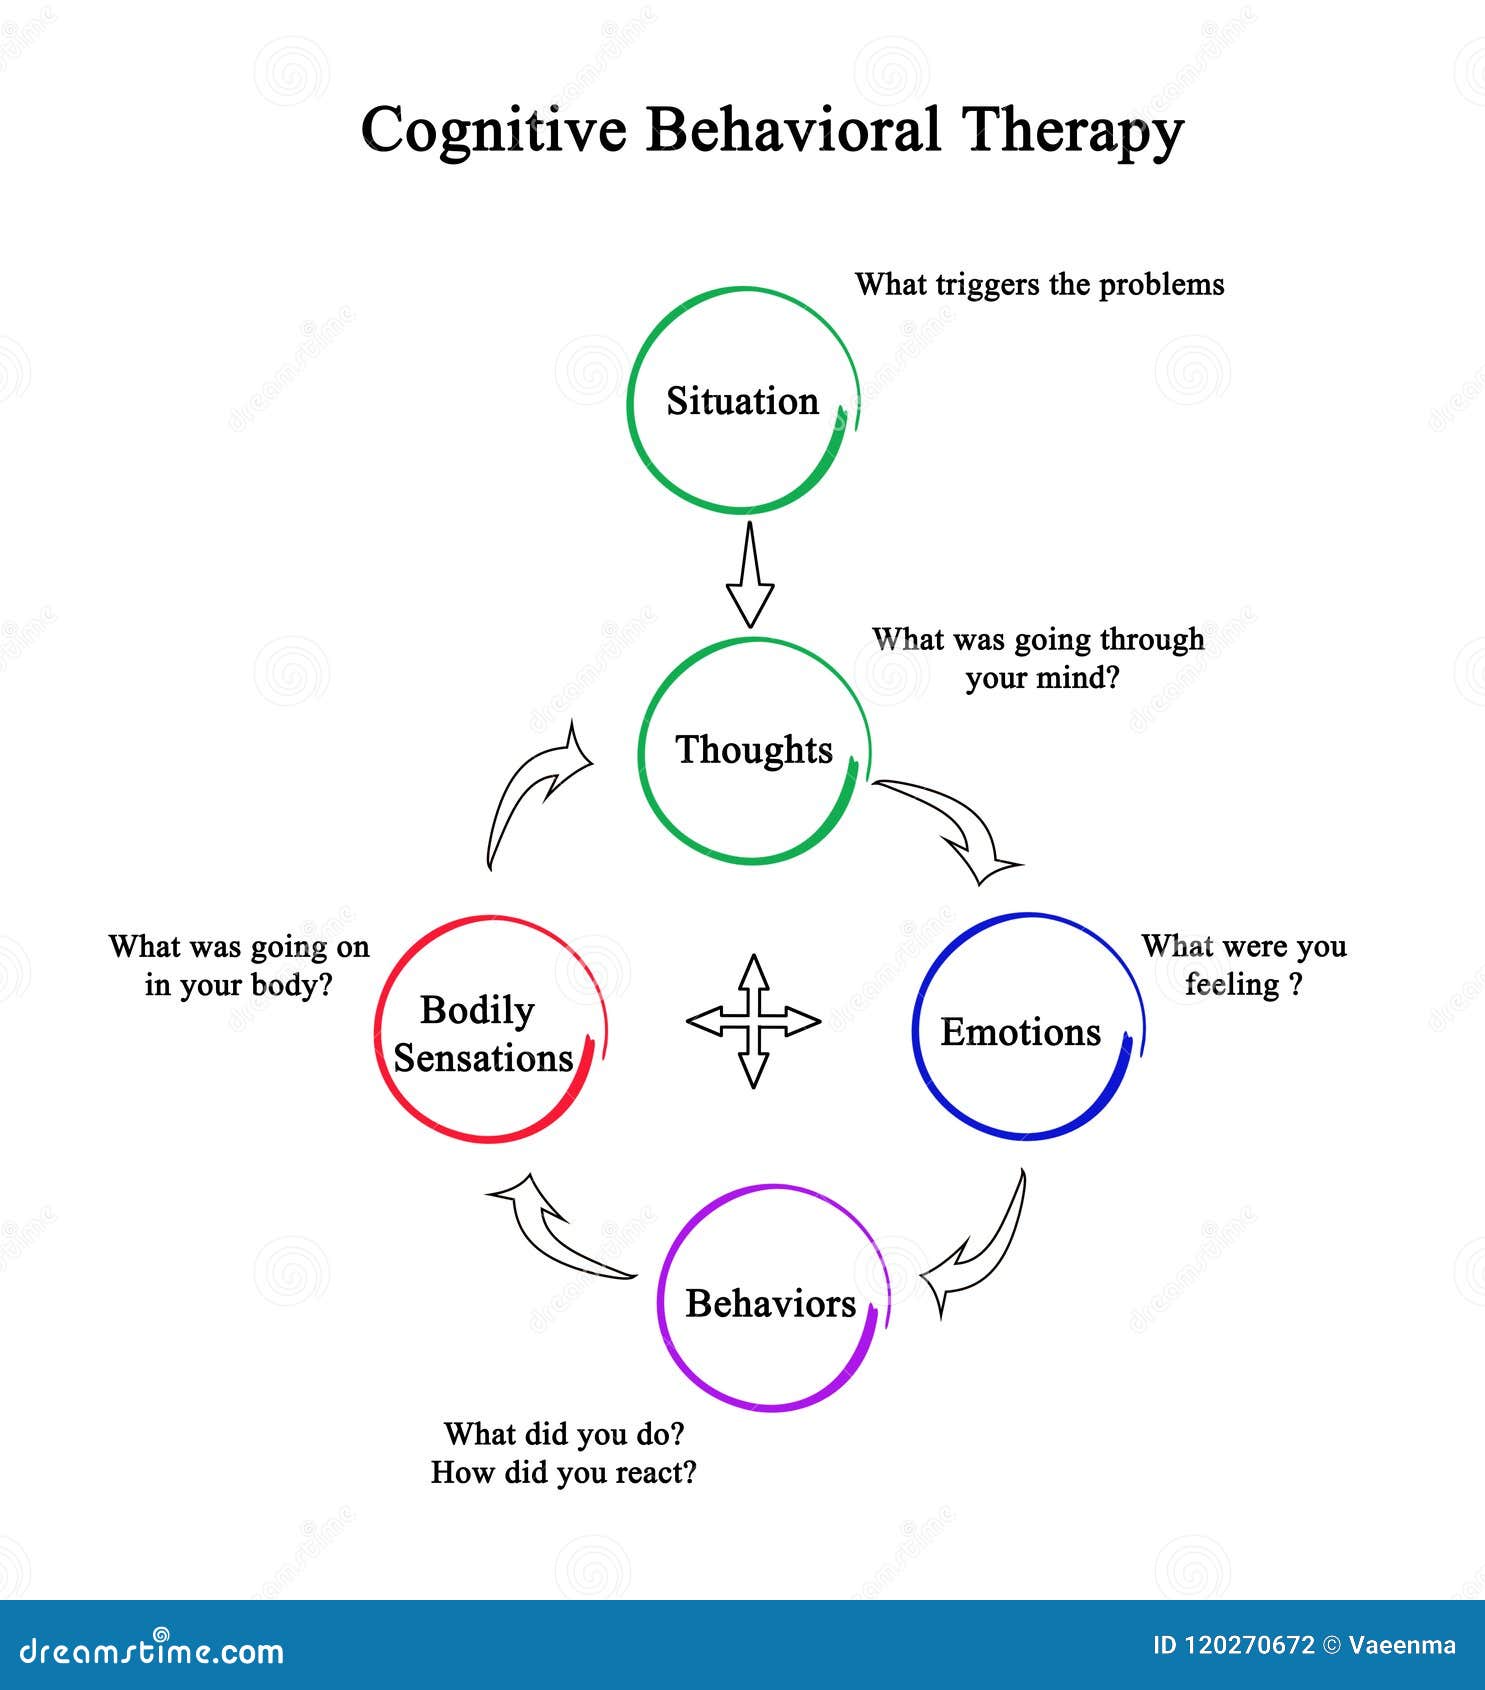
I spent about three years working with clients who had mild cognitive impairment and kept coming back with the same complaint: they forgot things, got anxious about forgetting, and then the anxiety made the forgetting worse. It is a real loop. The therapy is not about rebuilding the hippocampus. It is about interrupting the spiral that turns a minor forgetful moment into a panic episode that shuts down working memory for the rest of the day. The core mechanism is straightforward enough that people sometimes think I am selling them something. You identify the automatic thought that fires when you cannot remember a name or where you put your keys, you test whether that thought is actually supported by evidence, and you replace it with a more accurate interpretation that does not trigger the stress response. The stress response is the thing that wrecks your recall. Cortisol floods the prefrontal cortex. That is basic neurobiology, not speculation. The protocol usually runs like this. A client keeps a brief log of every time they catch themselves thinking something like "I am losing my mind" after a memory slip. You go through those logs together and look for patterns. Is it always when they are tired? Always after checking email? Always when they feel watched by someone else? The pattern matters more than the individual incidents. One client, for example, realized her catastrophic thoughts about her memory only appeared in the evening after she had been suppressing worries about her work performance all day. The memory issue was secondary. The suppression was the real cost.
Behavioral experiments are the other half. You do not just talk about the thoughts. You have the person do something that tests them. If someone believes that worrying about forgetting will somehow make them remember better, you have them split time between a worried state and a neutral state while doing a memory task. The results almost always contradict the fear. This is where people get surprised. They genuinely do not expect the data to go against their assumption. I ran into a specific edge-case that took me a while to figure out. A client in his late sixties had vascular risk factors and mild episodic memory complaints. His anxiety was high, sure, but his memory lapses were not purely anxiety-driven. The worry made things worse, but treating the worry alone did not move the needle much. What finally helped was pairing the CBT work with a strict sleep schedule and a referral to a neurologist for a proper workup. The CBT was not useless. It just was not sufficient on its own for this particular person. I learned to screen for vascular and metabolic contributors before diving too deep into the cognitive restructuring. Doing that screening first saves everybody a lot of time and prevents false hope. There is a common pitfall that trips up a lot of beginners in this space. They treat memory loss as if it were entirely a product of negative thinking. It is not. Depression and anxiety absolutely impair encoding and retrieval. But structural changes from things like early-stage neurodegeneration do not care how reframed your thoughts are. You need to be honest about that boundary. If someone is making errors in familiar routines, getting lost in places they know well, or repeating questions in the span of minutes, CBT alone is the wrong first step. A medical evaluation comes first. The therapy can still help with the emotional burden after that, but you do not skip the workup.
Another nuance that people miss is the difference between compensatory strategies and cognitive restructuring. Using a planner, setting phone reminders, and establishing routines are compensatory strategies. They are useful. They are also not CBT. A therapist who only teaches you tricks to compensate without addressing the anxiety component often sees clients improve slightly on the task level but stall emotionally. The anxiety does not leave just because you stopped misplacing your glasses. It stays and finds a new target, like forgetting a conversation you had five minutes ago. The restructuring work needs to touch that too. Here is a practical way to start if you want to try this on your own before seeing anyone. You pick one type of memory lapse that happens regularly. For me, it was walking into a room and immediately forgetting why. The automatic thought was "I am becoming forgetful in a bad way." I wrote that down exactly. Then I looked for disconfirming evidence. Had I actually failed at something important because of it? No. Was I tired? Yes. Did I ever remember why when I walked back to where I started? Usually yes. The thought was not false, but it was overstated. Replacing it with "I am tired and my attention was elsewhere" changed the physiological response. I stopped spiraling. The actual recall came back faster because the interference dropped. That single technique takes about ten minutes a day if you do it consistently. It does not reverse cognitive decline. It stops the anxiety from multiplying the problem by two or three times its original size. Most people who stick with it report a noticeable reduction in the distress attached to memory slips within four to six weeks. The slips themselves may continue, but they stop dominating the day.
Get the Full Details

If you are looking for structured materials, the standard CBT workbooks on anxiety and depression contain chapters that apply directly to this. Books like Feeling Good by David Burns and Mind Over Mood by Greenberger and Padesky both have exercises for thought records and behavioral experiments that you can adapt. You do not need a special memory version. You just need to apply the same framework to memory-related thoughts instead of the usual social or performance scenarios those books often use as examples. The honest limitation is that this approach works best for subjective memory complaints driven by anxiety, depression, or stress. It is less effective for objective memory deficits from conditions like traumatic brain injury, untreated sleep apnea, thyroid dysfunction, or early dementia. In those cases, the therapy can still reduce distress, but it will not restore the lost function. You should pair it with whatever the appropriate medical treatment is rather than treating it as a standalone solution. One more thing that comes up often. People assume that doing memory exercises like puzzles or brain-training apps counts as part of this work. It does not. Those are cognitive training. CBT is about changing the thinking pattern that surrounds the memory lapse. Mixing them up in your head makes the whole process confusing. Keep the anxiety work separate from the cognitive stimulation. They can coexist, but they are different tools.