So You Want to Use CBT to Stop Panicking Before You Speak
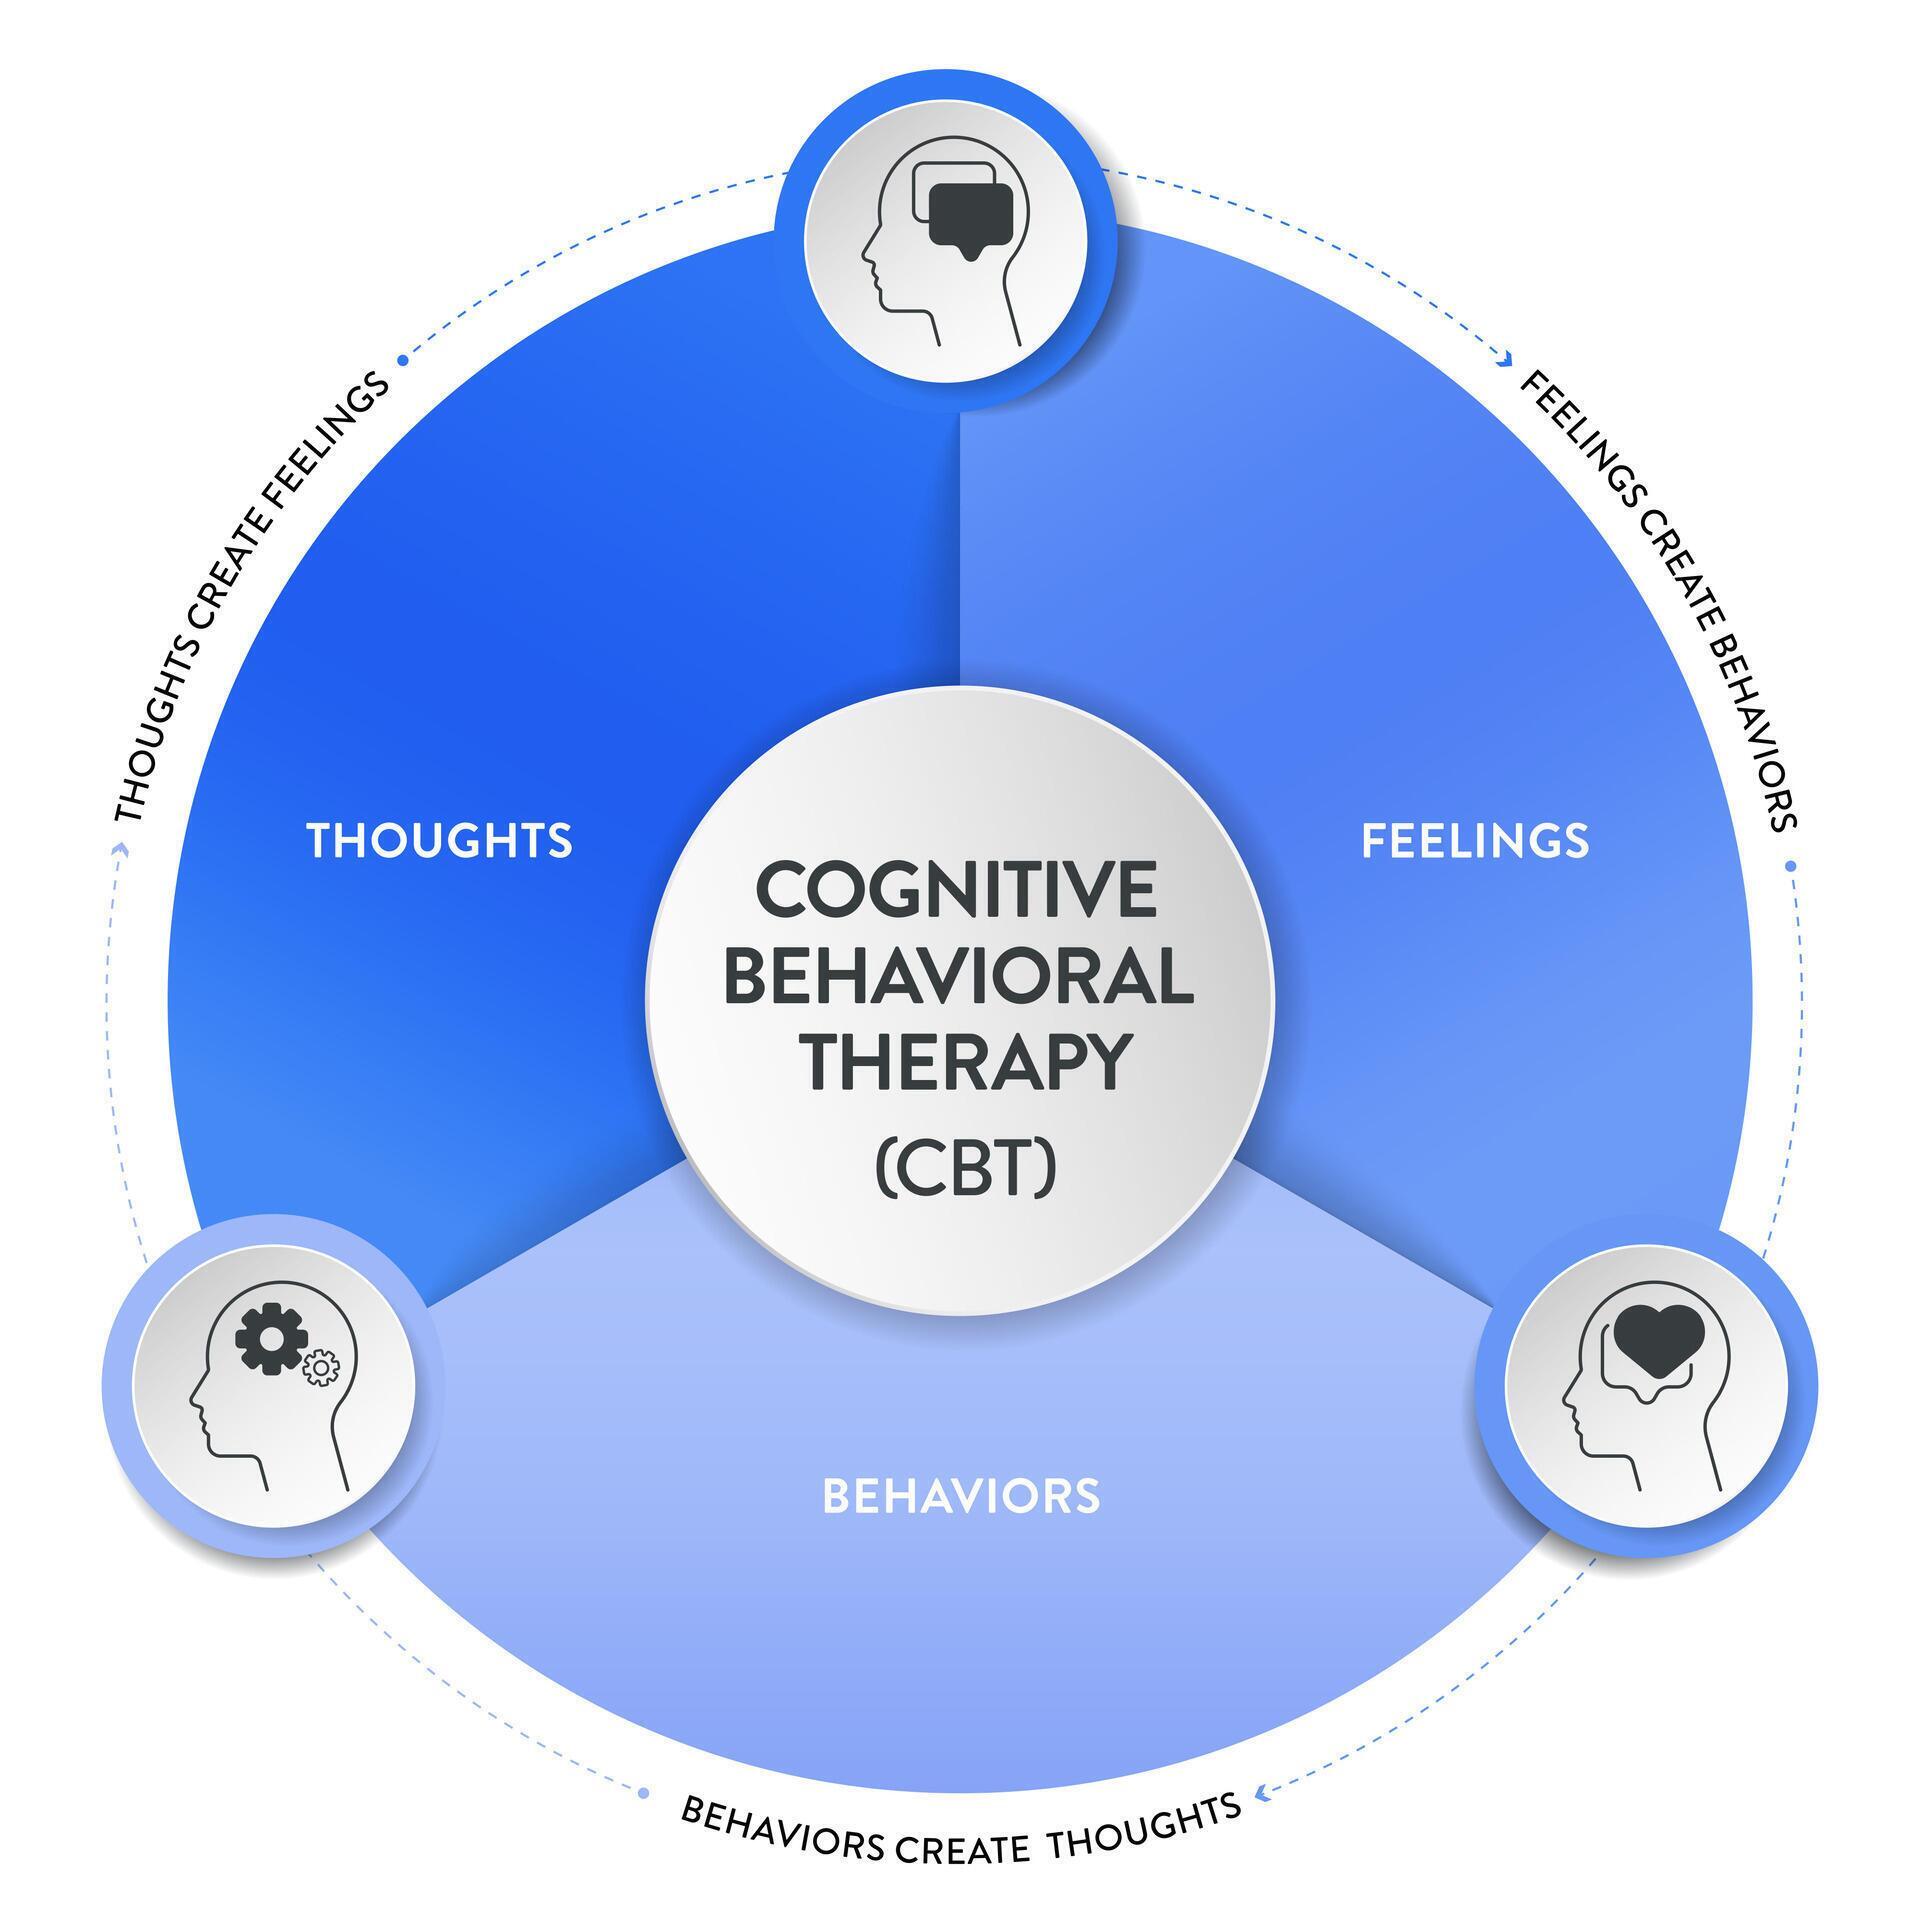
Cognitive Behavioral Therapy For Public Speaking is basically a structured way of training your brain to stop treating a meeting room like a lion cage. It works by targeting the feedback loop between what you think will happen, what your body does about it, and the evidence you collect afterward. Most people skip the middle part and just try to "think positive," which is why it never actually works for them. The core mechanism is pretty straightforward. You identify the automatic thought — usually something like "everyone is going to notice I'm shaking and they'll think I'm incompetent" — then you test it. Not by arguing with it in your head, which just loops, but by setting up a real-world behavior experiment. You say the thing you've been avoiding and you collect data on what actually happens. The anxiety drops because the prediction fails. That's the whole thing.
Cognitive Behavioral Therapy For Public Speaking
Here's the part most guides skip: the hierarchy has to be built from your own avoidance list, not a generic internet template. I had a client once who couldn't even picture himself making eye contact with one person in a group of three. He jumped straight to "present to twenty people without notes" on his exposure ladder and bailed after thirty seconds of panic. That's not a CBT problem. That's a bad exposure design problem. We spent two weeks just doing voice recordings of him saying two sentences into a phone app, then watching the playback back, before he was ready for anything face-to-face. The rule of thumb is that each step should provoke a 5 out of 10 anxiety level. If it's an 8 or above, you're moving too fast and your nervous system just learns to associate the situation with full threat response. That reinforces the very fear you're trying to dismantle. Another thing people miss is the difference between safety behaviors and actual coping skills. Nodding your head while speaking to distract yourself? Safety behavior. Having a written outline? Coping skill. Scrolling through your notes on your phone before going on stage? Safety behavior. The problem with safety behaviors is that they preserve the anxiety long-term because you never get the disconfirming evidence. Your brain says "I only survived because I had my notes open" instead of "I survived even though I was terrified." You have to systematically fade those out. I've seen people work a full twelve-week protocol and still not make progress because they never actually dropped the crutches. The behavioral part of this is where the real work lives. Cognitive restructuring — the identifying-challenging-replacing thought sequence — handles about thirty percent of the outcome. The remaining seventy comes from repeated exposure where you sit in the discomfort until your amygdala updates its threat assessment. That's called habituation. It takes roughly six to eight consecutive sessions at the same anxiety level before the reduction becomes durable. Doing it once a month does almost nothing. This isn't motivational speaking. It's neurobiology.
There's also the interoceptive exposure piece, which is uncomfortable but effective for people whose main issue is the physical symptoms themselves. You deliberately induce the sensations you're afraid of — elevated heart rate, shallow breathing, trembling hands — through exercise or controlled breathing variations, then sit with them without using any avoidance strategy. Over time, your brain stops flagging "heart racing" as "impending doom." I ran into a case last year with a corporate trainer who could speak fine to large audiences but would hyperventilate the moment someone asked an unplanned question. Turns out it wasn't the public speaking anxiety. It was a fear of losing control of his physiological state. We spent four weeks doing breath-hold drills and sprint-up-stairs exercises before we ever touched the actual Q&A scenario. Once the body fear was gone, the situational fear collapsed with it. Pretty unusual presentation, honestly. A few structural notes on how this actually looks in practice. You need a baseline measurement. Record yourself giving your typical presentation once, before any intervention, and score it on a few fixed criteria — filler word count, average sentence length, self-rated anxiety from zero to ten. Do the same at week four and week eight. Without concrete numbers you're just guessing whether anything is working. Most people improve measurably within six weeks if they're actually doing the exposure homework, not just reading about it. The downsides are worth stating plainly. CBT for public speaking requires consistent effort over several weeks. It doesn't work if you treat it like a weekend workshop. It's also not particularly effective for people whose anxiety is rooted in actual trauma around speaking — a humiliating experience in front of peers, for example. That tends to need something more along the lines of EMDR or prolonged exposure therapy, not standard cognitive restructuring. And for people with severe social anxiety disorder beyond just speaking situations, the gains from a targeted public speaking protocol tend to be narrow. You'll speak better in meetings but still avoid the coffee break afterward. That's normal. The treatment was scoped to a specific fear, not a personality overhaul.
Get the Full Details

Medication is another variable. Some people use beta-blockers like propranolol on an as-needed basis for performance-only anxiety. It blunts the physical symptoms — the shaking, the racing heart — without the cognitive dulling of benzodiazepines. It's not a substitute for the exposure work, but it can be a useful bridge while you're building the behavioral hierarchy. That said, it only masks the physiology. If you rely on it exclusively, your anxiety returns at full strength the moment you stop taking it. The exposure protocol is what actually changes the prediction error. The medication just buys you a window to do it more comfortably. If you want a structured starting point, there are publicly available CBT worksheets for public speaking anxiety from university psychology departments. The one from the Beck Institute is thorough but dense. A simpler version is the Thought Record form adapted for performance situations — it has columns for the event, the automatic thought, the emotion intensity, the evidence for and against, and a restructured thought. You fill it out after every exposure session. It takes about five minutes per entry. The tracking data from these forms is usually the clearest indicator of whether the approach is working for you or whether you need to adjust the hierarchy. I'd also recommend recording the exposures themselves, not just the formal presentations. A voice memo of you doing a three-minute monologue for your empty living room counts as exposure if you stay in it without checking your phone or muting the recording. The medium doesn't matter. The sustained proximity to the fear does. That's the active ingredient.
One more thing that tends to get overlooked: the post-event processing pattern. After you do an exposure, most anxious speakers immediately replay the whole thing in their head and catalog every mistake. This literally undoes the habituation that just occurred. The brain is re-firing the threat network retroactively. I tell people to write down three things that went neutrally or well within five minutes of finishing, and then physically close the notebook. Don't analyze. Just note and move on. It sounds trivial. It makes a measurable difference over a multi-week protocol. The whole approach is mechanical. It's not inspiring. It's also one of the most reliably effective interventions for performance anxiety when you actually stick with the exposure component and don't shortcut it. The people who bounce off it are usually the ones who want the cognitive restructuring to do the heavy lifting. It won't. The behavioral part does.